The anti-Jo-1 antibody test detects autoantibodies against histidyl-transfer RNA synthetase, an enzyme involved in protein production. Anti-Jo-1 is the most common antisynthetase antibody and strongly supports antisynthetase syndrome when it appears with inflammatory muscle disease, interstitial lung disease, inflammatory arthritis, mechanic’s hands, Raynaud phenomenon, or unexplained fever. The syndrome is variable: one person may have prominent weakness, while another first presents to a lung clinic with cough or breathlessness and little obvious muscle disease.
A positive result is not enough to diagnose the syndrome without compatible clinical evidence. Commercial myositis panels, especially line blots, can produce weak or discordant results. Conversely, a negative anti-Jo-1 test does not exclude antisynthetase syndrome because other synthetase antibodies include PL-7, PL-12, EJ, OJ, KS, Zo, and Ha. Lung disease is a central concern and may be present before muscle enzymes rise. Interpretation therefore combines the antibody with strength examination, creatine kinase, pulmonary function tests, high-resolution chest CT, joint and skin findings, and the performance characteristics of the assay.
- Anti-Jo-1 is a myositis-specific antibody and the most frequently detected marker of antisynthetase syndrome.
- Interstitial lung disease may be the first or dominant manifestation, even without obvious muscle weakness.
- A strong result that matches the phenotype is much more credible than an isolated weak line-blot band.
- The antibody level itself does not replace lung-function trends, CT findings, muscle strength, or creatine kinase.
- New shortness of breath, low oxygen, swallowing difficulty, or rapidly progressive weakness requires prompt assessment.
Table of Contents
- Jo-1 and the Antisynthetase Syndrome Concept
- Ways Anti-Jo-1 Disease Can Present
- Test Methods and Confidence in the Result
- Evaluating Interstitial Lung Disease
- Muscle, Joint, and Skin Workup
- Treatment and Monitoring
- Questions and Next Steps After Testing
Jo-1 and the Antisynthetase Syndrome Concept
Aminoacyl-transfer RNA synthetases attach specific amino acids to transfer RNA during protein synthesis. Jo-1 is histidyl-tRNA synthetase. In antisynthetase syndrome, the immune system targets one of these enzymes and a recognizable group of inflammatory manifestations develops.
Anti-Jo-1 is the best-known antibody in this family and remains an important bridge between rheumatology, pulmonology, neurology, and laboratory medicine worldwide. It is more common than the non-Jo-1 antisynthetase antibodies and is often associated with a “complete” phenotype that includes myositis, arthritis, and lung disease. However, patients rarely develop every feature at once. The syndrome can unfold over months or years, so an initial label of isolated interstitial lung disease, rheumatoid-like arthritis, or undifferentiated myositis may later change as additional clinical features become visible during longitudinal specialist follow-up.
The antibody is called myositis-specific because it is strongly linked to idiopathic inflammatory myopathy and related syndromes. It is not the same as ANA, although some patients have a cytoplasmic staining pattern on indirect immunofluorescence. A standard ANA report may be negative because many laboratories focus on nuclear staining. That does not rule out anti-Jo-1 disease.
Proposed diagnostic criteria generally require an antisynthetase antibody plus one or more characteristic manifestations. There is no single universally accepted classification system, and clinical judgment remains important. A person with anti-Jo-1, typical interstitial lung disease, and inflammatory arthritis may reasonably have antisynthetase syndrome even before clear muscle weakness appears.
Anti-Ro52 frequently coexists with anti-Jo-1. In some cohorts, this combination has been associated with more severe lung disease, but it is not deterministic. Other antibodies and the overall phenotype can refine risk, while direct organ testing remains more important than serology alone.
Anti-Jo-1 levels may change with disease activity in some patients, but research has not established a universally useful treatment target. The antibody commonly remains detectable during improvement. Repeated measurement is secondary to clinical and physiological monitoring.
Ways Anti-Jo-1 Disease Can Present
The central manifestations are interstitial lung disease, inflammatory myopathy, and inflammatory arthritis. Additional clues include mechanic’s hands, Raynaud phenomenon, and fever. Their order and severity vary.
Lung-first disease
A dry cough, breathlessness on exertion, reduced oxygen saturation, or an abnormal CT may precede muscle symptoms. Some patients initially appear to have idiopathic interstitial pneumonia. Asking about subtle hand changes, episodic finger color change, morning stiffness, and difficulty rising from a chair can reveal a systemic pattern.
Muscle-first disease
Myositis usually causes symmetrical proximal weakness: trouble climbing stairs, standing from a low seat, lifting the arms, washing hair, or holding the neck upright. Muscle aching may occur, but pain without objective weakness is less specific. Creatine kinase can be markedly elevated, modestly elevated, or occasionally normal when muscle disease is mild or treated.
Arthritis-first disease
Inflammatory arthritis can resemble rheumatoid arthritis, with pain, stiffness, and swelling in the small joints of the hands. It may be nonerosive, but erosive disease can occur. Rheumatoid factor or anti-CCP antibodies may be present in some patients and can influence the joint phenotype.
Skin and vascular clues
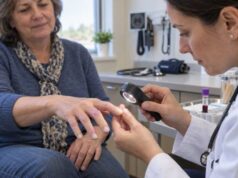
Mechanic’s hands are rough, cracked, thickened skin along the sides of the fingers and palms. They are suggestive but not exclusive to antisynthetase syndrome. Raynaud phenomenon causes episodic white, blue, or red color changes in response to cold or stress. Dermatomyositis-type rashes can coexist, although they are not required.
| Dominant presentation | Possible clues | Common diagnostic pitfall |
|---|---|---|
| Interstitial lung disease | Dry cough, exertional breathlessness, restrictive PFTs, NSIP or organizing pneumonia pattern | Assuming the lung disease is idiopathic because weakness is absent |
| Myositis | Proximal weakness, high CK, muscle edema on MRI | Attributing elevated AST and ALT only to liver disease |
| Inflammatory arthritis | Morning stiffness and swollen hand joints | Diagnosing rheumatoid arthritis without evaluating lung and muscle features |
| Incomplete or evolving syndrome | One major feature plus mechanic’s hands, Raynaud phenomenon, or fever | Expecting all manifestations to appear simultaneously |
The phenotype can change, so follow-up should not stop after a single normal CK or chest study. New cough, weakness, or joint inflammation may represent evolution of the same syndrome rather than an unrelated condition. Because manifestations can appear asynchronously, patients and clinicians benefit from reviewing all organ systems at follow-up instead of limiting attention to the problem that was most prominent at diagnosis.
Test Methods and Confidence in the Result
Anti-Jo-1 can be measured by enzyme immunoassay, chemiluminescence, multiplex bead assay, line immunoblot, or immunoprecipitation. Immunoprecipitation is a specialist reference technique but is not routinely available. Commercial platforms vary in antigen source, cutoff, and sensitivity.
Anti-Jo-1 generally performs better on commercial panels than many rare antisynthetase antibodies, but false positives and false negatives still occur. A strong positive across two methods with a compatible phenotype is highly persuasive. An isolated weak band among several weak myositis antibodies is less trustworthy.
Line-blot intensity matters. Studies have found that strong results and high pretest probability are more likely to represent true disease. Multiple simultaneous myositis-specific antibody bands may reflect assay noise because these antibodies are usually mutually exclusive. Laboratories and clinicians should resist treating every printed band as a separate diagnosis.
| Test pattern | Interpretation | Useful response |
|---|---|---|
| Strong positive with ILD, myositis, or arthritis | Strong support for antisynthetase syndrome | Complete multisystem evaluation |
| Weak positive with no compatible features | Possible nonspecific line-blot signal | Review method and consider confirmation |
| Negative Jo-1 with a convincing phenotype | Another synthetase antibody or seronegative myositis is possible | Use an expanded panel and clinical workup |
| Positive after treatment response | Antibody may persist despite control | Track organs and function rather than seronegativity |
A focused myositis autoantibody panel can identify other synthetases and markers such as MDA5, Mi-2, NXP2, TIF1-gamma, SRP, and HMGCR. The panel should be chosen according to the suspected phenotype because content differs among laboratories.
A negative result does not exclude inflammatory myositis or connective tissue disease-associated ILD. It means only that anti-Jo-1 was not detected by that method. If suspicion remains high, specialists may repeat testing, use a different platform, or prioritize imaging, physiology, and biopsy evidence.
Pre-analytical and reporting details can matter. Hemolysis, sample handling, immunosuppressive treatment, and laboratory-specific reflex rules may influence what is tested or reported. Some panels list only a qualitative band, whereas focused assays provide a numerical result. The numerical value should not be interpreted as a universal severity scale. When results are discordant, obtaining the original report—including method, units, cutoff, and band intensity—allows a specialist laboratory to advise whether confirmation is worthwhile.
Evaluating Interstitial Lung Disease
Interstitial lung disease is a major cause of illness in antisynthetase syndrome and may determine prognosis. Screening is appropriate even when respiratory symptoms are mild because patients can compensate for early loss of lung function.
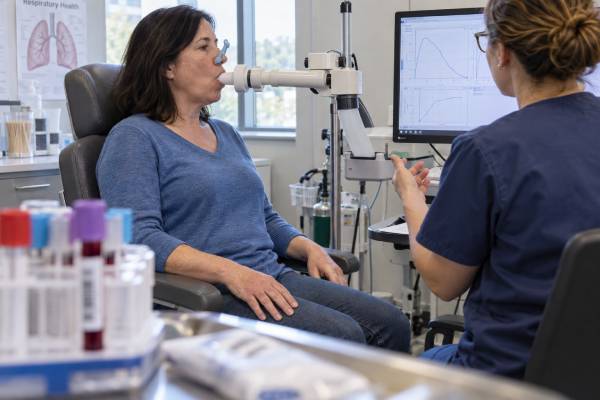
Pulmonary function tests usually include forced vital capacity, total lung capacity, and diffusing capacity for carbon monoxide. A restrictive pattern or reduced diffusion can support ILD, but normal results do not exclude subtle disease. Trends using the same laboratory and technique are more informative than a single measurement.
High-resolution CT is the key imaging test. Common patterns include nonspecific interstitial pneumonia, organizing pneumonia, or a mixture of the two. Ground-glass opacity, reticulation, consolidation, traction bronchiectasis, and volume loss may appear. A usual interstitial pneumonia pattern is possible but less typical.
The CT pattern does not identify anti-Jo-1 by itself. Infection, aspiration, drug toxicity, pulmonary edema, and other connective tissue diseases can produce overlapping findings. Multidisciplinary review by pulmonology, radiology, and rheumatology can improve classification.
The anti-Ro52 antibody may add context when present, but it does not replace PFTs or CT. Oxygen saturation at rest and with exertion, symptoms, and functional capacity should also be recorded.
Rapidly progressive ILD is less strongly associated with anti-Jo-1 than with anti-MDA5, but it can occur. Warning signs include breathlessness worsening over days or weeks, falling oxygen saturation, new diffuse CT abnormalities, or declining lung function. Infection must be evaluated urgently because immunosuppression and lung disease both increase risk.
Monitoring frequency depends on severity and recent change. ACR/CHEST guidance supports PFTs and HRCT for screening and monitoring systemic autoimmune rheumatic disease-associated ILD, with the interval individualized. Routine chest radiography is less sensitive and should not be relied on to exclude progression.
Lung biopsy is rarely required when the clinical, serologic, HRCT, and physiological picture is coherent. It may be considered when the diagnosis remains unclear or an alternative such as malignancy or infection must be excluded.
Muscle, Joint, and Skin Workup
Creatine kinase is the principal blood marker of muscle injury, but aldolase can be helpful when CK is normal. AST, ALT, and LDH may rise from muscle. Troponin interpretation requires care because some assays can reflect skeletal muscle; cardiac symptoms may require ECG, echocardiography, or cardiac MRI.
Strength examination should assess neck flexion, shoulder abduction, hip flexion, chair rise, gait, and swallowing. Electromyography can show an irritable myopathy. MRI can identify edema and guide biopsy. Muscle biopsy may demonstrate perifascicular necrosis, inflammation, or other features, but it is not always necessary when serology and phenotype are classic.
Dysphagia can result from pharyngeal or esophageal muscle involvement and raises aspiration risk. Cough during meals, a wet voice, weight loss, or recurrent pneumonia should prompt swallowing assessment. Respiratory muscle weakness should be considered when breathlessness is out of proportion to CT findings.
Joint evaluation distinguishes inflammatory swelling from mechanical pain. Ultrasound can detect synovitis when examination is uncertain. Anti-CCP positivity may identify a more rheumatoid-like, potentially erosive pattern, although the patient can still have antisynthetase syndrome.
Skin examination includes the palms and sides of the fingers for mechanic’s hands, nailfolds for capillary changes, and sun-exposed areas for dermatomyositis rashes. The absence of rash does not weaken a classic lung-muscle-arthritis presentation.
Other tests may include complete blood count, metabolic panel, urinalysis, inflammatory markers, thyroid testing, infection screening, and age-appropriate cancer screening. Cancer risk is not as strongly linked to anti-Jo-1 as to some dermatomyositis antibodies, but standard screening and symptom-guided evaluation remain appropriate.
Treatment and Monitoring
Treatment is directed at the organs involved and the speed of progression. Corticosteroids are often used initially, but steroid monotherapy commonly leads to relapse or excessive toxicity. Mycophenolate, azathioprine, tacrolimus, rituximab, cyclophosphamide, intravenous immunoglobulin, and other agents may be selected according to lung severity, muscle disease, comorbidities, pregnancy plans, and prior response.
For ILD, current ACR/CHEST guidance supports several immunosuppressive options as first-line therapy and discourages some drugs in particular settings. Rapid progression may require hospital care and combination treatment. No single regimen is best for every anti-Jo-1 patient, and evidence comes largely from observational studies rather than large antibody-specific trials.
Muscle recovery is tracked with strength, daily function, and CK. Lung response is tracked with symptoms, PFTs, oxygen needs, and imaging when indicated. Arthritis and skin findings may improve at a different pace. A treatment that controls myositis may not fully control ILD, so organ-specific monitoring is essential.
Rehabilitation should be gradual and coordinated with disease control. Physical therapy can preserve mobility and rebuild strength; pulmonary rehabilitation may improve endurance. Vaccination, infection prevention, bone health, and monitoring for medication toxicity are integral parts of care.
Relapse can occur during tapering. A rising CK, worsening cough, reduced FVC, or renewed inflammatory arthritis deserves assessment, but anti-Jo-1 titer alone should not drive escalation. Infection, deconditioning, steroid myopathy, and irreversible fibrosis can mimic active disease.
Monitoring should establish a personal baseline before treatment whenever it is safe to do so. Recording FVC, DLCO, oxygen saturation, CK, manual strength, chair-rise ability, swallowing status, and joint findings makes later change easier to recognize. Stable fibrosis may leave persistent CT abnormalities even when inflammation is controlled, so radiology should be interpreted together with physiology and symptoms rather than as a binary normal-or-abnormal result.
Questions and Next Steps After Testing
The blood draw usually needs no fasting. Before testing, document medications, recent infection, intense exercise, and symptom timing. Exercise can transiently raise CK, while corticosteroids can reduce inflammation and alter the presentation.
After a positive anti-Jo-1 result, ask:
- Was the result weak or strong, and which assay was used?
- Does the antibody fit my lung, muscle, joint, or skin findings?
- Do I need baseline high-resolution CT and full pulmonary function testing?
- Are CK, aldolase, strength, swallowing, and oxygen levels normal?
- Was anti-Ro52 or another myositis antibody also detected, and is confirmation needed?
- Which organ will determine treatment and monitoring frequency?
A normal CK should not delay lung evaluation in a breathless anti-Jo-1-positive patient. Likewise, a normal CT at one point does not guarantee that ILD will never develop. Follow-up should be proportionate to symptoms, initial findings, and specialist judgment.
Seek urgent care for rapidly worsening shortness of breath, low oxygen, chest pain, coughing blood, inability to swallow safely, choking, severe weakness, or inability to stand. These symptoms require direct assessment rather than waiting for repeat antibody testing.
References
- A Comparison of Line Blots, Enzyme-linked Immunosorbent Assays and RNA-immunoprecipitation in the Detection of Myositis-specific Antibodies in Patients with Idiopathic Inflammatory Myopathy 2022
- Diagnosis and Management of Myositis-Associated Lung Disease 2023 (Review)
- A Review of Antisynthetase Syndrome-Associated Interstitial Lung Disease 2024 (Review)
- 2023 American College of Rheumatology (ACR)/American College of Chest Physicians (CHEST) Guideline for the Screening and Monitoring of Interstitial Lung Disease in People with Systemic Autoimmune Rheumatic Diseases 2024 (Guideline)
- 2023 American College of Rheumatology (ACR)/American College of Chest Physicians (CHEST) Guideline for the Treatment of Interstitial Lung Disease in People with Systemic Autoimmune Rheumatic Diseases 2024 (Guideline)
- Clinical and prognostic associations of anti-Jo-1 antibody levels in patients with antisynthetase syndrome 2024
Disclaimer
This article provides general education and does not diagnose antisynthetase syndrome, myositis, or interstitial lung disease. Anti-Jo-1 results must be interpreted by qualified clinicians with the assay method, symptoms, examination, muscle enzymes, lung function, and imaging. Rapid respiratory decline, swallowing problems, low oxygen, or severe weakness requires urgent medical care.