A positive anti-TIF1-gamma antibody result can carry two different messages at once. First, it may support a diagnosis within the dermatomyositis spectrum, especially when distinctive skin findings are present. Second, in adults with dermatomyositis, it identifies a group with a higher probability of an associated cancer than dermatomyositis patients without this antibody. Neither message is complete without clinical context.
Anti-TIF1-gamma is not a cancer test, tumor marker, or proof that malignancy exists. It also does not diagnose dermatomyositis by itself. The result must be interpreted alongside age at disease onset, rash pattern, muscle strength, swallowing symptoms, muscle enzymes, imaging or biopsy findings, and other myositis antibodies. When adult-onset dermatomyositis is confirmed, the antibody can change the urgency and intensity of cancer screening. In children, by contrast, anti-TIF1-gamma is associated with juvenile dermatomyositis but not with the same established malignancy signal seen in adults.
- Anti-TIF1-gamma is a myositis-specific autoantibody most strongly associated with dermatomyositis.
- Adults with anti-TIF1-gamma-positive dermatomyositis need individualized, risk-based cancer screening.
- A positive antibody does not mean cancer has been found, and a negative antibody does not remove all cancer risk.
- Dermatomyositis may affect skin with little or no measurable muscle weakness.
- Assay choice matters because line blot, ELISA, and immunoprecipitation can produce different results.
Table of Contents
- The protein and the antibody
- The dermatomyositis phenotype
- What the cancer association really means
- How cancer screening is planned
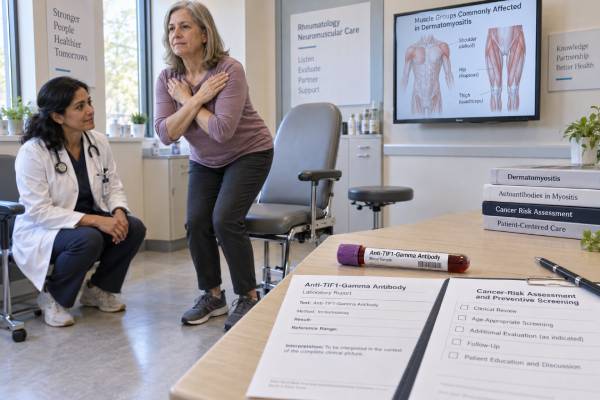
- Reading the laboratory result
- Diagnosis, treatment, and follow-up
- Practical questions after testing
The protein and the antibody
TIF1-gamma stands for transcription intermediary factor 1 gamma. The protein is also called TRIM33 and belongs to a family of proteins involved in transcriptional regulation, cell differentiation, DNA-damage responses, and tumor biology. Anti-TIF1-gamma antibodies are immune proteins directed against this intracellular target.
The antibody is classified as a myositis-specific autoantibody because it is found predominantly in idiopathic inflammatory myopathies and is particularly linked with dermatomyositis. It may be reported as anti-TIF1-γ, anti-p155/140, or anti-TRIM33. The older “p155/140” name reflects proteins recognized by patient serum on laboratory testing.
Dermatomyositis is not simply “muscle inflammation with a rash.” It is a heterogeneous autoimmune disease with characteristic cutaneous features and variable muscle, swallowing, lung, joint, and systemic involvement. Myositis-specific antibodies help divide this broad diagnosis into clinically useful phenotypes. An expanded myositis antibody panel may include anti-TIF1-gamma alongside anti-Mi-2, anti-MDA5, anti-NXP2, anti-SAE, antisynthetase antibodies, anti-SRP, and anti-HMGCR.
Anti-TIF1-gamma is best viewed as a phenotype marker. It can increase confidence that a compatible rash belongs to dermatomyositis, help explain disease with little muscle involvement, and alert the care team to malignancy risk in an adult. It does not show where a cancer might be, whether a tumor is present today, or which treatment will control the autoimmune disease.
The biological link between anti-TIF1-gamma dermatomyositis and cancer is still being studied. One leading model is that altered or overexpressed proteins in a tumor may trigger an immune response that cross-reacts with skin and muscle. Genetic changes in TIF1-related pathways and the development of additional antibodies may modify the risk. This is plausible biology, not a simple one-antibody/one-tumor mechanism.
The dermatomyositis phenotype
Anti-TIF1-gamma-positive dermatomyositis often has prominent skin disease. Recognizing that pattern is important because a patient can have severe cutaneous disease while creatine kinase is only mildly elevated or normal.
Features that may prompt testing include:
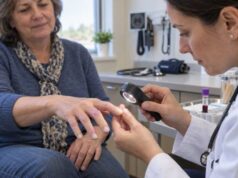
- Gottron papules or Gottron sign over the knuckles and other extensor joints.
- A violaceous heliotrope eruption around the eyelids, sometimes with swelling.
- A photosensitive rash over the upper chest, upper back, shoulders, face, or outer thighs.
- Scalp redness, scaling, itch, or hair thinning.
- Painful or itchy plaques, ulceration, or extensive redness.
- Ragged cuticles and abnormal nailfold capillaries.
- Symmetric difficulty rising from a chair, climbing stairs, lifting the arms, or holding the head up.
- Trouble swallowing, choking, nasal speech, or unexplained weight loss.
Published cohorts describe anti-TIF1-gamma disease as frequently having extensive or treatment-resistant skin involvement. Some patients develop ovoid palatal patches, psoriasiform lesions, or striking facial and ear involvement. These clues are supportive rather than mandatory; the appearance varies across skin tones and among individuals.
Muscle involvement ranges from absent to severe. Clinically amyopathic dermatomyositis refers to characteristic skin disease without clinically apparent muscle weakness for a defined period. Hypomyopathic dermatomyositis has no obvious weakness but shows subclinical muscle abnormalities on enzymes, imaging, electromyography, or biopsy. Anti-TIF1-gamma can occur in either pattern.
This means a normal creatine kinase does not dismiss a convincing dermatomyositis rash. Aldolase, careful strength testing, magnetic resonance imaging, electromyography, skin biopsy, or muscle biopsy may provide additional evidence when needed. Conversely, the antibody should not turn every nonspecific rash into dermatomyositis. Eczema, psoriasis, drug eruptions, lupus, rosacea, and other conditions can mimic parts of the cutaneous picture.
Compared with antibodies such as anti-MDA5 or antisynthetase antibodies, anti-TIF1-gamma is generally not the marker most associated with interstitial lung disease. Lung symptoms still deserve evaluation because individuals do not always follow group-level patterns and because infection, aspiration, treatment toxicity, or other cardiopulmonary disease may occur.
Age changes the interpretation. Anti-TIF1-gamma is also seen in juvenile dermatomyositis, where it may accompany extensive photosensitive skin disease, ulceration, or a chronic course. The strong adult malignancy association has not been established in children, so an adult cancer-screening framework should not be automatically applied to a child.
What the cancer association really means
Dermatomyositis in adults has a recognized temporal association with malignancy. Cancer may be diagnosed before, at the same time as, or after the autoimmune disease begins. The period of greatest concern is concentrated around myositis onset—commonly described as the three years before through the three years after onset—although ordinary age-appropriate cancer risk continues throughout life.
Among myositis-specific antibodies, anti-TIF1-gamma has one of the strongest and most consistently reproduced associations with cancer in adult dermatomyositis. Studies differ in the exact percentage because populations, ages, screening intensity, follow-up duration, ethnicity, and laboratory methods differ. A statistic from one referral-center cohort should not be treated as an individual prediction.
The key points are:
- The result raises probability; it does not establish a diagnosis. Many anti-TIF1-gamma-positive adults never have a malignancy identified.
- Risk depends on the setting. An antibody in confirmed adult dermatomyositis carries different meaning from an isolated weak positive in a person without a characteristic rash.
- Age matters. New dermatomyositis after age 40 is more concerning than childhood-onset disease, and risk generally rises with older age.
- Clinical features modify risk. Dysphagia, persistent high disease activity, skin necrosis or ulceration, unexplained fever, and weight loss can increase concern. Interstitial lung disease, Raynaud phenomenon, and inflammatory arthritis have been associated with lower cancer risk in some myositis datasets, but none can safely exclude malignancy.
- A negative result is not a clearance certificate. Adult dermatomyositis itself can be cancer-associated, and other phenotypes or antibodies may also confer risk.
Cancers reported with dermatomyositis reflect geography, age, sex, and background population patterns. Ovarian, lung, gastrointestinal, pancreatic, breast, and hematologic malignancies are among those described, while nasopharyngeal cancer is especially relevant in some Asian populations. There is no single “anti-TIF1-gamma cancer.” Screening therefore needs broader reasoning than ordering one tumor marker.
Cancer and dermatomyositis can move together, but not predictably. In some patients, successful cancer treatment improves the autoimmune disease; in others, dermatomyositis requires independent immunosuppressive treatment. A flare after remission may prompt renewed clinical review, but it does not prove tumor recurrence.
The emotional impact of this result is substantial. “Higher risk” is easily heard as “cancer is probably present.” A clinician should translate the result into an explicit plan: what screening is indicated, when it will occur, what a negative evaluation means, and how follow-up will be handled.
How cancer screening is planned
Cancer screening in adult inflammatory myopathy should be risk-stratified rather than improvised. The International Myositis Assessment and Clinical Studies Group guideline classifies dermatomyositis and anti-TIF1-gamma positivity as high-risk factors. In an adult with newly diagnosed anti-TIF1-gamma-positive dermatomyositis, those factors usually place the person in a high-risk category for myositis-associated cancer.
The guideline separates screening into “basic” and “enhanced” approaches. Exact implementation varies with country, available tests, age, pregnancy status, radiation exposure, comorbidities, and prior screening.
Basic assessment may include:
- Detailed history and physical examination, including skin, lymph nodes, breasts or testes where appropriate, and review of constitutional symptoms.
- Complete blood count, liver tests, inflammatory markers, urinalysis, and selected protein studies.
- Chest imaging, depending on the protocol and what has already been performed.
- Confirmation that routine population screening is current, such as cervical, breast, colorectal, lung, or prostate-related screening when applicable.
Enhanced assessment may include cross-sectional imaging of the neck, chest, abdomen, and pelvis; cervical screening; mammography; prostate-specific antigen testing; pelvic or transvaginal ultrasound; and fecal occult blood testing, selected according to anatomy, age, sex, and previous testing. The international guideline recommends both basic and enhanced screening at diagnosis for high-risk patients, followed by basic screening annually for three years. It also allows consideration of whole-body FDG-PET/CT and upper or lower gastrointestinal endoscopy in selected high-risk patients when initial investigations have not identified a cancer.
These are not automatic orders for every person. For example, CT may duplicate recent imaging; PET/CT can reveal incidental findings and involves radiation; transvaginal ultrasound is not an all-purpose ovarian cancer screen; endoscopy has procedural risks; and tumor markers can produce false-positive or false-negative results. Screening should be coordinated to avoid fragmented, repetitive testing.
A strong plan answers four questions:
- What has already been done? Recent emergency imaging, routine mammography, colonoscopy, or gynecologic assessment may satisfy parts of the evaluation.
- Which cancers are plausible for this patient? Family history, smoking, occupational exposure, ancestry, prior cancer, and symptoms matter.
- What is the myositis timeline? Risk is most concentrated near adult disease onset.
- What will happen after a negative screen? High-risk follow-up should be scheduled rather than left vague.
Any alarm symptom should be investigated on its own merits, regardless of a prior negative screen. Examples include unexplained bleeding, a new mass, persistent focal pain, progressive swallowing difficulty, altered bowel habits, unexplained iron-deficiency anemia, unintentional weight loss, or persistent fever.
Screening cannot reduce risk to zero. Its purpose is to find clinically occult disease at a more treatable stage while minimizing unnecessary harm from overtesting.
Reading the laboratory result
Anti-TIF1-gamma may be tested by immunoprecipitation, enzyme-linked immunosorbent assay, immunoblot, line blot, or multiplex platforms. Immunoprecipitation has often served as a research reference method, but it is specialized and not widely available. Commercial line blots are convenient because they test many myositis antibodies at once, yet weak bands and discordant results are well recognized.
A report should be interpreted at three levels.
Analytic level
Look for the testing method, numerical value or band intensity, reference range, and whether the laboratory labels the result weak, moderate, or strong. Different platforms are not interchangeable. Studies comparing methods have found that ELISA, line blot, and immunoprecipitation may differ in sensitivity, specificity, and their relationship to cancer-associated dermatomyositis.
Serologic level
Review the whole antibody panel. Major myositis-specific antibodies tend to define distinct phenotypes, although genuine overlap can occur and commercial assays may report multiple weak positives. A strong anti-TIF1-gamma result with a characteristic phenotype is more persuasive than several unrelated low-intensity bands.
An ANA test may be positive or negative and does not confirm or exclude anti-TIF1-gamma dermatomyositis. The target antigen can produce a nuclear pattern, but ANA pattern alone is not sufficiently specific.
Clinical level
Ask whether the patient actually has features of dermatomyositis. A positive result in an adult with Gottron papules, a heliotrope eruption, proximal weakness, and compatible biopsy findings has high clinical coherence. A weak isolated positive in someone tested for nonspecific fatigue has much lower pretest probability and may warrant expert review or confirmation before major cancer imaging is launched.
A negative anti-TIF1-gamma result does not rule out dermatomyositis. Other antibodies may define the phenotype, and a meaningful proportion of patients are negative for currently available myositis-specific antibodies. Nor does a negative result eliminate cancer screening in adult dermatomyositis; the plan should reflect the total risk profile.
Repeating anti-TIF1-gamma levels is not an established substitute for monitoring skin activity, muscle strength, swallowing, or cancer status. Some research suggests antibody levels may change with disease or tumor treatment, but routine serial measurement has not been standardized sufficiently to guide care by itself.
Diagnosis, treatment, and follow-up
The diagnostic workup is selected according to the presentation. A dermatologist, rheumatologist, neurologist, and sometimes an oncologist may all contribute.
Common components include:
- Full skin and muscle examination, with standardized strength testing.
- Creatine kinase, aldolase, AST, ALT, LDH, and other laboratory studies.
- Skin biopsy from an active representative lesion.
- Muscle MRI, electromyography, or muscle biopsy when the diagnosis or extent of myositis remains uncertain.
- Swallowing assessment for choking, coughing with meals, nasal regurgitation, or weight loss.
- Pulmonary and cardiac assessment when symptoms or phenotype warrant it.
- Cancer risk assessment and coordinated screening in adult-onset disease.
Treatment is based on the affected organs and severity, not the antibody alone. Sun protection and topical therapies are important for cutaneous disease. Systemic corticosteroids, methotrexate, mycophenolate, azathioprine, intravenous immunoglobulin, rituximab, calcineurin inhibitors, antimalarial drugs, and other agents may be considered in different circumstances. Exercise and rehabilitation are usually part of recovery once medically appropriate. Severe dysphagia, respiratory muscle weakness, rapidly progressive weakness, or extensive ulcerative skin disease may require urgent treatment.
Anti-TIF1-gamma-positive skin disease can be persistent even when muscle enzymes improve. Follow-up therefore should not rely on creatine kinase alone. Clinicians may track rash distribution, itch, pain, ulceration, muscle strength, function, swallowing, weight, treatment toxicity, and cancer-screening status as separate domains.
When cancer is found, treatment planning should be shared across specialties. Immunosuppression may still be needed, but the timing and drug choice can be influenced by surgery, chemotherapy, radiation, infection risk, blood counts, and the specific malignancy. There is no universal rule that dermatomyositis will resolve once a tumor is treated.
Urgent assessment is appropriate for difficulty breathing, choking or inability to swallow liquids, rapidly worsening weakness, dark urine with severe muscle symptoms, signs of infection during immunosuppression, or new symptoms concerning for malignancy.
Practical questions after testing
A useful review of a positive result should lead to decisions, not simply an alarming label. Questions to discuss include:
- Is the anti-TIF1-gamma result strong and clinically convincing, or does it need confirmation?
- Do my skin findings meet a dermatomyositis pattern, and should a skin biopsy be performed?
- Is there objective muscle involvement even if my creatine kinase is normal?
- When did my dermatomyositis symptoms probably begin?
- Which cancer-risk category applies to me under current myositis guidance?
- Which routine screening tests are already current, and which enhanced tests are appropriate now?
- Who will coordinate the screening and review incidental findings?
- What follow-up is planned if the first evaluation is negative?
- Which symptoms should trigger earlier reassessment?
- How will skin disease, muscle function, swallowing, and treatment effects be monitored separately?
Bring a complete medication list, family cancer history, prior pathology reports, dates and results of mammograms or colonoscopies, and copies of recent CT or other imaging. This can prevent unnecessary repetition and help the team choose the most informative next test.
The core interpretation is straightforward but nuanced: anti-TIF1-gamma can strongly support a dermatomyositis phenotype, and in an adult with that disease it justifies deliberate cancer-risk assessment. It is a signal to investigate thoughtfully—not a diagnosis of cancer and not a forecast of one person’s future.
References
- International Guideline for Idiopathic Inflammatory Myopathy-Associated Cancer Screening: an International Myositis Assessment and Clinical Studies Group (IMACS) Initiative (2023, PubMed)
- A Systematic Review and Meta-Analysis to Inform Cancer Screening Guidelines in Idiopathic Inflammatory Myopathies (2021, PubMed Central)
- Dermatomyositis: Practical Guidance and Unmet Needs (2024, PubMed)
- Clinical Features of Dermatomyositis Patients With Anti-TIF1 Antibodies: A Case Based Comprehensive Review (2023, PubMed)
- ELISA, Protein Immunoprecipitation and Line Blot Assays for Anti-TIF1-Gamma Autoantibody Detection in Cancer-Associated Dermatomyositis (2022, PubMed Central)
- The Role of Myositis-Specific Autoantibodies and the Management of Dermatomyositis-Associated Interstitial Lung Disease (2022, PubMed)
Disclaimer
This article provides general education and cannot diagnose dermatomyositis or cancer. Anti-TIF1-gamma results and cancer-screening decisions require individualized interpretation by qualified clinicians using the full clinical history, examination, assay details, and local guidelines. Seek urgent care for severe breathing or swallowing difficulty, rapidly progressive weakness, or other acute symptoms.