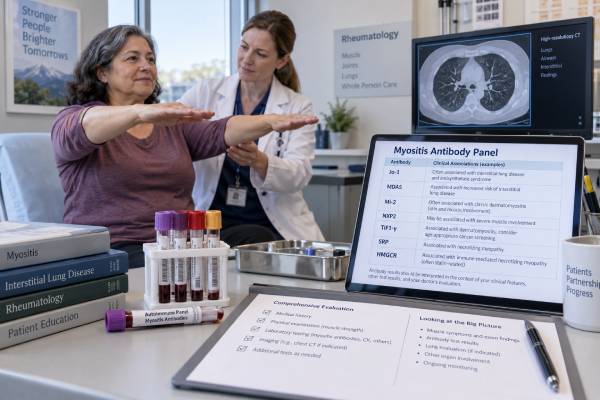
A myositis antibody panel looks for autoantibodies associated with inflammatory muscle diseases and related syndromes. The panel can help distinguish dermatomyositis, antisynthetase syndrome, immune-mediated necrotizing myopathy, overlap myositis, and some cases of inclusion body myositis. It can also reveal risks that are not obvious from muscle symptoms alone, especially interstitial lung disease, rapidly progressive lung inflammation, swallowing problems, characteristic skin disease, and cancer-associated dermatomyositis.
The panel does not diagnose myositis by itself. Results must match the person’s pattern of weakness, skin findings, muscle enzymes, lung evaluation, imaging, electromyography, and sometimes biopsy. Commercial panels also differ in which antibodies they include and how accurately they detect them. A strong, clinically coherent result may change screening and treatment decisions; a weak, isolated result in someone without compatible symptoms may be false positive or of uncertain significance.
- Myositis-specific antibodies often identify a clinical subtype, but a negative panel does not rule out inflammatory myopathy.
- Antisynthetase and anti-MDA5 antibodies can signal important interstitial lung disease risk, even when muscle weakness is mild.
- Anti-SRP and anti-HMGCR support immune-mediated necrotizing myopathy when rapid weakness and high creatine kinase are present.
- Anti-TIF1-gamma and some other dermatomyositis markers affect cancer-risk assessment but do not diagnose cancer.
- Rapid breathlessness, trouble swallowing, neck weakness, or quickly progressive limb weakness needs prompt medical evaluation.
Table of Contents
- What a myositis panel measures
- Antibody patterns and the phenotypes they suggest
- Lung risk on a myositis panel
- How results fit with muscle, skin, and swallowing findings
- Why test method and signal strength matter
- Diagnosis after a positive or negative panel
- Monitoring, treatment, and urgent warning signs
What a myositis panel measures
Myositis panels test for autoantibodies directed against proteins involved in cell signaling, RNA processing, protein synthesis, muscle repair, or immune responses. Laboratories usually divide them into two broad groups.
Myositis-specific autoantibodies (MSAs) are strongly associated with particular inflammatory myopathy subtypes. Examples include anti-Jo-1 and other antisynthetase antibodies, anti-Mi-2, anti-TIF1-gamma, anti-MDA5, anti-NXP2, anti-SAE, anti-SRP, and anti-HMGCR. “Specific” does not mean perfect specificity. Some results occur outside classic myositis, and assay errors can produce misleading positives.
Myositis-associated autoantibodies (MAAs) are seen in myositis overlap syndromes and other connective tissue diseases. Common examples include anti-PM/Scl, anti-Ku, anti-U1 RNP, and anti-Ro52. These results may suggest that muscle inflammation is part of a broader systemic autoimmune disease rather than an isolated myopathy.
Panel composition varies substantially. One laboratory may include 11 antibodies; another may include more than 20. Anti-HMGCR is sometimes ordered separately. Anti-cN1A, used as supportive evidence in suspected inclusion body myositis, may also require a separate test. A report labeled “negative myositis panel” therefore means only that the included antibodies were not detected by that laboratory’s method.
The test is usually performed on serum and generally needs no fasting or special timing. Medication does not have to be withheld solely for the blood draw unless the treating clinician gives specific instructions. Immunosuppressive treatment may affect some antibody concentrations, but this does not make the panel a reliable activity-monitoring test.
A panel is most useful when the pretest question is clear. Examples include:
- New symmetric proximal weakness with elevated creatine kinase
- A dermatomyositis-type rash, with or without weakness
- Unexplained interstitial lung disease, especially with arthritis, Raynaud phenomenon, fever, or “mechanic’s hands”
- Rapidly progressive weakness suggesting necrotizing myopathy
- Muscle disease occurring with systemic sclerosis, lupus, or another connective tissue disease
- Persistent swallowing dysfunction or respiratory muscle weakness when inflammatory myopathy is plausible
Testing every antibody in a person with nonspecific fatigue or muscle aches can produce incidental results that are harder to interpret than the original symptoms.
Antibody patterns and the phenotypes they suggest
The strongest value of a myositis panel is phenotype prediction. Each antibody should be viewed as a clue to a pattern, not as a stand-alone disease label.
| Antibody group | Common clinical association | Key interpretation point |
|---|---|---|
| Anti-Jo-1, PL-7, PL-12, EJ, OJ and other antisynthetases | Antisynthetase syndrome with interstitial lung disease, myositis, inflammatory arthritis, Raynaud phenomenon, fever, and mechanic’s hands | Lung disease may dominate, and weakness may appear later or remain mild |
| Anti-MDA5 | Dermatomyositis, often with little muscle inflammation; skin ulcers, painful palmar papules, arthritis, and rapidly progressive ILD | Normal or modest creatine kinase does not remove lung risk |
| Anti-Mi-2 | Classic dermatomyositis rash and muscle disease | Often associated with prominent skin findings and a generally treatment-responsive phenotype |
| Anti-TIF1-gamma | Adult dermatomyositis with increased malignancy risk; characteristic skin disease | It changes cancer screening intensity but does not prove that cancer is present |
| Anti-NXP2 | Dermatomyositis, edema, severe weakness, dysphagia, and calcinosis, especially in juvenile disease | Adult malignancy associations are less consistent than for TIF1-gamma and require full risk context |
| Anti-SAE | Dermatomyositis, sometimes beginning with skin disease before weakness; dysphagia can be prominent | Muscle involvement may emerge after the rash |
| Anti-SRP | Immune-mediated necrotizing myopathy with severe, rapidly progressive proximal weakness and very high CK | Cardiac or respiratory involvement can occur; treatment often needs to be aggressive |
| Anti-HMGCR | Immune-mediated necrotizing myopathy, sometimes after statin exposure | Disease can occur without statin use and may persist after the drug is stopped |
| Anti-PM/Scl, Ku, U1 RNP | Overlap myositis with systemic sclerosis, lupus, or mixed connective tissue disease features | The broader connective tissue phenotype determines organ screening |
| Anti-Ro52 | Common accompanying antibody in several systemic autoimmune diseases | It is not myositis-specific; with antisynthetase or MDA5 antibodies it may mark a more complex ILD phenotype |
| Anti-cN1A | Supportive marker for inclusion body myositis | Sensitivity and specificity are limited; it also occurs in Sjögren disease and other conditions |
Most people have one dominant MSA rather than several unrelated MSAs. A commercial report showing multiple weak MSA positives should therefore prompt careful review of signal strength, method, and clinical fit. This pattern may reflect analytical cross-reactivity rather than several simultaneous myositis syndromes.
Anti-SRP and anti-HMGCR belong to a distinct necrotizing-myopathy group. A detailed anti-SRP antibody interpretation is most useful when the patient has objective weakness, marked CK elevation, and muscle imaging or biopsy consistent with immune-mediated necrosis.
Anti-TIF1-gamma belongs to the dermatomyositis group. Its main practical consequence in adults is risk-stratified malignancy screening. The anti-TIF1-gamma result must be integrated with age, disease onset, skin findings, dysphagia, weight change, smoking history, family history, sex-specific risks, and routine population screening.
Lung risk on a myositis panel
Interstitial lung disease (ILD) is one of the most important reasons to order and correctly interpret a myositis antibody panel. ILD can precede weakness, develop at the same time, or emerge later. In some patients, the lungs are the main affected organ.
Antisynthetase antibodies are the classic lung-associated markers. Anti-Jo-1 is the best known, but non-Jo-1 antibodies such as PL-7, PL-12, EJ, and OJ may present with proportionally greater lung involvement and less obvious muscle disease. A person may initially be labeled as having idiopathic ILD until arthritis, Raynaud phenomenon, mechanic’s hands, muscle enzyme abnormalities, or antibody testing reveals the systemic pattern.
Anti-MDA5 requires a different level of urgency. It is associated with dermatomyositis that may be clinically amyopathic, meaning there is little or no obvious muscle weakness. Some affected patients develop rapidly progressive ILD over days to weeks. Skin ulcers, tender palmar papules, arthritis, fever, and a characteristic dermatomyositis rash can be important clues. A normal CK does not make this phenotype safe.
Symptoms that should trigger lung assessment include new dry cough, breathlessness, declining exercise tolerance, chest tightness, or oxygen desaturation. Yet early ILD can be asymptomatic. Current guidance supports pulmonary function tests and high-resolution chest CT for screening people with idiopathic inflammatory myopathy who are at increased ILD risk. A routine chest X-ray is not sensitive enough to exclude early disease.
Pulmonary function tests typically include forced vital capacity and diffusing capacity for carbon monoxide. These numbers help quantify impairment but do not identify the exact cause. High-resolution CT shows the pattern and extent of lung injury. Oxygen saturation at rest and during activity, echocardiography when pulmonary hypertension is possible, infection testing, and sometimes bronchoscopy may be needed for specific clinical questions.
An antibody result cannot tell whether ILD is active, fibrotic, infected, or responding to treatment. Follow-up depends on symptoms, PFT trends, oxygenation, imaging, and treatment toxicity. Rapid clinical deterioration requires urgent specialist assessment rather than waiting for repeat antibody testing.
How results fit with muscle, skin, and swallowing findings
Inflammatory myopathy usually causes objective weakness, not just soreness. The classic pattern affects muscles closest to the trunk: hips, thighs, shoulders, upper arms, and neck flexors. People may struggle to rise from a low chair, climb stairs, lift objects overhead, wash their hair, or hold up their head. Weakness is often symmetric, although inclusion body myositis commonly produces an asymmetric pattern involving finger flexors and quadriceps.
Creatine kinase (CK) is an important muscle injury marker, but it is not an all-purpose screening answer. CK may rise into the thousands in immune-mediated necrotizing myopathy. It can be moderately elevated in antisynthetase syndrome or dermatomyositis. It may be normal in clinically amyopathic dermatomyositis, anti-MDA5 disease, chronic burned-out muscle damage, or some inclusion body myositis cases. Aldolase can occasionally be abnormal when CK is not, but neither enzyme is specific to autoimmune myositis.
Dermatomyositis skin findings include a violet or reddish discoloration around the eyelids, scaly papules over the knuckles, photosensitive redness over the chest or upper back, scalp inflammation, nailfold changes, and cracking along the sides of the fingers. Anti-MDA5, TIF1-gamma, Mi-2, NXP2, and SAE may point toward different skin and systemic patterns, but dermatologic examination and sometimes skin biopsy remain important.
Swallowing deserves direct questioning because patients may adapt without describing it as weakness. Warning signs include coughing with liquids, food sticking, repeated throat clearing, a wet voice after swallowing, prolonged meals, nasal regurgitation, aspiration pneumonia, and unintended weight loss. Anti-NXP2, anti-SAE, TIF1-gamma dermatomyositis, necrotizing myopathy, and inclusion body myositis can all involve swallowing.
Respiratory muscle weakness is different from ILD but can produce similar breathlessness. Orthopnea, weak cough, morning headache, or reduced vital capacity when lying flat may suggest neuromuscular respiratory involvement. Clinicians may need diaphragm assessment, supine and upright spirometry, maximal inspiratory pressure, or sleep-related breathing evaluation.
Cancer assessment is not triggered by every positive panel. Adult dermatomyositis carries a time-linked malignancy risk, greatest near disease onset, and the level varies by antibody and clinical features. International guidance uses risk categories rather than one universal scan for everyone. Basic and enhanced screening may include history, physical examination, routine blood tests, age- and sex-appropriate screening, and selected imaging or procedures. The goal is neither to ignore risk nor to expose every patient to unlimited testing.
Why test method and signal strength matter
Myositis antibody testing is analytically challenging. Immunoprecipitation is often treated as a reference method in research, but it is labor-intensive and not widely available for routine care. Commercial laboratories commonly use line blot, dot blot, enzyme immunoassay, chemiluminescence, or multiplex methods. These platforms can disagree because they present antigens differently and use different thresholds.
Line immunoblots make broad testing accessible, but weak bands can be misleading. Studies have found that stronger signal intensities correlate better with expected clinical phenotypes than weak positives. The likelihood that a result is meaningful also rises when the pretest probability is high. For example, a strong anti-Jo-1 result in a patient with ILD, inflammatory arthritis, mechanic’s hands, and elevated CK is much more persuasive than a weak anti-Jo-1 band found during evaluation of isolated fatigue.
Several practical questions improve interpretation:
- Which exact antigens were included? A “negative” report cannot exclude an antibody the laboratory never tested.
- Was the result weak, moderate, or strong? The manufacturer’s categories are not standardized across platforms.
- Does the antibody match the phenotype? Discordance should reduce confidence, especially with multiple weak MSA positives.
- Was a second method used? Confirmation may be valuable when the result would change cancer screening, urgent ILD treatment, or a lifelong diagnosis.
- Could another disease explain it? Anti-Ro52, U1 RNP, PM/Scl, Ku, and cN1A occur in broader autoimmune settings.
Panel results should not be compared numerically across laboratories. A value of 45 units on one assay may have no direct relationship to 45 units on another. Repeating the entire panel every few months is usually not useful. Some antibody levels change with treatment, but routine serial titers are not established substitutes for strength testing, CK, lung function, skin assessment, or imaging.
Diagnosis after a positive or negative panel
A positive antibody narrows the diagnostic path; it does not finish it. Clinicians combine symptoms, examination, laboratory results, imaging, electrophysiology, pathology, and exclusion of mimics.
The initial laboratory assessment commonly includes CK, aldolase, AST, ALT, lactate dehydrogenase, complete blood count, kidney function, inflammatory markers, urinalysis, thyroid testing, and medication review. AST and ALT can come from injured muscle, so an abnormal “liver panel” should be interpreted with CK and other muscle markers rather than assumed to be liver disease.
Muscle MRI can identify edema, fatty replacement, and a suitable biopsy site. Electromyography can support an irritable myopathy and identify neuropathic alternatives. Muscle biopsy remains valuable when the phenotype and antibody do not align, when inclusion body myositis is possible, when genetic or metabolic disease remains in the differential, or when treatment consequences are substantial. Skin biopsy may help in rash-predominant dermatomyositis.
Important mimics include statin toxicity without persistent autoimmune myopathy, thyroid disease, adrenal disorders, electrolyte problems, infection, muscular dystrophy, metabolic myopathy, motor neuron disease, neuropathy, medication-induced weakness, deconditioning, and fibromyalgia. A broad connective tissue disease panel can help when arthritis, Raynaud phenomenon, low blood counts, kidney findings, or systemic-sclerosis features accompany muscle symptoms. Anti-U1 RNP, PM/Scl, and Ku results may place the patient in an overlap category, including mixed connective tissue disease.
A negative panel does not exclude myositis for several reasons: the relevant antigen may be absent from the kit, the assay may miss it, the disease may be seronegative, or the diagnosis may be a subtype not well captured by current commercial panels. The 2017 EULAR/ACR classification criteria can estimate the probability of idiopathic inflammatory myopathy, but newer reviews note limitations for immune-mediated necrotizing myopathy, amyopathic dermatomyositis, antisynthetase syndrome, and overlap myositis. Classification criteria support research consistency; they are not a replacement for clinical diagnosis.
Monitoring, treatment, and urgent warning signs
Treatment depends on the phenotype and affected organs. Glucocorticoids are often used for active inflammatory myopathy, but many patients need a steroid-sparing agent such as methotrexate, azathioprine, mycophenolate, tacrolimus, cyclophosphamide, rituximab, intravenous immunoglobulin, or another targeted therapy. The choice differs for severe ILD, dermatomyositis skin disease, immune-mediated necrotizing myopathy, swallowing dysfunction, and overlap disease.
Exercise is part of treatment when tailored to disease severity. Supervised resistance and aerobic activity can help preserve strength, endurance, and function after acute instability is controlled. Physical and occupational therapists can address falls, transfers, hand function, and energy use. Speech-language pathologists and nutrition specialists are important when swallowing is affected.
Monitoring usually focuses on:
- Standardized strength and functional testing
- CK and other muscle enzymes when they were abnormal at baseline
- Skin activity and ulceration
- Swallowing safety, nutrition, and aspiration risk
- Pulmonary symptoms, oxygenation, PFTs, and selected repeat HRCT
- Medication adverse effects, infection risk, vaccination, and bone health
- Age-appropriate and risk-stratified malignancy screening
Antibody titers are rarely the central follow-up measure. A patient can improve while remaining antibody positive, or deteriorate without a meaningful titer change. Clinical function and organ tests carry more weight.
Urgent assessment is warranted for rapidly increasing breathlessness, falling oxygen saturation, chest pain, coughing blood, rapidly progressive limb or neck weakness, inability to rise or walk safely, weak cough, choking, inability to swallow liquids, dark urine with severe muscle symptoms, fever during immunosuppression, or new confusion. In anti-MDA5 disease, a seemingly modest muscle presentation should not delay evaluation of fast-moving respiratory symptoms. In necrotizing myopathy, severe weakness and very high CK can lead to immobility, aspiration, or respiratory complications.
The best use of a myositis antibody panel is to turn a complex result into a practical plan: confirm that the signal is credible, identify the likely phenotype, screen the organs linked to that phenotype, exclude mimics, and follow objective clinical change rather than the antibody name alone.
References
- 256th ENMC international workshop: Myositis specific and associated autoantibodies (MSA-ab): Amsterdam, The Netherlands, 8-10 October 2021 2022 (Position Statement)
- Myositis autoantibodies detected by line blot immunoassay: clinical associations and correlation with antibody signal intensity 2023
- International Guideline for Idiopathic Inflammatory Myopathy-Associated Cancer Screening: an International Myositis Assessment and Clinical Studies Group (IMACS) Initiative 2023 (Guideline)
- 2023 American College of Rheumatology (ACR)/American College of Chest Physicians (CHEST) Guideline for the Screening and Monitoring of Interstitial Lung Disease in People with Systemic Autoimmune Rheumatic Diseases 2024 (Guideline)
- A Review of Myositis-Associated Interstitial Lung Disease 2024 (Review)
- Performance of the 2017 EULAR/ACR Classification Criteria for Adult and Juvenile Idiopathic Inflammatory Myopathies and their Major Subgroups: A Scoping Review 2024 (Review)
Disclaimer
This article provides general education and cannot diagnose inflammatory myopathy or replace care from a rheumatologist, neurologist, pulmonologist, dermatologist, or other qualified clinician. Myositis antibody results must be interpreted with the laboratory method, symptoms, examination, muscle enzymes, lung testing, and imaging or biopsy when needed. Seek urgent care for rapidly worsening breathing, severe weakness, unsafe swallowing, or other acute symptoms.