
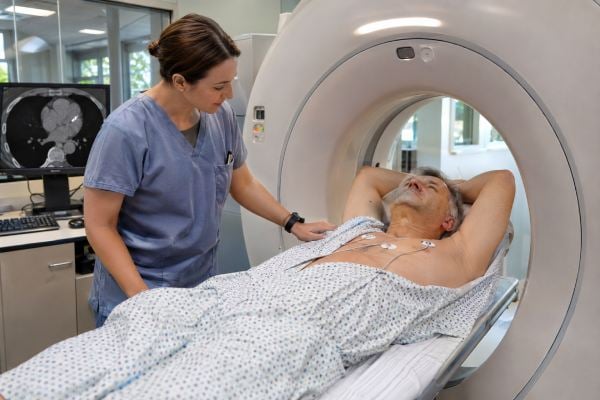
A coronary artery calcium score, or CAC score, is a low-dose CT test that detects calcified plaque in the arteries that supply the heart. It does not directly measure how narrow an artery is, and it is not the same as a coronary CT angiogram. Its main purpose is risk refinement: it can show whether a person who has no known coronary disease already has measurable coronary atherosclerosis, then help guide prevention decisions such as whether to start or intensify statin therapy.
The test is most useful when the answer could change what you do next. A score of 0 can support a lower near-term coronary risk in selected people, while a score of 100 or more, or a high age- and sex-specific percentile, generally strengthens the case for aggressive risk reduction. CAC is not a routine screening test for everyone, and it is not the right test for active chest pain. Age, diabetes, smoking, family history, LDL level, and existing cardiovascular disease all affect how the result should be interpreted.
Table of Contents
- What a CAC Score Measures
- How the Test Is Done
- What CAC Numbers Mean
- Who Should Consider CAC Scoring?
- Who Usually Does Not Need It?
- How Results Can Change Treatment
- Limits, Radiation, and Repeat Testing
- Common CAC Questions and Misunderstandings
What a CAC Score Measures
CAC scoring detects calcium deposited within atherosclerotic plaque in coronary artery walls. Coronary atherosclerosis is the process behind most heart attacks: cholesterol-rich plaque develops over years, can calcify, and may eventually narrow an artery or rupture and trigger a clot.
The scan usually reports an Agatston score. The calculation combines the area and density of visible coronary calcium. The more calcified plaque present, the higher the score and, on average, the higher the future risk of coronary heart disease events.
A CAC score is therefore a plaque-burden marker, not a stress test and not a direct measurement of blood flow. A score of 300 does not mean an artery is 300% blocked, and a score of 0 does not prove that every artery is perfectly clean. Noncalcified, or “soft,” plaque can exist before calcium becomes visible.
That distinction is especially important in younger adults. A 40-year-old can have noncalcified atherosclerosis despite CAC 0, while any detectable calcium at a young age may be more unusual than the same absolute score in an older adult.
CAC adds information beyond traditional risk factors. Blood pressure, smoking, diabetes, cholesterol, kidney disease, and family history estimate the probability of disease; CAC shows whether calcified coronary plaque is already present. If you are unfamiliar with the disease process itself, see coronary artery disease symptoms, risk factors, and prevention.
How the Test Is Done
The test uses a noncontrast CT scanner synchronized with the ECG. Electrodes on the chest allow images to be captured at a consistent point in the heartbeat, which reduces motion. No IV contrast dye is normally needed.
The scan itself takes only a few minutes. Preparation varies by center, but patients are commonly told to avoid caffeine and smoking for several hours because a slower, steadier heart rate improves image quality. You lie flat, hold your breath for short periods, and the scanner acquires thin images through the heart.
A dedicated CAC scan is relatively low radiation, often around 1 millisievert, though dose varies by scanner, body size, and protocol. For perspective, that is in the range of a fraction of annual natural background radiation in many locations. Radiation is not zero, so the test should have a clinical purpose.
Unlike coronary CT angiography, CAC scoring does not require iodinated contrast and cannot map the coronary lumen in the same detail. It is also different from an exercise or pharmacologic stress test, which looks for evidence that blood flow becomes inadequate under stress.
The report may include the total Agatston score, scores for individual coronary arteries, an age/sex/race percentile, and incidental findings outside the heart. Increasingly, coronary calcium is also identified opportunistically on chest CT scans performed for other reasons. A 2025 American Heart Association scientific statement emphasized that reporting incidental CAC can improve prevention without adding radiation because the scan has already been done.
What CAC Numbers Mean
Common categories are useful, but context matters.
| CAC score | Typical interpretation | Practical meaning |
|---|---|---|
| 0 | No detectable calcified coronary plaque | Often indicates low near-term coronary event risk, with important exceptions |
| 1–99 | Mild calcified plaque | Atherosclerosis is present; treatment discussion becomes more favorable, especially with increasing age |
| 100–299 | Moderate plaque burden | Generally supports statin therapy and stronger risk-factor control |
| 300–999 | High plaque burden | High preventive priority; risk can approach that of some secondary-prevention groups |
| 1,000 or more | Very extensive calcification | Very high risk; aggressive preventive management is typically warranted |
A score of 0 is sometimes called the “power of zero.” In an otherwise appropriate primary-prevention patient, it can support delaying a statin when the decision is uncertain. But CAC 0 should not automatically down-classify risk in everyone. Current guidance generally treats diabetes, active smoking, and strong premature family history as important exceptions. Very high LDL cholesterol can also create high lifetime risk regardless of CAC.
A positive score proves coronary atherosclerosis is present. The percentile can be particularly useful in younger people. For example, a CAC of 40 may sound low in absolute terms, but it can be unusually high for a person in their early 40s. Conversely, an older adult may have a higher absolute score that is less unusual for age, though the plaque burden still matters.
The result should be interpreted together with LDL, non-HDL cholesterol, apoB, blood pressure, diabetes status, smoking, and family history. In some patients, apoB testing can further clarify the number of atherogenic particles driving risk.
Who Should Consider CAC Scoring?
CAC is most helpful for adults without known atherosclerotic cardiovascular disease when preventive treatment is genuinely uncertain. Major guidelines commonly use it as a decision aid in borderline- or intermediate-risk adults rather than as universal screening.
Examples include:
- A middle-aged adult with a 10-year ASCVD risk in the borderline or intermediate range who is unsure about starting a statin.
- Someone with risk-enhancing factors—such as a strong family history, elevated lipoprotein(a), chronic inflammatory disease, or metabolic syndrome—whose standard risk estimate does not clearly settle the treatment decision.
- An older adult reluctant to start lifelong statin therapy when a CAC result would materially change that choice.
- A younger adult with multiple risk factors or a strong premature family history when detecting unexpectedly early plaque would lead to more intensive prevention.
- A person with incidental coronary calcium noted on another CT who needs more formal risk assessment.
The key phrase is “would change management.” If you and your clinician already agree on statin treatment regardless of the result, a dedicated CAC scan may add little. If you would decline a statin even with a very high score, the scan also may not help.
CAC can be especially powerful when the decision is close. A person with LDL 145 mg/dL, treated blood pressure, no diabetes, no smoking, and an intermediate calculated risk may reasonably hesitate about medication. CAC 0 might support continued lifestyle therapy and reassessment, while CAC 250 strongly indicates established plaque and can make the benefit of LDL lowering more concrete.
Who Usually Does Not Need It?
CAC is not intended to diagnose acute coronary syndrome. New chest pressure, exertional chest discomfort, unexplained shortness of breath, fainting, or other potentially cardiac symptoms require a clinical evaluation. A normal CAC score should never be used to dismiss concerning symptoms.
People with known coronary artery disease, prior heart attack, coronary stent, bypass surgery, ischemic stroke from atherosclerosis, or peripheral artery disease generally already qualify for intensive prevention. A CAC score rarely changes that.
CAC is also usually unnecessary when treatment is already clearly indicated because of very high LDL cholesterol or another major risk condition. For instance, an untreated LDL level of 190 mg/dL or higher typically warrants LDL-lowering treatment regardless of CAC because lifetime exposure is important. A CAC of 0 is not a free pass to ignore severe hypercholesterolemia.
Routine testing in very young, very low-risk adults is unlikely to be useful because calcium is uncommon and the result usually does not change management. Pregnancy is another situation in which elective CT radiation is generally avoided.
Finally, repeated scanning simply to watch the number rise is usually not useful. Calcium scores tend to increase over time, and statins can increase plaque calcification density while stabilizing plaque. A rising CAC after statin treatment does not necessarily mean therapy is failing.
How Results Can Change Treatment
The clearest use of CAC is deciding how intensively to lower LDL cholesterol. U.S. guidance has traditionally used thresholds such as CAC 1–99 to favor statin therapy, particularly after age 55, and CAC 100 or higher or at least the 75th percentile to strongly support statin treatment.
More recent preventive cardiology literature increasingly recognizes that CAC 300 or more can represent risk comparable to some people with established cardiovascular disease. CAC 1,000 or more marks an especially high-risk group. Those patients often warrant intensive LDL lowering, blood-pressure control, smoking cessation, exercise, weight management, and diabetes treatment when applicable.
If a score is 0 and there are no major exceptions, a clinician may reasonably defer a statin and revisit the decision later. That is not the same as “no risk.” Lifestyle measures still matter, and plaque can develop over time.
Aspirin is more complicated. CAC can help identify people with enough atherosclerotic burden that aspirin might have a favorable benefit-risk balance, but aspirin also raises bleeding risk. It should not be started from a CAC number alone.
CAC also changes the conversation. Some people understand abstract percentages poorly but respond strongly to knowing that plaque is already visible. That can improve adherence to lifestyle changes and medication. Others may feel undue anxiety, so the result should be explained in terms of action rather than alarm.
If a high CAC score leads to a statin discussion, reviewing who benefits from statins can help put the scan in context.
Limits, Radiation, and Repeat Testing
CAC is a strong risk marker, but it has limitations. It detects calcified plaque, not all plaque. It does not tell you which lesion will rupture, whether a specific artery is severely narrowed, or whether the heart muscle is receiving enough blood during exercise.
A score can also be falsely reassuring in younger people, who may have predominantly noncalcified plaque. Symptoms always override a screening result.
Incidental findings are another tradeoff. CT may reveal lung nodules or other abnormalities that require follow-up. Sometimes that is beneficial; sometimes it leads to additional testing for findings that would never have caused harm.
For repeat testing after CAC 0, suggested intervals often range from about three to seven years depending on baseline risk. There is no single schedule for everyone. Repeating sooner usually adds little, while waiting too long can miss changing risk in a person who develops diabetes, starts smoking, or experiences a major increase in cholesterol or blood pressure.
When CAC is already clearly positive, repeat scoring is less useful because the presence of plaque has already answered the central prevention question. Follow treatment targets rather than chasing a lower calcium score; CAC usually does not decrease with effective therapy.
The best use of the test is therefore selective: order it when uncertainty exists, interpret it with the full risk profile, and turn the result into a prevention plan.
Common CAC Questions and Misunderstandings
CAC reports are simple on the surface but easy to misinterpret. These questions clarify what the score can and cannot tell you.
Can a high CAC score be reversed?
The practical treatment goal is not to make the calcium number go down. Calcification is part of plaque biology, and effective statin therapy can increase calcium density while making plaque more stable. A higher follow-up score therefore does not automatically mean treatment failed.
Focus on reducing future event risk: lower LDL and apoB, control blood pressure, avoid tobacco, exercise regularly, manage diabetes, and follow a heart-healthy eating pattern. Those actions are useful even if calcium remains visible.
Does CAC 0 mean you cannot have a heart attack?
No. CAC 0 is associated with a very low near-term rate of coronary events in appropriately selected asymptomatic adults, but risk is not zero. Soft plaque can exist without calcification, especially in younger people. A plaque can also develop after the scan.
Symptoms change the question entirely. If you develop exertional chest pressure or other concerning symptoms, a prior CAC 0 should not prevent further evaluation.
Does a high score mean you need a stent?
No. CAC measures total calcified plaque burden, not whether one artery has a flow-limiting blockage. A person can have CAC 600 without a severe focal stenosis, while another person can have a lower CAC with an important noncalcified narrowing.
Stents are used for specific clinical indications such as acute coronary syndromes or selected cases of symptomatic ischemia. A high CAC score by itself is a prevention signal, not a stent referral.
Can CAC decide whether aspirin is right for you?
CAC can contribute to the discussion, but it cannot decide alone. Aspirin can reduce thrombotic events and also cause gastrointestinal or intracranial bleeding. Age, bleeding history, kidney disease, other medications, and overall cardiovascular risk must be considered. Never start daily aspirin solely because a calcium score is elevated without discussing the tradeoff with a clinician.
What if incidental calcium is seen on a lung CT?
Coronary calcium seen on a routine chest CT is clinically meaningful. The scan may not produce a formal Agatston score because it was not ECG-gated, but visual categories such as mild, moderate, or severe still provide risk information. A 2025 AHA scientific statement supports using incidental CAC to improve preventive care.
The next step is usually a cardiovascular risk review, not automatically another CT. If the incidental burden is clearly moderate or severe and the treatment decision is already obvious, a dedicated scoring scan may add little.
How often should CAC 0 be repeated?
There is no universal interval. In selected adults with CAC 0, repeat testing may be considered after roughly three to seven years depending on age and risk. Higher-risk people may convert from zero sooner. Lower-risk people may not need another scan at all if the result would not change treatment.
A new diagnosis of diabetes, substantial LDL increase, smoking, or other major risk change can alter the timetable. Repeat scanning should be a decision tool, not an annual tracking ritual.
Why does percentile matter?
Absolute score describes plaque burden; percentile describes how unusual that burden is for people of similar age and sex, and in some calculators race or ethnicity. A CAC of 50 in a younger adult can place that person at a high percentile and signal premature atherosclerosis. In an older adult, 50 may be a lower percentile but still proves plaque is present.
Both views matter. Clinicians usually interpret absolute score, percentile, and the full risk profile together.
What should you do after a high result?
Do not panic and do not schedule repeated scans on your own. Use the result to build a prevention plan. Review LDL, apoB when appropriate, blood pressure, A1C or glucose, smoking, exercise, weight, and family history. Discuss the intensity of lipid lowering and whether other testing is needed based on symptoms—not based on fear of the number.
A CAC report is most valuable when it changes behavior or treatment. Its purpose is to turn hidden atherosclerosis into actionable prevention, not to predict the exact date of a future event.
References
- Guideline-Directed Application of Coronary Artery Calcium Scores for Primary Prevention of Atherosclerotic Cardiovascular Disease 2025 (Review)
- Coronary artery calcium in 2023: Guidelines for LDL-C goals, non-statin therapies, and aspirin use 2024 (Review)
- Opportunistic Detection of Coronary Artery Calcium on Noncardiac Chest Computed Tomography: An Emerging Tool for Cardiovascular Disease Prevention: A Scientific Statement From the American Heart Association 2025 (Position Statement)
- Coronary Artery Calcium in Assessment of Atherosclerotic Cardiovascular Disease Risk and its Role in Primary Prevention 2023 (Review)
- Coronary Artery Calcium Scoring for Risk Reclassification and Prediction of Hard Cardiovascular Events in Asymptomatic Adults at Low-to-Intermediate Cardiovascular Risk: A Systematic Review 2026 (Systematic Review)
Disclaimer
This article provides general education and does not diagnose coronary disease or determine whether you personally need a CT scan. CAC scoring should be considered with a clinician who can interpret your age, symptoms, cholesterol, blood pressure, diabetes status, smoking history, and family history. New or concerning chest symptoms require medical evaluation regardless of a prior CAC result.





