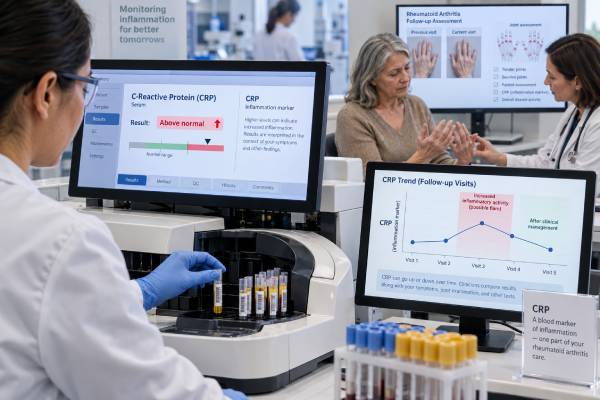
The C-reactive protein (CRP) test helps estimate inflammation in rheumatoid arthritis (RA), but it does not measure joint damage directly and cannot confirm a flare by itself. CRP is a liver protein that can rise and fall within hours to days. Clinicians use the result with swollen-joint counts, pain and stiffness, physical function, and sometimes imaging.
A normal value does not guarantee that RA is quiet. Some people have active synovitis despite repeatedly normal inflammatory markers, while others have elevated results because of infection, anemia, obesity, kidney disease, or another inflammatory condition. The most useful approach is to compare the result with the person’s baseline, the laboratory range, and the same-day clinical picture. This article explains ranges, trends, flares, treatment monitoring, and the situations in which a surprising result needs follow-up.
- What it measures: a liver-made acute-phase protein, providing an indirect estimate of systemic inflammation.
- Typical reference range: often below 3–10 mg/L, depending on assay.
- A high result is not RA-specific: infection and many non-RA conditions can raise it.
- A normal result does not exclude active synovitis: examination and imaging may show inflammation that blood testing misses.
- Trends are most useful: compare results from the same laboratory with symptoms and treatment timing.
Table of Contents
- What the CRP Test Measures
- Reference Ranges, Units, and Meaning
- How CRP Relates to RA Flares and Disease Activity
- Common Reasons for a High Result
- Why Active RA Can Occur With a Normal Result
- Using the Test to Monitor Treatment
- Preparation and Practical Next Steps
- Detailed Questions About CRP
What the CRP Test Measures
CRP is produced mainly by the liver in response to cytokines such as interleukin-6. It can rise within about 6–8 hours after a strong inflammatory stimulus, often peaks within roughly 48 hours, and falls relatively quickly when the stimulus resolves.
The test detects systemic inflammation rather than RA-specific immunity. It does not identify which joint is inflamed, distinguish rheumatoid arthritis from infection, or prove that pain comes from active synovitis. That distinction matters because osteoarthritis, tendon pain, fibromyalgia, and old structural damage can cause major symptoms without raising inflammatory markers.
Reference Ranges, Units, and Meaning
Standard CRP is commonly reported in mg/L. Some laboratories use an upper reference limit near 5 mg/L; others use 8 or 10 mg/L. High-sensitivity CRP uses the same analyte but is optimized for low cardiovascular-risk ranges and is not required for routine RA assessment.
Results are best divided into three practical questions: Is the value outside this laboratory’s range? Is it meaningfully different from the person’s usual value? Does the change match the clinical picture? Small moves around the upper limit may reflect normal biological and analytical variation. A large rise accompanied by new swollen joints, fever, or systemic symptoms carries more weight.
How CRP Relates to RA Flares and Disease Activity
C-reactive protein (CRP) contributes to composite RA scores, including versions of DAS28. Yet no blood marker defines a flare on its own. A flare is a clinically important worsening in inflammation, symptoms, function, or all three. The result may support that conclusion when it rises at the same time as objective synovitis.
Timing matters. CRP may already be changing while symptoms are evolving and can fall rapidly after corticosteroids or effective treatment. A sample drawn shortly after medication, during an infection, or weeks after symptoms began may not mirror the patient’s worst day.
Common Reasons for a High Result
CRP can rise with bacterial or viral infection, tissue injury, surgery, inflammatory bowel disease, vasculitis, obesity, and some cancers. Very high values—especially above 100 mg/L—should prompt careful assessment for infection or major inflammation rather than automatic attribution to RA.
When a person taking immunosuppressive therapy has a new high result, infection must remain on the list even if joints hurt. Fever, chills, cough, urinary symptoms, skin infection, or one intensely hot joint needs prompt medical review. The synovial fluid culture test may be critical when septic arthritis is possible.
Why Active RA Can Occur With a Normal Result
Genetics, body composition, liver response, cytokine pattern, medication, and localized rather than systemic synovitis can all produce normal CRP. Ultrasound may reveal power-Doppler activity even when CRP is low.
Clinicians therefore examine joints rather than treating a laboratory target in isolation. Ultrasound or MRI may help when pain, stiffness, and examination disagree with the blood work. Conversely, a high result with no swollen joints should trigger a search for non-RA causes instead of automatic escalation of DMARD therapy.
Using the Test to Monitor Treatment
The most useful pattern is a consistent baseline, followed by repeat measurement at clinically meaningful visits. A decline that accompanies fewer swollen joints and better function supports treatment response. A persistent elevation may reflect uncontrolled RA, infection, another inflammatory disease, or a noninflammatory confounder.
CRP is commonly combined with the other acute-phase marker. The ESR test for rheumatoid arthritis can provide complementary timing and context. Neither should replace medication safety monitoring such as blood counts and liver tests.
Preparation and Practical Next Steps
Fasting is usually unnecessary. Tell the clinician about infection symptoms, recent vaccination, surgery, injury, pregnancy, anemia, kidney disease, and corticosteroid use. Whenever possible, use the same laboratory to make trends easier to compare.
Contact the care team when the value rises substantially, symptoms worsen, or the result conflicts with how the joints look and feel. Seek urgent assessment for fever with a hot swollen joint, severe shortness of breath, chest pain, confusion, or rapidly worsening illness. The goal is not to normalize one number at all costs; it is to control inflammatory disease safely while identifying other causes of abnormal results.
Detailed Questions About CRP
How much day-to-day variation is normal?
A small change near the reference limit may not represent a true flare. Hydration, minor illness, collection timing, and normal analytical variation can all contribute. The larger and more sustained the change, the more likely it is to matter—especially when swollen joints and function worsen at the same time. Clinicians usually avoid reacting to a single modest increase without confirming the clinical context.
Can pain be severe while CRP is normal?
Yes. Pain intensity and systemic inflammation are related but not identical. Active synovitis can occur with normal markers, and noninflammatory pain from osteoarthritis, tendon injury, nerve irritation, fibromyalgia, sleep disruption, or previous joint damage can be intense. This is why a treatment visit should include examination and functional questions instead of relying only on the laboratory dashboard.
Can CRP remain high when the joints feel better?
Yes. The marker may lag behind improvement, or another condition may be driving it. Infection, obesity, anemia, kidney disease, dental inflammation, and inflammatory conditions outside the joints can all contribute, depending on the test. Persistent elevation deserves explanation, but it does not automatically mean the current RA medicine has failed.
How often should it be checked?
There is no single interval for everyone. During active disease or a treatment change, clinicians may measure inflammatory markers every one to three months along with safety laboratories and examination. Once disease is stable, testing may be spaced farther apart. More frequent checks are justified by symptoms, medication risks, or a specific concern—not by a need to chase normal variation.
Does a very high result require urgent care?
The number alone does not define an emergency, but a very high result combined with fever, shaking chills, low blood pressure, confusion, shortness of breath, or one hot swollen joint requires urgent assessment. People receiving steroids, biologics, or JAK inhibitors may have muted infection symptoms, so a sudden unexplained rise deserves prompt contact with the care team.
Can lifestyle changes lower CRP?
Regular activity, adequate sleep, smoking cessation, weight management when appropriate, and a balanced dietary pattern can improve overall inflammatory health. These measures support RA care but do not replace disease-modifying treatment. A lower laboratory value is not the only goal; preserving mobility, preventing joint damage, and reducing cardiovascular and infection risk matter as well.
What should be recorded between appointments?
Track the duration of morning stiffness, visible swelling, nighttime symptoms, grip or walking difficulty, fever or infection symptoms, and timing of medication doses. Note whether symptoms improve after movement or rest. This brief record helps explain whether a change in CRP reflects an RA flare, another illness, or a temporary fluctuation and makes the next clinical decision more precise.
References
- 2021 American College of Rheumatology Guideline for the Treatment of Rheumatoid Arthritis 2021 (Guideline)
- EULAR recommendations for the management of rheumatoid arthritis with synthetic and biological disease-modifying antirheumatic drugs: 2022 update 2023 (Guideline)
- Biomarkers in the diagnosis, prognosis and management of rheumatoid arthritis: a comprehensive review 2024 (Review)
- 2022 American College of Rheumatology Guideline for Exercise, Rehabilitation, Diet, and Additional Integrative Interventions for Rheumatoid Arthritis 2023 (Guideline)
Disclaimer
This article is general education about C-reactive protein (CRP) in rheumatoid arthritis and is not a diagnosis or treatment plan. Results must be interpreted with symptoms, examination, medicines, and the laboratory reference range. Fever with a hot swollen joint or severe systemic illness requires urgent medical assessment.