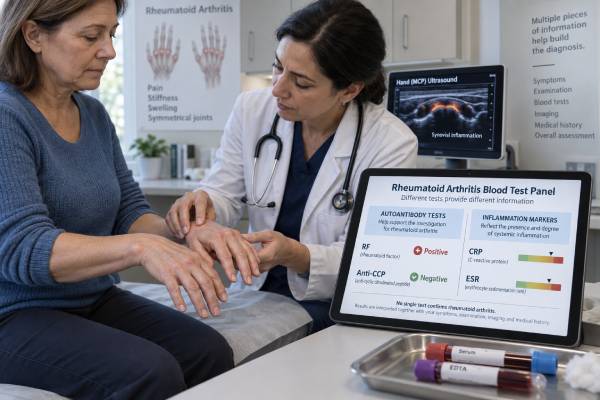
A rheumatoid arthritis blood test panel helps answer two different questions: whether the immune pattern supports rheumatoid arthritis and whether inflammation is active. Rheumatoid factor (RF) and anti-cyclic citrullinated peptide (anti-CCP) antibodies support the diagnosis and can add prognostic information. C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) reflect inflammation but are not specific to rheumatoid arthritis.
No blood panel can diagnose rheumatoid arthritis by itself. Some people with clear rheumatoid arthritis have negative RF and anti-CCP results, while RF can be positive in infections, other autoimmune diseases, and healthy older adults. CRP and ESR may also stay normal despite swollen joints. Doctors combine the panel with the location and duration of joint swelling, morning stiffness, physical examination, imaging, and exclusion of other causes. Because early treatment can prevent permanent damage, persistent swelling in the small joints of the hands or feet deserves prompt assessment even when the first laboratory results look reassuring.
- RF and anti-CCP support rheumatoid arthritis, but anti-CCP is generally more specific for the disease.
- CRP and ESR show inflammation; they cannot identify rheumatoid arthritis as the cause.
- Negative RF and anti-CCP results do not rule out seronegative rheumatoid arthritis.
- Reference ranges and positive cutoffs vary by laboratory, so interpret each value against the report.
- Persistent joint swelling, especially in several hand or foot joints, warrants timely rheumatology referral regardless of blood-test results.
Table of Contents
- What the Rheumatoid Arthritis Panel Includes
- How to Interpret Rheumatoid Factor
- How to Interpret Anti-CCP Antibodies
- What CRP and ESR Add
- Common Result Patterns and Their Meaning
- How Rheumatoid Arthritis Is Actually Diagnosed
- Preparation, Follow-Up, and When to Seek Care
What the Rheumatoid Arthritis Panel Includes
A typical rheumatoid arthritis blood panel contains four core tests, although the exact order set varies by clinic and laboratory.
| Test | What it measures | Main clinical role |
|---|---|---|
| Rheumatoid factor (RF) | An autoantibody, usually directed against part of IgG | Supports diagnosis and helps estimate prognosis |
| Anti-CCP antibody | Antibodies to citrullinated proteins or peptides | More specific support for RA; may indicate erosive risk |
| CRP | A liver-made acute-phase protein | Tracks current systemic inflammation relatively quickly |
| ESR | How fast red blood cells settle in a tube | Provides a broad, slower-changing inflammation signal |
The panel is often expanded. A complete blood count can identify anemia, high platelets, low white cells, or another clue to infection or systemic disease. A comprehensive metabolic panel establishes kidney and liver function before certain medications. Antinuclear antibodies may be useful when lupus or another connective tissue disease is possible. Uric acid and joint-fluid testing may be considered when gout is in the differential diagnosis.
Blood tests answer only part of the diagnostic question. Rheumatoid arthritis is defined by persistent inflammatory synovitis, not by antibody status alone. A person with high anti-CCP but no swollen joints does not automatically have rheumatoid arthritis. Conversely, someone with several persistently swollen joints may have rheumatoid arthritis even when all four panel results are normal.
The most informative use of the panel is targeted testing after a clinical history and examination. Symptoms that make inflammatory arthritis more likely include visible or palpable joint swelling, morning stiffness lasting 30 to 60 minutes or longer, difficulty making a fist on waking, symmetrical involvement of wrists or finger joints, and symptoms lasting more than six weeks.
Test performance depends on who is being tested. In a rheumatology clinic where persistent inflammatory arthritis is common, a positive antibody result has more diagnostic value than it does in a low-risk population with nonspecific aches. Sensitivity describes how often a test is positive in people who have the disease; specificity describes how often it stays negative in people who do not. Anti-CCP generally has higher specificity than RF, but neither has perfect sensitivity. CRP and ESR have even lower disease specificity because many illnesses can activate the acute-phase response.
How to Interpret Rheumatoid Factor
Rheumatoid factor is an autoantibody. Most clinical assays measure the IgM form, which binds to the Fc portion of immunoglobulin G. The laboratory may report RF in international units per milliliter (IU/mL) with a cutoff such as less than 14 or less than 20 IU/mL, but the exact reference range depends on the method.
A positive RF means the concentration exceeds the laboratory’s cutoff. In a person with persistent small-joint synovitis, positivity strengthens the case for rheumatoid arthritis. Higher values—particularly levels more than three times the upper limit of normal—carry more diagnostic weight in classification systems and may be associated with a greater likelihood of erosive disease, nodules, or extra-articular complications.
RF is not specific to rheumatoid arthritis. It can occur with:
- Sjögren syndrome, lupus, mixed connective tissue disease, or vasculitis
- Chronic infections such as hepatitis C, endocarditis, or tuberculosis
- Certain lung, liver, and blood disorders
- Some cancers
- Older age
- No identifiable disease
A low-positive value near the cutoff therefore means much less than a high value in a patient with a classic joint pattern. This is why a rheumatoid factor test should never be interpreted without clinical context.
A negative RF does not exclude rheumatoid arthritis. Roughly one-quarter to one-third of patients may be RF-negative at presentation, depending on the population and disease stage. Some later become positive; others remain negative. Repeating RF frequently is usually not useful once the diagnosis and serologic status are established because the value does not reliably track day-to-day disease activity.
RF can add prognostic information, but treatment should not be based on the number alone. A patient with high RF and no active synovitis does not need therapy intensified merely to lower RF. The treatment target is remission or low disease activity, assessed through symptoms, examination, function, and suitable inflammatory measures.
How to Interpret Anti-CCP Antibodies
Anti-CCP is a laboratory test for antibodies against citrullinated proteins. Citrullination is a normal chemical modification in which the amino acid arginine is changed to citrulline. In susceptible people, inflammation can lead the immune system to recognize citrullinated proteins as targets.
Anti-CCP belongs to the broader family of anti-citrullinated protein antibodies, or ACPA. Most current assays use second- or third-generation cyclic citrullinated peptides. The report may list the result in units per milliliter and classify it as negative, weak positive, moderate positive, or strong positive. Cutoffs are assay-specific.
A positive anti-CCP result is more specific for rheumatoid arthritis than RF. In a patient with appropriate joint swelling, it can strongly support the diagnosis. Anti-CCP may appear years before clinical arthritis, but a positive result in someone without synovitis predicts risk rather than certainty. Not everyone with the antibody develops rheumatoid arthritis.
Higher anti-CCP levels and combined RF/anti-CCP positivity are associated with a higher average risk of erosive joint damage. Smoking, periodontal inflammation, genetic susceptibility, and mucosal immune changes may contribute to the development of ACPA-positive disease. Still, antibody level cannot forecast an individual outcome with precision.
A negative anti-CCP result lowers the likelihood of classic seropositive rheumatoid arthritis but does not rule out the disease. Early disease, seronegative rheumatoid arthritis, assay differences, and biologic variation all matter. A clinician may rely more heavily on the swollen-joint pattern and ultrasound or MRI when anti-CCP is negative.
The anti-CCP antibody test is primarily diagnostic and prognostic. It is not normally repeated to monitor treatment because titers may remain positive even when inflammation is well controlled. A falling anti-CCP value is not required for remission.
When RF and anti-CCP disagree, anti-CCP usually carries more disease-specific information. However, an isolated anti-CCP result should be checked for strength, assay cutoff, symptoms, and possible alternative conditions. Rare positive results can occur in other autoimmune or lung diseases and some infections.
What CRP and ESR Add
CRP and ESR are acute-phase reactants. They help estimate inflammatory activity but cannot tell where inflammation comes from.
CRP is produced by the liver after stimulation by cytokines such as interleukin-6. It can rise within hours and decline relatively quickly when inflammation improves. Standard CRP is commonly reported in mg/L. Many laboratories consider values below about 3 to 10 mg/L within range, but the cutoff varies. High-sensitivity CRP is designed mainly for cardiovascular-risk assessment and should not be confused with the standard inflammatory CRP used in rheumatology.
ESR measures how many millimeters red blood cells fall in one hour, reported as mm/hr. Inflammation raises proteins such as fibrinogen, causing red cells to clump and settle faster. ESR changes more slowly than CRP and is affected by factors unrelated to inflammatory arthritis.
| Feature | CRP | ESR |
|---|---|---|
| Response speed | Rises and falls relatively quickly | Often changes more slowly |
| Common confounders | Infection, obesity, tissue injury, liver response | Age, anemia, pregnancy, kidney disease, immunoglobulins |
| Normal result | Does not exclude active RA | Does not exclude active RA |
| Main value | Current systemic inflammation and monitoring | Broader inflammatory context and some activity scores |
Elevated CRP or ESR can support active inflammatory arthritis when the examination shows synovitis. They may also rise because of infection, inflammatory bowel disease, obesity, malignancy, tissue injury, or another autoimmune condition. A sudden large increase in a patient whose joints are stable should raise concern for infection or another new cause rather than being labeled an arthritis flare automatically.
Normal values are common in rheumatoid arthritis. Some patients have active swollen joints with consistently normal acute-phase reactants. Others take medications that suppress the laboratory signal. Clinical disease-activity tools that do not require a lab result, such as the Clinical Disease Activity Index, can help when CRP or ESR is discordant.
For detailed interpretation, see the separate guides to CRP in rheumatoid arthritis and ESR in rheumatoid arthritis.
Common Result Patterns and Their Meaning
Looking at the pattern is more useful than labeling each test “good” or “bad.”
| RF | Anti-CCP | CRP/ESR | Possible interpretation |
|---|---|---|---|
| Positive | Positive | High | Strong support for seropositive RA with active systemic inflammation when synovitis is present |
| Positive | Positive | Normal | RA remains likely; activity may be limited, treated, or not reflected by acute-phase reactants |
| Positive | Negative | Variable | RA is possible, but alternative causes of RF should be considered |
| Negative | Positive | Variable | Anti-CCP can strongly support RA despite negative RF |
| Negative | Negative | High | Seronegative inflammatory arthritis, infection, crystal disease, or another inflammatory condition is possible |
| Negative | Negative | Normal | RA is less supported by blood tests but still possible if persistent synovitis is present |
A double-positive result is not the same as a diagnosis in the absence of joint inflammation. Preclinical autoimmunity can exist for years, and some people never progress. Likewise, a fully negative panel should not delay referral when several joints are visibly swollen.
Borderline results need restraint. A weakly positive RF or anti-CCP may be repeated if the laboratory suspects interference, the clinical picture is unclear, or a different assay is needed. Repeating every few weeks rarely adds value. Trends in CRP and ESR are more useful for monitoring than trends in RF or anti-CCP.
How Rheumatoid Arthritis Is Actually Diagnosed
Diagnosis begins with confirming synovitis—soft, often tender swelling caused by inflammation inside a joint. Typical sites include the wrists, metacarpophalangeal joints at the knuckles, proximal interphalangeal joints in the middle of the fingers, and metatarsophalangeal joints in the forefoot. The end finger joints are usually spared.
The clinician considers:
- Joint distribution and number. More small joints and symmetrical involvement increase suspicion.
- Duration. Symptoms lasting six weeks or longer are more consistent with persistent inflammatory arthritis, but treatment should not be withheld while waiting for a time threshold.
- Serology. RF and anti-CCP are weighted by whether they are low or high positive.
- Acute-phase response. Abnormal CRP or ESR adds support.
- Alternative diagnoses. Psoriatic arthritis, lupus, viral arthritis, gout, osteoarthritis, polymyalgia rheumatica, and infection must be considered.
The 2010 ACR/EULAR classification criteria use these domains to identify patients likely to have rheumatoid arthritis for research and clinical consistency. They are helpful but are not a substitute for judgment. A patient can be diagnosed before meeting a score, and someone can meet a score yet ultimately have another condition.
Ultrasound can detect synovial thickening, power Doppler activity, tendon-sheath inflammation, and erosions. MRI is sensitive but less commonly needed for routine diagnosis. Plain X-rays establish a structural baseline but may be normal early. Imaging is particularly valuable when the examination is uncertain or blood tests are negative.
Rapid referral matters because joint damage can begin early. Primary care should not wait for positive RF, anti-CCP, or X-ray erosions before referring persistent synovitis. Disease-modifying antirheumatic drugs work best when started promptly after specialist assessment.
Preparation, Follow-Up, and When to Seek Care
The panel requires blood drawn from a vein. Fasting is usually unnecessary, although a laboratory may bundle other tests that do require fasting. Tell the clinician about medications, supplements, recent infections, pregnancy, anemia, and chronic liver or kidney disease because these can affect interpretation.
Before the appointment, write down:
- Which joints swell and whether swelling is visible
- How long morning stiffness lasts
- When symptoms began and whether they are continuous or episodic
- Photos of swelling that comes and goes
- Family history of rheumatoid arthritis, psoriasis, lupus, or inflammatory bowel disease
- Smoking history and recent infections
- Medicines that improve or mask symptoms, including steroids
After testing, the next step depends on the pattern rather than one number. Positive anti-CCP with persistent swelling usually supports rheumatology evaluation. Negative antibodies with convincing synovitis may lead to ultrasound, repeat examination, or evaluation for seronegative disease. High CRP or ESR without swollen joints calls for a broader search for infection or another inflammatory source.
A routine positive antibody result is not an emergency. Urgent assessment is needed for a hot, rapidly swollen joint with fever, severe illness, inability to bear weight, or suspected septic arthritis. Chest pain, new shortness of breath, neurologic symptoms, or eye pain and redness also require prompt care based on severity.
Once rheumatoid arthritis is diagnosed, RF and anti-CCP usually do not need frequent repetition. Follow-up focuses on swollen and tender joints, function, medication safety, CRP or ESR when informative, and a treat-to-target plan. The purpose of the panel is not to create a perfect laboratory profile. It is to help identify inflammatory arthritis early and guide the next clinical decision.
References
- Rheumatoid arthritis in adults: management 2024 (Guideline)
- Rheumatoid Factor (RF) Test 2025 (Official Page)
- CCP Antibody Test 2024 (Official Page)
- C-Reactive Protein (CRP) Test 2025 (Official Page)
- Erythrocyte Sedimentation Rate (ESR) 2024 (Official Page)
- Biomarkers in the diagnosis, prognosis and management of rheumatoid arthritis: A comprehensive review 2024 (Review)
Disclaimer
This article is for general education and does not diagnose rheumatoid arthritis. A qualified clinician must interpret RF, anti-CCP, CRP, and ESR with the joint examination, symptoms, imaging, and other health conditions. Seek urgent care for a hot swollen joint with fever or severe illness because joint infection can cause rapid damage.