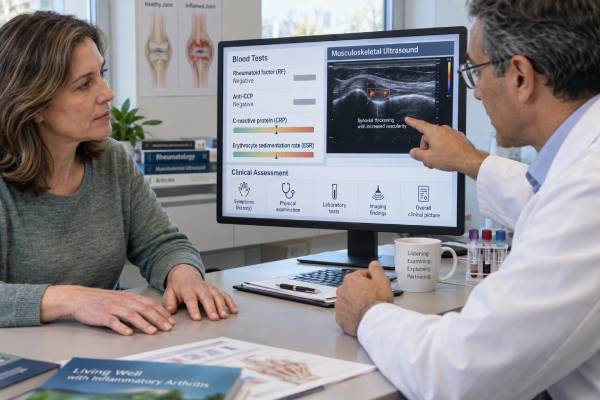
Seronegative rheumatoid arthritis means a person has rheumatoid arthritis without detectable rheumatoid factor (RF) or anti-citrullinated protein antibodies, usually measured by an anti-CCP test. Because the two best-known antibodies are absent, diagnosis depends more heavily on persistent synovitis, the pattern of affected joints, inflammation markers, imaging, and careful exclusion of other diseases.
CRP and ESR can support active inflammation, but normal values do not rule out seronegative rheumatoid arthritis. Ultrasound may show synovial thickening, power Doppler blood flow, tendon-sheath inflammation, or erosions before plain X-rays become abnormal. MRI can detect synovitis, bone marrow edema, and early structural damage when the diagnosis remains uncertain. No emerging blood marker has replaced clinical assessment or RF and anti-CCP in routine practice. The most important step is timely rheumatology evaluation for persistent joint swelling rather than waiting for a positive antibody result. Seronegative disease can still damage joints and deserves the same treat-to-target approach once the diagnosis is established.
- Seronegative rheumatoid arthritis usually means both RF and anti-CCP/ACPA are negative.
- Normal CRP and ESR do not exclude active synovitis or early joint damage.
- Ultrasound can confirm inflammation when swelling is subtle; MRI is useful for selected unresolved cases.
- Diagnosis requires excluding mimics such as psoriatic arthritis, gout, viral arthritis, lupus, and osteoarthritis.
- Persistent swelling in several small joints warrants prompt rheumatology referral even when all blood tests are negative.
Table of Contents
- What Seronegative Rheumatoid Arthritis Means
- Blood Tests Beyond RF and Anti-CCP
- CRP, ESR, and the Problem of Normal Results
- Ultrasound, X-Ray, and MRI Findings
- Conditions That Mimic Seronegative RA
- A Practical Diagnostic Pathway
- Monitoring, Treatment, and Outlook
What Seronegative Rheumatoid Arthritis Means
“Seronegative” describes laboratory status, not the absence of disease. In contemporary practice, the term generally means that both RF and anti-CCP, a common assay for anti-citrullinated protein antibodies, are negative. Some older records use seronegative to mean RF-negative alone, so it is worth checking which antibodies were actually tested.
Rheumatoid arthritis is an inflammatory disease of the synovium, the lining inside movable joints. Diagnosis rests on evidence of persistent inflammatory synovitis. Typical features include soft swelling of the wrists, knuckles, middle finger joints, or forefeet; prolonged morning stiffness; reduced grip; and a pattern that often affects both sides. The end joints nearest the fingernails are less typical.
Seronegative disease is not a single biologic category. Research suggests that antibody-negative patients may contain several immune and clinical subgroups, some closer to classic rheumatoid arthritis and others closer to different inflammatory syndromes. This heterogeneity explains why one proposed biomarker rarely performs well across every seronegative cohort and why careful phenotyping—joint distribution, imaging pattern, age at onset, and features outside the joints—matters so much.
Seronegativity can occur for several reasons:
- The person has a genuine rheumatoid arthritis subtype that does not produce RF or ACPA.
- Disease is very early and antibodies have not become detectable, although many patients remain negative permanently.
- The antibody concentration is below the assay cutoff.
- The clinical syndrome was initially labeled rheumatoid arthritis but later proves to be another inflammatory or non-inflammatory condition.
Estimates vary, but about 20% to 30% of patients with rheumatoid arthritis are negative for both major antibodies. The group is heterogeneous. Some have milder disease, while others develop persistent swelling, erosions, disability, and extra-articular problems. Seronegative should never be translated as “not serious.”
The diagnosis may evolve over time. A clinician may initially use terms such as undifferentiated inflammatory arthritis while observing the pattern, response, imaging, and emergence of new features. This is not necessarily diagnostic failure; several rheumatic diseases look similar during their earliest months.
Blood Tests Beyond RF and Anti-CCP
A seronegative evaluation begins by confirming that both standard antibodies were measured with appropriate assays. Borderline or unexpected results can occasionally be repeated, but frequent retesting is not a substitute for examination.
The blood panel often includes:
| Test | What it contributes | Main limitation |
|---|---|---|
| CRP | Current systemic inflammation | Can be normal in active RA and high from infection or obesity |
| ESR | Broad inflammatory signal | Affected by age, anemia, pregnancy, kidney disease, and immunoglobulins |
| Complete blood count | Anemia, high platelets, infection clues, alternative blood disorders | Changes are nonspecific |
| Kidney and liver tests | Alternative causes and treatment baseline | Do not diagnose RA |
| ANA and targeted autoantibodies | Evaluate lupus, Sjögren syndrome, or connective tissue disease when indicated | Positive ANA is common and may be incidental |
| Uric acid | Provides context for gout risk | Cannot confirm or exclude gout during an attack |
Additional proposed markers include 14-3-3 eta protein, anti-carbamylated protein antibodies, anti-mutated citrullinated vimentin, calprotectin, matrix metalloproteinase-3, and multi-protein algorithms. Some can identify a subset of antibody-negative patients or add prognostic information in studies. Their performance varies by population and assay, and no single marker is sufficiently validated to replace the established diagnostic process.
The 14-3-3 eta protein test, for example, may be specific when positive in selected settings but can have limited sensitivity in strictly double-seronegative patients. A negative result therefore offers little reassurance. The same principle applies to many emerging biomarkers: promising group statistics do not guarantee a useful answer for one patient.
Infection testing should be targeted. Parvovirus B19, hepatitis B or C, HIV, tuberculosis, Lyme disease, and other infections can produce joint symptoms in the right epidemiologic setting. Broad indiscriminate panels increase false positives; exposure history and symptom pattern should guide selection.
CRP, ESR, and the Problem of Normal Results
CRP and ESR are useful because they can show inflammation even when RF and anti-CCP are absent. However, they are neither sensitive enough nor specific enough to decide the diagnosis alone.
CRP is a liver-made acute-phase protein that can change rapidly. ESR is the rate at which red blood cells settle in a tube and usually changes more slowly. Both may rise with rheumatoid synovitis, infection, inflammatory bowel disease, cancer, tissue injury, or another autoimmune condition.
A patient can have one of four broad patterns:
- High CRP and ESR: supports systemic inflammation but does not identify the source.
- High CRP with normal ESR: can occur early in an inflammatory process or when ESR is affected by blood-cell factors.
- Normal CRP with high ESR: may reflect anemia, age, kidney disease, immunoglobulins, or slower residual inflammation.
- Both normal: lowers evidence for systemic inflammation but does not exclude localized or biologically “low-marker” synovitis.
Normal markers can delay diagnosis when clinicians equate rheumatoid arthritis with an abnormal blood panel. Some patients consistently produce little acute-phase response. Others have only a few inflamed joints, use anti-inflammatory medication, or are examined between flares. Ultrasound becomes particularly valuable when the physical examination suggests swelling but the blood tests are quiet.
CRP and ESR are more informative as trends after diagnosis if they previously tracked the patient’s disease. A person whose markers remain normal during every documented flare should be monitored primarily with joint counts, symptoms, function, and selected imaging. For further detail, see CRP monitoring in rheumatoid arthritis and ESR monitoring in rheumatoid arthritis.
A sudden high CRP or ESR with fever, weight loss, or symptoms outside the usual joint pattern should prompt evaluation for infection or another illness before escalating immunosuppression.
Ultrasound, X-Ray, and MRI Findings
Imaging does not replace clinical judgment, but it can provide objective evidence when serology is negative.
Plain X-rays of hands and feet establish a baseline and can show joint-space narrowing or marginal erosions. Early rheumatoid arthritis may have normal X-rays because structural damage has not yet developed. A normal film therefore does not rule out active inflammatory disease.
Musculoskeletal ultrasound can detect:
- Synovial hypertrophy, meaning thickened joint lining
- Joint effusion
- Power Doppler blood flow that supports active inflammation
- Tenosynovitis around tendons
- Small erosions not visible on plain films
Ultrasound is dynamic, allows comparison of several joints in one visit, and can guide aspiration or injection. Its accuracy depends on equipment, scanning protocol, operator skill, and interpretation. Mild gray-scale changes can occur in healthy people or osteoarthritis, so power Doppler and the clinical pattern matter.
MRI is highly sensitive for synovitis, tenosynovitis, bone marrow edema—also called osteitis—and erosions. Bone marrow edema in early inflammatory arthritis can predict later structural damage at a group level. MRI may help when deep or complex joints are involved, ultrasound is inconclusive, or diagnosis remains uncertain despite persistent symptoms.
MRI also detects abnormalities that are not rheumatoid arthritis. Mechanical stress, age, trauma, and healthy variation can produce findings. Imaging a painful area without a clear diagnostic question can generate incidental results and overdiagnosis.
CT and nuclear medicine imaging have limited routine roles in early rheumatoid arthritis. CT shows bone well but exposes the patient to radiation and is less useful for active synovitis. PET and other specialized methods are generally research or problem-solving tools.
The best modality depends on the question. If several small joints feel swollen but X-rays are normal, ultrasound may be the most practical next step. If symptoms are persistent and ultrasound is unavailable or conflicting, MRI may add value. If a single joint is hot and acutely swollen, aspiration is usually more urgent than advanced imaging.
Conditions That Mimic Seronegative RA
The central diagnostic challenge is not proving that antibodies are absent. It is identifying which disease explains the synovitis.
Psoriatic arthritis may involve finger or toe swelling, nail pitting, psoriasis hidden in the scalp or skin folds, tendon-attachment pain, and end finger joints. Psoriasis can appear after arthritis, so family history and nail examination matter.
Peripheral spondyloarthritis often causes asymmetric lower-limb arthritis, heel enthesitis, dactylitis, uveitis, inflammatory back pain, inflammatory bowel disease, or a preceding infection. HLA-B27 may support selected cases but is not a general screening answer.
Crystal arthritis includes gout and calcium pyrophosphate deposition disease. Either can affect several joints and mimic rheumatoid arthritis, particularly in older adults. Crystal identification in synovial fluid is the key test when an accessible joint is swollen.
Viral arthritis can be abrupt and symmetrical. Parvovirus, hepatitis viruses, chikungunya, and other infections are considered according to exposures, geography, rash, fever, and liver findings. Many viral syndromes resolve, while rheumatoid arthritis persists.
Lupus and other connective tissue diseases may cause inflammatory joint symptoms alongside rash, photosensitivity, mouth ulcers, Raynaud phenomenon, low blood counts, kidney findings, dry eyes or mouth, or muscle weakness. Targeted autoantibodies are chosen from the full pattern.
Osteoarthritis causes bony enlargement and pain that often worsens with use, but inflammatory flares and hand involvement can resemble RA. Ultrasound can distinguish bony change from active synovitis, though both diseases can coexist.
Polymyalgia rheumatica affects older adults with shoulder and hip girdle stiffness and usually high inflammatory markers. Peripheral swelling can occur. Age, distribution, ultrasound, and treatment response help distinguish it from elderly-onset RA.
Other mimics include sarcoidosis, palindromic rheumatism, hemochromatosis, thyroid disease, medication reactions, paraneoplastic arthritis, and infection. Atypical features—marked fever, one dominant hot joint, rash, muscle weakness, severe weight loss, or prominent back/heel symptoms—should widen the differential.
A Practical Diagnostic Pathway
A thoughtful pathway prevents both delayed treatment and overdiagnosis.
- Confirm objective inflammation. The clinician looks for soft synovial swelling, warmth, restricted movement, tenosynovitis, or a reproducible inflammatory pattern.
- Map the joint distribution. Small-joint symmetry supports RA, while end-joint disease, dactylitis, enthesitis, or dominant axial symptoms suggest alternatives.
- Establish duration and tempo. Persistent symptoms beyond six weeks increase concern, but rapid referral should not wait for a calendar threshold when swelling is clear.
- Verify RF and anti-CCP status. Review actual values, assay cutoffs, and whether both tests were performed.
- Measure inflammation and baseline health. CRP, ESR, blood count, kidney, and liver tests provide context and prepare for treatment.
- Use targeted tests for mimics. ANA-related testing, infection studies, HLA-B27, thyroid tests, or iron studies should follow clinical clues.
- Obtain imaging when it can resolve uncertainty. X-rays provide baseline structure; ultrasound or MRI can demonstrate active inflammation.
- Aspirate an acutely swollen joint when possible. Cell count, crystals, Gram stain, and culture can identify urgent alternatives.
- Reassess over time. The diagnosis may become clearer through persistence, new features, imaging progression, or response—not through response alone—to appropriate therapy.
Classification criteria can support a consistent assessment, but seronegative patients may score fewer points because they receive no serology points. A rheumatologist can diagnose rheumatoid arthritis even when formal classification criteria are not met, provided the overall evidence is convincing and another diagnosis fits less well.
This distinction between classification and diagnosis is especially important in antibody-negative disease. Classification criteria are built to create relatively uniform research groups and favor specificity. Clinical diagnosis must also protect an individual from the harm of delayed treatment. A rheumatologist may reasonably treat persistent, imaging-confirmed small-joint synovitis as rheumatoid arthritis while continuing to watch for psoriasis, bowel disease, crystals, infection, or another feature that changes the label. The diagnosis should remain open to revision when new evidence appears.
Do not use a steroid response as proof of RA. Many inflammatory diseases improve with glucocorticoids, and even some non-inflammatory pain can feel temporarily better. Response is one clue, not a disease-specific test.
Monitoring, Treatment, and Outlook
Once seronegative rheumatoid arthritis is diagnosed, treatment principles are the same as for seropositive disease: begin an appropriate disease-modifying antirheumatic drug, measure disease activity, and adjust therapy toward remission or low disease activity.
RF and anti-CCP do not need frequent repetition. Monitoring focuses on swollen and tender joints, function, CRP or ESR when informative, a composite score, and medication-safety tests. Ultrasound may help when symptoms and examination conflict, but routine scanning of every stable patient is not required.
Seronegative disease has often been described as milder, but outcomes are mixed. Some cohorts show less radiographic progression on average; others show substantial disease burden and delayed treatment because negative tests falsely reassure clinicians. Prognosis depends on persistent inflammation, erosions, functional loss, smoking, comorbidities, and how quickly effective control is achieved.
Patients can improve the quality of follow-up by photographing visible swelling, recording morning stiffness and function, and noting whether symptoms involve joints, tendons, heels, skin, eyes, or bowel. New psoriasis or nail changes can substantially alter the diagnostic picture.
Seek urgent care for a single intensely painful, hot swollen joint with fever or systemic illness because septic arthritis can destroy a joint quickly. New inability to bear weight, severe weakness, chest pain, shortness of breath, or neurologic symptoms also require prompt assessment.
The absence of antibodies removes two useful clues, but it does not make diagnosis impossible. Persistent synovitis, an appropriate joint pattern, objective imaging, and exclusion of mimics can provide a strong foundation for treatment.
References
- A cohort study of ultrasonic semi-quantitative scoring for the diagnosis of seronegative rheumatoid arthritis 2024 (Clinical Study)
- Rheumatoid arthritis in adults: management 2024 (Guideline)
- Seronegative Rheumatoid Arthritis: A Distinct Immunopathological Entity with Erosive Potential 2025 (Review)
- Rheumatoid Arthritis: Biomarkers and the Latest Breakthroughs 2025 (Review)
- Serum and urine lipidomic profiles identify biomarkers associated with seronegative rheumatoid arthritis 2024 (Clinical Study)
- Evaluation of 14-3-3eta protein as a diagnostic biomarker in rheumatoid arthritis 2024 (Clinical Study)
Disclaimer
This article is for general education and cannot determine whether a person has seronegative rheumatoid arthritis. Diagnosis requires a clinician to confirm synovitis, review imaging and laboratory results, and exclude infection, crystals, and other rheumatic diseases. A hot swollen joint with fever or severe illness requires urgent medical evaluation.