
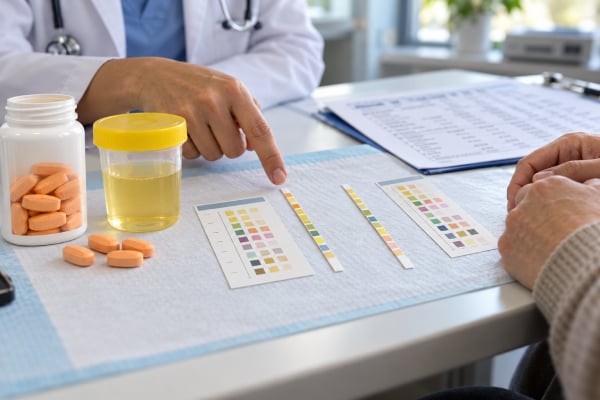
A urine ascorbic acid test detects vitamin C in urine mainly so laboratories can recognize possible interference with other dipstick results. Vitamin C is a strong reducing agent, and at sufficient urinary concentrations it can weaken color reactions used by some reagent strips. Depending on the strip design, this can produce false-negative or falsely low results for blood, glucose, nitrite, bilirubin, and sometimes leukocyte esterase. The effect is not identical across manufacturers because modern strips use different chemistries and interference protection. A positive urine vitamin C pad does not diagnose vitamin C deficiency or excess and does not measure blood vitamin C status. Its practical value is quality control: if ascorbic acid is present and another dipstick result seems inconsistent with symptoms, microscopy or a more specific laboratory test may be needed before concluding the urine is normal.
- What the test means: A positive urine ascorbic acid pad shows vitamin C is present at or above the strip’s threshold; it is primarily an interference warning, not a disease diagnosis.
- Most important risk: Vitamin C can cause false-negative or weaker reactions for blood and glucose on susceptible dipsticks and may also affect nitrite, bilirubin, or leukocyte esterase.
- Interference is strip-specific: Some modern reagent strips are designed to resist ascorbic acid better than others, so the laboratory method matters.
- Supplements can raise urinary vitamin C: Even ordinary oral supplements can increase urinary ascorbic acid, while high-dose therapy can produce much higher concentrations.
- What to do with a mismatch: If symptoms or microscopy conflict with a negative dipstick, confirm the suspected marker rather than relying on the strip alone.
Table of Contents
- What the Urine Ascorbic Acid Test Measures
- How Vitamin C Causes Dipstick Interference
- Which Dipstick Markers Can Be Affected
- Supplements, Dose, and Timing
- How to Interpret a Positive Ascorbic Acid Result
- What the Test Cannot Tell You
- How Laboratories Reduce False-Negative Errors
- What to Do if Results Do Not Match Symptoms
What the Urine Ascorbic Acid Test Measures
Ascorbic acid is vitamin C, a water-soluble nutrient. The body absorbs vitamin C from food and supplements, uses what it needs, and excretes excess amounts through the kidneys. Urinary vitamin C therefore varies with recent intake, timing, kidney handling, and hydration.
Some multiparameter urine strips include a dedicated ascorbic acid pad. The pad is not part of every urinalysis system, and reporting differs by manufacturer. Results may be qualitative, such as negative or positive, or semiquantitative in concentration ranges.
There is no universal “normal urine vitamin C range” that is clinically interpreted like urine protein or glucose. A positive result often simply means enough ascorbic acid is present to potentially alter other reagent reactions. The threshold at which that matters depends on the strip.
This is different from a nutritional vitamin C test. If a clinician needs to assess vitamin C deficiency or systemic exposure, urine dipstick ascorbic acid is not the standard diagnostic tool. Its role in routine urinalysis is primarily to warn that certain chemical pads may be less reliable.
A broader urinalysis with dipstick and microscopy can help resolve the problem because microscopy detects cells directly rather than through the same oxidation-reduction chemistry used by some dipstick pads.
How Vitamin C Causes Dipstick Interference
Vitamin C can interfere because it is a reducing agent—it readily donates electrons and can consume oxidizing chemicals needed to generate a visible color reaction. Many urine dipstick tests depend on precisely controlled oxidation or color-forming chemistry.
For example, many glucose pads use a glucose oxidase/peroxidase reaction. Glucose produces hydrogen peroxide, and the peroxide helps oxidize a chromogen to create color. Ascorbic acid can compete in this oxidation system and reduce the amount of color produced. If enough vitamin C is present, a urine sample containing glucose may appear less positive or even negative.
The blood pad commonly relies on the pseudoperoxidase activity of hemoglobin or myoglobin. Ascorbic acid can reduce the oxidized chromogen in susceptible systems, again weakening the expected color. This is why a dipstick can be negative for blood even when microscopy shows red blood cells.
Nitrite and bilirubin use different chemistries, but ascorbic acid can also suppress color formation on some strips. The exact concentration that causes interference is not universal because manufacturers use different reagents, buffers, protective compounds, and reading technologies.
Modern strips may include chemical modifications that make certain pads more resistant to vitamin C. Resistance is not absolute across all analytes or concentrations. The correct interpretation therefore depends on the exact strip used, not on a single vitamin C cutoff taken from another product.
Which Dipstick Markers Can Be Affected
The best-documented clinically important effects involve blood and glucose, but other markers can be affected depending on strip design.
| Dipstick marker | Possible vitamin C effect | Useful confirmation |
|---|---|---|
| Blood/hemoglobin | False-negative or weaker positive result | Urine microscopy for red cells; targeted testing for hemoglobin or myoglobin when needed |
| Glucose | False-negative or underestimated glucosuria | Blood glucose and laboratory urine glucose if clinically necessary |
| Nitrite | False-negative on susceptible strips | Symptoms, leukocytes, microscopy, and urine culture when indicated |
| Bilirubin | False-negative or reduced reaction on some strips | Serum bilirubin and liver tests; repeat urinalysis with suitable method |
| Leukocyte esterase | May be reduced in some systems or clinical specimens | Microscopic white blood cell count and culture when appropriate |
A multicenter clinical study found urinary vitamin C in 18.1% of more than 5,000 routine samples. Among vitamin C-positive clinical samples, the investigators reported false-negative rates of 42.3% for urine glucose, 10.6% for hemoglobin, and 8.2% for leukocyte esterase using the systems and definitions in that study. These percentages should not be applied to every laboratory because modern strip chemistry differs, but they illustrate why the interference can matter in real specimens.
The most important clue is discordance. If a patient has classic hematuria symptoms or microscopy shows red blood cells but the blood pad is negative, interference should be considered. Similarly, high blood glucose with a negative urine glucose strip can reflect urine timing, renal threshold differences, or chemical interference rather than proof that glucosuria is absent.
For blood specifically, the urine blood dipstick is already a screening test that requires context. Vitamin C adds another reason to confirm unexpected negative results with microscopy.
Supplements, Dose, and Timing
Urinary ascorbic acid can rise after vitamin C-rich food, drinks, multivitamins, dedicated vitamin C supplements, and high-dose intravenous therapy. The amount appearing in urine depends on absorption, recent intake, kidney function, and the time between ingestion and sample collection.
Older controlled studies showed that even modest oral vitamin C doses could produce urinary concentrations high enough to interfere with some glucose and blood strips available at the time. Newer products may be more resistant, but high urinary concentrations can still be relevant.
A positive ascorbic acid pad is therefore not surprising in someone who takes supplements. It does not necessarily mean the dose is excessive or unsafe. It means the laboratory should consider whether the detected concentration could affect that strip’s other reactions.
Timing matters because urinary vitamin C can change over hours. A person may have a positive ascorbic acid pad after recent supplementation and a negative result on another day. Hydration also changes the measured concentration by diluting or concentrating urine.
Do not stop a prescribed vitamin C regimen solely to “normalize” a urine strip. If repeat urinalysis is needed and supplement interference is suspected, ask the ordering clinician or laboratory whether temporary avoidance before collection is appropriate. This is especially important when vitamin C is being used as part of medical treatment rather than as an optional supplement.
High-dose intravenous vitamin C deserves separate caution because it can also interfere with some blood glucose meters and laboratory assays, not only urine strips. Clinicians should know about recent high-dose vitamin C exposure when interpreting unexpected point-of-care results.
How to Interpret a Positive Ascorbic Acid Result
A positive urine ascorbic acid result is best interpreted as an analytical flag. It answers the question, “Could vitamin C be present at a concentration that matters for this testing system?” It does not answer, “Does this person have too much vitamin C?”
The practical interpretation depends on the rest of the urinalysis:
- Positive ascorbic acid with otherwise normal urine and no symptoms: Often no action is needed beyond recognizing possible interference.
- Positive ascorbic acid plus negative blood despite red cells on microscopy: The blood pad may be falsely low; microscopy should take priority for hematuria confirmation.
- Positive ascorbic acid plus negative glucose despite marked hyperglycemia: Use blood glucose and, if needed, a laboratory method rather than the urine strip to assess glycemia.
- Positive ascorbic acid plus UTI symptoms and negative nitrite: Do not use nitrite alone to exclude infection; leukocyte esterase, microscopy, and culture may still support UTI.
- Positive ascorbic acid plus suspected bilirubinuria: Serum liver tests and a repeat or alternative urine method can clarify the discrepancy.
If the strip reports an ascorbic acid concentration, use the manufacturer’s interference table rather than a generic cutoff. Some analytes may remain reliable at a concentration that interferes with others.
The absence of a vitamin C pad does not guarantee the sample is free of ascorbic acid. Many strips do not measure it. When results are clinically implausible, interference remains a possibility even if the report does not mention vitamin C.
What the Test Cannot Tell You
A urine ascorbic acid pad is easy to overinterpret because it reports a familiar nutrient. It does not function as a nutritional-status test. Urinary excretion can rise rapidly after a supplement or vitamin C-rich meal even when blood and tissue status are normal. Conversely, a negative urine pad does not prove deficiency.
The test also cannot tell how much vitamin C was taken. Two people taking the same oral dose may produce different urine concentrations because absorption, kidney filtration, tubular handling, timing, and hydration vary. A concentrated morning sample can appear more strongly positive than a dilute sample collected after several glasses of water.
It cannot predict the exact size of interference without knowing the reagent strip. A urine vitamin C concentration that has little effect on one manufacturer’s blood pad may suppress another manufacturer’s reaction. Even within the same strip, glucose, blood, bilirubin, and nitrite can have different susceptibility thresholds. Laboratory package inserts and local validation data are therefore more useful than a single universal “interference level.”
A positive ascorbic acid pad also does not prove that another result is wrong. It only raises the possibility. If blood is strongly positive despite vitamin C, the result may still be valid because the analyte concentration overwhelms the interference. In contrast, low-level abnormalities are more easily masked. This helps explain why false negatives are especially concerning near a strip’s detection threshold.
Finally, the test cannot determine whether a symptom comes from vitamin C. Urinary burning, visible blood, fever, jaundice, or high glucose symptoms require ordinary clinical evaluation. The ascorbic acid result is most useful when it explains a laboratory mismatch, not when it is treated as the cause of the patient’s condition.
One practical way to use the result is as an interpretive flag. If the ascorbic acid pad is positive and every other urine marker fits the clinical picture, no special conclusion is needed. If a potentially affected marker is unexpectedly negative, however, the vitamin C result becomes more important. The next step is usually confirmation with a method that does not depend on the same reagent-strip reaction. This approach avoids two opposite errors: dismissing a true abnormality because the dipstick is negative, and assuming every negative result is false simply because vitamin C is present. The size of the mismatch, the patient’s symptoms, and the laboratory method should all be considered together.
This is especially important when a missed low-level abnormality could change diagnosis, follow-up, or treatment.
How Laboratories Reduce False-Negative Errors
Laboratories reduce vitamin C-related errors in several ways. The first is method selection. Some reagent strips contain protective chemistry designed to minimize ascorbic acid interference, while others include a dedicated ascorbate indicator.
The second is cross-checking chemistry with microscopy or blood tests. A negative blood pad with microscopic red blood cells is a clear discrepancy. A negative urine glucose result with high serum glucose is another. Laboratory rules can trigger review when these combinations occur.
The third is proper strip storage and timing. Reagent strips are sensitive to moisture, heat, air, and expiration. Automated readers improve consistency by reading each pad at the correct interval, but automation cannot fully correct chemical interference already occurring in the reaction.
Modern urinalysis guidelines emphasize understanding strip performance specifications and known interferences. Laboratories validate their own systems because interference claims can differ from one product to another. A 2022 point-of-care analyzer evaluation, for example, found a significant inhibitory effect of high ascorbate concentration on lower-level hemoglobin reactions, while stronger hemoglobin reactions were more resistant under the tested conditions.
More recent work also shows that ascorbic acid can interfere with some quantitative urine chemistry measurements beyond standard dipsticks. A 2025 laboratory study found significant interference with certain urine chloride, calcium, and magnesium measurements under its experimental conditions. This reinforces a broader rule: unexpected urine chemistry should be interpreted with knowledge of the analytical method and potential interferents.
What to Do if Results Do Not Match Symptoms
When a dipstick result conflicts with symptoms or other test data, confirm the clinical question instead of repeating the same assumption.
For suspected blood in urine, microscopy can determine whether red blood cells are present. For diabetes concerns, blood glucose and A1C are more reliable than urine glucose. For possible UTI, urinary symptoms, pyuria, and culture may be more informative than nitrite alone. For bilirubin concerns, serum bilirubin and liver enzymes provide direct systemic information.
Tell the clinician or laboratory about vitamin C supplements, multivitamins, fortified drinks, and especially recent high-dose or intravenous vitamin C. The exact dose and timing can help explain an unexpected result.
If repeat testing is planned, use a fresh, properly collected sample and follow any instructions about supplements. Do not make medication or supplement changes that were prescribed for a medical reason without discussing them with the treating clinician.
Seek prompt medical care when a possibly false-negative urine result is paired with concerning symptoms such as visible blood in urine, fever with flank pain, severe urinary symptoms, very high blood glucose with vomiting or dehydration, jaundice, or severe muscle pain with dark urine. The safety issue is not the vitamin C itself—it is the possibility that an important abnormality could be hidden by an analytical interference.
The urine ascorbic acid pad is therefore a small but useful quality-control marker. Its main purpose is to make negative dipstick results more trustworthy by identifying situations where “negative” may need a second look.
References
- Ascorbic acid and glucose can cause significant interference on quantitative measurement of biochemistry analytes in urine 2025
- The EFLM European Urinalysis Guideline 2023 2024 (Guideline)
- Performance evaluation of Hipee S2 point-of-care testing urine dipstick analyser: a cross-sectional study. 2022
- Urinalysis: Interpretation and Clinical Correlations 2023 (Review)
- Office-Based Urinalysis: A Comprehensive Review 2022 (Review)
- The influence of vitamin C on the urine dipstick tests in the clinical specimens: a multicenter study 2017
Disclaimer
A urine ascorbic acid result is an interference marker, not a diagnosis of vitamin C deficiency or toxicity. Dipstick performance varies by manufacturer, so unexpected results should be confirmed using the laboratory’s validated methods and the clinical context. Do not stop prescribed vitamin C therapy without guidance from the clinician managing it.





