
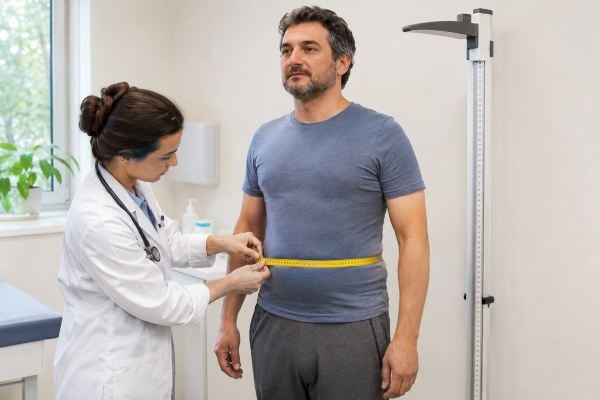
BMI tells you how much you weigh for your height. Waist-to-height ratio (WHtR) tells you where that weight is carried. For metabolic risk, location often matters more than total mass. By capturing central adiposity—the tendency to store fat around the abdomen—WHtR offers a sharper lens on health risks than BMI alone.
The rule is simple: keep your waist below half your height. A ratio under 0.5 suggests a lower risk of type 2 diabetes, metabolic syndrome, cardiovascular disease, and premature death. While “better” doesn’t mean BMI is obsolete, the two metrics work best in tandem. BMI remains a practical screen for overall body size, while WHtR highlights central fat accumulation. A person can have a normal BMI yet a high WHtR, indicating hidden metabolic risk. Conversely, a muscular individual may have a high BMI without excess abdominal fat. Measuring your waist correctly and tracking the trend over time can reveal changes that the scale alone misses.
Table of Contents
- What Waist-to-Height Ratio Measures
- How to Calculate It Correctly
- What the Numbers Mean
- Waist-to-Height Ratio vs BMI
- Why Central Fat Matters for Blood Sugar
- Limitations and Special Cases
- How to Use It in Real Life
What Waist-to-Height Ratio Measures
Waist-to-height ratio is your waist circumference divided by your height, using the same units for both. If your waist is 34 inches and your height is 68 inches, the calculation is straightforward: 34 ÷ 68 = 0.50. The result is identical whether you use inches or centimeters, provided consistency is maintained.
The metric estimates central adiposity, a key driver of metabolic disease. Abdominal fat, particularly the deeper visceral fat surrounding internal organs, is more strongly linked to insulin resistance and cardiometabolic issues than subcutaneous fat stored around the hips or limbs. While a tape measure cannot directly scan visceral tissue—capturing skin, muscle, organs, and abdominal cavity size instead—a larger waist relative to height serves as a reliable population-level marker for central fat burden.
Height normalizes the waist measurement in a way fixed cutoffs cannot. A 36-inch waist carries different implications for someone who is 5 feet tall versus someone who is 6 feet 4 inches. By dividing by height, WHtR adjusts for body size, creating a universal threshold applicable across diverse adult groups. Two adults with the same 90-cm waist can have vastly different metabolic profiles depending on their stature: at 150 cm tall, the ratio is 0.60; at 190 cm tall, it is 0.47.
This simplicity is WHtR’s greatest advantage. No special calculator is required once you grasp the core principle: keep your waist to less than half your height. If you are 70 inches tall, your target is under 35 inches. If you are 170 cm tall, aim for under 85 cm.
How to Calculate It Correctly
The math is trivial; the measurement technique is where errors creep in. Accurate data depends on consistent anatomical landmarks and proper tape placement.
A standard method involves:
- Stand upright with feet comfortably apart and your abdomen relaxed.
- Identify the bottom of your ribs and the top of your hip bones.
- Wrap a flexible tape around the midpoint between these landmarks, roughly at the natural waist.
- Ensure the tape is level and snug without compressing the skin.
- Exhale naturally—do not suck in your stomach—and record the measurement.
- Measure height without shoes.
- Divide waist by height using the same units.
For instance, a 92-cm waist and 178-cm height yields 0.52 (92 ÷ 178). A 31-inch waist and 65-inch height results in 0.48 (31 ÷ 65).
Consistency is critical. Waist circumference fluctuates with meals, bloating, posture, and tape placement. Morning measurements before eating are often easier to standardize, but sticking to the same routine matters more than the specific time of day. If two measurements differ by more than about 1 cm (half an inch), take a third and average the two closest values to minimize technique errors.
Avoid pulling the tape tightly enough to indent the skin. Equally important is maintaining the same anatomical location each time; measuring at the widest part one month and the narrowest the next invalidates trend analysis. A reliable trajectory requires repeatable precision.
What the Numbers Mean
For adults, 0.5 is the pivotal cutoff. NICE guidance classifies waist-to-height ratio for adults with a BMI below 35 kg/m² as follows:
| Waist-to-height ratio | Interpretation |
|---|---|
| 0.40–0.49 | Healthy central adiposity range |
| 0.50–0.59 | Increased central adiposity and health risk |
| 0.60 or higher | High central adiposity and further increased health risk |
A ratio below 0.4 is not automatically superior. Very low measurements can indicate underweight status or low muscle mass, so WHtR must always be interpreted within the context of overall health. The 0.5 rule appeals for its simplicity and universality; unlike some waist-circumference cutoffs, current NICE guidance does not require different numbers for men and women. It translates easily into personal targets: a person who is 5 feet 8 inches (68 inches) tall aims for a waist under 34 inches; someone 180 cm tall aims for under 90 cm.
The ratio also facilitates concrete goal-setting. Consider a 172-cm-tall individual with a 94-cm waist, resulting in a ratio of 0.55. Reducing the waist to 86 cm brings the ratio to 0.50. Breaking this down into incremental steps—94 to 91 cm, then 88 cm, then 86 cm—makes the goal more manageable than fixating on a single threshold. Research across diverse populations confirms that thresholds near 0.5 effectively identify increased cardiometabolic risk.
Crucially, the cutoff is a screening boundary, not a biological cliff. Risk rises on a continuum; a ratio of 0.49 is not inherently safe while 0.50 is suddenly dangerous. A shift from 0.61 to 0.55 represents meaningful progress, even if both values remain above the threshold. This makes WHtR an excellent tool for tracking long-term trends. If your ratio declines steadily over several months, central adiposity is likely decreasing, even if the scale moves slowly.
Waist-to-Height Ratio vs BMI
BMI answers a different question. Calculated as weight in kilograms divided by height in meters squared, it categorizes overall body size. It is quick, inexpensive, and strongly associated with health outcomes across large populations. Its primary limitation is that it cannot distinguish fat from muscle or indicate fat distribution. Two individuals with identical BMIs can have vastly different body compositions and metabolic risks.
WHtR addresses this gap by incorporating fat distribution. Recent studies show waist-based measures often outperform BMI in identifying diabetes or metabolic syndrome. A large systematic review of cohort studies found that increases in BMI, waist circumference, and WHtR were all strongly associated with future type 2 diabetes, with WHtR performing at least as well as the other metrics.
BMI persists because it is well-studied, easy to standardize, and captures overall mass—a factor relevant for joint loading, sleep apnea risk, medication dosing, and severe underweight or obesity. WHtR cannot detect a 10 kg weight loss if the waist remains unchanged, just as BMI cannot determine whether a 10 kg difference is muscle or abdominal fat. They answer related but distinct questions.
WHtR does not render BMI obsolete. BMI remains useful for:
- Identifying very low or very high body weight
- Tracking significant weight changes
- Guiding medication and surgical eligibility criteria
- Population screening and epidemiology
- Providing context for waist measurements
WHtR is particularly valuable when BMI may be misleading. A muscular person might fall into the overweight BMI category despite a relatively small waist. Conversely, someone with a “normal” BMI of 23 or 24 could have a WHtR above 0.5, signaling central fat accumulation. Current obesity standards increasingly advocate combining BMI with waist-based measures rather than relying on either alone.
A simple matrix illustrates how to interpret the combination:
| BMI pattern | WHtR pattern | What it can suggest |
|---|---|---|
| Normal BMI | WHtR under 0.5 | Lower central-fat risk, though other risk factors still matter |
| Normal BMI | WHtR 0.5 or higher | Central adiposity may be missed by BMI alone |
| High BMI | WHtR under 0.5 | Consider high muscle mass or noncentral weight distribution |
| High BMI | WHtR 0.5 or higher | Overall and central adiposity both likely contribute to risk |
Why Central Fat Matters for Blood Sugar
Abdominal fat is intimately linked with insulin resistance. Visceral fat releases fatty acids and metabolic signals that increase liver fat, triglyceride production, inflammation, and hepatic glucose output. The liver plays a central role in regulating fasting blood sugar; when insulin functions normally, it signals the liver to reduce glucose release. With hepatic insulin resistance, the liver continues pumping excess glucose into the bloodstream even when insulin levels are already elevated.
This explains why a growing waist often accompanies rising fasting glucose, triglycerides, blood pressure, and A1C. The waist itself is not the sole cause of these issues but acts as a visible marker of a deeper metabolic pattern. Studies comparing adiposity measures frequently find that waist-based indicators correlate more strongly with type 2 diabetes than BMI. In a 2025 population study, high WHtR was more strongly associated with diabetes risk than high BMI. Notably, individuals with low BMI but high WHtR faced greater risk than those with high BMI but low WHtR, illustrating why “normal weight” does not guarantee low metabolic risk.
A high WHtR does not mean diabetes is inevitable; it signals the need to examine the broader clinical picture: fasting glucose, A1C, blood pressure, triglycerides, HDL cholesterol, family history, sleep, and activity levels. People with prediabetes often benefit from reducing central fat through weight loss and exercise. Even a modest 5–7% weight loss can improve glucose regulation in many adults with overweight or obesity, typically accompanied by a reduction in waist circumference.
Limitations and Special Cases
WHtR is a screening tool, not a diagnostic test for visceral fat, insulin resistance, or cardiovascular disease. Its utility diminishes at very high BMI values. NICE notes that for adults with a BMI above 35 kg/m², the ratio is generally already high, adding little discriminatory value. In such cases, clinical risk is better assessed through the broader health profile rather than distinguishing between ratios like 0.62 and 0.66.
Pregnancy invalidates standard adult WHtR thresholds due to obvious changes in abdominal size. Similarly, conditions that enlarge the abdomen—such as tumors, large hernias, or ascites—can render waist measurements misleading.
Age also complicates interpretation. Older adults may lose height due to vertebral compression or postural changes, artificially raising their WHtR even if waist size remains unchanged. Simultaneously, age-related muscle loss combined with central fat gain can still make the ratio a useful indicator of real risk. A 2024 meta-analysis found WHtR outperformed BMI for screening metabolic syndrome in older adults, though no single metric should replace clinical judgment.
Ethnicity plays a role in metabolic risk, with some populations developing type 2 diabetes at lower BMI levels. One advantage of WHtR is that the simple 0.5 threshold has performed reasonably well across diverse groups, though researchers continue to investigate whether optimal cutoffs vary by ethnicity. For athletes and very muscular individuals, WHtR is often more informative than BMI, but it is not perfect. Strong abdominal musculature can slightly increase waist size, so broader context—including body composition, performance metrics, blood pressure, lipids, and glucose—remains essential.
Finally, avoid using repeated waist checks as a daily scorecard. Hydration, meals, and bowel contents can shift the tape by a centimeter or more. Monthly or bi-weekly measurements are sufficient for tracking lifestyle changes without being distracted by normal physiological noise.
How to Use It in Real Life
Treat WHtR as a low-cost trend marker alongside body weight and basic metabolic labs. Recalculate it whenever you deliberately remeasure your waist; weekly checks are unnecessary unless the data provides strong motivation. A monthly interval is typically enough to identify meaningful trends while filtering out measurement noise.
If your ratio is already below 0.5, maintenance is a sensible goal rather than pushing for ever-lower numbers. A smaller waist is not inherently better if it results from excessive dieting, muscle loss, or undernutrition. Fitness, strength, blood pressure, glucose levels, and quality of life belong in the same holistic view.
Start with one careful baseline measurement. Record both the ratio and the raw waist value. If the ratio exceeds 0.5, avoid obsessing over immediate correction to 0.49. Instead, set smaller initial goals, such as reducing waist circumference by 2–5 cm over several months while improving diet quality and activity levels. For a person 170 cm tall with a starting waist of 96 cm (target: 85 cm), reaching 92 cm represents meaningful progress, even if it remains above the long-term target. Health improves gradually, not just when thresholds are crossed.
Pair the tape measure with controllable behaviors:
- Walk more during the day and after meals
- Perform resistance training at least twice weekly if able
- Reduce sugary drinks and frequent refined snacks
- Build meals around protein, vegetables, legumes, and minimally processed foods
- Moderate alcohol intake
- Prioritize consistent sleep
If weight is stable but WHtR is falling, you may be losing abdominal fat while maintaining or gaining lean mass. Conversely, if weight drops but the waist remains static for months, re-evaluate measurement technique and consider whether the weight loss is primarily water or lean tissue rather than visceral fat.
Complete the picture with lab values. A1C, fasting glucose, triglycerides, HDL cholesterol, blood pressure, and liver enzymes reveal whether waist changes are translating into metabolic improvement. If your waist is below half your height but glucose or lipids are abnormal, do not dismiss the lab findings because the ratio appears favorable.
For individuals using medication-assisted weight loss, lifestyle interventions, or bariatric surgery, WHtR remains a useful monitor for central-fat change. However, clinical teams will likely rely on additional measures—such as body composition analysis, blood pressure, glucose levels, liver markers, and medication adjustments—to judge the full therapeutic response.
WHtR works best as an early warning signal and progress marker. It is often more metabolically informative than BMI alone, but the strongest approach involves integrating body size, central adiposity, blood tests, fitness, family history, and clinical context to understand overall risk.
References
- Screening, Diagnosis, Evaluation, and Staging of Obesity in Adults: Standards of Care in Overweight and Obesity-2026 2026 (Guideline)
- Which adiposity index is best? Comparison of five indicators and their ability to identify type 2 diabetes risk in a population study 2025 (Clinical Study)
- Diagnostic Accuracy of Waist-to-Height Ratio, Waist Circumference, and Body Mass Index in Identifying Metabolic Syndrome and Its Components in Older Adults: A Systematic Review and Meta-Analysis 2024 (Systematic Review)
- Waist to height ratio as a simple tool for predicting mortality: a systematic review and meta-analysis 2023 (Systematic Review)
- Anthropometric and adiposity indicators and risk of type 2 diabetes: systematic review and dose-response meta-analysis of cohort studies 2022 (Systematic Review)
Disclaimer
Waist-to-height ratio is a screening measure, not a diagnosis of obesity, insulin resistance, diabetes, or cardiovascular disease. Pregnancy and certain medical conditions can make waist measurements inappropriate or misleading. Discuss concerning measurements or abnormal glucose, lipid, or blood-pressure results with a qualified health professional.





