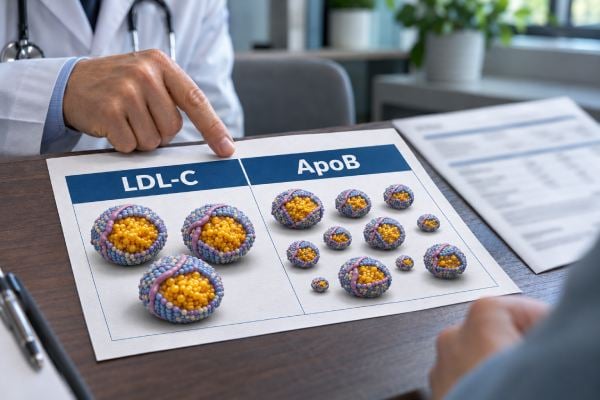
LDL cholesterol and ApoB are both useful for estimating atherosclerotic cardiovascular risk, but they measure different things. LDL cholesterol measures how much cholesterol is carried inside LDL particles. ApoB measures the number of atherogenic particles capable of entering artery walls, including LDL, VLDL remnants, IDL, and lipoprotein(a). When the two markers agree, either one usually tells a similar story. When they disagree, a growing body of evidence suggests ApoB often predicts risk more accurately because particle number is closer to the underlying biology of atherosclerosis.
This difference is most important in people with high triglycerides, diabetes, insulin resistance, obesity, or metabolic syndrome, where many cholesterol-poor particles can circulate despite a seemingly acceptable LDL-C level. That does not make LDL obsolete. LDL-C remains the primary treatment target in many guidelines and is strongly validated. The practical approach is to use ApoB when it adds information, especially when the standard lipid panel and the overall risk picture do not match.
Table of Contents
- What LDL and ApoB Measure
- Which Predicts Heart Risk Better?
- What It Means When ApoB and LDL Disagree
- Who Benefits Most From ApoB Testing
- How the Results Can Change Treatment
- How to Lower Both ApoB and LDL
- Practical Next Steps
What LDL and ApoB Measure
LDL-C is the amount of cholesterol contained inside LDL particles. ApoB is the structural protein found one per atherogenic particle. That makes ApoB a proxy for particle number.
Imagine two trucks carrying cargo. LDL-C tells you the total amount of cargo. ApoB tells you how many trucks are on the road. If each truck carries the same load, the two measures move together. If some trucks carry much less cargo, you can have many more trucks for the same total cargo amount.
The artery wall is exposed to particles, not just free cholesterol. Each circulating ApoB-containing particle has an opportunity to cross the endothelium and become retained. Over time, more particles generally mean more opportunities for plaque formation.
LDL-C remains valuable because it is strongly associated with risk, responds predictably to therapy, and has decades of randomized trial evidence behind LDL-lowering treatment. ApoB adds precision by revealing whether the cholesterol measurement is accurately representing particle number.
Non-HDL cholesterol sits between the two conceptually. It measures cholesterol carried by all non-HDL particles, including LDL and triglyceride-rich remnants. It often performs better than LDL-C when triglycerides are elevated, but it still measures cholesterol mass rather than particle count.
Which Predicts Heart Risk Better?
When LDL-C and ApoB are concordant, their predictive performance is often similar because both are describing the same atherogenic burden from different angles. The clinically important evidence comes from discordance studies, which specifically examine people whose particle number and cholesterol mass do not match.
A 2025 systematic review of discordance studies found ApoB outperformed LDL-C in all nine comparisons that directly assessed the two. A separate 2025 systematic review in people with metabolic disease found that LDL-C can appear optimal while ApoB remains elevated, potentially underestimating risk. Large observational analyses likewise show that residual ApoB information remains associated with cardiovascular events after accounting for LDL-C or non-HDL-C.
This does not mean ApoB is a perfect predictor. Cardiovascular risk also depends on blood pressure, smoking, diabetes, kidney disease, age, family history, inflammation, Lp(a), and the duration of exposure. A person with low ApoB can still have risk from other pathways.
It also does not mean that every guideline should abandon LDL-C. Treatment trials have historically used LDL-C, and clinical systems are built around it. The more useful conclusion is narrower: when ApoB and LDL-C disagree, ApoB often better reflects the concentration of atherogenic particles and may better indicate residual risk.
What It Means When ApoB and LDL Disagree
Discordance is not rare. It tends to appear when lipoprotein composition shifts because of metabolic conditions or treatment.
ApoB high, LDL-C lower
This is the pattern most likely to cause underestimation by LDL-C. It means there are many particles, but each carries relatively little cholesterol.
Common settings include:
- High triglycerides.
- Insulin resistance.
- Type 2 diabetes.
- Metabolic syndrome.
- Obesity or visceral fat.
- Some people on lipid-lowering therapy.
For example, LDL-C could be 90 mg/dL while ApoB is 115 mg/dL. The LDL number may look near a conventional goal, but the particle count remains high.
LDL-C high, ApoB lower
This pattern suggests fewer, cholesterol-rich particles. Risk is not absent, and markedly high LDL-C still deserves attention, particularly when familial hypercholesterolemia is possible. But ApoB may show that the number of atherogenic particles is less extreme than LDL-C suggests.
Why triglycerides create discordance
Higher triglycerides often reflect increased VLDL production. These particles are progressively remodeled into remnants and LDL. The process can generate more particles with less cholesterol per particle. LDL-C therefore becomes a less reliable stand-in for particle number.
If triglycerides are elevated, review diet changes that lower triglycerides because improving the metabolic driver can reduce both remnant burden and ApoB.
Who Benefits Most From ApoB Testing
ApoB is most useful when it has a reasonable chance of changing the interpretation of risk or the intensity of treatment.
It is especially worth considering for people with:
- Triglycerides above normal.
- Diabetes or prediabetes.
- Metabolic syndrome.
- Obesity, especially abdominal obesity.
- Known coronary, cerebrovascular, or peripheral artery disease.
- A strong family history of premature cardiovascular disease.
- LDL-C that appears controlled despite substantial residual risk.
- Uncertain need for medication after standard risk assessment.
ApoB can also be helpful after treatment. Suppose a statin lowers LDL-C impressively but ApoB remains above the level expected for a high-risk patient. That may indicate residual particle burden and support adding another therapy.
For the nuts and bolts of testing, see ApoB testing explained.
How the Results Can Change Treatment
The point of measuring an extra biomarker is not to collect more numbers. It is to make better decisions.
Scenario 1: LDL-C looks fine, ApoB is high
This pattern should prompt a review of triglycerides, diet, weight, diabetes control, and overall risk. In a high-risk patient, it may justify intensifying lipid-lowering therapy even though LDL-C appears acceptable.
Scenario 2: Both are high
The message is straightforward: cholesterol mass and particle number are both elevated. Lifestyle changes and medication are considered according to risk.
Scenario 3: LDL-C is high but ApoB is less elevated
Treatment still depends on absolute LDL-C, family history, genetic suspicion, age, and global risk. ApoB may refine the picture, but it should not be used to dismiss severe LDL elevation.
Scenario 4: Both are low
This is generally reassuring from an atherogenic lipoprotein perspective, although other risk factors still matter. Blood pressure, smoking, diabetes, physical inactivity, and Lp(a) remain relevant.
ApoB targets are risk-based. A lower-risk person may be well served by a value below about 90 mg/dL, while higher-risk patients often aim below about 80 mg/dL and very-high-risk patients may target around 65 mg/dL or lower. For context, see ApoB target levels.
How to Lower Both ApoB and LDL
Because LDL particles make up a large share of the ApoB particle pool in many people, interventions that lower LDL-C generally lower ApoB too.
Replace saturated fat with unsaturated fat
Reduce butter, fatty processed meats, coconut oil, and high-saturated-fat baked foods. Replace them with olive oil, nuts, seeds, avocado, and fish. This often lowers LDL-C and particle number.
Increase soluble fiber
Oats, barley, beans, lentils, psyllium, apples, and citrus can reduce cholesterol absorption and help lower LDL-C. A soluble fiber strategy for LDL lowering can be useful when diet is the first treatment step.
Improve insulin resistance
When high ApoB is driven by triglyceride-rich particles, weight loss, exercise, reduced added sugar, less refined carbohydrate, and lower alcohol intake can be especially helpful.
Use medication when appropriate
Statins lower LDL-C and ApoB and have strong evidence for reducing cardiovascular events. Ezetimibe, PCSK9-directed therapies, and bempedoic acid can provide additional lowering when needed.
The best medication choice depends on baseline risk and how far the markers need to fall. In secondary prevention, modest lifestyle changes alone are often insufficient to reach recommended lipid levels.
Practical Next Steps
If your LDL-C and overall risk assessment already point clearly toward treatment, you do not need ApoB before taking action. But if the picture is uncertain, ApoB can add valuable information.
A practical sequence is:
- Get a standard lipid panel that includes total cholesterol, HDL-C, triglycerides, and LDL-C.
- Add ApoB if triglycerides are high, metabolic disease is present, or risk seems greater than LDL-C suggests.
- Consider Lp(a) at least once, especially with a strong family history or premature cardiovascular disease.
- Compare LDL-C, non-HDL-C, and ApoB rather than viewing any one marker in isolation.
- Set treatment intensity based on total cardiovascular risk.
- Recheck after lifestyle or medication changes to confirm that particle burden has fallen.
Do not focus on tiny differences between labs. The clinically meaningful question is whether you have persistently high atherogenic particle exposure and whether treatment is lowering it enough.
The simplest way to remember the difference is this: LDL-C measures cholesterol cargo; ApoB measures the number of atherogenic carriers. When cargo and carrier count disagree, carrier count often gives the clearer picture of atherosclerotic risk.
Why guidelines still emphasize LDL-C
It can seem contradictory that ApoB often performs better in discordance studies while most treatment guidelines still lead with LDL-C. The reason is historical and practical. Decades of randomized cardiovascular outcome trials measured LDL-C, used it to describe treatment intensity, and showed that therapies lowering LDL-related particles reduce heart attacks and strokes. LDL-C testing is also available almost everywhere and is embedded in risk calculators and treatment systems.
ApoB does not undermine that evidence. Most drugs that lower LDL-C also lower ApoB because they remove ApoB-containing particles from circulation. ApoB simply measures the particle response more directly. As evidence and laboratory access improve, more clinicians are using both markers rather than choosing one side.
What about non-HDL cholesterol?
Non-HDL-C is a useful middle ground. It equals total cholesterol minus HDL-C and therefore captures cholesterol carried by all atherogenic particles, including remnants. It is automatically available from a standard lipid panel and does not require fasting.
When triglycerides are elevated, non-HDL-C can be more informative than LDL-C because remnant cholesterol becomes a larger part of the atherogenic burden. Still, non-HDL-C is cholesterol mass, not particle number. In people with marked metabolic disease, ApoB can remain the clearer measure when the two are discordant.
A practical hierarchy is not “ApoB good, LDL bad.” It is: use LDL-C routinely, look at non-HDL-C automatically, and add ApoB when particle number may clarify the risk picture.
How treatment can create new discordance
Discordance does not only occur before treatment. Statins and other lipid-lowering therapies can change particle composition as well as particle concentration. In some treated patients, LDL-C falls more than ApoB, leaving a higher particle count than the LDL-C value suggests.
That matters most when absolute risk is high. A person with prior myocardial infarction, diabetes, and residual ApoB elevation may benefit from additional treatment even if LDL-C appears close to goal. In a low-risk person, the same numerical discordance may not justify aggressive medication because the absolute event reduction would be smaller.
Do particle size tests add more information?
Small dense LDL is often discussed because metabolic disease can shift LDL particles toward smaller size. But if ApoB is known, measuring LDL particle size usually adds much less clinically useful information. Small particles are concerning largely because a given amount of cholesterol can be distributed across more particles. ApoB already captures that number directly.
The same logic applies to many advanced lipid panels. More measurements are not automatically better. A test should improve risk classification or change management. ApoB has a strong case because it is standardized, relatively simple, and biologically tied to atherogenic particle count.
The best marker is ultimately the one that leads to the right treatment decision. For routine care that may be LDL-C. For metabolic disease or unexplained residual risk, ApoB can be the number that reveals what LDL-C misses.
Three common interpretation mistakes
The first mistake is treating a normal LDL-C as proof that particle burden is low. This is exactly where ApoB can add value, particularly when triglycerides are elevated or diabetes is present. LDL-C may look acceptable while ApoB remains high.
The second mistake is doing the reverse: using a lower ApoB to dismiss a very high LDL-C. Severe LDL elevation can reflect inherited disease and substantial lifetime exposure, and it still requires careful evaluation even if particle number is not as high as the LDL-C value might suggest.
The third mistake is comparing your result with someone else’s without considering risk. A value that is reasonable for a young low-risk adult may be above target for someone with established coronary disease.
How to decide whether you need the extra test
If your LDL-C is clearly high and treatment is already indicated, ApoB may not change the first step. Likewise, if LDL-C, non-HDL-C, triglycerides, and overall risk are all low, ApoB may simply confirm what is already obvious.
The test earns its keep when uncertainty exists. Examples include LDL-C that looks “normal” despite high triglycerides, unexplained premature cardiovascular disease, diabetes with residual risk, or treated patients whose LDL-C is at goal but whose risk remains high. In these cases, ApoB can reveal whether the total number of atherogenic particles is still excessive.
A practical question to ask before ordering it is: “Would the result change what I do?” If a high ApoB would prompt medication, a dose increase, a change in diet, or closer follow-up, the test has clear value. If nothing would change, it may be reasonable to wait.
The bottom line for decision-making
LDL-C remains a highly useful, evidence-based marker and should not be discarded. ApoB adds a layer of precision by measuring particle number directly. The two markers are best viewed as complementary.
When they agree, you usually do not need to choose between them. When they disagree, especially in metabolic disease, ApoB often provides the stronger clue to atherosclerotic risk. Treatment should then focus on the person rather than the laboratory rivalry: lower atherogenic particle exposure, control the other major risk factors, and use follow-up testing to confirm that the plan is working.
One final point is that trends matter. A single result is a snapshot, while repeated measurements after a meaningful treatment change show whether atherogenic particle exposure is moving in the right direction. Consistent long-term lowering matters more than chasing minor laboratory fluctuations.
ApoB can also be useful when lifestyle changes improve triglycerides more than LDL-C. In that situation, the particle count may fall even if the LDL-C number changes modestly, showing a real improvement in atherogenic burden. Conversely, if LDL-C falls but ApoB barely moves, the remaining particle count may deserve attention. Looking at both markers can therefore show not only where you started, but what kind of response a treatment produced.
References
- ApoB, LDL-C, and non-HDL-C as markers of cardiovascular risk 2025 (Systematic Review)
- Discordance analyses comparing LDL cholesterol, Non-HDL cholesterol, and apolipoprotein B for cardiovascular risk estimation 2025 (Review)
- Discordance between serum cholesterol concentration and atherogenic lipoprotein particle number in people with metabolic disease: A systematic review 2025 (Systematic Review)
- Apolipoprotein B: Bridging the Gap Between Evidence and Clinical Practice 2024 (Review)
- Discordance among apoB, non-high-density lipoprotein cholesterol, and triglycerides: implications for cardiovascular prevention 2024
- ADLM Guidance Document on the Measurement and Reporting of Lipids and Lipoproteins 2024 (Guideline)
Disclaimer
This article is for general education and does not replace individualized cardiovascular risk assessment. LDL-C and ApoB goals depend on medical history, age, diabetes, kidney disease, other risk factors, and medications. Discuss testing and treatment decisions with a qualified healthcare professional.