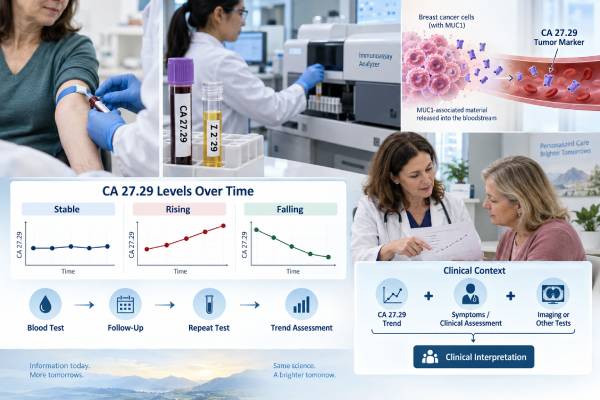
CA 27.29 is a blood tumor marker that measures a circulating form of the MUC1 protein, which can be released by breast cancer cells and some normal tissues. Its main role is not screening or diagnosing breast cancer. Instead, clinicians may use serial CA 27.29 measurements as an adjunct when monitoring some people with metastatic breast cancer, especially when the marker was elevated at baseline and changes broadly track the disease. A single high result cannot prove recurrence or progression, and a normal result cannot rule cancer out. Values can also rise because of non-breast cancers, benign conditions, assay interference, or ordinary laboratory variation. After curative treatment for early-stage breast cancer, current ASCO guidance does not recommend routine tumor-marker testing in asymptomatic patients for surveillance. The safest way to interpret CA 27.29 is therefore as a trend that is connected to symptoms, examination, imaging, and the patient’s known disease—not as an independent cancer detector.
- CA 27.29 measures a MUC1-related tumor antigen in serum and is mainly used as an adjunct for monitoring known breast cancer, not for screening.
- A commonly used laboratory reference limit is ≤38.0 U/mL, but the correct range is the one printed by the performing laboratory.
- Rising serial CA 27.29 values may support concern for progression when they agree with the clinical picture; one isolated rise is not diagnostic.
- A normal CA 27.29 level does not exclude breast cancer, recurrence, or progression because many tumors do not release enough marker to raise the blood level.
- For asymptomatic patients after primary curative treatment, routine CA 15-3/CA 27.29 surveillance is not recommended by the 2026 ASCO follow-up guideline.
Table of Contents
- What the CA 27.29 Test Measures
- When CA 27.29 Is Used in Breast Cancer Care
- CA 27.29 Reference Range and How to Read a Trend
- What a High CA 27.29 Level Can Mean
- Why a Normal CA 27.29 Result Does Not Rule Out Cancer
- Using CA 27.29 to Monitor Treatment or Suspected Recurrence
- Practical Questions to Ask About a CA 27.29 Result
What the CA 27.29 Test Measures
CA 27.29 is an immunoassay for an epitope associated with MUC1, a large glycoprotein normally present on epithelial cells. Breast cancers can alter MUC1 expression and release measurable antigen into the bloodstream. CA 27.29 and CA 15-3 recognize related MUC1-associated material, which is why they often move in similar directions in patients with breast cancer.
The assay is performed on serum from a standard blood draw. Fasting is usually unnecessary unless another test ordered at the same time requires it. The laboratory reports the result in units per milliliter (U/mL). A commonly used upper reference limit for this assay is ≤38.0 U/mL, but the exact cutoff depends on the assay platform and laboratory validation.
The number is not a direct count of tumor cells. A value of 80 U/mL does not mean there are twice as many cancer cells as a value of 40 U/mL. Marker release depends on tumor biology, disease sites, treatment, liver clearance, assay design, and individual variation. Some people with extensive metastatic disease have modest or normal values, while another person may have a much higher concentration.
For that reason, the most clinically useful information is often the within-person trend when the same assay is repeated over time. A marker that was elevated before treatment and then falls with a documented response can become a useful adjunct. A marker that was normal throughout the course may offer little value even if it is checked repeatedly.
CA 27.29 is also distinct from tissue biomarkers such as ER, PR, and HER2. Those tests help classify the tumor and select therapy. A breast cancer biomarker profile answers treatment-selection questions that a serum tumor marker cannot.
When CA 27.29 Is Used in Breast Cancer Care
The clearest role for CA 27.29 is as an adjunct in monitoring selected patients with metastatic breast cancer. If the marker is elevated and has tracked the known cancer, clinicians may follow it alongside symptoms, physical findings, and imaging. A consistent fall during effective therapy can support the impression of response; a sustained rise can prompt closer evaluation for progression.
ASCO’s metastatic breast cancer biomarker guideline has long emphasized that CA 15-3 and CA 27.29 may contribute to therapy assessment but should not be used alone. That principle remains important because tumor markers can fluctuate for reasons unrelated to true progression. A treatment should not usually be abandoned solely because one blood result rose when the patient is clinically stable and imaging does not confirm worsening disease.
The role is different after primary curative-intent treatment. The 2026 ASCO follow-up and surveillance guideline states that routine blood tests including CEA, CA 15-3, and CA 27.29 are not recommended for routine surveillance in asymptomatic patients. Earlier detection of a marker rise has not been shown to improve outcomes enough to justify routine testing, and false-positive results can lead to anxiety, repeated scans, procedures, radiation exposure, and cost.
The marker is not appropriate for population screening or for deciding whether a breast lump is cancer. Sensitivity is too low in early disease and specificity is too limited. Mammography, diagnostic imaging, examination, and tissue biopsy remain the tools used to diagnose breast cancer.
Some laboratories note that serial testing may detect recurrence before it becomes clinically apparent, but “earlier signal” and “proven benefit from routine surveillance” are not the same thing. That distinction explains why a test can be biologically informative yet still not be recommended as routine follow-up for every survivor.
CA 27.29 Reference Range and How to Read a Trend
A reference interval marks the range expected in most people without the condition the assay is designed to monitor; it is not a cancer/no-cancer boundary. For CA 27.29, a commonly used laboratory reference limit is ≤38.0 U/mL. The report from the performing laboratory should take priority because different platforms can use different antibodies, calibration systems, and reference ranges.
Serial values should ideally be measured by the same method in the same laboratory. Switching assays can create an apparent rise or fall that reflects the platform rather than the patient. This is especially relevant when comparing CA 27.29 with CA 15-3: although both are MUC1-related, their numerical results are not interchangeable.
A trend becomes more credible when several features align: the marker was previously informative for that patient, the change is sustained on repeat testing, the magnitude exceeds expected analytic and biological variation, and symptoms or imaging point in the same direction. A one-time modest increase just above the reference limit is much less persuasive.
Timing also matters. Tumor markers can transiently rise early after a new therapy, and interpreting an isolated early value without the treatment context may be misleading. Clinicians usually focus on the overall trajectory across multiple measurements rather than reacting to every small oscillation.
If a result jumps unexpectedly, it is reasonable to confirm the laboratory method, repeat the test when appropriate, review liver or other medical conditions, and ask whether there were changes in medications, pregnancy status, or specimen quality that could affect interpretation. The correct response to a surprising number is verification and clinical correlation—not assuming progression from the laboratory value alone.
What a High CA 27.29 Level Can Mean
A high CA 27.29 value can occur when breast cancer is active, particularly in metastatic disease, but the result is not specific for breast cancer. Higher concentrations are more common when disease burden is greater, and elevations are often seen with liver or bone metastases, yet there is substantial overlap among patients.
Other cancers can also raise MUC1-related markers. Depending on the assay and clinical setting, elevations have been reported with malignancies of the lung, ovary, pancreas, liver, colon, cervix, endometrium, and other epithelial tissues. This is one reason the marker cannot identify the cancer’s origin.
Benign conditions can produce elevations as well. Liver dysfunction, inflammatory conditions, benign breast or gynecologic disease, pregnancy, and other nonmalignant states may alter a result. Immunoassay interference, including heterophile antibodies, can occasionally produce misleading measurements. The exact list of interfering conditions differs by assay and should be checked with the laboratory when a result does not fit the clinical picture.
The degree of elevation can influence how seriously a result is taken, but no universal value proves recurrence. A large and steadily rising change in a patient with known metastatic breast cancer is more concerning than a stable value a few units above the reference range in an otherwise well survivor. Context changes the pretest probability.
If the patient has no known active cancer and an unexpected high result appears, the next step is not to label the result as recurrence. The clinician reviews symptoms and examination, confirms the test, and orders imaging or other evaluation only when justified. The test is best treated as a signal to investigate, not a diagnosis.
Why a Normal CA 27.29 Result Does Not Rule Out Cancer
Many breast cancers do not release enough MUC1-associated antigen to produce an abnormal blood value. This is especially true in small-volume or early-stage disease, but it can also occur in metastatic cancer. A normal result therefore cannot be used to exclude recurrence, and it cannot override new symptoms or suspicious imaging.
This limitation is central to screening. A screening test must reliably detect disease at a stage when treatment can improve outcome and must avoid excessive false positives. CA 27.29 does not meet those requirements for breast cancer screening. A person can have breast cancer with a normal marker, and a person without breast cancer can have an elevated marker.
There are also analytic limitations. Different assays may recognize somewhat different MUC1 epitopes, so numerical values from two platforms should not be stitched into one trend line. Laboratory variation, specimen handling, antibodies that interfere with immunoassays, and changes in organ function can all alter results.
The marker does not reveal where disease is located. A rising value cannot distinguish bone metastasis from liver metastasis or local recurrence. It also does not identify actionable mutations or receptor changes. For that, clinicians may need imaging, tissue biopsy, or a circulating tumor DNA test in an appropriate advanced-disease setting.
Finally, a marker can become less informative over time. Tumor clones evolve, and treatment can change the biology of the disease. If CA 27.29 stops paralleling imaging and symptoms, clinicians may stop relying on it rather than forcing the number to remain useful.
Using CA 27.29 to Monitor Treatment or Suspected Recurrence
For metastatic breast cancer, serial tumor markers are most defensible when they are part of a preplanned monitoring strategy. The oncology team establishes a baseline, repeats the assay at clinically meaningful intervals, and interprets changes alongside scans and symptoms. If the patient has measurable disease on imaging, imaging usually remains the principal objective assessment.
A decline after therapy can be reassuring when it matches clinical improvement and radiologic response. A sustained rise can raise concern for resistance or progression, but confirmation matters. The 2015 ASCO metastatic biomarker guideline explicitly states that circulating markers can be adjunctive but should not be used alone to make therapy decisions. This protects patients from switching an effective treatment because of a laboratory fluctuation.
For survivors of early-stage breast cancer who have completed primary treatment, routine surveillance is different. Current ASCO guidance recommends history, physical examination, and mammography, with additional evaluation driven by symptoms, examination, and individualized risk. Routine CA 15-3/CA 27.29 testing in asymptomatic patients is not recommended.
When symptoms do arise—persistent focal bone pain, unexplained shortness of breath, new neurologic symptoms, abdominal pain, or other concerning changes—the evaluation should be symptom-directed. A tumor marker may be included in some workups, but it should not delay appropriate imaging or diagnostic testing.
The difference between monitoring known metastatic disease and screening an asymptomatic survivor for hidden recurrence is one of the most important distinctions in tumor-marker use. The same blood test can have different value in those two contexts because the baseline probability of active disease is very different.
Practical Questions to Ask About a CA 27.29 Result
When a CA 27.29 result is ordered, ask what decision the clinician expects it to inform. If the answer is “to monitor metastatic disease that has previously produced this marker,” the test has a clear role. If the answer is “to make sure cancer never comes back” after curative treatment in an asymptomatic patient, ask how that plan fits the 2026 ASCO surveillance guideline.
Keep copies of prior results and note whether the same laboratory method was used. A graph of values over time is often more informative than a single result viewed in isolation. Also compare the marker trend with the timing of scans and treatment changes.
If the level rises, ask whether the change is large enough and sustained enough to be clinically meaningful, whether the test should be repeated, and what noncancer causes are plausible. Ask what evidence would actually confirm progression. This shifts the conversation from anxiety about a number to a structured diagnostic plan.
If the level is normal, do not use that as a reason to ignore persistent symptoms. Tumor markers have false negatives. The correct workup of symptoms is based on the symptom pattern and the person’s cancer history, not on a reassuring serum value.
Finally, know which marker is being followed. CA 27.29 and CA 15-3 are related MUC1 assays, but their numbers should not be directly compared. If the oncology team changes from one marker to the other, a new baseline may be needed.
A well-used tumor marker reduces uncertainty when it follows known disease. A poorly used marker can create false reassurance or false alarms. The difference is not the blood draw itself—it is the clinical question and how the result is acted on.
How to interpret a trend instead of one cutoff
CA 27.29 is most informative when the same assay is followed over time in a patient whose marker was elevated with measurable metastatic disease. A value above a laboratory reference limit can draw attention, but the clinical meaning comes from the trajectory. Three rising results obtained under comparable conditions may be more concerning than one mildly high result that returns to baseline. Likewise, a meaningful fall during therapy can support other evidence of response.
Assay consistency matters because different MUC1-based tumor-marker methods can produce numerically different results. A patient who moves between laboratories should not assume that two values are directly interchangeable just because both are labeled CA 27.29. The report’s own reference interval and method should be checked.
A normal result is not a safety guarantee. Some metastatic breast cancers produce little circulating CA 27.29, and a marker that was never elevated at baseline may be poorly suited to monitoring that person. A high result is also not specific for breast-cancer progression. Benign liver conditions and other cancers can raise MUC1-related markers.
When a change is surprising, clinicians may repeat the test, review the assay and specimen timing, examine the patient, and use imaging when clinically indicated. Treatment should not be stopped, started, or switched from the marker alone. This approach avoids two common errors: reacting to harmless laboratory noise and being falsely reassured by a normal value in a cancer that does not shed the marker reliably.
References
- Breast Cancer Follow-Up and Surveillance After Primary Treatment: ASCO Guideline Update 2026 (Guideline)
- ESMO Clinical Practice Guideline for the diagnosis, staging and treatment of patients with metastatic breast cancer. 2021 (Guideline)
- Use of Biomarkers to Guide Decisions on Systemic Therapy for Women With Metastatic Breast Cancer: American Society of Clinical Oncology Clinical Practice Guideline 2015 (Guideline)
- C2729 – Overview: Breast Carcinoma-Associated Antigen, Serum 2026
- From Serum Markers to Liquid Biopsy: Precision Monitoring in Breast, Ovarian, Pancreatic, and Prostate Cancers 2026 (Review)
- The assessment of breast cancer biomarkers in diagnosis, prognosis and treatment monitoring: integrated analysis 2025 (Review)
Disclaimer
This article provides general information about CA 27.29 testing in breast cancer. Tumor-marker results are not diagnostic by themselves and should be interpreted by the oncology team together with symptoms, examination, imaging, treatment history, and the performing laboratory’s reference range.