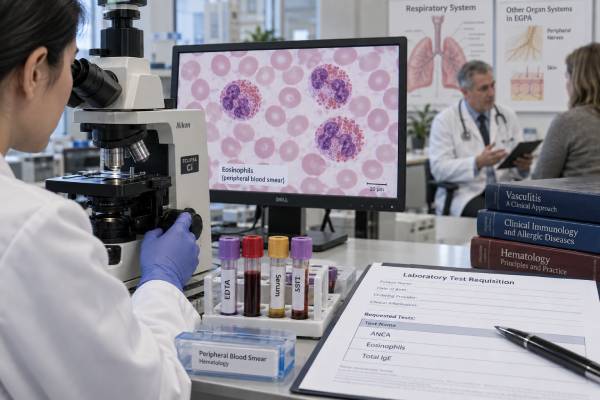
A blood test panel for eosinophilic granulomatosis with polyangiitis (EGPA) helps identify a pattern of eosinophilic inflammation, vasculitis, and organ injury. The core tests often include a complete blood count with absolute eosinophil count, ANCA testing with myeloperoxidase and proteinase 3 antibodies, total IgE, C-reactive protein, erythrocyte sedimentation rate, kidney and liver tests, and urinalysis. Additional tests depend on symptoms and the organs that may be affected.
No single blood marker confirms or excludes EGPA. Many people with EGPA have negative ANCA results, and high eosinophils or IgE can occur in asthma, allergy, medication reactions, parasites, and other eosinophilic disorders. Clinicians diagnose EGPA by combining the laboratory pattern with asthma or airway disease, sinus symptoms, imaging, neurologic findings, cardiac assessment, kidney testing, and sometimes a biopsy. The most useful panel is therefore not a fixed commercial bundle, but a focused set of tests chosen to answer specific diagnostic and safety questions.
- The most important screening value is the absolute eosinophil count, not the eosinophil percentage alone.
- ANCA is positive in only a minority of EGPA cases, most often with MPO antibodies; a negative result does not rule out the disease.
- Total IgE is often elevated but is nonspecific, so it cannot distinguish EGPA from ordinary allergic disease.
- Urinalysis, creatinine, troponin, and organ-directed tests may be more urgent than antibody results when kidney or heart involvement is possible.
- Corticosteroids can rapidly lower eosinophils and inflammatory markers, making older untreated results especially valuable.
Table of Contents
- What an EGPA blood test panel can show
- Core tests in the panel
- How to read ANCA, eosinophils, and IgE together
- Tests for organ involvement
- How EGPA is diagnosed
- Conditions that can mimic EGPA
- Monitoring results after diagnosis
What an EGPA blood test panel can show
An EGPA panel supports three separate tasks: finding eosinophilic inflammation, looking for evidence of vasculitis, and checking whether organs are being injured. Those tasks matter more than any particular brand or laboratory package.
EGPA is a rare systemic disease characterized by asthma or obstructive airway disease, blood and tissue eosinophilia, and inflammation that may involve small- to medium-sized blood vessels. It can affect the lungs, sinuses, skin, nerves, heart, gastrointestinal tract, and kidneys. The combination varies greatly from person to person.
A useful panel can answer questions such as:
- Is the eosinophil count truly elevated, and how high has it been before treatment?
- Is an ANCA antibody present, and is it directed against MPO or PR3?
- Are general inflammation markers elevated?
- Is there hidden kidney, liver, muscle, or cardiac injury?
- Does the blood count suggest a medication reaction, infection, or bone marrow disorder instead?
The panel cannot show whether a blood vessel is inflamed with certainty. ANCA may support the diagnosis, but vasculitis is established through the whole clinical picture and sometimes tissue biopsy. Likewise, eosinophilia supports an eosinophilic disease but does not specify which one.
The best starting point is often a complete blood count with differential plus a review of earlier results. A dedicated eosinophil count interpretation is especially useful because inhaled, oral, or injected corticosteroids can reduce the number before a specialist evaluates the patient.
Core tests in the panel
The exact order varies, but the following tests commonly form the laboratory foundation of an EGPA evaluation.
| Test | What it assesses | Main limitation |
|---|---|---|
| Complete blood count with differential | Absolute eosinophil count, anemia, platelets, and other white blood cells | Eosinophils may normalize after corticosteroids |
| ANCA with MPO and PR3 antibodies | Autoantibodies associated with ANCA-related vasculitis | Most people with EGPA are ANCA-negative |
| Total IgE | Broad type 2 or allergic immune activity | Highly nonspecific and sometimes normal |
| CRP and ESR | Systemic inflammation | Can be normal in active disease or high for unrelated reasons |
| Creatinine and estimated GFR | Kidney function | May remain normal early in kidney inflammation |
| Urinalysis and urine protein measurement | Blood, protein, and cellular casts suggesting kidney injury | Abnormalities are not specific to vasculitis |
| Liver enzymes and metabolic panel | Organ function, treatment safety, and alternative diagnoses | Does not diagnose EGPA |
Complete blood count and eosinophils
Eosinophilia usually means an absolute eosinophil count of at least 500 cells/µL. In EGPA, the untreated count may be substantially higher. The 2022 classification criteria assign strong weight to a maximum eosinophil count of at least 1,000 cells/µL, but this is a classification feature rather than a stand-alone diagnostic threshold.
Clinicians should look at the maximum documented count, not only the current value. Prednisone and other glucocorticoids can suppress eosinophils quickly. Biologic medicines targeting interleukin-5 or its receptor can also produce very low counts even when a person has a well-established EGPA diagnosis.
The rest of the blood count matters. Anemia, abnormal platelets, unusually high total white cells, immature cells, or other atypical features may point toward bleeding, chronic inflammation, medication effects, or a hematologic disorder.
ANCA, MPO, and PR3 antibodies
ANCA testing is most useful when it identifies the antibody target. In EGPA, a positive result is usually MPO-ANCA. PR3-ANCA is uncommon and may prompt careful consideration of granulomatosis with polyangiitis or another diagnosis.
A laboratory may begin with immunoassays for MPO and PR3, indirect immunofluorescence for a p-ANCA or c-ANCA pattern, or a reflex combination. A targeted MPO-ANCA test is more clinically specific than relying on the p-ANCA pattern alone. Atypical p-ANCA patterns can occur in inflammatory bowel disease, autoimmune liver disease, infection, and other conditions.
Total IgE
Total IgE is often elevated in EGPA because the disease commonly develops in people with asthma, rhinosinusitis, nasal polyps, and type 2 inflammation. However, a high result also occurs in atopic dermatitis, allergic sensitization, parasitic infection, some immune deficiencies, and other disorders. A normal value does not exclude EGPA.
The value is best treated as context rather than a diagnostic score. It may support the overall picture or help characterize coexisting allergic disease, but it should not drive the diagnosis by itself. A total IgE result also cannot identify a specific allergen.
CRP and ESR
CRP and ESR can rise during systemic inflammation, infection, or tissue injury. They may help show whether inflammatory activity is changing, but neither test is specific to vasculitis. CRP often changes faster, while ESR can remain elevated because of anemia, age, pregnancy, or altered blood proteins.
Normal inflammatory markers do not safely exclude active EGPA, especially when disease is limited to a particular organ or treatment has already started.
How to read ANCA, eosinophils, and IgE together
The three headline markers answer different questions. Eosinophils reflect a cell population, ANCA identifies a particular autoimmune response, and IgE reflects broad allergic or type 2 immune activity. They should not be treated as interchangeable measures of severity.
Several common patterns illustrate the point:
| Pattern | What it may suggest | What still needs checking |
|---|---|---|
| High eosinophils, high IgE, negative ANCA | EGPA remains possible, but allergy, parasites, drug reactions, and other eosinophilic disorders are also common | Asthma history, sinus disease, imaging, nerves, heart, exposures, medications |
| High eosinophils, positive MPO-ANCA | Raises suspicion for EGPA when the clinical pattern fits | Evidence of actual vasculitis and exclusion of mimics |
| Normal eosinophils after prednisone, negative ANCA | Does not exclude EGPA | Older counts, treatment timing, tissue findings, organ involvement |
| Very high eosinophils with abnormal smear or splenomegaly | May indicate a clonal eosinophilic disorder | Hematology testing and molecular studies |
| Positive MPO-ANCA without eosinophilia or asthma | May fit microscopic polyangiitis better than EGPA | Kidney, lung, and systemic vasculitis features |
ANCA status also correlates imperfectly with clinical phenotype. ANCA-positive EGPA more often includes peripheral neuropathy, purpura, and kidney inflammation. ANCA-negative disease more often has prominent eosinophilic tissue disease and cardiac involvement. These are tendencies, not rules, and both phenotypes can affect any organ.
An ANCA level should not be used alone to decide whether disease is active or treatment should change. Titers can remain positive during remission, disappear despite later relapse, or fluctuate without matching symptoms. Clinical assessment remains primary.
Tests for organ involvement
Organ screening is a central part of the panel because EGPA can cause serious damage before routine symptoms become obvious. The next test should be chosen by the potential consequence of missing disease, not simply by which marker is easiest to order.
Kidney and urine assessment
Serum creatinine, estimated glomerular filtration rate, urinalysis, and urine protein measurement help detect glomerulonephritis. Blood and protein in urine, especially with red-cell casts or rising creatinine, require prompt evaluation. A normal creatinine does not exclude early kidney inflammation because substantial function may remain while urine abnormalities have already appeared.
An ANCA reflex panel may support the evaluation, but urine microscopy often provides more immediate evidence of renal involvement.
Cardiac assessment
Cardiac disease is a major concern in EGPA and can occur even when ANCA is negative. Symptoms include chest pain, breathlessness, palpitations, fainting, swelling, or unexplained fatigue. Initial testing may include an electrocardiogram, cardiac troponin, natriuretic peptide, and echocardiography. Cardiac MRI can detect myocarditis, fibrosis, or other abnormalities when suspicion remains.
A normal routine blood panel does not rule out cardiac involvement. Clinicians may screen at diagnosis even when symptoms are subtle because missed eosinophilic heart disease can be dangerous.
Lungs, sinuses, and airways
Chest imaging may show transient or patchy infiltrates, nodules, ground-glass changes, or other abnormalities. Pulmonary function tests assess airflow obstruction and help separate uncontrolled asthma from additional lung disease. Sinus CT or ear, nose, and throat evaluation may document chronic rhinosinusitis or nasal polyps.
Blood eosinophils do not distinguish asthma alone from eosinophilic lung infiltration. Imaging and the clinical course are essential.
Nerves, skin, and gastrointestinal tract
New asymmetric numbness, weakness, foot drop, wrist drop, or severe neuropathic pain can signal mononeuritis multiplex. Nerve conduction studies and electromyography may identify the pattern, and selected cases require nerve or muscle biopsy.
Purpura or nodules may provide an accessible site for skin biopsy. Severe abdominal pain, bleeding, persistent vomiting, or unexplained diarrhea may prompt imaging, endoscopy, or other gastrointestinal evaluation.
How EGPA is diagnosed
EGPA is diagnosed clinically by integrating airway disease, eosinophilia, organ manifestations, imaging, antibodies, and pathology. There is no universally accepted single diagnostic blood test.
A practical diagnostic sequence is:
- Confirm eosinophilia and review its untreated history. Calculate the absolute count and note corticosteroid or biologic exposure.
- Establish the clinical pattern. Adult-onset asthma, chronic sinusitis, and nasal polyps are common background features.
- Search for vasculitic or eosinophilic organ injury. Focus on nerves, skin, lungs, heart, kidneys, and gastrointestinal tract.
- Test ANCA properly. Include antigen-specific MPO and PR3 assays rather than relying only on a fluorescence label.
- Exclude important mimics. Review medications, parasite exposures, allergic bronchopulmonary aspergillosis, hypereosinophilic syndromes, and blood cancers.
- Obtain tissue when it will clarify the diagnosis safely. Biopsy is helpful but not always possible or necessary.
The 2022 ACR/EULAR classification criteria use a weighted score after mimics have been excluded and a diagnosis of small- or medium-vessel vasculitis has been made. Features include eosinophils of at least 1,000 cells/µL, obstructive airway disease, nasal polyps, extravascular eosinophilic inflammation, mononeuritis multiplex, hematuria, and c-ANCA or PR3-ANCA. The criteria are valuable for creating consistent research groups, but they are not a substitute for clinical diagnosis.
Biopsy may show eosinophil-rich inflammation, necrotizing vasculitis, or granulomatous inflammation. Not every specimen contains all classic findings, especially after treatment. The choice of tissue should balance diagnostic yield and safety.
Conditions that can mimic EGPA
Several disorders can produce asthma, eosinophilia, lung findings, or a positive antibody test. Excluding them prevents inappropriate immune suppression.
Common alternatives include:
- Severe eosinophilic asthma without systemic vasculitis
- Allergic bronchopulmonary aspergillosis
- Medication reactions, including DRESS
- Helminth infection, particularly Strongyloides when exposure is plausible
- Chronic eosinophilic pneumonia
- Hypereosinophilic syndrome
- Eosinophilic gastrointestinal disease
- Granulomatosis with polyangiitis or microscopic polyangiitis
- IgG4-related disease
- Lymphoma or a myeloid/lymphoid neoplasm with eosinophilia
The evaluation should follow the clues. Travel or residence history may lead to parasite serology. A very high tryptase, enlarged spleen, abnormal blood smear, or cytopenias may lead to bone marrow and molecular testing. Central bronchiectasis and fungal sensitization may support allergic bronchopulmonary aspergillosis.
A broad vasculitis blood test panel can organize the differential, but indiscriminate testing may generate weak positive results that do not match the illness.
Monitoring results after diagnosis
After diagnosis, blood tests help track treatment safety and selected aspects of disease, but they do not replace symptom and organ assessment. A falling eosinophil count may show a biologic effect while neuropathy, asthma, or cardiac disease still requires separate evaluation.
Monitoring often includes:
- Complete blood count with differential
- Creatinine, liver enzymes, and metabolic panel
- Urinalysis and urine protein measurements
- CRP and ESR when they previously reflected disease activity
- Medication-specific safety tests
- Troponin, imaging, pulmonary testing, or neurologic studies when clinically indicated
Eosinophil counts may be nearly zero during anti-interleukin-5 treatment. This expected pharmacologic effect does not prove complete remission. Conversely, a small rise does not automatically mean systemic relapse; asthma, allergy, infection, and medication changes can alter the count.
ANCA titers are not reliable enough to dictate treatment in isolation. Clinicians look for a coherent change in symptoms, examination, organ tests, and imaging. The goal is to distinguish active vasculitis from persistent damage, asthma symptoms, treatment side effects, and unrelated illness.
Before testing, patients should report all corticosteroid doses and biologic treatment dates. They should also bring prior laboratory reports, because the highest pretreatment eosinophil count and earlier urine or cardiac findings may be more informative than the current panel.
References
- Evidence-Based Guideline for the diagnosis and management of eosinophilic granulomatosis with polyangiitis 2023 (Guideline)
- 2022 American College of Rheumatology/European Alliance of Associations for Rheumatology Classification Criteria for Eosinophilic Granulomatosis with Polyangiitis 2022 (Guideline)
- EULAR recommendations for the management of ANCA-associated vasculitis: 2022 update 2024 (Guideline)
- 2021 American College of Rheumatology/Vasculitis Foundation Guideline for the Management of Antineutrophil Cytoplasmic Antibody-Associated Vasculitis 2021 (Guideline)
- Eosinophilic granulomatosis with polyangiitis 2023 (Review)
- Eosinophilic Granulomatosis with Polyangiitis: Latest Findings and Updated Treatment Recommendations 2023 (Review)
Disclaimer
An EGPA blood test panel cannot establish or exclude the diagnosis without clinical assessment and organ-specific evaluation. Results may be altered by corticosteroids, biologic treatment, infection, allergy, and other eosinophilic diseases. New chest pain, breathing difficulty, fainting, weakness, numbness, coughing blood, reduced urine, or severe abdominal symptoms require prompt medical care.