Urine Creatinine Spot Test is most useful when it is read as part of a clinical pattern, not as a stand-alone verdict. In practical terms, a spot urine creatinine test can quickly show whether urine contains expected substances or clues that point toward infection, kidney disease, diabetes, bleeding, dehydration, liver or biliary problems, or another process. The result can be highly informative, but collection quality, urine concentration, recent foods and medicines, and the time between collection and testing can change what appears on the report. That is why an abnormal result often leads to confirmation rather than an immediate diagnosis. This guide explains what the test measures, what common normal and abnormal patterns mean, which false results matter, how clinicians connect the findings with symptoms and other tests, and when a result deserves faster medical attention.
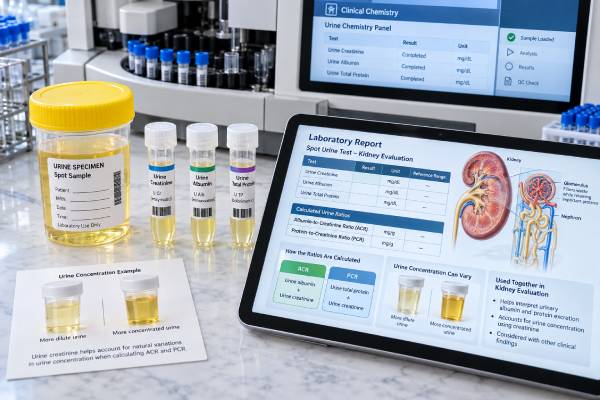
- What it measures: creatinine concentration in a single urine specimen; by itself it is strongly affected by urine dilution, but it is especially useful as the denominator in albumin-to-creatinine and protein-to-creatinine ratios.
- Typical normal finding: there is no single universal “normal” spot concentration because hydration, muscle mass, age, sex, diet, and collection timing alter the value; ratio tests are interpreted with their own thresholds.
- What an abnormal result may mean: a low spot creatinine often means dilute urine but may also reflect low muscle mass; a high concentration often means concentrated urine; the clinically important result is frequently the albumin/creatinine or protein/creatinine ratio rather than creatinine alone.
- Common reasons results mislead: extreme dilution or concentration, unusual muscle mass, recent intense exercise, collection errors, and assay interference can make ratios less representative; repeat first-morning samples can improve confidence when results are borderline.
- When follow-up matters: spot urine creatinine alone is almost never an emergency; urgency depends on associated findings such as acute kidney injury, severe electrolyte problems, oliguria, major edema, or systemic illness.
Table of Contents
- What the Test Shows
- Normal and Abnormal Results
- Common Causes of Abnormal Findings
- Accuracy, Interference, and False Results
- How Results Are Confirmed and Used
- Practical Interpretation Examples
- How to Prepare and Collect a Useful Sample
- When to Seek Medical Care
What the Test Shows
The test is designed to answer a focused question: creatinine concentration in a single urine specimen; by itself it is strongly affected by urine dilution, but it is especially useful as the denominator in albumin-to-creatinine and protein-to-creatinine ratios. A urine result is different from a blood result because urine is the product of filtration, tubular reabsorption and secretion, water balance, and time spent in the bladder. That means a substance can be absent from blood yet appear in urine, or be present in blood without appearing strongly in urine. Hydration can also dilute a real abnormality or concentrate an otherwise small amount.
Most routine testing starts with physical inspection and a reagent strip. Each dipstick pad contains chemicals that change color when a target reaction occurs. Laboratories may read the strip with an automated analyzer, while office or home tests may use a printed color chart. Microscopy adds another layer by looking directly for cells, casts, crystals, organisms, and debris. The distinction matters because a chemical signal is not always the same as seeing the actual substance. For example, a heme reaction may be positive even when intact red blood cells are not visible.
A useful interpretation therefore asks three questions: What did the test detect? Is the finding plausible in this clinical setting? Does it need confirmation with a more specific method? The broader urine albumin dipstick and albuminuria can help place a single marker in context when several pads are abnormal at once.
Results are usually semiquantitative. Terms such as negative, trace, small, moderate, large, 1+, 2+, or 3+ are screening categories, not precise concentrations. The exact cutoff for each category varies by strip manufacturer and laboratory. When a numerical threshold drives diagnosis or treatment, clinicians generally choose a quantitative laboratory test rather than estimating from color intensity.
Normal and Abnormal Results
For this topic, the usual reference pattern is there is no single universal “normal” spot concentration because hydration, muscle mass, age, sex, diet, and collection timing alter the value; ratio tests are interpreted with their own thresholds. A reference range describes what is expected under specified conditions; it does not mean every result outside that range represents disease. Hydration, recent exercise, fever, fasting, pregnancy, medications, and specimen timing can shift urine chemistry without causing permanent organ damage.
An abnormal pattern is a low spot creatinine often means dilute urine but may also reflect low muscle mass; a high concentration often means concentrated urine; the clinically important result is frequently the albumin/creatinine or protein/creatinine ratio rather than creatinine alone. The importance of that finding depends on how strong it is, whether it repeats, and whether other markers point in the same direction. A single trace result in a concentrated sample may be far less important than the same finding on several properly collected specimens, particularly when symptoms or blood tests are also abnormal.
| Result pattern | How to think about it | Typical next step |
|---|---|---|
| Negative or expected | Lowers the likelihood of conditions detected well by this test, but does not exclude every disorder. | Usually no action beyond the reason the test was ordered. |
| Trace or borderline | May be temporary, concentration-related, or early disease. | Review collection, hydration, symptoms, and repeat if clinically relevant. |
| Clearly positive | More likely to represent a real biologic finding, especially when matching symptoms or other markers. | Confirm with a targeted laboratory test or microscopy. |
| Persistent on repeat testing | Raises concern for an ongoing process rather than a transient change. | Evaluate the underlying cause and quantify the abnormality when possible. |
Do not compare a result with a generic internet range if the laboratory provides its own method-specific reference interval. Dipstick brands use different chemistry and category cutoffs. The report, clinical setting, and reason for testing should take priority.
Common Causes of Abnormal Findings
Common explanations include hydration status, diuretic use, muscle mass, recent meat intake, timing, kidney handling, and collection quality; creatinine in a ratio helps correct for concentration but does not eliminate all biologic variability. The list is intentionally broad because the same urine finding can arise through different mechanisms. The most useful clue is usually the combination of symptoms, other urine markers, and whether the abnormality persists.
A clinician often sorts causes into four practical groups. Urinary-tract causes include infection, stones, obstruction, bleeding, and inflammation. Kidney causes include glomerular disease, tubular injury, and impaired concentration. Metabolic or systemic causes include diabetes, ketosis, hemolysis, muscle injury, or liver and biliary disease. Temporary or non-disease causes include exercise, fasting, dehydration, foods, medications, and collection contamination.
Context can sharply change the interpretation. Burning urination, frequency, and suprapubic discomfort make infection markers more meaningful. Flank colic makes stones more plausible. Edema, high blood pressure, reduced eGFR, or persistent albumin/protein makes kidney disease more important. Polyuria, thirst, weight loss, or known diabetes changes the meaning of glucose and ketones. Jaundice changes the significance of dark urine or bilirubin. Heavy exercise or muscle pain changes the meaning of a heme-positive specimen.
The goal is not to attach a diagnosis to one colored square. It is to identify the mechanism most consistent with the whole pattern and then use a more specific test where needed. For related patterns, kidney disease urinalysis can be useful when that marker is part of the same result set.
Accuracy, Interference, and False Results
Urinalysis is fast, inexpensive, and clinically useful, but it is unusually sensitive to pre-analytical error. For this test, important limitations include extreme dilution or concentration, unusual muscle mass, recent intense exercise, collection errors, and assay interference can make ratios less representative; repeat first-morning samples can improve confidence when results are borderline. A technically correct result can still be misleading if the specimen was collected poorly, stored too long, or interpreted without the patient’s medications and symptoms.
Freshness matters because urine changes after it leaves the body. Cells and casts can break down, bacteria can multiply, glucose may fall as cells or organisms consume it, pH may rise, and light-sensitive compounds such as bilirubin can degrade. Refrigeration can preserve some components but may also cause crystals to precipitate; a refrigerated sample often needs to return to the laboratory’s specified temperature and be mixed before analysis.
Chemical interference is also marker-specific. Vitamin C can suppress oxidation-based reactions on some dipsticks. Strong oxidizing contaminants can push other pads falsely positive. Highly pigmented urine can make color interpretation difficult. Very concentrated urine may increase the apparent amount of some substances simply because there is less water, while extreme dilution can make a real abnormality harder to detect.
A surprising result should trigger a quality check before a disease label: Was this a clean-catch sample? Was there menstruation or vaginal contamination? Was the specimen tested promptly? Were supplements or medicines taken? Does microscopy agree with the strip? Does a quantitative test agree? These questions prevent unnecessary treatment and reduce the risk of missing a true abnormality hidden by interference.
How Results Are Confirmed and Used
The usual follow-up is to interpret spot creatinine with the paired analyte and clinical question; for CKD, uACR is commonly categorized as <30, 30–300, or >300 mg/g and persistent abnormality matters more than one isolated value. Confirmation is especially important when a result could change treatment, suggest chronic organ damage, or lead to antibiotics, imaging, emergency care, or specialist referral.
A repeat urinalysis is often reasonable for an unexpected mild abnormality after a temporary trigger has resolved. Repeating the same test is most useful when the second specimen is better controlled—for example, a fresh clean-catch sample collected away from menstruation and after avoiding unusually strenuous exercise. For persistent abnormalities, clinicians often move from a screening method to a quantitative or more specific method rather than repeatedly relying on semiquantitative dipsticks.
Microscopy answers questions the strip cannot. It can confirm whether heme positivity comes with red blood cells, show pyuria when leukocyte esterase is uncertain, identify casts that point toward renal parenchymal disease, and reveal crystals or epithelial cells that change the differential diagnosis. Culture identifies organisms and antibiotic susceptibility when bacterial infection needs confirmation. Blood tests add information about kidney filtration, glucose control, acid-base status, liver function, hemolysis, or muscle injury.
Trend matters. One abnormal specimen during fever, dehydration, or strenuous exercise may normalize. A result that remains abnormal over weeks or months carries more weight. For kidney disease in particular, persistence and quantitative albumin testing are central to risk assessment. The related topic of complete urinalysis may help explain how a specific companion marker is interpreted when follow-up testing is ordered.
Practical Interpretation Examples
A useful way to read this result is to compare several real-world patterns rather than memorize one cutoff. Pattern one: an isolated mild abnormality in a person who feels well. If the sample was collected after hard exercise, during a short illness, after unusual fluid intake, or with possible contamination, repeating a fresh specimen may be more informative than acting on the first result. The key question is whether the finding disappears when the temporary factor is gone.
Pattern two: the same abnormality appears with matching symptoms. In that setting, the pretest probability is higher. A result consistent with hydration status or another plausible cause deserves targeted confirmation rather than repeated screening alone. Symptoms can also determine speed: a laboratory abnormality that is routine in an asymptomatic person may need same-day evaluation when paired with fever, severe pain, vomiting, jaundice, marked weakness, or reduced urine output.
Pattern three: several urine markers point toward the same organ system. This is generally more informative than one isolated pad. For example, chemistry plus microscopy can show whether a signal is accompanied by cells or casts, while a ratio test can distinguish a concentration effect from persistent excess excretion. Concordant findings increase confidence; discordant findings are a reason to check specimen quality, assay limitations, and an alternative mechanism.
Pattern four: the result stays abnormal on properly collected repeat samples. Persistence changes the question from “Could this be temporary?” to “What underlying process explains it?” At that point, quantitative testing, blood work, imaging, culture, or specialist evaluation may be appropriate depending on the marker. This stepwise approach avoids both extremes: dismissing a meaningful signal and overreacting to a single imperfect screen.
How to Prepare and Collect a Useful Sample
Most urine tests do not require fasting unless another test ordered at the same time does. The best preparation is to follow the collection instructions exactly and tell the clinician or laboratory about medications, supplements, pregnancy, menstruation, intense exercise, and recent illness when those factors could affect interpretation.
For a clean-catch midstream specimen, wash or clean the genital area as instructed, begin urinating into the toilet, then collect the middle portion without touching the inside of the cup or lid. Finish voiding into the toilet. This method reduces contamination from skin, vaginal secretions, and distal urethral material. In some settings, a first-morning specimen is preferred because it is more concentrated and less influenced by recent fluid intake; in other settings, a random sample is appropriate.
Do not deliberately dehydrate yourself to make urine “stronger,” and do not drink excessive water just before testing unless specifically instructed. Either extreme can distort concentration-dependent results. If the specimen is collected at home, deliver it according to the laboratory’s time and temperature instructions. A sample left at room temperature for hours may no longer represent the urine at the time it was passed.
Home dipsticks add another source of variability. Use an unexpired product, store it as directed, fully wet the pads, remove excess urine as instructed, and read each pad at the exact time specified. Reading too early or too late can change the color category. A home result that is strongly abnormal, repeatedly abnormal, or inconsistent with how you feel should be confirmed through a medical laboratory rather than used as the sole basis for treatment.
When to Seek Medical Care
The result should be treated more urgently when spot urine creatinine alone is almost never an emergency; urgency depends on associated findings such as acute kidney injury, severe electrolyte problems, oliguria, major edema, or systemic illness. These warning signs matter because they can indicate obstruction, kidney infection, severe metabolic illness, significant bleeding, acute kidney injury, or another condition where delay can increase risk.
Contact a clinician soon for a new abnormal result that persists on repeat testing, especially with urinary pain, swelling, high blood pressure, unexplained weight loss, recurrent fever, reduced urine output, or known kidney, liver, blood, or metabolic disease. People who are pregnant, immunocompromised, have a single functioning kidney, or have a history of complicated urinary disease may need a lower threshold for evaluation.
For a result discovered during routine screening without symptoms, the next step is usually not emergency treatment. It is confirmation and risk-based evaluation. Keep the original laboratory report, note whether the sample was collected during illness or menstruation, and list medicines and supplements. Those details can explain an isolated abnormality and help a clinician decide whether to repeat the test, order a quantitative measurement, or investigate a specific organ system.
The safest summary is simple: urine screening works best as an early signal. A normal result can be reassuring in the right setting, and an abnormal result can be highly useful, but important decisions should rest on the pattern, specimen quality, symptoms, and confirmatory testing rather than on one dipstick pad alone.
References
- KDIGO 2024 CKD Guideline 2024 (Guideline)
- Diagnostic accuracy of urine dipstick testing for albumin-to-creatinine ratio and albuminuria: A systematic review and meta-analysis 2021 (Systematic Review)
- Evaluation of pre-analytical factors impacting urine test strip and chemistry results 2025 (Review)
- Urinary Biomarkers and Point-of-Care Urinalysis Devices for Early Diagnosis and Management of Disease: A Review 2023 (Review)
- Urinalysis 2023 (Review)
- Advances and Progress in Automated Urine Analyzers. 2024 (Review)
Disclaimer
This information is for general education and does not diagnose or treat any condition. Urine test results should be interpreted with symptoms, medical history, medications, and the laboratory’s own reference ranges. Seek urgent medical care for severe symptoms or the warning signs described above.