
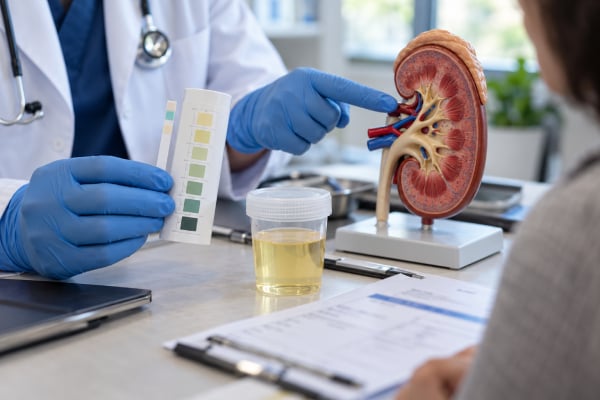
A positive urine albumin dipstick means albumin was detected in the sample, but it does not by itself prove chronic kidney disease or show exactly how much albumin is being lost. Albumin is a blood protein that normally stays largely inside the circulation. When the kidney’s filtration barrier is damaged—or when temporary stress raises albumin excretion—more albumin can enter urine. Dipstick methods are useful for screening, especially when rapid or point-of-care testing is needed, but urine concentration can make albumin appear higher or lower than it truly is. The preferred confirmatory test is a urine albumin-to-creatinine ratio (uACR), which adjusts for urine concentration. Persistent albuminuria is clinically important because it can be an early sign of kidney disease and is associated with higher cardiovascular and kidney-progression risk. Repeat testing is often necessary before a diagnosis is made.
- Positive albumin dipstick: Shows albumin is present above the strip’s detection threshold, but the result is semiquantitative and affected by urine concentration.
- Best confirmation: A spot uACR is preferred; less than 30 mg/g is usually normal to mildly increased, 30–299 mg/g moderately increased, and 300 mg/g or more severely increased.
- One positive test is not enough: Exercise, fever, UTI, severe hyperglycemia, heart failure, menstruation, and marked hypertension can temporarily raise urine albumin.
- Persistent albuminuria can signal kidney damage even when eGFR is normal and should be interpreted together with serum creatinine and eGFR.
- Dipstick protein and albumin are not identical: Standard protein strips are mainly sensitive to albumin but are less suitable than uACR for detecting early albuminuria.
Table of Contents
- What the Urine Albumin Dipstick Measures
- What a Positive Result Means
- Albuminuria Ranges and uACR
- Temporary Causes and False Results
- Albuminuria and Kidney Damage
- Who Should Be Tested and How Often
- Dipstick Versus Quantitative Testing
- What to Do After a Positive Test
What the Urine Albumin Dipstick Measures
A urine albumin dipstick uses a reagent pad that changes color when albumin is present above a certain concentration. Depending on the product, the result may be reported as negative, trace, 1+, 2+, or a semiquantitative albumin concentration. Some point-of-care systems also include a creatinine pad and estimate the albumin-to-creatinine ratio directly.
Albumin is made by the liver and circulates in blood. Healthy glomeruli—the microscopic filters in the kidneys—allow only very small amounts to pass into urine. Increased albumin excretion can occur when the filtration barrier becomes more permeable, when pressure within the glomerulus rises, or during temporary physiologic stress.
The important limitation is that a dipstick measures concentration in that particular urine sample. A person who is dehydrated may have a concentrated sample that makes albumin look more prominent, while high fluid intake can dilute the same amount of albumin and make it harder to detect.
This is why a dedicated urine albumin test is usually interpreted with creatinine rather than as albumin concentration alone. The ratio compensates partly for dilution and is more closely tied to clinical kidney-disease categories.
A standard total-protein dipstick is related but not identical. It is mainly sensitive to albumin, often at higher concentrations, and can miss early albuminuria. For CKD screening in adults at risk, sensitive albumin measurement and uACR are preferred.
What a Positive Result Means
A positive albumin dipstick means the urine contains enough albumin to cross that test’s detection threshold. The result is a screening signal, not a final diagnosis.
A positive result can represent:
- persistent kidney damage from diabetes, hypertension, glomerular disease, or another kidney disorder;
- temporary albumin leakage during acute illness or physiologic stress;
- a concentrated urine sample that exaggerates albumin concentration;
- contamination or another preanalytical problem;
- a true result that still needs quantitative staging.
The stronger the dipstick result, the more likely clinically important albuminuria is present, but there is substantial overlap. A “trace” or low-positive result can disappear on repeat testing, while a negative standard protein strip can miss albumin levels in the 30–299 mg/g uACR range.
The result becomes more meaningful when it persists and when other kidney findings are present. Albuminuria combined with reduced eGFR, hypertension, diabetes, edema, hematuria, or an active urine sediment raises the likelihood of kidney disease.
Albuminuria can also be a cardiovascular risk marker. Even within categories, higher uACR generally tracks with higher risk. That is one reason modern kidney assessment uses uACR not only to detect disease but also to help classify prognosis.
A confirmed albuminuria result therefore has more clinical value than the initial color change on a strip.
Albuminuria Ranges and uACR
The urine albumin-to-creatinine ratio (uACR) is the standard way to express albuminuria in a spot urine sample. It is usually reported in milligrams of albumin per gram of creatinine (mg/g) in the United States or milligrams per millimole (mg/mmol) in many other countries.
| uACR | Category | Meaning |
|---|---|---|
| <30 mg/g | A1 | Normal to mildly increased |
| 30–299 mg/g | A2 | Moderately increased albuminuria |
| ≥300 mg/g | A3 | Severely increased albuminuria |
The older terms “microalbuminuria” and “macroalbuminuria” are still encountered, but current guidelines generally use moderately and severely increased albuminuria. This avoids the mistaken idea that “microalbumin” is a different type of albumin molecule.
A spot uACR test is convenient and usually preferred over a timed 24-hour collection for routine screening. A first-morning sample can reduce variability, but a random sample is acceptable in many clinical settings.
uACR is not perfectly stable. Day-to-day biological variation can be substantial, so a single A2 result does not always represent persistent kidney damage. Clinicians commonly confirm albuminuria with repeat samples, often looking for at least two abnormal results out of three over a three- to six-month period when the situation is not urgent.
Very high uACR, rapid increases, nephrotic-range protein loss, or albuminuria accompanied by hematuria or falling eGFR may prompt faster evaluation rather than routine repeat testing alone.
Temporary Causes and False Results
Albumin excretion changes with physiology, illness, and sample concentration. A temporarily positive test does not necessarily mean chronic kidney damage.
Common situations that can raise urine albumin transiently include:
- strenuous exercise within the previous day;
- fever or acute systemic illness;
- urinary tract infection;
- marked hyperglycemia;
- severe or uncontrolled hypertension;
- heart failure or major fluid shifts;
- menstruation or blood contamination;
- significant dehydration.
These factors can be especially important when the result is only mildly abnormal. If the clinical situation is stable, repeating the test after the temporary factor resolves can prevent overdiagnosis.
False or misleading dipstick results can also come from urine chemistry and handling. Very concentrated urine can increase apparent albumin concentration. Very dilute urine can reduce sensitivity. Manual strips must be read at the manufacturer’s specified time; old strips, moisture exposure, and poor storage can alter performance.
Some “albumin dipsticks” are actually standard total-protein pads. Those pads are mainly sensitive to albumin but are less sensitive at low concentrations than dedicated albumin assays. Strongly alkaline urine can create false-positive protein results on some conventional protein strips, while non-albumin proteins may be underdetected.
Collection quality matters as well. A clean-catch sample helps reduce contamination. If a result is unexpected, clinicians often repeat it under ordinary hydration and without unusual exercise rather than trying to interpret a questionable specimen.
Albuminuria and Kidney Damage
Persistent albuminuria is a recognized marker of chronic kidney disease because it can reflect structural damage to the glomerular filtration barrier. It may appear before serum creatinine rises or eGFR falls, particularly in diabetes and some glomerular disorders.
Albuminuria and eGFR answer different questions. uACR measures kidney damage; eGFR estimates filtration. A person can have a normal eGFR and clinically important albuminuria, or a reduced eGFR with little albuminuria. Both should be assessed when evaluating CKD risk.
Common causes of persistent albuminuria include:
- diabetic kidney disease;
- hypertension-related kidney damage;
- glomerulonephritis;
- obesity-associated kidney stress;
- heart failure and vascular disease;
- inherited or structural kidney disorders;
- some medication-related or systemic diseases.
The pattern can suggest whether another kidney process needs consideration. Typical diabetic kidney disease often develops gradually. In contrast, rapidly rising albumin, heavy proteinuria, active urine sediment with red or white blood cells or cellular casts, or a rapid decline in eGFR may suggest an additional or alternative kidney disease.
Albuminuria is also used to guide treatment and monitoring. In people with CKD, a fall in uACR can indicate improvement in kidney risk after blood-pressure control or kidney-protective therapy, although day-to-day variation means trends should be interpreted over multiple measurements.
The key point is persistence. CKD generally requires evidence of kidney abnormality for at least three months. One positive dipstick can start the evaluation, but it should not automatically become a permanent diagnosis.
Who Should Be Tested and How Often
Albumin testing is most useful in people who have a meaningful risk of kidney disease. Diabetes, hypertension, cardiovascular disease, and known CKD are common reasons to measure uACR even when a routine dipstick is negative. The goal is to detect kidney damage early enough to guide treatment before filtration declines substantially.
In diabetes, current guidance recommends at least annual assessment of uACR and eGFR in everyone with type 2 diabetes and in people with type 1 diabetes after several years of disease, commonly beginning after five years. Testing may be more frequent when CKD is already present, uACR is high, eGFR is falling, or treatment changes are being monitored.
People with hypertension may also benefit from albumin testing because albuminuria helps identify kidney involvement and higher cardiovascular risk. A person can have normal serum creatinine yet still have persistent albumin leakage, so relying on blood tests alone can miss early disease.
For established CKD, monitoring frequency depends on both eGFR and albuminuria category. Someone with stable kidney function and low albumin may need relatively infrequent monitoring, while a person with severe albuminuria or advanced CKD may need testing several times per year. The exact schedule depends on the cause of kidney disease, medications, blood pressure, diabetes control, and whether results are changing.
Population-wide dipstick screening is more controversial. A low-cost strip can detect some people with previously unrecognized kidney disease, but standard protein dipsticks miss many cases of moderately increased albuminuria and can generate false positives in low-risk populations. Targeted uACR testing in higher-risk groups generally provides more clinically useful information.
Children require a different approach because normal excretion, body size, and causes of kidney disease differ from adults. Pediatric clinicians may repeat an initial positive dipstick using a first-morning urine sample and then obtain quantitative uACR or protein-to-creatinine testing when the abnormality persists.
Testing should also be repeated sooner than routine schedules when the clinical picture changes. New edema, rising blood pressure, falling eGFR, new hematuria, pregnancy-related concerns, or a medication that affects kidney hemodynamics can all justify reassessment. The purpose is not simply to collect more numbers, but to determine whether kidney damage is stable, improving, or progressing.
Dipstick Versus Quantitative Testing
Dipstick testing is attractive because it is fast, inexpensive, portable, and easy to use at the point of care. Quantitative laboratory uACR is more accurate for staging and follow-up.
| Feature | Albumin dipstick | Laboratory uACR |
|---|---|---|
| Speed | Minutes | Usually same day or laboratory turnaround |
| Result type | Qualitative or semiquantitative | Quantitative ratio |
| Adjusts for urine concentration | No, unless paired with creatinine pad | Yes |
| Best use | Screening when quantitative testing is not immediately available | Diagnosis, staging, confirmation, and monitoring |
| Positive result | Needs confirmation | Usually repeated to confirm persistence |
Modern semiquantitative point-of-care systems that measure both albumin and creatinine perform better than albumin concentration alone. In one 2022 evaluation, semiquantitative ACR showed sensitivity around 87%–91% and specificity around 71%–78% for albuminuria compared with quantitative testing. That level can be useful for screening, but it still leaves room for false negatives and false positives.
Laboratory recommendations generally state that semiquantitative tests should detect at least 85% of people with moderately increased albuminuria to be suitable for screening, and positive results should be confirmed with quantitative laboratory analysis.
Standard protein dipsticks should not be used as a substitute for sensitive albumin screening in people at risk for CKD. A negative protein pad can coexist with a clinically important uACR above 30 mg/g.
Point-of-care and home-capable albumin systems can improve access, but their usefulness depends on following the instructions closely. The strip must be stored correctly, exposed to urine for the specified time, and read with the intended instrument or color scale. If the device estimates both albumin and creatinine, the ratio is more informative than albumin concentration alone. Even then, a screening result should not be used to self-diagnose CKD or change prescription therapy without confirmation.
When results from different methods disagree, quantitative laboratory uACR generally takes priority for staging. Differences can arise from urine dilution, analytical thresholds, timing, and the fact that conventional protein dipsticks and albumin-specific assays are not measuring exactly the same thing. Repeating the test under stable conditions with a laboratory method often resolves the discrepancy. If albumin remains elevated, the clinician can then interpret the value alongside eGFR, blood pressure, diabetes status, and the urine sediment. That sequence avoids both false reassurance from a negative screening strip and unnecessary alarm from one isolated low-level positive result. It also creates a reliable baseline for future monitoring, which is more useful than comparing loosely graded dipstick colors over time from different samples, methods, or different testing devices.
What to Do After a Positive Test
A practical follow-up plan is to confirm the result, look for temporary causes, and assess kidney function.
Common next steps include:
- Confirm with quantitative uACR. If the original test already estimated ACR at the point of care, a laboratory uACR can verify the category.
- Repeat abnormal albumin measurements. When the situation is stable, repeat testing over several months determines whether albuminuria is persistent.
- Check serum creatinine and eGFR. Albuminuria and filtration should be interpreted together.
- Measure blood pressure and review diabetes status. Hypertension and diabetes are major causes and treatment targets.
- Review temporary factors and medicines. Infection, exercise, acute illness, NSAID use, and other factors may change the result or kidney risk.
- Look for atypical kidney findings. Significant hematuria, cellular casts, rapidly falling eGFR, nephrotic syndrome, or rapidly increasing protein may justify nephrology referral.
People with diabetes, hypertension, cardiovascular disease, or known CKD often need periodic uACR monitoring even after the initial result is clarified. The frequency depends on kidney stage and treatment plan.
Seek prompt evaluation for rapidly worsening swelling, shortness of breath, very low urine output, visible blood, severe hypertension symptoms, or a rapid decline in kidney function. A positive albumin strip alone is rarely an emergency, but the symptoms and accompanying kidney findings can be.
The main takeaway is simple: use the dipstick to detect a possible problem, then use uACR and eGFR to define it. This sequence reduces the risk of both missing early kidney disease and overreacting to a temporary positive result.
References
- KDIGO 2024 CKD Guideline 2024 (Guideline)
- Guidelines and Recommendations for Laboratory Analysis in the Diagnosis and Management of Diabetes Mellitus 2023 (Guideline)
- The EFLM European Urinalysis Guideline 2023 2024 (Guideline)
- Testing for Chronic Kidney Disease 2024
- Performance evaluation of Hipee S2 point-of-care testing urine dipstick analyser: a cross-sectional study. 2022
Disclaimer
A positive urine albumin dipstick is a screening result and does not by itself diagnose chronic kidney disease. Albuminuria should be confirmed and interpreted with uACR, eGFR, blood pressure, symptoms, medications, and medical history. Seek prompt medical care for rapidly worsening swelling, breathing difficulty, very low urine output, or rapidly worsening kidney-function results.





