A urine albumin-creatinine ratio (uACR) test is one of the most useful ways to look for early kidney damage, especially in people with diabetes, high blood pressure, cardiovascular disease, or another reason to be at risk for chronic kidney disease (CKD). The test measures albumin, a blood protein that normally stays in the bloodstream, and compares it with urine creatinine to correct for how concentrated or dilute the urine is. That ratio makes a single urine sample much more informative than urine albumin concentration alone. A uACR below 30 mg/g is generally considered normal to mildly increased, while repeated values of 30 mg/g or higher indicate albuminuria. One abnormal result does not automatically mean chronic kidney disease because exercise, fever, infection, dehydration, marked hyperglycemia, menstruation, or temporary illness can raise albumin excretion. The result matters most when it is confirmed and interpreted together with estimated glomerular filtration rate (eGFR), medical history, blood pressure, and trends over time.
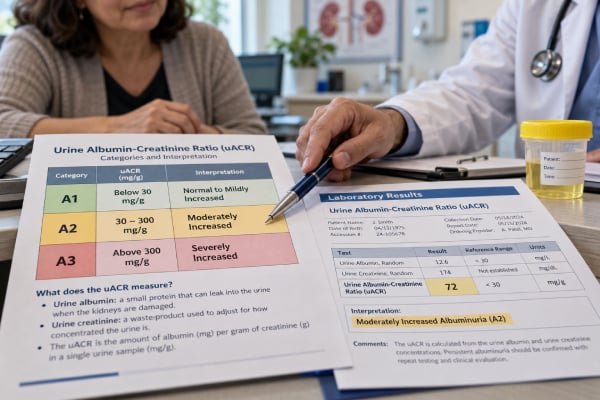
- A uACR below 30 mg/g is usually considered normal to mildly increased; 30–299 mg/g is moderately increased, and 300 mg/g or more is severely increased.
- A spot urine sample is usually sufficient; a first-morning sample can reduce day-to-day variation when confirmation is needed.
- A single high result should usually be repeated because exercise, infection, fever, menstruation, and temporary blood sugar or blood pressure changes can raise uACR.
- Persistent uACR elevation can signal kidney damage even when eGFR is still normal.
- Very high or rapidly rising uACR, falling eGFR, blood in the urine, swelling, or other concerning findings may require earlier kidney evaluation.
Table of Contents
- What the uACR test measures
- uACR normal range and albuminuria categories
- Why the test is ordered
- Preparation and urine collection
- What causes a high uACR
- How to interpret and confirm results
- What to do after an abnormal uACR
What the uACR test measures
The uACR test answers a practical question: how much albumin is appearing in the urine relative to the urine’s creatinine concentration? Albumin is a relatively large protein made by the liver. Healthy glomeruli—the kidney’s microscopic filtering units—keep almost all albumin in the bloodstream. When the filtration barrier becomes damaged or unusually permeable, more albumin can pass into urine.
Urine concentration changes constantly with fluid intake, sweating, medications, and time of day. A plain urine albumin value can therefore look lower in dilute urine and higher in concentrated urine even when the underlying albumin loss is similar. Creatinine is released into urine more steadily from muscle metabolism. Dividing albumin by creatinine provides a concentration-corrected estimate, usually reported as milligrams of albumin per gram of creatinine (mg/g). Some laboratories report milligrams per millimole (mg/mmol).
For most routine CKD screening and follow-up, uACR is preferred to a 24-hour urine collection. A spot sample is simpler and avoids the common collection errors that occur when someone misses a void during a 24-hour period. If a result is unexpected or precise daily excretion is clinically important, a clinician may still use a 24-hour urine albumin test.
uACR measures albumin, not every protein in urine. That distinction matters. Some kidney conditions, especially certain tubular disorders and monoclonal light-chain disorders, can produce substantial non-albumin protein. In those situations, a urine protein-creatinine ratio or specialized protein studies may add information.
uACR normal range and albuminuria categories
The standard adult categories are based on the amount of albumin relative to creatinine. They describe risk categories, not a simple healthy-versus-diseased switch.
| uACR | Category | General meaning |
|---|---|---|
| <30 mg/g | A1, normal to mildly increased | Usually below the diagnostic threshold for albuminuria, though lower values can still carry risk in context. |
| 30–299 mg/g | A2, moderately increased | Abnormal if persistent; common in early diabetic and hypertensive kidney disease. |
| ≥300 mg/g | A3, severely increased | Higher kidney and cardiovascular risk and a stronger signal for significant glomerular injury. |
In SI units, the approximate category boundaries are below 3 mg/mmol, 3–29 mg/mmol, and 30 mg/mmol or higher. Exact laboratory conventions vary slightly.
Older terminology called A2 albuminuria microalbuminuria and A3 albuminuria macroalbuminuria. Those terms are still common, but they can be misleading because the albumin molecule is not “micro.” The difference is the amount excreted. Modern kidney guidelines generally use “moderately increased” and “severely increased” albuminuria instead. A reader who receives an older-style report may find the albuminuria categories useful for translating the language.
A uACR below 30 mg/g should not be treated as proof that kidney disease is absent. CKD can exist with little albuminuria, for example in some tubulointerstitial disorders, structural kidney disease, or later vascular disease. Conversely, a value above 30 mg/g is not enough by itself to prove chronic disease. Persistence for at least three months, or other evidence of lasting kidney damage, is what makes the finding chronic.
Why the test is ordered
Clinicians order uACR primarily to detect, classify, and monitor kidney damage. It is especially valuable because albumin leakage can appear before the blood creatinine level rises or eGFR falls substantially.
People with diabetes are a major group for routine testing. Current diabetes standards recommend at least annual assessment of uACR and eGFR in people with type 2 diabetes and in people with type 1 diabetes of at least five years’ duration. Testing is often more frequent once CKD is present because the combination of albuminuria level and eGFR helps determine kidney risk and monitoring frequency. A broader diabetic kidney disease urine panel can include uACR with other urine findings when the clinical picture is more complex.
High blood pressure, cardiovascular disease, a family history of kidney failure, obesity, older age, prior acute kidney injury, and certain systemic diseases can also increase the reason to test. The purpose is not just diagnosis. uACR is a prognostic marker: as albuminuria rises, the risks of CKD progression, cardiovascular events, and mortality generally rise as well.
The test is also useful after treatment begins. A falling uACR can be one sign that therapy is reducing stress on the kidneys. Clinicians may follow uACR after improving blood pressure control, starting a renin-angiotensin system blocker, or using kidney-protective diabetes therapies when appropriate. The goal is not to chase a single number from week to week; biological variability is too large for that. Trends across properly collected samples are more meaningful.
Preparation and urine collection
Most uACR tests require no fasting and no special diet. The laboratory usually needs a clean urine sample in a sterile cup. A random sample obtained during a clinic visit is acceptable for screening, but a first-morning void is often preferred for confirmation because it is less influenced by recent activity and fluid intake.
To improve the chance of a representative result:
- Avoid unusually strenuous exercise for about 24 hours before the sample when practical.
- Tell the clinician about fever, urinary symptoms, acute illness, or a recent major change in blood sugar or blood pressure.
- If menstruating, ask whether the sample should be delayed, especially if contamination is likely.
- Follow clean-catch instructions if the laboratory provides them.
- Do not deliberately dehydrate yourself or drink excessive water just to change the urine concentration.
Certain temporary states can increase albumin excretion. Heavy exercise, a urinary tract infection, marked hyperglycemia, uncontrolled hypertension, fever, heart failure exacerbation, and acute illness are common examples. These factors do not make the test useless, but they affect when a result should be repeated.
The lab measures urine albumin and urine creatinine, then calculates the ratio. For example, if the albumin concentration and creatinine concentration produce a ratio of 45 mg/g, the result falls in the A2 category even if the urine looked completely normal. Albuminuria is usually invisible to the eye.
What causes a high uACR
Persistent high uACR most often reflects increased leakage of albumin through the kidney’s glomerular filtration barrier. Diabetes and hypertension are common causes, but they are not the only ones.
Diabetic kidney disease can gradually increase albumin excretion as prolonged hyperglycemia and related metabolic changes damage the glomeruli. High blood pressure can injure small kidney blood vessels and raise pressure within glomeruli. Because the two conditions often coexist, a high uACR may reflect several mechanisms at once.
Other important causes include glomerulonephritis, IgA nephropathy, lupus nephritis, focal segmental glomerulosclerosis, membranous nephropathy, and other primary or systemic glomerular diseases. Severe obesity, smoking, sleep apnea, cardiovascular disease, and heart failure can also be associated with albuminuria. Pregnancy requires separate interpretation because albumin or protein in urine may be evaluated in the context of preeclampsia.
A very high uACR can occur in nephrotic-range protein loss, but uACR alone does not diagnose nephrotic syndrome. Clinicians look at the magnitude of protein loss, serum albumin, edema, lipids, kidney function, and the underlying disease. If broad urine protein is markedly elevated, the nephrotic-range proteinuria framework may be more appropriate.
Temporary causes are common enough that repeat testing matters. Someone who completes an intense endurance event and has a uACR of 80 mg/g the next morning may return to below 30 mg/g after recovery. Similarly, a urinary infection can transiently increase albumin. The clinical question is whether albuminuria persists when temporary influences have resolved.
How to interpret and confirm results
A good interpretation uses the number, the trend, and the context. The same uACR can mean different things in different people.
For example, a first uACR of 42 mg/g in a person with diabetes is abnormal but not enough to establish persistent albuminuria. Because urine albumin varies considerably from day to day, clinicians commonly confirm an elevated value with additional specimens over the next several months. Diabetes guidance notes that two of three specimens collected over roughly three to six months should be abnormal before labeling moderately or severely increased albuminuria, unless the clinical situation makes persistence obvious.
A uACR of 650 mg/g carries more concern than 42 mg/g, especially if it is repeated or accompanied by a falling eGFR. Yet even severe albuminuria should be interpreted with urine sediment and other data. Blood or cellular casts in urine, a rapid rise in protein, an abrupt drop in kidney function, or systemic symptoms can suggest a kidney disorder other than typical diabetic kidney disease.
The relationship with eGFR is especially important. A person can have eGFR of 95 mL/min/1.73 m² and persistent uACR of 120 mg/g. If that albuminuria persists for at least three months, it can meet criteria for CKD despite preserved filtration. Conversely, a person with eGFR of 42 may have CKD even with uACR of 10 mg/g. The eGFR result and uACR describe different aspects of kidney health.
Large changes deserve confirmation rather than instant conclusions. Collection timing, acute illness, medications, blood pressure, and glycemic control can all affect the value. Laboratories also use different measurement systems, which can add analytical variation near category cutoffs.
What to do after an abnormal uACR
The first step after a mildly or moderately elevated uACR is usually to confirm that the finding is real and persistent. A clinician may repeat a first-morning uACR after exercise, infection, fever, menstruation, or other temporary factors have resolved. At the same time, eGFR, serum creatinine, blood pressure, diabetes control, and a urinalysis may be reviewed.
If albuminuria persists, management focuses on the cause and on reducing kidney and cardiovascular risk. Depending on the person, that can include better blood pressure control, glucose management, smoking cessation, moderation of excess dietary sodium, weight management, and kidney-protective medicines. ACE inhibitors or angiotensin receptor blockers are commonly used in people with hypertension and albuminuria when appropriate. SGLT2 inhibitors and other therapies may be indicated in certain people with diabetes or CKD based on eGFR, albuminuria, cardiovascular status, and medication tolerability. Treatment decisions belong with a clinician because potassium, kidney function, pregnancy status, and other medications can change what is safe.
Referral to a kidney specialist may be appropriate for rapidly rising albuminuria, very high persistent uACR, unclear cause, active urine sediment, resistant hypertension, rapidly falling eGFR, or advanced CKD. Significant swelling, shortness of breath, visibly bloody urine, severe hypertension, or symptoms of acute illness deserve prompt medical assessment rather than waiting for routine repeat testing.
A useful way to think about uACR is as a risk and damage marker, not a stand-alone diagnosis. It is strongest when repeated under stable conditions and paired with eGFR. Following both over time helps distinguish a one-off laboratory fluctuation from a meaningful kidney trend.
Practical examples of uACR interpretation
A few examples show why uACR is more useful as a trend than as an isolated label. Consider a person with type 2 diabetes whose uACR is 18 mg/g one year, 44 mg/g during a week of poor glucose control, and 22 mg/g on a first-morning repeat two months later. The temporary A2 result deserves attention, but the follow-up does not establish persistent albuminuria. The clinician would continue routine surveillance and address the factors that may have driven the temporary increase.
Now consider someone with hypertension whose first-morning uACR values are 85, 110, and 96 mg/g over six months. Even if eGFR remains 82 mL/min/1.73 m², the repeated A2 pattern is meaningful kidney damage and carries cardiovascular implications. That person may need tighter risk-factor management and ongoing monitoring rather than reassurance based only on preserved filtration.
A third pattern is a uACR of 1,200 mg/g with new ankle swelling. That is not simply “a little albumin.” It is severe albuminuria and may reflect substantial glomerular disease. The next steps would usually include serum creatinine/eGFR, serum albumin, quantitative protein assessment, urinalysis with sediment, blood pressure evaluation, and consideration of nephrology referral. If the rise was abrupt, clinicians would also consider causes beyond typical diabetic or hypertensive CKD.
Common interpretation mistakes include comparing results reported in different units without conversion, assuming any value under 30 mg/g means zero risk, diagnosing chronic kidney disease from a single sample, and judging treatment response from very small short-term changes. It is also a mistake to ignore the urine collection context. A sample obtained immediately after strenuous exercise or during a urinary infection may not represent baseline albumin excretion.
For long-term monitoring, it helps to compare like with like: similar collection timing, preferably the same laboratory when practical, and repeat testing after major transient influences have passed. A change in albuminuria is most useful when it is large enough and persistent enough to exceed expected day-to-day variation. Clinicians then interpret that change alongside blood pressure, eGFR, potassium, diabetes control, medication changes, and symptoms.
Finally, uACR is not a home “score” that should be chased daily. Kidney risk develops over months and years, and treatment decisions depend on the overall pattern. The practical goal is to detect sustained albumin leakage early, identify why it is happening, and use that information to protect kidney and cardiovascular health.
References
- KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease 2024 (Guideline)
- 11. Chronic Kidney Disease and Risk Management: Standards of Care in Diabetes-2026 2026 (Guideline)
- Urine Albumin Measurements in Clinical Diagnostics 2024 (Review)
- Albuminuria in Cardiovascular, Kidney, and Metabolic Disorders: A State-of-the-Art Review 2025 (Review)
- Systematic review and meta-analysis of biological variation data of urine albumin, albumin to creatinine ratio and other markers in urine 2024 (Systematic Review)
Disclaimer
This article is for general education and cannot diagnose the cause of an abnormal uACR. Result interpretation depends on repeat testing, eGFR, symptoms, medications, pregnancy status, and the rest of the clinical picture. Seek prompt medical care for severe swelling, shortness of breath, visible blood in urine, very low urine output, or other acute symptoms.