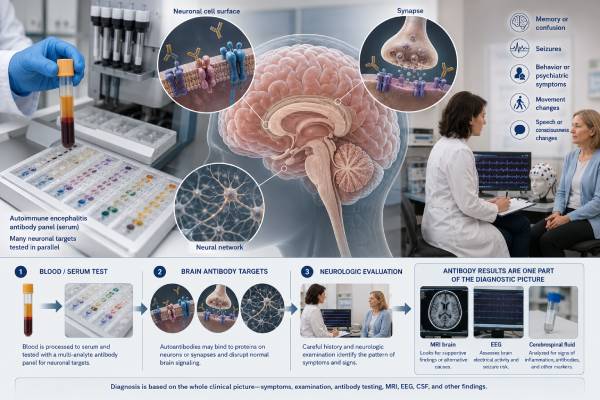
An autoimmune encephalitis antibody panel looks for immune proteins linked to inflammation or dysfunction in the brain. Doctors may order it when a person develops a rapid change in memory, behavior, awareness, movement, sleep, or seizure activity that cannot be explained by a more common cause. The panel can help identify conditions such as anti-NMDA receptor encephalitis, LGI1 antibody encephalitis, CASPR2 antibody disease, and some cancer-associated neurologic syndromes. However, the blood test is only one part of the evaluation. Results must be interpreted alongside cerebrospinal fluid testing, brain imaging, electroencephalography, infection studies, medication and toxin review, and the person’s clinical course. A positive antibody does not automatically prove autoimmune encephalitis, and a negative panel does not always exclude it. Accurate diagnosis depends on matching the antibody, specimen, laboratory method, symptoms, and other objective findings.
- Autoimmune encephalitis usually causes subacute neurologic or psychiatric symptoms that evolve over days to several weeks.
- Many patients need both serum and cerebrospinal fluid antibody testing because sensitivity and specificity differ by antibody.
- Cell-surface antibodies often guide diagnosis and treatment, while intracellular antibodies may point more strongly toward an underlying cancer.
- Low-level or isolated serum positives can be misleading when the clinical picture does not fit.
- A negative panel does not rule out antibody-negative autoimmune encephalitis or another treatable brain disorder.
Table of Contents
- When an Autoimmune Encephalitis Panel Is Used
- Major Brain Antibodies and Their Clinical Syndromes
- Paraneoplastic and Intracellular Antibodies
- Serum, Cerebrospinal Fluid, and Laboratory Methods
- How to Interpret Positive, Negative, and Discordant Results
- Tests Used Alongside the Antibody Panel
- Treatment, Cancer Screening, and Next Steps
When an Autoimmune Encephalitis Panel Is Used
Autoimmune encephalitis is a group of disorders in which the immune system targets proteins involved in brain signaling or is associated with inflammation directed against nerve cells. The illness often begins over less than three months. A person who was previously functioning normally may develop new short-term memory loss, confusion, seizures, abnormal movements, severe sleep disruption, hallucinations, paranoia, agitation, reduced speech, or fluctuating consciousness.
The exact presentation depends on the antibody and the part of the nervous system affected. Some people initially appear to have a primary psychiatric disorder. Others first present with repeated seizures, a rapidly progressive dementia-like syndrome, or unexplained autonomic instability such as major changes in heart rate, blood pressure, breathing, or temperature. Children may show behavioral regression, loss of language, unusual movements, or a sudden decline in school and daily functioning.
Doctors are more likely to consider an autoimmune encephalitis panel when symptoms are both new and rapidly progressive, especially when routine testing has not found a clear explanation. Findings that raise suspicion include:
- New seizures without a prior epilepsy history
- Rapid memory decline or altered mental status
- Psychiatric symptoms combined with neurologic abnormalities
- Abnormal movements, rigidity, catatonia, or reduced responsiveness
- Sleep disturbance with confusion, seizures, or autonomic changes
- Inflammatory changes in cerebrospinal fluid
- Brain MRI or EEG findings consistent with encephalitis
- A known or suspected tumor associated with a neurologic immune syndrome
The panel is not designed as a general screening test for chronic fatigue, isolated headache, long-standing anxiety, stable memory complaints, or nonspecific dizziness. Testing people with a very low clinical probability increases the chance that an unrelated or false-positive antibody result will cause confusion. A targeted autoimmune neurology antibody panel should be chosen according to the actual syndrome rather than ordered as a broad search for any possible explanation.
Autoimmune encephalitis can resemble viral encephalitis, toxic or metabolic illness, medication effects, primary psychiatric disease, epilepsy, stroke, neurodegenerative disease, or cancer-related complications. Because several of these alternatives are urgent and treatable, the antibody panel should not delay basic stabilization, infection testing, brain imaging, or seizure management.
Major Brain Antibodies and Their Clinical Syndromes
Many of the best-established autoimmune encephalitis antibodies target proteins on the surface of neurons or at synapses. These antibodies can interfere directly with signaling between brain cells. Their associated syndromes often respond to immunotherapy, although recovery may take months and treatment decisions depend on the full clinical picture.
NMDA receptor IgG: Anti-NMDA receptor encephalitis can affect people of any age but is especially recognized in children and young adults. Early symptoms may include anxiety, insomnia, unusual behavior, paranoia, or confusion. The illness can progress to seizures, reduced speech, abnormal facial or limb movements, catatonia, autonomic instability, and decreased consciousness. Ovarian teratoma is an important association in some patients, particularly postpubertal females, but many cases occur without a tumor. Cerebrospinal fluid is generally the preferred specimen for confirming clinically meaningful NMDA receptor IgG.
LGI1 IgG: LGI1 antibody encephalitis often affects middle-aged or older adults. It commonly causes short-term memory loss, confusion, and seizures. Brief, frequent jerking episodes involving the face and arm, called faciobrachial dystonic seizures, can precede more obvious encephalitis. Low blood sodium is common and may be a useful clue. MRI may show abnormalities in the medial temporal lobes, although normal imaging does not exclude the condition.
CASPR2 IgG: CASPR2 antibodies can be associated with limbic encephalitis, nerve hyperexcitability, neuropathic pain, autonomic symptoms, sleep disturbance, or Morvan syndrome. Some patients have both central and peripheral nervous system involvement. The significance of the result depends strongly on the clinical phenotype, antibody level, and testing method.
GABA-B receptor IgG: GABA-B receptor encephalitis often presents with severe or frequent seizures and limbic encephalitis. It has a meaningful association with small cell lung cancer, particularly in older adults or people with smoking exposure. A positive result usually prompts tumor evaluation as well as neurologic treatment.
AMPA receptor IgG: AMPA receptor encephalitis commonly causes confusion, memory loss, behavioral change, and seizures related to limbic system dysfunction. Some cases are paraneoplastic, with reported associations including lung, breast, and thymic tumors. Relapse may occur, so long-term clinical follow-up can be important.
GABA-A receptor IgG: This antibody can be associated with severe seizures, status epilepticus, encephalopathy, and multifocal brain MRI abnormalities. Results require careful confirmation because not every low-level finding has the same clinical meaning.
DPPX IgG: DPPX autoimmunity may cause encephalopathy, exaggerated startle, tremor or muscle jerks, sleep problems, and marked gastrointestinal symptoms such as diarrhea or weight loss. The combination of neurologic hyperexcitability and unexplained digestive symptoms can be a useful diagnostic clue.
Glycine receptor IgG: Glycine receptor antibodies are most strongly associated with progressive encephalomyelitis with rigidity and myoclonus, stiff-person-spectrum disorders, exaggerated startle, spasms, and brainstem symptoms. Some laboratories include this antibody in an encephalitis or movement-disorder panel rather than a basic brain antibody panel.
A laboratory panel may also include antibodies to mGluR1, mGluR5, IgLON5, neurexin-3 alpha, or other less common targets. Their interpretation is highly specialized. The presence of an antibody should be judged against a recognizable syndrome, not treated as a stand-alone diagnosis. An autoantibody blood test panel can identify immune markers, but it cannot substitute for neurologic examination and syndrome recognition.
Paraneoplastic and Intracellular Antibodies
Some neural antibodies target proteins located inside nerve cells rather than on the cell surface. These antibodies often act as markers of a T-cell-driven immune response and may be strongly associated with cancer. They are commonly called onconeural or paraneoplastic antibodies. Unlike many surface-antibody syndromes, the antibody itself may not be the direct cause of nerve-cell injury.
ANNA-1, also called anti-Hu: Anti-Hu can occur with encephalomyelitis, sensory neuronopathy, autonomic dysfunction, brainstem disease, or limbic encephalitis. It is strongly associated with small cell lung cancer. Neurologic symptoms may appear before the cancer is found.
Ma2 or Ta antibodies: These antibodies may be linked to limbic, diencephalic, or brainstem encephalitis. Testicular germ-cell tumors are a classic association in younger men, although other cancers can occur in different age groups.
CRMP5, also called CV2: CRMP5 antibodies can accompany encephalitis, chorea, neuropathy, optic nerve disease, or other mixed neurologic syndromes. Small cell lung cancer and thymoma are important associations.
Amphiphysin antibodies: Amphiphysin is associated with stiff-person-spectrum disease, encephalomyelitis, neuropathy, and other paraneoplastic neurologic syndromes. Breast cancer and small cell lung cancer are common tumor associations.
ANNA-2, also called anti-Ri: Anti-Ri may be associated with brainstem encephalitis, abnormal eye movements, jaw-opening dystonia, or other movement disorders. Breast and lung cancers are among the reported associations.
PCA-1, also called anti-Yo: Anti-Yo is best known for paraneoplastic cerebellar degeneration rather than classic encephalitis. It is associated most often with breast or gynecologic cancer. Its presence on a broad panel may redirect the workup toward a different neurologic syndrome.
GAD65 antibodies: High-titer GAD65 antibodies can be associated with stiff-person-spectrum disease, cerebellar ataxia, epilepsy, or limbic encephalitis. Lower levels are common in autoimmune diabetes and may not explain neurologic symptoms. The numerical level, specimen, method, and clinical syndrome are therefore essential for interpretation.
A positive intracellular antibody may have two major implications: it can support a paraneoplastic neurologic diagnosis, and it can signal the need for a focused cancer search. However, even a cancer-associated antibody does not identify the tumor’s location with certainty. Age, sex, smoking history, examination findings, and the known antibody-tumor relationship guide imaging and follow-up.
Treatment response also differs. Surface-antibody disorders often improve substantially with immunotherapy and tumor removal when applicable. Intracellular-antigen syndromes may respond less completely because irreversible nerve-cell injury can occur early. Rapid tumor detection and treatment remain important, but expectations should be individualized.
Serum, Cerebrospinal Fluid, and Laboratory Methods
Autoimmune encephalitis testing is usually most informative when serum and cerebrospinal fluid, or CSF, are submitted together. A lumbar puncture collects CSF from around the spinal cord. The two specimens provide different information, and the best specimen depends on the antibody.
For NMDA receptor IgG, CSF testing is particularly important. A serum-only result can miss a case or produce a result that is difficult to interpret. For LGI1 and CASPR2 antibodies, serum may sometimes be more sensitive, but CSF still helps assess inflammation and supports the diagnosis. Some paraneoplastic antibodies may be found in both specimen types. Laboratories commonly calculate whether antibody production is occurring within the central nervous system when paired samples and supporting measurements are available.
The routine CSF evaluation is separate from the antibody panel. It may include white blood cell count, protein, glucose, oligoclonal bands, immunoglobulin measurements, bacterial studies, viral testing, and other tests based on the situation. Mild lymphocytic inflammation or oligoclonal bands can support autoimmune encephalitis, but normal CSF does not exclude every subtype. LGI1 encephalitis, for example, may have little or no routine CSF inflammation.
Laboratories use several methods to detect neural antibodies:
Cell-based assays use cells engineered to express a specific target protein. They are widely used for antibodies against cell-surface and synaptic antigens. A positive result may be reported qualitatively or with a titer.
Tissue-based immunofluorescence exposes patient serum or CSF to brain tissue. The staining pattern can reveal a known antibody pattern or suggest an unclassified neural antibody. It can also help confirm that a cell-based result behaves like a true neural antibody.
Immunoblot or line blot methods are often used for intracellular paraneoplastic antibodies. These methods can produce weak bands that do not always represent clinically meaningful disease, so confirmatory testing and phenotype matching may be needed.
Immunoprecipitation, radioimmunoassay, or other specialized techniques may be used for selected antibodies such as GAD65 or voltage-gated calcium channel antibodies.
No single method is perfect. Commercial panels vary in which antibodies they include, the antigen form used, the cutoff for positivity, and whether confirmatory testing is performed. A negative result from one panel does not prove that every relevant antibody was assessed. Likewise, a weak positive on a single method may need confirmation in a specialized neuroimmunology laboratory.
Pretest probability matters. When a panel is ordered for a patient with a classic syndrome, a matching antibody is much more likely to be meaningful. When it is ordered for chronic, nonspecific symptoms without objective evidence of encephalitis, the same low-level result is more likely to be incidental or false positive.
How to Interpret Positive, Negative, and Discordant Results
A laboratory report may label an antibody as positive, negative, borderline, or indeterminate. Some reports include titers or quantitative values. Interpretation should begin with four questions: Does the patient have the expected syndrome? Was the right specimen tested? Is the laboratory method appropriate? Do other findings support active brain disease?
A positive result that matches the syndrome: This is the most useful situation. For example, CSF NMDA receptor IgG in a patient with rapidly progressive psychiatric symptoms, seizures, abnormal movements, and encephalopathy strongly supports anti-NMDA receptor encephalitis. Serum LGI1 IgG in an older adult with faciobrachial dystonic seizures, memory loss, and low sodium is also highly meaningful. The result can guide treatment, tumor screening, prognosis, and relapse monitoring.
A positive result that does not match the syndrome: This requires caution. Low-titer serum antibodies can occur without autoimmune encephalitis. Weak line-blot bands for intracellular antibodies may be nonspecific. GAD65 positivity may reflect autoimmune diabetes rather than neurologic autoimmunity. Voltage-gated potassium channel complex results without specific LGI1 or CASPR2 antibodies are generally less useful than target-specific testing. The clinician may repeat testing, request confirmation by another method, or seek review from a neuroimmunology laboratory.
Serum positive but CSF negative: The meaning depends on the antibody. For some targets, a serum result may still be clinically important. For others, especially NMDA receptor IgG, isolated serum positivity should be interpreted very carefully. The laboratory method, titer, clinical syndrome, and whether intrathecal antibody production is present all matter.
CSF positive but serum negative: This can occur and may be highly significant, particularly for antibodies that are more reliably detected in CSF. A CSF-only result should still be checked against the clinical phenotype and assay quality.
A negative panel: A negative result lowers the probability of the specific antibodies tested but does not exclude autoimmune encephalitis. The patient may have an antibody not included in the panel, an antibody below the assay’s detection limit, a primarily T-cell-mediated disorder, or seronegative autoimmune encephalitis. Timing, specimen choice, prior immunotherapy, and laboratory technique can also affect results.
Doctors may diagnose probable antibody-negative autoimmune encephalitis when the clinical course, MRI, EEG, CSF, biopsy findings, and exclusion of alternatives fit accepted criteria. This is not a diagnosis made simply because symptoms are unexplained. It requires objective evidence and careful exclusion of mimics.
Antibody levels should not be used alone to measure recovery. Some titers fall with improvement, especially in CSF, but symptoms, neurologic examination, seizure control, cognition, function, imaging, and EEG are usually more important. Persistent serum antibodies can remain after clinical recovery. Repeating a full panel without a clear clinical question may add little value.
Tests Used Alongside the Antibody Panel
Autoimmune encephalitis is a clinical diagnosis supported by testing. The workup is designed both to find evidence of brain inflammation and to exclude dangerous alternatives.
Brain MRI: MRI may show inflammation in the medial temporal lobes, cortex, basal ganglia, brainstem, or other regions. Limbic encephalitis often affects the hippocampi and nearby structures. However, MRI can be normal, especially early in anti-NMDA receptor encephalitis. A normal scan should not end the evaluation when the syndrome remains convincing.
Electroencephalogram: EEG can detect seizures, nonconvulsive status epilepticus, slowing, or patterns consistent with diffuse brain dysfunction. Extreme delta brush is associated with anti-NMDA receptor encephalitis but is not present in every case and is not entirely specific. Continuous EEG monitoring may be needed when awareness fluctuates or abnormal movements could represent seizures.
Lumbar puncture and infection testing: Viral encephalitis, particularly herpes simplex virus encephalitis, can look very similar to autoimmune encephalitis and requires urgent antiviral treatment. CSF polymerase chain reaction testing, cultures, and other infection studies are selected according to exposure, immune status, geography, and clinical features. Autoimmune and infectious processes can occasionally overlap, and autoimmune encephalitis may follow an infection.
Blood studies: Routine testing can identify metabolic, endocrine, toxic, nutritional, or systemic inflammatory causes of encephalopathy. Common studies may include blood count, electrolytes, liver and kidney function, glucose, thyroid testing, vitamin levels, toxicology, and infection screening. Broad autoimmune disease blood tests may be useful when systemic lupus, vasculitis, thyroid autoimmunity, or another multisystem illness is suspected, but ANA or inflammatory markers do not diagnose autoimmune encephalitis.
Cancer evaluation: The antibody and patient profile determine the search. CT of the chest, abdomen, and pelvis, pelvic ultrasound or MRI, testicular ultrasound, mammography, whole-body PET, or other targeted studies may be considered. If initial screening is negative but a high-risk paraneoplastic antibody is present, periodic repeat screening may be recommended.
Medication, substance, and exposure review: Prescription drugs, recreational substances, withdrawal states, toxins, and immune therapies can cause encephalopathy, seizures, movement disorders, or psychiatric symptoms. Immune checkpoint inhibitors used in cancer treatment can trigger neurologic immune complications.
Psychiatric and neuropsychological assessment: Psychiatric evaluation is valuable, particularly when psychosis, catatonia, mood change, or agitation dominates. It should complement, not replace, neurologic assessment when red flags such as seizures, autonomic instability, abnormal movements, fluctuating consciousness, or rapid cognitive decline are present. Formal cognitive testing can help document recovery and guide rehabilitation.
In rare cases, brain biopsy is considered when the diagnosis remains uncertain and conditions such as lymphoma, vasculitis, infection, or infiltrative disease must be distinguished. Biopsy is not routinely required for a typical antibody-confirmed syndrome.
Treatment, Cancer Screening, and Next Steps
Treatment decisions are based on the severity and probability of autoimmune encephalitis, not solely on how quickly an antibody report returns. Patients with a convincing, rapidly progressive syndrome may begin immunotherapy after reasonable steps have been taken to evaluate and treat infection. Delaying therapy in severe disease can increase the risk of complications and long-term disability.
First-line immunotherapy commonly includes high-dose corticosteroids, intravenous immunoglobulin, plasma exchange, or a combination. The choice depends on the suspected antibody, severity, infection risk, medical conditions, and local expertise. Patients who do not improve adequately may receive second-line treatment such as rituximab or cyclophosphamide. Other immune therapies may be considered for resistant or relapsing disease under specialist care.
When a tumor is found, prompt cancer treatment is a central part of care. Removing an ovarian teratoma in anti-NMDA receptor encephalitis or treating a tumor associated with a paraneoplastic syndrome can improve the chance of neurologic recovery and reduce ongoing immune stimulation. Cancer evaluation should be tailored rather than identical for every antibody.
Supportive care is equally important. Patients may need antiseizure medication, management of severe agitation or catatonia, treatment for autonomic instability, breathing support, prevention of blood clots and pressure injuries, nutrition, sleep regulation, physical therapy, speech therapy, and cognitive rehabilitation. Some medications used for agitation can worsen movement disorders or autonomic problems, so treatment often requires a coordinated neurology, psychiatry, intensive-care, and rehabilitation team.
Recovery can be slow and uneven. Attention, memory, mood, sleep, behavior, and executive function may continue to improve for many months. Families may notice that physical recovery occurs before judgment, impulse control, or higher-level thinking returns. Return to school, work, driving, or independent living should be based on function and specialist assessment rather than a single laboratory result.
Relapse risk varies by antibody and whether a tumor was identified and treated. New seizures, cognitive decline, psychiatric change, sleep disturbance, or abnormal movements after recovery should prompt reassessment. A repeat antibody test may be useful in selected cases, but clinicians should also repeat MRI, EEG, CSF studies, tumor screening, or other investigations according to the syndrome.
Emergency evaluation is needed for a first seizure, repeated seizures, rapidly worsening confusion, inability to stay awake, new weakness, severe abnormal movements, difficulty breathing, high fever with altered mental status, or major changes in heart rate or blood pressure. These symptoms can signal encephalitis, status epilepticus, infection, stroke, or another critical neurologic condition. An antibody panel is not an emergency triage tool and should never delay immediate care.
References
- ARUP Consult. Autoimmune Encephalitis. Updated 2025.
- Ford H, et al. Indications and Diagnostic Yield of Paraneoplastic and Autoimmune Encephalitis Antibody Testing: A Retrospective Cohort Study. Brain and Behavior. 2025.
- Irani SR. Autoimmune Encephalitis. Continuum. 2024.
- Dalmau J, Graus F. Diagnostic criteria for autoimmune encephalitis: utility and pitfalls for antibody-negative disease. The Lancet Neurology. 2023.
- Budhram A, et al. Clinical Sensitivity, Specificity, and Predictive Value of Neural Antibody Testing for Autoimmune Encephalitis. The Journal of Applied Laboratory Medicine. 2022.
- Abboud H, et al. Autoimmune encephalitis: proposed best practice recommendations for diagnosis and acute management. Journal of Neurology, Neurosurgery & Psychiatry. 2021.
Disclaimer
This article is for general educational purposes and does not replace medical evaluation, diagnosis, or treatment. Autoimmune encephalitis and its mimics can be medical emergencies; new seizures, rapidly worsening confusion, reduced consciousness, breathing difficulty, or autonomic instability require urgent care. Test selection and interpretation should be handled by qualified clinicians familiar with neurologic antibody testing.