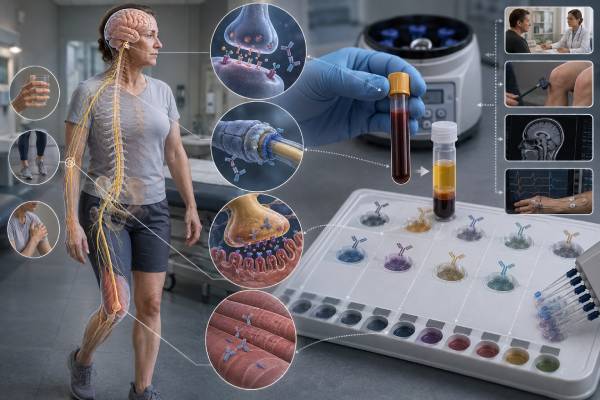
An autoimmune neurology antibody panel looks for immune proteins associated with disorders of the brain, spinal cord, peripheral nerves, neuromuscular junction, or muscles. The name can be misleading because there is no single panel that is ideal for every neurologic symptom. A patient with rapidly progressive confusion needs different testing from someone with optic neuritis, fluctuating eyelid weakness, painful neuropathy, or inflammatory muscle weakness. The most useful approach is to identify the neurologic syndrome first, then select a targeted serum, cerebrospinal fluid, or combined antibody panel. Results may support a diagnosis, guide cancer screening, or influence treatment, but they must be interpreted with the examination, imaging, electrodiagnostic studies, routine blood tests, and cerebrospinal fluid findings. Broad testing without a matching clinical picture increases false-positive results. A negative panel also does not exclude every autoimmune neurologic disease.
- Autoimmune neurology testing should be selected according to where the nervous system appears to be affected.
- Brain and spinal cord disorders may require paired serum and cerebrospinal fluid, while many nerve, junction, and muscle antibodies are tested mainly in serum.
- Some antibodies are directly involved in disease; others are markers of a cancer-associated immune response.
- Low-level or method-dependent positives can be misleading when symptoms do not match the expected syndrome.
- Antibody testing complements, rather than replaces, MRI, EEG, nerve conduction studies, EMG, lumbar puncture, and clinical assessment.
Table of Contents
- Localize the Neurologic Problem Before Choosing a Panel
- Brain, Spinal Cord, Optic Nerve, and Paraneoplastic Antibodies
- Peripheral Nerve and Autonomic Antibodies
- Neuromuscular Junction Antibodies
- Inflammatory Muscle and Myositis Antibodies
- Serum, CSF, Test Methods, and False Positives
- Interpreting Results and Planning the Next Steps
Localize the Neurologic Problem Before Choosing a Panel
“Autoimmune neurology panel” can refer to a comprehensive antineural test containing dozens of markers or to a focused group designed for one clinical phenotype. Laboratories may offer separate panels for encephalopathy, epilepsy, movement disorders, myelopathy, neuropathy, dysautonomia, neuromuscular junction disease, inflammatory myopathy, optic neuritis, or paraneoplastic syndromes. The antibody lists are not standardized, so two panels with similar names may test very different targets.
A neurologic examination helps determine where the problem is located:
- Brain involvement may cause seizures, memory loss, behavior change, confusion, abnormal movements, sleep disturbance, or loss of consciousness.
- Spinal cord involvement may cause weakness, sensory loss, a defined sensory level, bladder dysfunction, or stiffness below a lesion.
- Optic nerve inflammation may cause painful vision loss, reduced color vision, or visual field changes.
- Peripheral nerve disease may produce numbness, burning pain, imbalance, reduced reflexes, or weakness in a length-dependent, multifocal, or rapidly progressive pattern.
- Neuromuscular junction disease causes fatigable weakness, often affecting the eyelids, eye movements, speech, swallowing, neck, or breathing muscles.
- Muscle inflammation commonly causes persistent proximal weakness, difficulty rising from a chair or lifting the arms, and sometimes rash, lung disease, or swallowing difficulty.
Time course also matters. Many autoimmune neurologic disorders develop over days to a few months, although some evolve more slowly. A very sudden deficit suggests stroke, seizure, migraine, or another acute cause. Years of steadily progressive symptoms may be more consistent with genetic, degenerative, structural, or metabolic disease. These are not absolute rules, but they help set the pretest probability.
Clinicians also look for inflammatory clues: abnormal MRI enhancement, cerebrospinal fluid white cells or oligoclonal bands, an unexplained high protein level, characteristic EEG abnormalities, conduction block on nerve studies, elevated creatine kinase, or a known cancer. A recent infection, immune checkpoint inhibitor therapy, another autoimmune disorder, or rapid response to immunotherapy may strengthen suspicion.
Testing should not begin with the largest available panel simply because the symptoms are unexplained. Every additional antibody creates another chance for a weak, incidental, or technically false-positive result. Phenotype-specific testing reduces noise and usually provides a more useful answer. A general autoantibody blood test panel may help identify systemic disease, but neurologic antibodies require a different level of specimen and method selection.
Brain, Spinal Cord, Optic Nerve, and Paraneoplastic Antibodies
Central nervous system panels contain antibodies associated with encephalitis, epilepsy, demyelination, movement disorders, ataxia, myelopathy, or cancer-related neurologic syndromes. The same antibody can produce more than one presentation, so the panel should reflect the dominant phenotype rather than a rigid disease label.
Neuronal surface and synaptic antibodies: NMDA receptor, LGI1, CASPR2, GABA-B receptor, AMPA receptor, GABA-A receptor, DPPX, glycine receptor, and IgLON5 antibodies are linked to recognizable combinations of seizures, cognitive decline, psychiatric change, abnormal movement, sleep disturbance, rigidity, or autonomic dysfunction. These disorders are often grouped under autoimmune encephalitis, although some affect both central and peripheral structures. A dedicated autoimmune encephalitis antibody panel is more appropriate than a broad neuromuscular panel when a rapidly progressive brain syndrome dominates.
AQP4-IgG: Aquaporin-4 antibodies support neuromyelitis optica spectrum disorder. Typical attacks include severe optic neuritis, long spinal cord lesions, area postrema syndrome with otherwise unexplained hiccups or vomiting, or certain brainstem and diencephalic syndromes. Serum testing with a high-quality cell-based assay is preferred. AQP4-IgG should not be ordered as a general multiple sclerosis screen without a compatible clinical and MRI pattern.
MOG-IgG: Myelin oligodendrocyte glycoprotein antibodies define MOG antibody-associated disease when a compatible demyelinating event is present and alternatives are excluded. Presentations include optic neuritis, transverse myelitis, acute disseminated encephalomyelitis, cortical encephalitis with seizures, and brainstem syndromes. Serum is generally the preferred specimen, and a cell-based assay using full-length MOG in its native conformation is important. Low-positive results require especially careful phenotype matching.
GAD65 antibodies: High levels can be associated with stiff-person-spectrum disorders, autoimmune epilepsy, cerebellar ataxia, or limbic encephalitis. Lower serum levels are common in autoimmune diabetes and may not explain neurologic symptoms. Cerebrospinal fluid positivity or evidence of intrathecal production can add weight in an appropriate syndrome.
Paraneoplastic antibodies: Hu, Yo, Ri, CRMP5, amphiphysin, Ma2, KLHL11, SOX1, and several other antibodies can mark an immune response associated with cancer. They may accompany encephalomyelitis, limbic encephalitis, sensory neuronopathy, cerebellar degeneration, brainstem disease, stiff-person syndrome, or mixed neurologic deficits. Many target intracellular proteins and indicate a T-cell-mediated process rather than an antibody that directly disrupts a surface receptor.
The cancer association varies widely. A high-risk antibody plus a matching phenotype can justify focused imaging and repeated surveillance even when the initial tumor search is negative. The antibody does not identify cancer with complete certainty, and a cancer diagnosis alone does not prove that the neurologic symptoms are paraneoplastic. Modern criteria combine phenotype, antibody risk category, cancer type, and timing.
Central nervous system antibody results must be integrated with brain and spine MRI, EEG when seizures or encephalopathy are possible, routine cerebrospinal fluid studies, infection testing, and metabolic or toxic evaluation. A normal MRI or CSF does not exclude every autoimmune disorder, but a positive antibody without objective or clinical support deserves reassessment rather than automatic immunotherapy.
Peripheral Nerve and Autonomic Antibodies
Peripheral neuropathy panels are useful only for selected patterns. Most common length-dependent neuropathies caused by diabetes, alcohol, chemotherapy, nutritional deficiency, kidney disease, or hereditary conditions are not diagnosed by neural antibody testing. Electrodiagnostic localization and a focused medical evaluation usually come first.
Ganglioside antibodies: Gangliosides are components of nerve membranes. IgM GM1 antibodies can support multifocal motor neuropathy in a patient with slowly progressive, asymmetric motor weakness and conduction block without prominent sensory loss. They are not required for diagnosis and can occur in other conditions. GQ1b IgG is strongly associated with Miller Fisher syndrome and related Guillain-Barré variants involving ophthalmoplegia, ataxia, or reduced reflexes. Other ganglioside antibodies, including GD1a, GD1b, GT1a, or disialosyl combinations, may be tested in specific acute neuropathy or sensory ataxia syndromes.
Myelin-associated glycoprotein antibodies: Anti-MAG IgM is associated with a slowly progressive distal demyelinating neuropathy, often with sensory loss, imbalance, and tremor. It usually occurs with an IgM monoclonal protein. Serum protein electrophoresis, immunofixation, quantitative immunoglobulins, and hematologic evaluation are therefore part of the workup. A low anti-MAG value without the expected neuropathy and paraprotein may be nonspecific.
Nodal and paranodal antibodies: Antibodies to neurofascin-155, pan-neurofascin, contactin-1, or CASPR1 identify autoimmune nodopathies in a minority of patients previously grouped with chronic inflammatory demyelinating polyradiculoneuropathy. Clues can include severe motor weakness, sensory ataxia, tremor, cranial nerve involvement, rapid progression, or poor response to standard intravenous immunoglobulin. These specialized tests should be ordered when the phenotype and nerve conduction findings justify them.
Ganglionic acetylcholine receptor antibodies: Alpha-3 ganglionic AChR antibodies can support autoimmune autonomic ganglionopathy. Symptoms may include severe orthostatic hypotension, fainting, dry mouth and eyes, impaired sweating, constipation or intestinal dysmotility, urinary retention, and abnormal pupils. Higher levels in a matching syndrome carry more weight than low levels found during broad screening.
CASPR2 and peripheral nerve hyperexcitability: CASPR2 antibodies may occur with neuromyotonia, painful muscle twitching, cramps, excessive sweating, sleep disturbance, or Morvan syndrome. Electromyography can show continuous muscle fiber activity. Because CASPR2 also appears in central nervous system disease, the complete phenotype determines which panel and specimen are most informative.
Paraneoplastic sensory neuronopathy markers: Hu and CRMP5 antibodies can accompany painful or non-length-dependent sensory loss, ataxia, autonomic involvement, or mixed neuropathy. Their detection should prompt evaluation for the associated cancers, especially when symptoms progress quickly.
Some commercially available tests for antibodies linked to small-fiber neuropathy or sensory syndromes have uncertain or evolving clinical value. A positive result should not replace skin biopsy, autonomic testing, nerve studies, metabolic evaluation, or assessment for systemic autoimmune disease. The more exploratory the marker, the stronger the need for specialist and laboratory consultation.
Neuromuscular Junction Antibodies
Neuromuscular junction disorders interfere with communication between motor nerves and skeletal muscle. They typically cause weakness that fluctuates or worsens with repeated activity, while sensation remains normal.
Acetylcholine receptor antibodies: AChR antibodies are the first-line serologic tests for suspected myasthenia gravis. Laboratories may report binding, blocking, and modulating antibodies. Binding antibody is the main diagnostic marker; the additional forms can improve detection in selected cases. A positive result in a patient with fatigable eyelid droop, double vision, nasal speech, swallowing difficulty, neck weakness, or generalized fatigability strongly supports autoimmune myasthenia.
AChR antibody level does not consistently match day-to-day severity, so serial titers are not a substitute for clinical assessment. Patients with confirmed myasthenia are typically evaluated for thymic abnormalities with chest imaging, but the antibody result alone does not diagnose thymoma.
MuSK antibodies: Muscle-specific kinase antibodies are tested when AChR antibodies are negative or when the phenotype strongly suggests MuSK myasthenia. Bulbar, facial, neck, and breathing weakness may be prominent, while eye symptoms can also occur. MuSK disease has different immune biology and may respond differently to specific therapies, making accurate antibody classification clinically useful.
LRP4 antibodies: Low-density lipoprotein receptor-related protein 4 antibodies may be found in a subset of patients who are negative for both AChR and MuSK antibodies. Their specificity depends on the assay and population, and positive results have been reported in other neurologic diseases. A compatible examination and abnormal neuromuscular transmission testing remain essential.
P/Q-type voltage-gated calcium channel antibodies: These antibodies support Lambert-Eaton myasthenic syndrome. Patients often have proximal leg weakness, reduced reflexes that may briefly improve after exercise, dry mouth, constipation, or erectile dysfunction. Electrophysiology demonstrates a characteristic increment after rapid stimulation or exercise. Lambert-Eaton syndrome is associated with small cell lung cancer in a substantial subset, so age, smoking history, SOX1 antibodies, and cancer screening matter.
Seronegative disease remains possible. Repetitive nerve stimulation, single-fiber EMG, bedside fatigability testing, pulmonary measurements, medication review, and exclusion of botulism, motor neuron disease, mitochondrial disease, or structural brainstem disorders help establish the diagnosis. Cell-based assays can detect some clustered AChR or MuSK antibodies missed by older methods, but availability varies.
Difficulty breathing, rapidly worsening swallowing, weak cough, inability to hold the head up, or marked decline in speech can indicate impending myasthenic crisis. These symptoms require emergency assessment rather than waiting for antibody results.
Inflammatory Muscle and Myositis Antibodies
Myositis panels test antibodies associated with idiopathic inflammatory myopathies. These tests are often grouped with rheumatology rather than antineural panels, even though patients may be referred to a neuromuscular specialist. The panel should be interpreted with the pattern of weakness, skin findings, creatine kinase, electromyography, muscle MRI, lung assessment, and sometimes muscle or skin biopsy.
Antisynthetase antibodies: Jo-1 is the most common, but PL-7, PL-12, EJ, OJ, KS, Zo, and others may be included. Antisynthetase syndrome can cause inflammatory muscle weakness, interstitial lung disease, inflammatory arthritis, fever, Raynaud phenomenon, or rough cracked skin on the fingers known as mechanic’s hands. Lung disease may dominate even when muscle enzymes are only mildly elevated.
Dermatomyositis-associated antibodies: Mi-2 is associated with classic skin and muscle disease. TIF1-gamma can signal an increased malignancy association in adults with dermatomyositis. NXP2 may occur with severe weakness, edema, calcinosis, or cancer risk depending on age. MDA5 is linked to clinically amyopathic dermatomyositis and potentially rapidly progressive interstitial lung disease. SAE antibodies may be associated with prominent rash followed by muscle or swallowing involvement.
Immune-mediated necrotizing myopathy antibodies: HMGCR and signal recognition particle antibodies support necrotizing autoimmune myopathy. Patients often have marked proximal weakness and very high creatine kinase. HMGCR disease can follow statin exposure but also occurs without it. Stopping a statin alone may not be sufficient when true immune-mediated necrotizing myopathy is present.
Overlap and associated antibodies: PM/Scl, Ku, U1-RNP, Ro52, and other markers can occur when myositis overlaps with systemic sclerosis, mixed connective tissue disease, Sjögren disease, or another autoimmune condition. Ro52 is common across several disorders and should not be treated as a myositis diagnosis by itself.
A positive myositis antibody can help define risks, such as lung disease or malignancy, but commercial line blots can produce weak or multiple positives that do not fit the patient. Some antibodies are technically difficult to detect, and panel performance varies. Strong phenotype matching and, when necessary, confirmation at an experienced laboratory are important.
A negative myositis panel does not exclude inflammatory myopathy. Inclusion body myositis, immune-mediated necrotizing myopathy, dermatomyositis, overlap myositis, and other inflammatory muscle diseases can be seronegative. Conversely, weakness with a positive antibody may still be caused by neuropathy, medication toxicity, endocrine disease, muscular dystrophy, deconditioning, or another noninflammatory problem.
Serum, CSF, Test Methods, and False Positives
Specimen choice is antibody-specific. Serum is preferred for AQP4-IgG, MOG-IgG, AChR, MuSK, LRP4, VGCC, ganglioside, MAG, nodal/paranodal, ganglionic AChR, and most myositis antibodies. For many brain-directed antibodies, testing both serum and cerebrospinal fluid improves diagnostic yield and specificity. NMDA receptor IgG is especially important to assess in CSF, while LGI1 and CASPR2 may be more readily detected in serum.
Laboratories use several methods:
Cell-based assays display target proteins in a cell membrane so antibodies can recognize a near-native structure. They are central for surface antigens such as AQP4, MOG, NMDA receptor, LGI1, CASPR2, MuSK, and some AChR antibodies.
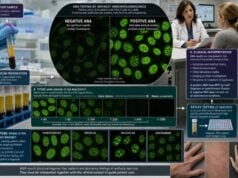
Tissue-based immunofluorescence screens serum or CSF against brain, nerve, or muscle tissue. A characteristic staining pattern can reveal a known antibody or suggest an unclassified one. The pattern may then be confirmed with an antigen-specific test.
Radioimmunoassay, immunoprecipitation, or enzyme immunoassay is used for selected neuromuscular junction, calcium channel, GAD65, and other antibodies. Performance depends on the antigen and cutoff.
Immunoblot and line blot can test many intracellular or myositis antigens at once. They are convenient but can produce weak bands that are not reproduced by other methods. A line blot should not automatically override a discordant phenotype or negative confirmatory test.
False positives become more likely when disease prevalence is low, the panel is very broad, or the result is barely above the cutoff. Other warning signs include an antibody found only in the less appropriate specimen, several unrelated weak antibodies, a method known to have limited specificity for that target, or symptoms that do not resemble the established syndrome.
Prior treatment can also affect sensitivity. Plasma exchange, intravenous immunoglobulin, B-cell therapy, or prolonged immunosuppression may alter antibody levels. Intravenous immunoglobulin contains pooled antibodies and can complicate some serologic results for a period after infusion. Whenever possible, clinically appropriate samples are obtained before immunotherapy, but urgent treatment should not be delayed solely to preserve test sensitivity.
Interpreting Results and Planning the Next Steps
A useful positive result forms a coherent triangle: the antibody is analytically credible, the specimen and method are appropriate, and the patient has the expected phenotype. When one side is missing, the probability of misinterpretation rises.
Positive and phenotype-matched: The result may confirm or strongly support a specific immune-mediated disorder. It can guide tumor screening, treatment selection, prognosis, relapse counseling, and testing of associated organ systems. Examples include AQP4-IgG with a characteristic optic-spinal syndrome, AChR antibody with fatigable weakness, or anti-MAG with a compatible demyelinating neuropathy and IgM monoclonal protein.
Positive but phenotype-mismatched: The clinician may review the raw value, reference range, specimen, assay, and laboratory comments; repeat the test; request a second method; or consult a neuroimmunology laboratory. Treatment should not be based on a surprising low-positive result alone.
Negative panel: The specific antibodies tested were not detected, but the disease may be seronegative, the relevant target may not be included, the specimen may be suboptimal, or another immune mechanism may be present. Clinical criteria, MRI, CSF, EEG, electrodiagnostic testing, biopsy, and treatment response may still support an autoimmune diagnosis.
Multiple positives: Occasionally more than one true antibody occurs, particularly in cancer-associated disease or overlapping autoimmunity. More often, a collection of weak unrelated results reflects assay noise. The dominant clinical syndrome should determine which result deserves attention.
Follow-up testing depends on localization. Brain disease may require MRI, EEG, lumbar puncture, infection studies, and neuropsychological assessment. Demyelinating disease requires targeted MRI and ophthalmologic testing. Neuropathy requires nerve conduction studies, EMG, metabolic and monoclonal protein evaluation, and sometimes autonomic or skin biopsy testing. Junction disease requires repetitive stimulation or single-fiber EMG. Muscle disease may require creatine kinase, lung imaging, MRI, EMG, and biopsy. A broad autoimmune disease blood test panel may identify systemic clues but cannot establish a neural diagnosis.
Cancer screening should match the antibody, phenotype, age, sex, and risk factors. High-risk paraneoplastic antibodies often justify a more intensive search and repeat surveillance. Surface antibodies with occasional tumor associations require a different approach. The presence of a low-specificity antibody should not lead to repeated radiation-heavy imaging without a clinically justified plan.
Antibody levels are not universally useful for monitoring. Some correlate partly with disease activity, while others remain positive after recovery or fluctuate independently of symptoms. Follow-up should prioritize examination, function, relapse signs, imaging, electrophysiology, respiratory status, and organ-specific laboratory measures.
Emergency care is required for new seizures, rapidly worsening confusion, sudden vision loss, ascending weakness, inability to walk, urinary retention with spinal symptoms, severe swallowing difficulty, weak cough, or breathing problems. Autoimmune neurologic diseases are treatable in many cases, but several mimics are equally urgent. Antibody testing should accelerate a focused diagnosis, not delay stabilization or evaluation for infection, stroke, compression, toxin exposure, or metabolic crisis.
References
- ARUP Consult. Autoimmune Neurologic Diseases – Antineural Antibody Testing. Updated 2026.
- Wu JL, Mills JR. The evolving landscape of autoantibody testing for autoimmune neurological diseases. Clinical Laboratory News. 2024.
- Gilligan M, McGuigan C, McKeon A. Autoimmune central nervous system disorders: Antibody testing and its clinical utility. Clinical Biochemistry. 2024.
- Loser V, Vicino A, Théaudin M. Autoantibodies in neuromuscular disorders: a review of their utility in clinical practice. Frontiers in Neurology. 2024.
- Pascual-Goñi E, Caballero-Ávila M, Querol L. Antibodies in autoimmune neuropathies: what to test, how to test, why to test. Neurology. 2024.
- Graus F, et al. Updated Diagnostic Criteria for Paraneoplastic Neurologic Syndromes. Neurology: Neuroimmunology & Neuroinflammation. 2021.
Disclaimer
This article provides general educational information and does not replace evaluation by a neurologist or other qualified clinician. Autoimmune neurology antibody results require interpretation with the clinical syndrome, specimen, assay method, imaging, and physiologic testing. New seizures, rapidly progressive weakness, severe swallowing difficulty, breathing problems, sudden vision loss, or major confusion require urgent medical care.