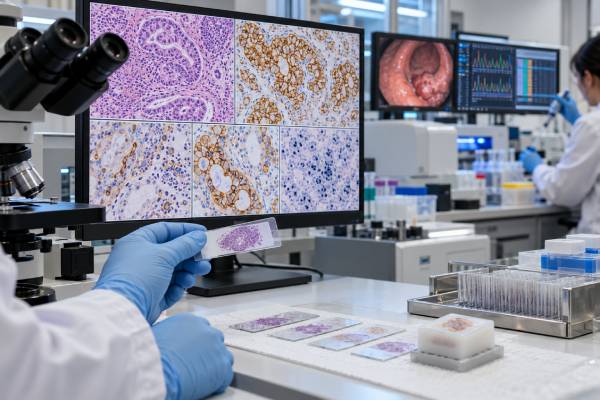
A modern gastric cancer biomarker panel can directly shape first-line and later treatment. The most clinically established markers include HER2, PD-L1, microsatellite instability or mismatch-repair status, and CLDN18.2; Epstein-Barr virus (EBV) and broader molecular profiling can add biologic context and occasionally reveal other actionable changes. These markers are usually measured on tumor tissue, not in a routine blood panel. They also answer different questions. HER2 and CLDN18.2 identify targetable proteins, PD-L1 helps estimate the likelihood and labeled use of some immune-checkpoint combinations, and MSI-high or dMMR can strongly support immunotherapy. EBV defines a molecularly distinctive subset but is not, by itself, a universal treatment-selection test. Because gastric cancers can be heterogeneous, specimen quality and cancer-specific scoring rules matter. The safest way to read the panel is as a set of linked treatment decisions rather than a single “positive versus negative” result.
- HER2, PD-L1, MSI/dMMR, and CLDN18.2 are the key treatment-shaping tissue biomarkers in advanced gastric/GEJ adenocarcinoma.
- HER2 positivity commonly means IHC 3+ or IHC 2+ with gene amplification/ISH positivity using gastric-specific scoring.
- CLDN18.2 treatment eligibility uses an assay-specific membranous-staining threshold; the current U.S. companion diagnostic uses high expression in at least 75% of tumor cells.
- PD-L1 is usually reported as combined positive score (CPS), and the meaningful cutoff depends on the drug, regimen, assay, and jurisdiction.
- MSI-H/dMMR can predict strong sensitivity to immune checkpoint blockade and may also prompt hereditary-cancer assessment.
Table of Contents
- What each gastric cancer biomarker measures
- Specimen selection and gastric-specific scoring
- How to interpret HER2, PD-L1, MSI, CLDN18.2, and EBV
- How the panel changes treatment choices
- Tumor heterogeneity, retesting, and discordant results
- What to look for on the pathology report
- Practical next steps after a gastric biomarker panel
What each gastric cancer biomarker measures
HER2 is a receptor protein encoded by ERBB2. Testing begins with immunohistochemistry, which scores membranous protein expression from 0 to 3+. Equivocal 2+ tumors usually need in-situ hybridization to determine whether ERBB2 is amplified. PD-L1 immunohistochemistry is commonly reported as combined positive score, which counts staining in tumor and certain immune cells relative to viable tumor cells.
MSI and MMR testing evaluate failure of the DNA mismatch-repair system. CLDN18.2 testing measures membranous expression of a tight-junction protein that becomes accessible on malignant gastric cells. EBV status is commonly assessed by EBER in-situ hybridization. Broader next-generation sequencing can examine mutations, amplifications, and fusions beyond these core markers. The tests are complementary; one does not substitute for another.
Specimen selection and gastric-specific scoring
Gastric and gastroesophageal tumors often show patchy biomarker expression. A biopsy may therefore sample a negative area of a tumor that contains positive regions elsewhere. Multiple viable biopsy fragments improve confidence, and a resection or newer metastatic specimen can be useful when the original sample is scant or old. Fixation quality also matters for immunohistochemistry and in-situ hybridization.
HER2 scoring in gastric cancer is not identical to breast scoring because basolateral or lateral membranous staining can count and incomplete membrane staining is common. CLDN18.2 requires a companion-diagnostic method when the result will determine use of zolbetuximab. PD-L1 CPS should be reported with the assay clone and numeric score rather than only “positive.” That preserves information when treatment thresholds differ.
How to interpret HER2, PD-L1, MSI, CLDN18.2, and EBV
HER2 IHC 3+ is strongly positive; IHC 2+ is equivocal and requires amplification confirmation for many treatment decisions. CLDN18.2 positivity for zolbetuximab in the United States requires a HER2-negative tumor with the specified high membranous expression threshold on an FDA-approved assay. PD-L1 CPS is continuous: a CPS of 1, 5, or 10 can carry different implications depending on regimen and label, so there is no single universal “PD-L1 positive” cutoff.
MSI-H or dMMR is a biologically important result because it can predict durable response to immune checkpoint therapy. EBV-positive gastric cancers often have an immune-rich biology, but EBV is not a stand-alone FDA companion diagnostic for a standard gastric regimen. A molecular profile may also reveal rare NTRK fusions, high tumor mutational burden, or other alterations that matter after standard options.
How the panel changes treatment choices
Treatment selection is increasingly biomarker-first in advanced gastric and GEJ adenocarcinoma. HER2-positive disease has dedicated HER2-directed combinations. In August 2026, the FDA expanded first-line HER2-positive gastroesophageal options with zanidatamab-based regimens under defined IHC/ISH criteria. HER2-negative, CLDN18.2-positive advanced disease can qualify for zolbetuximab plus fluoropyrimidine- and platinum-containing chemotherapy.
PD-L1 and MSI/dMMR help determine the role of checkpoint inhibitors. The exact immunotherapy regimen depends on HER2 status, PD-L1 assay and score, line of therapy, and current labeling. This is why an oncology note that simply says “PD-L1 positive” is less useful than one that records CPS and assay. Biomarker overlap is possible, so the team may need to prioritize or sequence treatments rather than choose one marker in isolation.
Tumor heterogeneity, retesting, and discordant results
No biomarker works in isolation. A technically accurate result can still be clinically misleading if it is applied to the wrong cancer type, disease stage, specimen, or treatment question. Cutoffs may also differ by assay, drug label, guideline, and country. For that reason, the laboratory’s own interpretive criteria and the treating team’s current guideline should take priority over a generic internet threshold.
Tumors are heterogeneous, meaning different areas can carry different alterations or levels of protein expression. A small biopsy may miss a positive clone, while a blood-based assay can miss disease that sheds little DNA into the circulation. Conversely, a detectable alteration may be real but not be the main driver of the current disease. Pre-analytic issues such as delayed fixation, decalcification, low tumor content, recent transfusion, or poor plasma handling can also affect some assays.
The safest interpretation separates three questions: analytical validity—did the assay measure what it claims to measure; clinical validity—does the result correlate with the cancer feature of interest; and clinical utility—does acting on the result improve a meaningful decision for this patient. A result can be strong in one category and limited in another.
What to look for on the pathology report
For HER2, look for the IHC score and, when relevant, the ISH result. For PD-L1, look for the antibody clone, CPS, and specimen. For MSI/MMR, identify whether the report used PCR/NGS or MMR immunohistochemistry and whether any MMR protein was lost. For CLDN18.2, look for the assay and the percentage/intensity of membranous staining. For EBV, look for EBER in-situ hybridization rather than a blood EBV antibody test.
Also check the specimen date, site, tumor cellularity, and whether treatment occurred before the biopsy. A report that contains these details can be reinterpreted as standards evolve without repeating every assay. When tissue is limited, the oncology and pathology teams may need to decide which tests have the highest immediate treatment value.
Practical next steps after a gastric biomarker panel
A biomarker result should be read beside the pathology report, stage, imaging, treatment history, and the exact specimen tested. A useful question for the oncology team is not simply “is this positive?” but “what decision does this result change now?” That keeps the result tied to a concrete action such as confirming a diagnosis, choosing a drug, deciding whether hereditary evaluation is needed, or setting a surveillance plan.
If a result seems inconsistent with the clinical picture, ask whether the sample had enough viable tumor, whether the method covered the relevant alteration, and whether a newer metastatic or recurrent specimen would be more representative. Repeating a test is most useful when there is a specific reason to think the original specimen was inadequate, old, or biologically different from the disease being treated today.
Patients should also keep a copy of the complete molecular or pathology report, not only a portal summary. The full report usually lists the method, specimen, tumor percentage, assay limitations, exact variant or staining score, and interpretive comments. Those details matter when seeking a second opinion, transferring care, or checking eligibility for a targeted therapy or clinical trial.
One practical way to avoid overreading Gastric Cancer Biomarker Panel is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for Gastric Cancer Biomarker Panel may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
Laboratory reports also vary in how much interpretation they provide. Some give only a final category; others show raw staining percentages, copy-number estimates, variant allele fractions, quality metrics, and assay limitations. For Gastric Cancer Biomarker Panel, the detailed version is preferable because treatment criteria can evolve. A result that was not actionable when the tissue was first tested may become relevant later, and the original numerical or molecular detail may allow the oncology team to reassess eligibility without immediately repeating a biopsy.
Finally, biomarker testing works best as part of multidisciplinary care. Pathologists judge specimen quality and assay interpretation; medical oncologists connect the finding to treatment; surgeons and gastroenterologists provide disease context; genetic counselors address possible inherited risk when appropriate. Patients do not need to master every technical detail, but they benefit from knowing the purpose of the test, the exact result, what uncertainty remains, and what concrete decision follows. Those four questions turn a complex biomarker report into a usable plan.
One practical way to avoid overreading Gastric Cancer Biomarker Panel is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for Gastric Cancer Biomarker Panel may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
Laboratory reports also vary in how much interpretation they provide. Some give only a final category; others show raw staining percentages, copy-number estimates, variant allele fractions, quality metrics, and assay limitations. For Gastric Cancer Biomarker Panel, the detailed version is preferable because treatment criteria can evolve. A result that was not actionable when the tissue was first tested may become relevant later, and the original numerical or molecular detail may allow the oncology team to reassess eligibility without immediately repeating a biopsy.
Finally, biomarker testing works best as part of multidisciplinary care. Pathologists judge specimen quality and assay interpretation; medical oncologists connect the finding to treatment; surgeons and gastroenterologists provide disease context; genetic counselors address possible inherited risk when appropriate. Patients do not need to master every technical detail, but they benefit from knowing the purpose of the test, the exact result, what uncertainty remains, and what concrete decision follows. Those four questions turn a complex biomarker report into a usable plan.
One practical way to avoid overreading Gastric Cancer Biomarker Panel is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for Gastric Cancer Biomarker Panel may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
Laboratory reports also vary in how much interpretation they provide. Some give only a final category; others show raw staining percentages, copy-number estimates, variant allele fractions, quality metrics, and assay limitations. For Gastric Cancer Biomarker Panel, the detailed version is preferable because treatment criteria can evolve. A result that was not actionable when the tissue was first tested may become relevant later, and the original numerical or molecular detail may allow the oncology team to reassess eligibility without immediately repeating a biopsy.
Finally, biomarker testing works best as part of multidisciplinary care. Pathologists judge specimen quality and assay interpretation; medical oncologists connect the finding to treatment; surgeons and gastroenterologists provide disease context; genetic counselors address possible inherited risk when appropriate. Patients do not need to master every technical detail, but they benefit from knowing the purpose of the test, the exact result, what uncertainty remains, and what concrete decision follows. Those four questions turn a complex biomarker report into a usable plan.
One practical way to avoid overreading Gastric Cancer Biomarker Panel is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for Gastric Cancer Biomarker Panel may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
References
- Korean Practice Guidelines for Gastric Cancer 2024: An Evidence-based, Multidisciplinary Approach (Update of 2022 Guideline) 2025 (Guideline)
- SEOM-GEMCAD-TTD clinical guideline for the diagnosis and treatment of gastric cancer (2023) 2024 (Guideline)
- Novel Biomarkers of Gastric Cancer: Current Research and Future Perspectives 2023 (Review)
- FDA approves zolbetuximab-clzb with chemotherapy for gastric or gastroesophageal junction adenocarcinoma 2024 (Official)
- FDA approves zanidatamab-hrii and tislelizumab-jsgr for HER2-positive gastric, gastroesophageal junction, or esophageal adenocarcinoma 2026 (Official)
Disclaimer
This article explains biomarker testing for educational purposes and is not a diagnosis or treatment plan. Cancer testing and treatment should be interpreted by the oncology and pathology teams using the complete medical record, current guidelines, and the specific laboratory method. Seek prompt medical care for new or rapidly worsening symptoms rather than relying on a biomarker result alone.