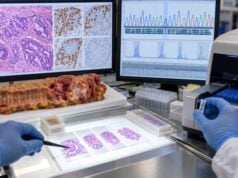
A GI cancer biomarker panel is not one universal blood test. It is a group of blood, pathology, and molecular tests selected according to the suspected or confirmed gastrointestinal cancer. CEA and CA 19-9 are serum tumor markers that may help with baseline assessment or follow-up in selected cancers, but neither can diagnose cancer by itself. MSI or mismatch-repair status, KRAS, BRAF, and HER2 are tumor biomarkers that can affect prognosis, hereditary-cancer evaluation, or treatment choices in specific diseases. The value of the panel therefore comes from matching each marker to the right cancer and clinical question. A colon cancer workup may emphasize MSI, RAS, BRAF, and sometimes HER2, while pancreatic or biliary cancers use different molecular priorities. Understanding the specimen, method, and purpose of each result prevents a common mistake: treating every “positive” or “high” value as if it carried the same meaning.
- CEA and CA 19-9 are blood markers mainly used for context and monitoring, not stand-alone cancer diagnosis.
- MSI/dMMR can identify tumors likely to respond to immune checkpoint therapy and can trigger Lynch syndrome evaluation.
- KRAS and NRAS mutations in colorectal cancer predict resistance to anti-EGFR antibodies; BRAF V600E has separate prognostic and treatment implications.
- HER2 positivity is defined and treated differently in colorectal, gastric, and other GI cancers.
- A useful panel combines pathology and molecular results with stage, imaging, and the exact tumor type.
Table of Contents
- What a GI cancer biomarker panel measures
- How the tests are performed and when they are ordered
- How to interpret CEA, CA 19-9, MSI, KRAS, BRAF, and HER2
- How biomarker results change treatment decisions
- Limitations, false positives, and false negatives
- Questions to ask before acting on a biomarker panel
- Practical next steps after results
What a GI cancer biomarker panel measures
CEA is a glycoprotein measured in blood. It is best established as a baseline and surveillance marker in colorectal cancer, where trends can be more informative than a single value. CA 19-9 is a carbohydrate antigen used most often in pancreatic and biliary cancers. Cholestasis and benign inflammation can raise CA 19-9, and people who do not express the Lewis antigen may produce little or no CA 19-9 even with cancer.
MSI evaluates instability in short repeated DNA sequences, while mismatch-repair testing evaluates the proteins that normally correct DNA-copying errors. KRAS and BRAF are genes in the MAPK signaling pathway. Their mutations can influence drug response and tumor behavior. HER2, encoded by ERBB2, can be assessed by protein overexpression, gene amplification, or sequencing depending on the cancer. These tests belong to different analytical families, so a “panel” may actually require blood, formalin-fixed tumor tissue, and sometimes circulating tumor DNA.
How the tests are performed and when they are ordered
Blood markers require a routine serum sample and usually need no fasting. The important practical point is consistency: trends are easiest to interpret when the same marker and, when possible, the same laboratory method are used over time. Tumor biomarkers require a pathology specimen from biopsy or surgery. MSI can be measured by PCR or next-generation sequencing, while dMMR is commonly assessed by immunohistochemistry. KRAS and BRAF are usually tested by targeted PCR or sequencing, and HER2 may require immunohistochemistry plus in-situ hybridization.
Timing depends on tumor type and stage. In metastatic colorectal cancer, RAS, BRAF, and MSI/dMMR should be available early because they can affect first-line strategy. HER2 is particularly relevant in selected RAS wild-type metastatic colorectal cancers. In gastric or gastroesophageal adenocarcinoma, HER2, PD-L1, MSI/dMMR, and increasingly CLDN18.2 can shape systemic treatment. In pancreatic and biliary cancers, broader genomic profiling can uncover uncommon but actionable alterations.
How to interpret CEA, CA 19-9, MSI, KRAS, BRAF, and HER2
A rising CEA or CA 19-9 is a signal to interpret, not proof of progression. Serial change, imaging, symptoms, liver tests, smoking status, biliary obstruction, and treatment timing all matter. Laboratories use their own reference intervals; a mildly abnormal result often has less specificity than a large, sustained change.
MSI-high or dMMR means the tumor has impaired DNA mismatch repair. In colorectal and several other cancers, this can predict meaningful sensitivity to immune checkpoint inhibitors. Loss of certain MMR proteins can also guide hereditary workup. A KRAS or NRAS activating mutation in colorectal cancer generally predicts lack of benefit from cetuximab or panitumumab. BRAF V600E identifies a biologically distinct colorectal subgroup with targeted-treatment implications. HER2 positivity requires cancer-specific scoring; the words “HER2 positive” should therefore be read with the IHC score, amplification result, and tumor type.
How biomarker results change treatment decisions
The strongest use of molecular biomarkers is predictive: identifying a treatment that is more or less likely to work. In metastatic colorectal cancer, RAS wild-type status is necessary before standard anti-EGFR therapy is considered. BRAF V600E can direct use of BRAF-targeted combinations. MSI-H/dMMR can move immunotherapy to a central role. HER2-positive, RAS wild-type colorectal cancer has dedicated HER2-targeted options after prior chemotherapy.
Serum markers play a different role. CEA may support postoperative surveillance or monitoring of metastatic colorectal cancer when it was elevated at baseline. CA 19-9 can help follow pancreatic or biliary cancer when the patient is a secretor and the marker tracks with disease. Neither should overrule imaging or pathology. A discordant marker is a reason to look for an explanation, not a reason to assume the scan or biopsy is wrong.
Limitations, false positives, and false negatives
No biomarker works in isolation. A technically accurate result can still be clinically misleading if it is applied to the wrong cancer type, disease stage, specimen, or treatment question. Cutoffs may also differ by assay, drug label, guideline, and country. For that reason, the laboratory’s own interpretive criteria and the treating team’s current guideline should take priority over a generic internet threshold.
Tumors are heterogeneous, meaning different areas can carry different alterations or levels of protein expression. A small biopsy may miss a positive clone, while a blood-based assay can miss disease that sheds little DNA into the circulation. Conversely, a detectable alteration may be real but not be the main driver of the current disease. Pre-analytic issues such as delayed fixation, decalcification, low tumor content, recent transfusion, or poor plasma handling can also affect some assays.
The safest interpretation separates three questions: analytical validity—did the assay measure what it claims to measure; clinical validity—does the result correlate with the cancer feature of interest; and clinical utility—does acting on the result improve a meaningful decision for this patient. A result can be strong in one category and limited in another.
Questions to ask before acting on a biomarker panel
Ask which marker is being used for diagnosis, prognosis, treatment selection, hereditary screening, or follow-up. Ask whether the test was performed on the primary tumor or a metastasis, and whether enough tumor was present. For a sequencing report, ask which genes and variant classes were covered and whether copy-number changes and fusions were included.
For CEA or CA 19-9, ask whether the value was elevated before treatment and whether there are benign reasons for a change. For MSI/dMMR, ask whether abnormal findings require germline genetic counseling. For RAS, BRAF, or HER2, ask whether the result changes an FDA-labeled option, a guideline-recommended therapy, or a clinical-trial opportunity. These questions turn a long report into a decision map rather than a list of laboratory facts.
Practical next steps after results
A biomarker result should be read beside the pathology report, stage, imaging, treatment history, and the exact specimen tested. A useful question for the oncology team is not simply “is this positive?” but “what decision does this result change now?” That keeps the result tied to a concrete action such as confirming a diagnosis, choosing a drug, deciding whether hereditary evaluation is needed, or setting a surveillance plan.
If a result seems inconsistent with the clinical picture, ask whether the sample had enough viable tumor, whether the method covered the relevant alteration, and whether a newer metastatic or recurrent specimen would be more representative. Repeating a test is most useful when there is a specific reason to think the original specimen was inadequate, old, or biologically different from the disease being treated today.
Patients should also keep a copy of the complete molecular or pathology report, not only a portal summary. The full report usually lists the method, specimen, tumor percentage, assay limitations, exact variant or staining score, and interpretive comments. Those details matter when seeking a second opinion, transferring care, or checking eligibility for a targeted therapy or clinical trial.
One practical way to avoid overreading GI Cancer Biomarker Panel is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for GI Cancer Biomarker Panel may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
Laboratory reports also vary in how much interpretation they provide. Some give only a final category; others show raw staining percentages, copy-number estimates, variant allele fractions, quality metrics, and assay limitations. For GI Cancer Biomarker Panel, the detailed version is preferable because treatment criteria can evolve. A result that was not actionable when the tissue was first tested may become relevant later, and the original numerical or molecular detail may allow the oncology team to reassess eligibility without immediately repeating a biopsy.
Finally, biomarker testing works best as part of multidisciplinary care. Pathologists judge specimen quality and assay interpretation; medical oncologists connect the finding to treatment; surgeons and gastroenterologists provide disease context; genetic counselors address possible inherited risk when appropriate. Patients do not need to master every technical detail, but they benefit from knowing the purpose of the test, the exact result, what uncertainty remains, and what concrete decision follows. Those four questions turn a complex biomarker report into a usable plan.
One practical way to avoid overreading GI Cancer Biomarker Panel is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
References
- SEOM-GEMCAD-TTD clinical guidelines for the systemic treatment of metastatic colorectal cancer (2022) 2023 (Guideline)
- Molecular Biomarkers for the Evaluation of Colorectal Cancer: Guideline From the American Society for Clinical Pathology, College of American Pathologists, Association for Molecular Pathology, and American Society of Clinical Oncology 2017 (Guideline)
- HER2-targeted therapy in colorectal cancer: a comprehensive review 2025 (Review)
- FDA grants accelerated approval to tucatinib with trastuzumab for colorectal cancer 2023 (Official)
- Japanese society for cancer of the colon and rectum (JSCCR) guidelines 2024 for the clinical practice of hereditary colorectal cancer 2025 (Guideline)
Disclaimer
This article explains biomarker testing for educational purposes and is not a diagnosis or treatment plan. Cancer testing and treatment should be interpreted by the oncology and pathology teams using the complete medical record, current guidelines, and the specific laboratory method. Seek prompt medical care for new or rapidly worsening symptoms rather than relying on a biomarker result alone.