MLH1 promoter methylation testing helps explain why a colorectal cancer has lost MLH1/PMS2 mismatch-repair proteins or shows microsatellite instability. In many older adults, MLH1 loss is caused by a somatic epigenetic change—methylation of the MLH1 promoter—that switches the gene off in the tumor. That pattern strongly favors a sporadic MSI-high cancer rather than classic Lynch syndrome. The test is therefore a triage step after tumor screening, not a general colon-cancer screening test and not a germline genetic test. A methylated result can substantially lower the probability of Lynch syndrome, but it is not an absolute exclusion in every patient because rare constitutional MLH1 epimutations and Lynch-associated tumors with secondary methylation have been reported. Age at diagnosis, family history, BRAF V600E status, tumor pattern, and genetics expertise still matter. An unmethylated MLH1-deficient tumor usually warrants germline evaluation and, when germline testing is negative, consideration of paired tumor-normal testing for double-somatic causes.
- MLH1 methylation is mainly ordered after a colorectal tumor shows loss of MLH1 and PMS2 or an MSI-high pattern.
- Tumor MLH1 promoter methylation strongly supports a sporadic pathway, especially in an older patient without a strong Lynch-type family history.
- An unmethylated MLH1-deficient tumor raises concern for Lynch syndrome and usually leads to germline genetic evaluation.
- BRAF V600E and MLH1 methylation are alternative tumor-triage tools in many colorectal workflows; neither is a germline test.
- Rare exceptions mean a methylated result should not automatically end hereditary evaluation when clinical suspicion remains high.
Table of Contents
- Why MLH1 promoter methylation causes dMMR and MSI
- When MLH1 methylation testing is ordered
- What a methylated MLH1 result means
- What an unmethylated result means
- How MLH1 methylation relates to treatment
- Limitations and rare exceptions
- Practical next steps after MLH1 methylation testing
Why MLH1 promoter methylation causes dMMR and MSI
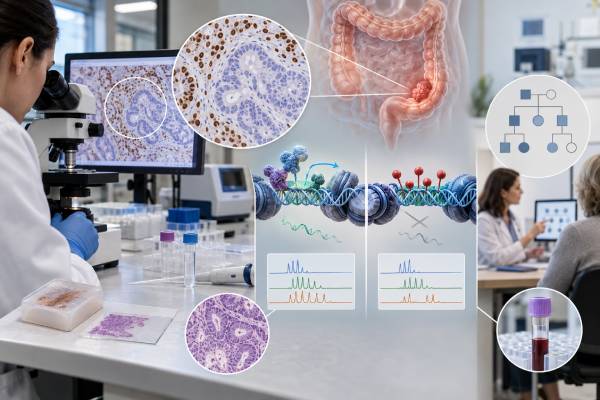
The MLH1 promoter is a regulatory region that helps control MLH1 gene expression. When cytosine residues in that region become heavily methylated, transcription can be silenced. Loss of MLH1 protein usually destabilizes PMS2, so immunohistochemistry commonly shows paired loss of MLH1 and PMS2. DNA-copying errors then accumulate at microsatellites, producing MSI-high status.
In sporadic colorectal cancer, this pathway often occurs as part of the CpG island methylator phenotype and is associated with BRAF V600E in many tumors. Lynch syndrome, by contrast, is caused by an inherited pathogenic variant in an MMR gene or EPCAM-related mechanism. The tumor tests overlap in phenotype but differ in cause.
When MLH1 methylation testing is ordered
Universal colorectal tumor screening commonly begins with MMR immunohistochemistry or MSI testing. If MLH1 and PMS2 are lost, the next question is whether the MLH1 loss is sporadic or inherited. Tumor MLH1 promoter methylation is one way to answer that question. BRAF V600E testing is another common triage tool because BRAF V600E strongly favors a sporadic MLH1-methylated pathway in colorectal cancer.
The exact algorithm varies by health system. Some laboratories reflex directly to methylation; others test BRAF first. Endometrial-cancer workflows are different because BRAF has little value there. The result should therefore be interpreted within the cancer-specific Lynch screening algorithm.
What a methylated MLH1 result means
A methylated MLH1 promoter in an MLH1/PMS2-deficient colorectal tumor makes a sporadic origin much more likely. In an older patient with no suggestive personal or family history, this often prevents unnecessary germline testing. The result is tumor-specific and does not mean the patient’s normal cells carry methylation.
The important qualifier is “much more likely,” not “impossible to be inherited.” Rare constitutional MLH1 epimutations can be present beyond the tumor, and studies have documented MLH1 methylation as a secondary event in some Lynch syndrome cancers. Young age, multiple Lynch-spectrum tumors, or a strong family history can therefore justify genetics referral despite tumor methylation.
What an unmethylated result means
When MLH1/PMS2 is lost and the MLH1 promoter is not methylated, the tumor lacks the common sporadic explanation for MLH1 silencing. That raises the probability of Lynch syndrome and usually leads to germline testing of MLH1 and the other relevant genes, guided by the MMR pattern and genetic counselor.
If germline testing is negative, the case is not automatically unexplained Lynch syndrome. Many dMMR tumors are caused by two somatic hits in mismatch-repair genes. Paired tumor-normal sequencing can distinguish double-somatic disease from an inherited variant that was missed by a limited germline method. The distinction affects relatives as well as the patient.
How MLH1 methylation relates to treatment
MLH1 promoter methylation explains the cause of dMMR but does not erase the tumor’s MSI-H/dMMR phenotype. For treatment selection, the clinically important predictive biomarker is usually MSI-H or dMMR itself, which can support immune checkpoint therapy in appropriate colorectal cancer settings.
The methylation result mainly changes hereditary-risk interpretation. It should not be used as a reason to deny immunotherapy when the tumor otherwise meets dMMR/MSI-H criteria. Conversely, a methylated tumor does not by itself prove that immunotherapy is needed; stage, disease setting, and current treatment guidelines determine use.
Limitations and rare exceptions
No biomarker works in isolation. A technically accurate result can still be clinically misleading if it is applied to the wrong cancer type, disease stage, specimen, or treatment question. Cutoffs may also differ by assay, drug label, guideline, and country. For that reason, the laboratory’s own interpretive criteria and the treating team’s current guideline should take priority over a generic internet threshold.
Tumors are heterogeneous, meaning different areas can carry different alterations or levels of protein expression. A small biopsy may miss a positive clone, while a blood-based assay can miss disease that sheds little DNA into the circulation. Conversely, a detectable alteration may be real but not be the main driver of the current disease. Pre-analytic issues such as delayed fixation, decalcification, low tumor content, recent transfusion, or poor plasma handling can also affect some assays.
The safest interpretation separates three questions: analytical validity—did the assay measure what it claims to measure; clinical validity—does the result correlate with the cancer feature of interest; and clinical utility—does acting on the result improve a meaningful decision for this patient. A result can be strong in one category and limited in another.
Practical next steps after MLH1 methylation testing
A biomarker result should be read beside the pathology report, stage, imaging, treatment history, and the exact specimen tested. A useful question for the oncology team is not simply “is this positive?” but “what decision does this result change now?” That keeps the result tied to a concrete action such as confirming a diagnosis, choosing a drug, deciding whether hereditary evaluation is needed, or setting a surveillance plan.
If a result seems inconsistent with the clinical picture, ask whether the sample had enough viable tumor, whether the method covered the relevant alteration, and whether a newer metastatic or recurrent specimen would be more representative. Repeating a test is most useful when there is a specific reason to think the original specimen was inadequate, old, or biologically different from the disease being treated today.
Patients should also keep a copy of the complete molecular or pathology report, not only a portal summary. The full report usually lists the method, specimen, tumor percentage, assay limitations, exact variant or staining score, and interpretive comments. Those details matter when seeking a second opinion, transferring care, or checking eligibility for a targeted therapy or clinical trial.
One practical way to avoid overreading MLH1 Promoter Methylation Test is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for MLH1 Promoter Methylation Test may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
Laboratory reports also vary in how much interpretation they provide. Some give only a final category; others show raw staining percentages, copy-number estimates, variant allele fractions, quality metrics, and assay limitations. For MLH1 Promoter Methylation Test, the detailed version is preferable because treatment criteria can evolve. A result that was not actionable when the tissue was first tested may become relevant later, and the original numerical or molecular detail may allow the oncology team to reassess eligibility without immediately repeating a biopsy.
Finally, biomarker testing works best as part of multidisciplinary care. Pathologists judge specimen quality and assay interpretation; medical oncologists connect the finding to treatment; surgeons and gastroenterologists provide disease context; genetic counselors address possible inherited risk when appropriate. Patients do not need to master every technical detail, but they benefit from knowing the purpose of the test, the exact result, what uncertainty remains, and what concrete decision follows. Those four questions turn a complex biomarker report into a usable plan.
One practical way to avoid overreading MLH1 Promoter Methylation Test is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for MLH1 Promoter Methylation Test may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
Laboratory reports also vary in how much interpretation they provide. Some give only a final category; others show raw staining percentages, copy-number estimates, variant allele fractions, quality metrics, and assay limitations. For MLH1 Promoter Methylation Test, the detailed version is preferable because treatment criteria can evolve. A result that was not actionable when the tissue was first tested may become relevant later, and the original numerical or molecular detail may allow the oncology team to reassess eligibility without immediately repeating a biopsy.
Finally, biomarker testing works best as part of multidisciplinary care. Pathologists judge specimen quality and assay interpretation; medical oncologists connect the finding to treatment; surgeons and gastroenterologists provide disease context; genetic counselors address possible inherited risk when appropriate. Patients do not need to master every technical detail, but they benefit from knowing the purpose of the test, the exact result, what uncertainty remains, and what concrete decision follows. Those four questions turn a complex biomarker report into a usable plan.
One practical way to avoid overreading MLH1 Promoter Methylation Test is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for MLH1 Promoter Methylation Test may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
Laboratory reports also vary in how much interpretation they provide. Some give only a final category; others show raw staining percentages, copy-number estimates, variant allele fractions, quality metrics, and assay limitations. For MLH1 Promoter Methylation Test, the detailed version is preferable because treatment criteria can evolve. A result that was not actionable when the tissue was first tested may become relevant later, and the original numerical or molecular detail may allow the oncology team to reassess eligibility without immediately repeating a biopsy.
Finally, biomarker testing works best as part of multidisciplinary care. Pathologists judge specimen quality and assay interpretation; medical oncologists connect the finding to treatment; surgeons and gastroenterologists provide disease context; genetic counselors address possible inherited risk when appropriate. Patients do not need to master every technical detail, but they benefit from knowing the purpose of the test, the exact result, what uncertainty remains, and what concrete decision follows. Those four questions turn a complex biomarker report into a usable plan.
One practical way to avoid overreading MLH1 Promoter Methylation Test is to separate the laboratory finding from the clinical decision. The report may be analytically clear while the next step remains conditional on stage, prior therapy, other biomarkers, and patient goals. For example, a result that is highly relevant in metastatic disease may have no established treatment role after curative surgery. Likewise, a biomarker that predicts drug resistance is not necessarily a marker of worse overall prognosis. Keeping those categories separate makes the report easier to use and prevents a single word such as “positive” from carrying more meaning than the evidence supports.
The specimen date deserves attention. Cancer evolves under treatment, and the sample used for MLH1 Promoter Methylation Test may have been collected months or years before the current decision. Early driver alterations often remain stable, but protein expression, copy number, and acquired resistance mechanisms can change. Retesting is most valuable when there is a plausible biological reason for change and when a new result could alter management. Repeating testing merely because a value is available is less useful than choosing the specimen that best represents the disease being treated now.
Laboratory reports also vary in how much interpretation they provide. Some give only a final category; others show raw staining percentages, copy-number estimates, variant allele fractions, quality metrics, and assay limitations. For MLH1 Promoter Methylation Test, the detailed version is preferable because treatment criteria can evolve. A result that was not actionable when the tissue was first tested may become relevant later, and the original numerical or molecular detail may allow the oncology team to reassess eligibility without immediately repeating a biopsy.
Finally, biomarker testing works best as part of multidisciplinary care. Pathologists judge specimen quality and assay interpretation; medical oncologists connect the finding to treatment; surgeons and gastroenterologists provide disease context; genetic counselors address possible inherited risk when appropriate. Patients do not need to master every technical detail, but they benefit from knowing the purpose of the test, the exact result, what uncertainty remains, and what concrete decision follows. Those four questions turn a complex biomarker report into a usable plan.
References
- Japanese society for cancer of the colon and rectum (JSCCR) guidelines 2024 for the clinical practice of hereditary colorectal cancer 2025 (Guideline)
- A registry-based study on universal screening for defective mismatch repair in colorectal cancer in Denmark highlights disparities in screening uptake and counselling referrals 2024 (Study)
- Universal tumor screening for lynch syndrome on colorectal cancer biopsies impacts surgical treatment decisions 2023 (Study)
- MLH1 Promoter Methylation Could Be the Second Hit in Lynch Syndrome Carcinogenesis 2023 (Study)
- Molecular Biomarkers for the Evaluation of Colorectal Cancer: Guideline From the American Society for Clinical Pathology, College of American Pathologists, Association for Molecular Pathology, and American Society of Clinical Oncology 2017 (Guideline)
Disclaimer
This article explains biomarker testing for educational purposes and is not a diagnosis or treatment plan. Cancer testing and treatment should be interpreted by the oncology and pathology teams using the complete medical record, current guidelines, and the specific laboratory method. Seek prompt medical care for new or rapidly worsening symptoms rather than relying on a biomarker result alone.