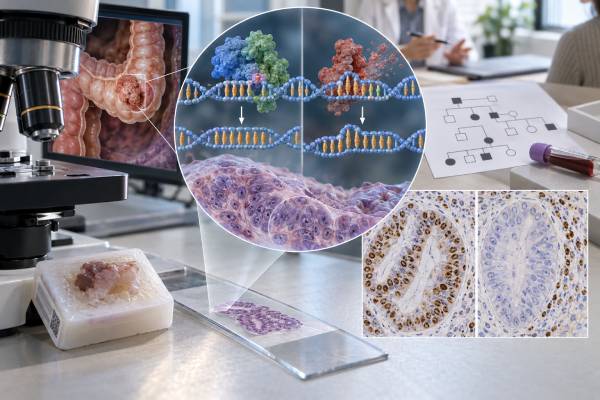
An MSI test for colon cancer checks whether a tumor has trouble repairing small DNA copying errors. When this repair system fails, short repeated DNA sequences called microsatellites become unstable. A tumor may therefore be reported as microsatellite instability-high (MSI-H) or as mismatch repair-deficient (dMMR). These findings matter for two major reasons: they can affect treatment, especially the use of immune checkpoint inhibitors in advanced disease, and they can raise the possibility of Lynch syndrome, an inherited cancer-predisposition condition. MSI testing is performed on tumor tissue, often along with mismatch repair immunohistochemistry (MMR IHC). The two methods examine the same biological pathway from different angles and usually agree. A positive tumor result does not by itself prove that a person has Lynch syndrome, because many dMMR colon cancers are caused by changes confined to the tumor. Correct interpretation depends on the exact test method, the pattern of lost MMR proteins, tumor stage, age, family history, and follow-up molecular testing.
- MSI-H or dMMR means the tumor has defective DNA mismatch repair; it does not automatically mean Lynch syndrome.
- MSS or pMMR means no major mismatch-repair defect was detected by the test, although rare hereditary cases can still require genetic evaluation.
- In metastatic colon cancer, MSI-H/dMMR status is a major predictive biomarker for immune checkpoint inhibitor treatment.
- Loss of MLH1 and PMS2 often triggers BRAF V600E and/or MLH1 promoter methylation testing to distinguish sporadic tumors from possible Lynch syndrome.
- MSI/MMR testing is generally performed on tumor tissue and usually requires no special patient preparation.
Table of Contents
- What MSI Testing Measures
- How MSI and MMR Tests Are Performed
- What MSI-H, dMMR, MSS, and pMMR Mean
- Lynch Syndrome and Follow-Up Testing
- How Results Affect Colon Cancer Treatment
- Limitations, Discordant Results, and Common Mistakes
- Questions to Ask After an MSI Result
What MSI Testing Measures
Microsatellite instability testing looks for a characteristic pattern of DNA errors that develops when the mismatch repair system is not working properly. During normal cell division, DNA is copied billions of letters at a time. Small insertion or deletion mistakes can occur, particularly in microsatellites, which are short repeated stretches of DNA. The mismatch repair system normally recognizes and repairs many of these mistakes.
Four proteins are central to routine colon-cancer testing: MLH1, PMS2, MSH2, and MSH6. They work in pairs. MLH1 pairs mainly with PMS2, while MSH2 pairs mainly with MSH6. If a gene is inactivated, the corresponding protein or protein pair may disappear on immunohistochemistry, and the tumor may accumulate enough DNA errors to become MSI-H.
MSI and MMR are closely related but are not identical terms. MSI describes the DNA-level consequence, while MMR describes the repair machinery itself. That is why reports may use either MSI-H/dMMR or MSS/pMMR. A small minority of tumors can produce discordant results, such as an abnormal MMR stain with a non-MSI-H molecular result, so the original pathology and testing method sometimes need review.
In colon cancer, MSI/MMR testing serves several purposes at once. It can:
- identify a molecular subtype of colon cancer;
- help estimate prognosis in certain stages;
- help guide adjuvant treatment decisions in stage II disease;
- identify patients with metastatic disease who may benefit strongly from immunotherapy; and
- act as a screening step for Lynch syndrome.
The test is not a general blood tumor-marker test. It does not measure how much cancer is present, and an MSI-H result is not a stage. A small localized tumor and a widely metastatic tumor can both be MSI-H. Stage is determined by the tumor’s local invasion, lymph-node involvement, and distant spread, while MSI/MMR describes tumor biology.
The prevalence of MSI-H/dMMR varies by setting. It is more common in earlier-stage colon cancer and less common among metastatic tumors. The exact percentage differs across populations, tumor locations, and study methods, but roughly 10%–15% of newly diagnosed colorectal cancers are often reported as dMMR/MSI-H, whereas the proportion in metastatic disease is lower. Right-sided colon cancers, mucinous features, prominent lymphocytes, and certain histologic patterns may increase suspicion, but pathology appearance cannot replace testing.
How MSI and MMR Tests Are Performed
Most patients do not need a separate procedure specifically for MSI/MMR testing. The laboratory usually uses tissue that was already obtained during colonoscopy biopsy or surgery. The pathology department selects an area containing enough tumor cells and performs one or more laboratory methods.
Mismatch repair immunohistochemistry
MMR IHC uses antibodies to determine whether the MLH1, PMS2, MSH2, and MSH6 proteins are present in tumor-cell nuclei. Normal noncancerous cells on the same slide provide an internal control. If tumor cells lose staining for one or more proteins while surrounding cells stain normally, the pattern is interpreted as loss of MMR protein expression.
The pattern can point toward the next step:
- MLH1 and PMS2 loss: often caused by MLH1 inactivation. In colon cancer, testing for tumor BRAF V600E and/or MLH1 promoter methylation can help determine whether the finding is more likely sporadic.
- MSH2 and MSH6 loss: raises concern for an abnormality involving MSH2 or related mechanisms and generally supports hereditary evaluation.
- Isolated MSH6 loss: can point toward MSH6 dysfunction.
- Isolated PMS2 loss: can point toward PMS2 dysfunction.
These are interpretive patterns, not final hereditary diagnoses. Germline testing is required to determine whether a pathogenic variant is inherited.
MSI by PCR or next-generation sequencing
A molecular MSI assay evaluates microsatellite loci for abnormal length variation. Traditional polymerase chain reaction (PCR) methods examine a defined panel of microsatellite markers. Next-generation sequencing (NGS) can assess MSI while simultaneously profiling many cancer-related genes, depending on the assay.
Molecular reports commonly classify tumors as MSI-H or microsatellite stable (MSS). Some older assays also used an MSI-low category, but current clinical interpretation for colon cancer often focuses on MSI-H versus non-MSI-H because that distinction is more useful for treatment decisions.
No fasting, medication change, or special timing is usually needed because the test is performed on stored tissue. Practical issues are mainly laboratory issues: whether enough viable tumor is present, whether the specimen was adequately fixed, and whether prior treatment has altered the tissue. If a small biopsy is inadequate, testing may be repeated on a resection specimen or another tumor sample.
When the result will determine immunotherapy eligibility, the laboratory should use a validated method appropriate for colorectal cancer. Professional guidance supports MMR IHC, MSI PCR, and appropriately validated NGS approaches in colorectal cancer. If the clinical picture and test result strongly conflict, repeating or confirming the test with an orthogonal method can be reasonable.
What MSI-H, dMMR, MSS, and pMMR Mean
An MSI-H result means the tumor shows instability across enough tested microsatellite markers to meet the assay’s high-instability threshold. A dMMR result means one or more mismatch repair proteins are absent or the repair system is otherwise shown to be deficient. These results usually describe the same biological phenotype.
MSI-H/dMMR tumors accumulate large numbers of mutations. Those mutations can create abnormal proteins that the immune system recognizes as foreign, which helps explain why immune checkpoint inhibitors can work particularly well in this group. This is a predictive use of the biomarker: the result helps estimate the likelihood of benefit from a specific treatment class.
An MSS result means the assay did not detect high-level microsatellite instability. A pMMR result means the four standard mismatch repair proteins are retained on IHC. Most colon cancers are MSS/pMMR. This result generally makes a classic mismatch-repair defect less likely, but it does not mean the cancer is biologically simple, low-risk, or nonhereditary. Colon cancers can be driven by many other molecular changes, including RAS, BRAF, HER2, and other alterations.
The result also has prognostic meaning in localized disease. Stage II dMMR/MSI-H colon cancers generally have a more favorable natural history than comparable pMMR/MSS tumors. This is one reason MMR status is considered when deciding whether adjuvant fluoropyrimidine chemotherapy is worthwhile after surgery for stage II colon cancer. Prognosis is still influenced strongly by T stage, obstruction or perforation, lymphovascular or perineural invasion, tumor budding, number of lymph nodes examined, and other pathology findings.
A key distinction is that MSI-H is not the same as a positive inherited genetic test. Tumor cells can lose mismatch repair because of acquired, noninherited changes. The most common example is MLH1 promoter hypermethylation, which switches off MLH1 in the tumor. This sporadic mechanism is especially common in older patients and may occur with a BRAF V600E mutation.
Likewise, MSS does not completely exclude Lynch syndrome. Most Lynch-associated colorectal cancers are dMMR/MSI-H, but unusual variants, technical issues, or particular tumor contexts can produce unexpected patterns. A person with a very young diagnosis, multiple Lynch-associated cancers, or a compelling family history may still need genetic counseling even when tumor screening appears normal.
Lynch Syndrome and Follow-Up Testing
Lynch syndrome is caused by an inherited pathogenic variant affecting a mismatch repair gene or, in some families, EPCAM. People with Lynch syndrome have increased risks of colorectal cancer and several other cancers, including endometrial cancer and, depending on the gene, cancers of the ovary, stomach, urinary tract, small bowel, pancreas, biliary tract, brain, and certain skin tumors.
Universal or near-universal tumor screening for MMR deficiency is widely used in newly diagnosed colorectal cancer because family history alone misses many affected people. The tumor test is therefore a screening gateway, not the final Lynch syndrome test.
When IHC shows MLH1/PMS2 loss, the next step often includes BRAF V600E testing, MLH1 promoter methylation testing, or both. A BRAF V600E mutation in a colorectal tumor strongly favors a sporadic process rather than Lynch syndrome. MLH1 promoter hypermethylation also supports sporadic MLH1 silencing. However, interpretation should be individualized, particularly in younger patients or families with a strong hereditary pattern.
When the tumor shows MSH2/MSH6 loss, isolated MSH6 loss, or isolated PMS2 loss, hereditary evaluation is usually more direct because those patterns are less commonly explained by the same sporadic MLH1 methylation pathway.
Germline testing uses blood, saliva, or another normal-tissue source to look for an inherited pathogenic variant. A genetic counselor or clinician trained in hereditary cancer can explain possible outcomes:
- Pathogenic or likely pathogenic variant: supports a hereditary diagnosis and can change screening recommendations for the patient and relatives.
- Negative result: no inherited pathogenic variant was identified in the genes tested. In a dMMR tumor, additional tumor testing may be needed to explain the mismatch-repair defect.
- Variant of uncertain significance (VUS): a DNA change is present, but evidence is insufficient to classify it as harmful. A VUS should not be treated as a positive Lynch syndrome result.
Some dMMR tumors have two acquired mutations in mismatch repair genes within the tumor but no germline pathogenic variant. These are sometimes called double-somatic cases. Recognizing them can prevent incorrectly labeling a family with Lynch syndrome.
If Lynch syndrome is confirmed, the implications extend beyond the person with colon cancer. First-degree relatives may have a 50% chance of carrying the familial variant when the syndrome follows the usual autosomal-dominant pattern. Targeted testing of adult relatives can identify who needs intensified cancer surveillance and who did not inherit the familial variant.
How Results Affect Colon Cancer Treatment
The treatment impact of MSI/MMR status depends strongly on cancer stage.
Stage II colon cancer
For resected stage II colon cancer, dMMR/MSI-H status is generally associated with a favorable prognosis and less benefit from fluoropyrimidine-only adjuvant chemotherapy. ASCO guidance does not recommend routine adjuvant chemotherapy for patients with stage II disease who are not in a high-risk subgroup, and dMMR/MSI-H tumors are not routinely treated with fluoropyrimidine alone solely to reduce recurrence risk.
High-risk pathology can change the discussion. T4 disease, inadequate lymph-node sampling, obstruction, perforation, lymphovascular or perineural invasion, poor differentiation in appropriate contexts, and high-grade tumor budding can increase recurrence risk. When treatment is chosen for a high-risk dMMR/MSI-H stage II tumor, the regimen decision should be made with an oncologist and may involve an oxaliplatin-containing combination rather than fluoropyrimidine alone.
Stage III colon cancer
Stage III disease has lymph-node involvement and is usually treated with adjuvant chemotherapy after surgery when the patient can tolerate it. MMR status provides useful biological information but does not replace stage-based treatment planning. The number of involved nodes, depth of tumor invasion, patient health, neuropathy risk, and expected benefit from chemotherapy remain central.
Metastatic colon cancer
In unresectable or metastatic colorectal cancer, MSI-H/dMMR is one of the most important treatment-selection biomarkers. Immune checkpoint blockade can produce deep and durable responses in a meaningful proportion of patients. Current guidelines include pembrolizumab as a preferred first-line option for many patients with MSI-H/dMMR metastatic colorectal cancer, while other immune checkpoint strategies may be used depending on the clinical setting, approvals, prior therapy, and patient factors.
The reason to test early is practical: if metastatic disease is MSI-H/dMMR, the first systemic treatment may be fundamentally different from the approach used for an MSS/pMMR tumor. For MSS/pMMR metastatic cancer, treatment selection depends on additional biomarkers such as RAS, BRAF, HER2, and tumor location, along with clinical factors.
MSI status should never be interpreted in isolation. A person can have an MSI-H tumor and still need surgery, radiation in selected rectal-cancer contexts, chemotherapy, targeted therapy, or other treatment depending on stage and response. Biomarkers refine the treatment plan; they do not replace complete oncology assessment.
Limitations, Discordant Results, and Common Mistakes
MSI/MMR testing is highly useful, but several pitfalls can lead to wrong conclusions.
Mistake 1: assuming dMMR equals Lynch syndrome. A large share of dMMR colorectal cancers, especially those with MLH1/PMS2 loss in older adults, are sporadic. BRAF and/or MLH1 promoter methylation testing helps separate common sporadic cases from those needing stronger hereditary suspicion.
Mistake 2: assuming MSS rules out hereditary cancer. Tumor screening is powerful but not perfect. A young age at diagnosis, multiple primary cancers, or a strong family history may justify germline evaluation despite a normal tumor screen.
Mistake 3: treating MSI as a recurrence marker. MSI is a tumor characteristic, not a serial measurement of tumor burden. It is not used like CEA or circulating tumor DNA to track whether the amount of cancer is rising or falling.
Mistake 4: comparing results from different specimen types without context. A biopsy, surgical specimen, and metastatic lesion can differ in tumor content and treatment exposure. Technical limitations can affect assay performance. A pathology review may be needed when results disagree.
Mistake 5: ignoring the exact IHC loss pattern. “Abnormal MMR” is only the beginning. MLH1/PMS2 loss leads to a different hereditary workup than isolated MSH6 loss.
True discordance between MMR IHC and MSI molecular testing is uncommon but real. Possible explanations include technical artifacts, low tumor content, unusual missense variants that preserve protein staining despite functional loss, treatment effects, or differences in assay sensitivity. When discordance would change treatment or hereditary counseling, clinicians may repeat the assay, test another specimen, use a second method, or request expert molecular-pathology review.
Tumor heterogeneity can also matter. Most colorectal cancers have stable MMR status across the tumor, but rare heterogeneous staining patterns exist. Pathologists distinguish true loss from weak staining, fixation artifacts, and absent internal controls.
Finally, a result must be read in the right clinical time frame. A historical MSI test performed with an older assay may still be valid, but if the report is incomplete or the original material is uncertain, retesting can be considered when treatment depends on the result.
Questions to Ask After an MSI Result
A useful follow-up conversation focuses on what the result changes now and what still needs to be clarified. Consider asking:
- Was the tumor tested by MMR IHC, MSI PCR, NGS, or more than one method?
- Is the result MSI-H/dMMR or MSS/pMMR?
- If IHC was abnormal, which proteins were lost?
- If MLH1/PMS2 were lost, was BRAF V600E or MLH1 promoter methylation tested?
- Do I meet criteria for germline genetic testing or genetic counseling?
- Does this result change whether I should receive adjuvant chemotherapy?
- If my cancer is metastatic, does this result make immunotherapy an option now?
- Are additional tumor biomarkers needed before treatment is selected?
- Should relatives receive genetic counseling if a hereditary pathogenic variant is found?
Patients should also keep a copy of the original pathology and molecular report. The exact wording matters more than a verbal summary such as “MSI positive.” A complete report shows the assay, specimen, result category, and often the protein-loss pattern or molecular markers tested.
If a germline pathogenic variant is identified, the next step is not simply “more colonoscopies.” Surveillance is tailored to the specific gene, personal history, sex, age, prior surgeries, and family pattern. Some people need screening for extracolonic cancers as well. Relatives should generally be offered testing for the known familial variant rather than broad testing without context.
For treatment decisions, the most useful question is often: Is this biomarker prognostic, predictive, hereditary, or some combination of the three in my situation? In colon cancer, MSI/MMR can serve all three roles, but the meaning changes with stage. That is why the same laboratory result can affect a stage II adjuvant discussion, a metastatic immunotherapy decision, and a hereditary cancer evaluation in different ways.
References
- Mismatch Repair and Microsatellite Instability Testing for Immune Checkpoint Inhibitor Therapy: Guideline From the College of American Pathologists in Collaboration With the Association for Molecular Pathology and Fight Colorectal Cancer 2022 (Guideline)
- Mismatch Repair and Microsatellite Instability Testing for Immune Checkpoint Inhibitor Therapy: ASCO Endorsement of College of American Pathologists Guideline 2023 (Guideline)
- Treatment of Metastatic Colorectal Cancer: ASCO Guideline 2023 (Guideline)
- Metastatic colorectal cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up 2023 (Guideline)
- Lynch Syndrome in Context of the Updated German S3 Guideline Colorectal Cancer: Implementation of Universal MMR/MSI Testing 2025 (Guideline Review)
Disclaimer
This article is for general education and does not replace advice from an oncologist, pathologist, or genetics professional. MSI/MMR results must be interpreted with cancer stage, pathology, family history, and the exact laboratory method. Do not start, stop, or change cancer treatment based on a biomarker result without discussing it with the treating cancer team.