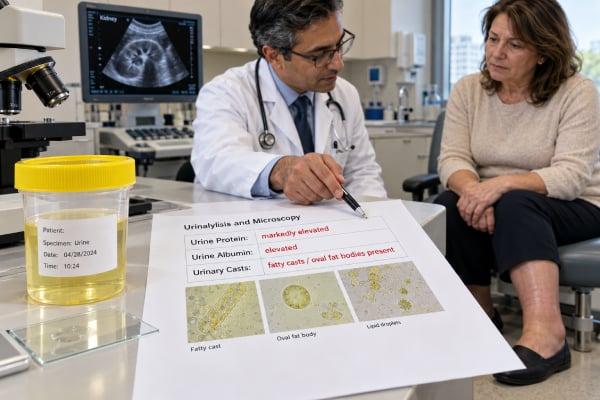
A nephrotic syndrome urine evaluation looks for very heavy protein loss and for urine findings that support a glomerular kidney disorder. The key measurement is quantitative proteinuria, usually with a spot urine protein-to-creatinine ratio (UPCR) or, in selected situations, a 24-hour urine protein collection. Urine albumin is often markedly increased because nephrotic syndrome reflects severe leakage across the glomerular filtration barrier. Routine urinalysis may show 3+ or 4+ protein, while microscopy can reveal oval fat bodies, lipid droplets, or fatty casts. These findings support the diagnosis but do not identify the exact glomerular disease. Nephrotic syndrome is a clinical syndrome, not a single urine-test result: heavy proteinuria is interpreted together with low serum albumin, edema, blood lipids, kidney function, and the underlying cause. In adults, nephrotic-range proteinuria is traditionally around 3.5 g or more per 24 hours, but spot ratios are commonly used to quantify protein loss without a full-day collection.
- Nephrotic-range proteinuria in adults is commonly about 3.5 g/24 h or more, or a roughly equivalent very high UPCR, but the full syndrome also involves hypoalbuminemia and often edema.
- A standard dipstick can strongly suggest heavy albumin-rich proteinuria, but quantitative UPCR or 24-hour urine protein is needed to measure the amount.
- Fatty casts and oval fat bodies can occur with nephrotic syndrome because lipids enter urine along with heavy protein loss.
- Red blood cell casts or strongly active urine sediment are not classic isolated nephrotic findings and can suggest an inflammatory glomerulonephritis or mixed nephritic-nephrotic picture.
- Urine tests confirm the pattern of protein loss; blood tests, serology, and sometimes kidney biopsy are needed to identify the cause.
Table of Contents
- What a Nephrotic Syndrome Urine Panel Includes
- How Much Protein Is Nephrotic Range?
- Albumin and Dipstick Findings
- Casts, Fat, and Urine Microscopy
- What Causes the Nephrotic Pattern?
- Spot Ratio vs. 24-Hour Collection
- What Happens After the Urine Results?
What a Nephrotic Syndrome Urine Panel Includes
There is no single standardized laboratory order called a “nephrotic syndrome urine panel” everywhere. In practice, the urine evaluation combines tests that answer three questions: How much protein is being lost? Is the protein mainly albumin? What else is present in the urine sediment?
The core tests often include:
- quantitative total urine protein, usually UPCR or a 24-hour total;
- uACR or another urine albumin measurement in selected cases;
- routine dipstick urinalysis;
- urine microscopy for red and white blood cells, casts, tubular cells, crystals, and lipid-containing structures.
A urine protein-creatinine ratio is convenient because it estimates protein loss from one specimen. For very heavy proteinuria, clinicians may repeat the ratio or use a timed collection if a more direct daily amount is needed.
Urine testing alone does not establish nephrotic syndrome. The clinical diagnosis also depends on blood tests—especially serum albumin—and the physical examination. Edema is common, and blood lipids are often elevated. Kidney function may be normal, chronically reduced, or acutely worse depending on the cause and complications.
The distinction between “nephrotic-range proteinuria” and “nephrotic syndrome” is therefore important. A patient can have a very high urine protein value without all features of the syndrome, particularly early in the process or when serum albumin is relatively preserved.
How Much Protein Is Nephrotic Range?
In adults, the traditional threshold for nephrotic-range proteinuria is about 3.5 g of total protein per 24 hours or more. A spot UPCR around 3.5 g/g creatinine is often used as an approximate equivalent, although spot ratios and 24-hour excretion do not match perfectly in every patient.
| Finding | Typical interpretation | Important limitation |
|---|---|---|
| Low or trace protein | No major proteinuria detected | Dipsticks can miss non-albumin proteins |
| Protein above the laboratory reference range | Proteinuria | Amount and protein type determine significance |
| Several grams per day | Heavy proteinuria | May approach nephrotic range |
| About ≥3.5 g/24 h | Nephrotic-range proteinuria | Does not alone prove full nephrotic syndrome |
The exact relationship between a spot ratio and daily excretion depends partly on creatinine production. Low muscle mass can raise a protein-to-creatinine ratio for a given daily protein loss, while high creatinine excretion can lower it. A single value near a threshold should therefore be interpreted in context.
Pediatric definitions differ and often use first-morning protein-to-creatinine ratios indexed to body size and age-specific guidance. Children with suspected nephrotic syndrome should be evaluated using pediatric nephrology criteria rather than adult cutoffs.
The nephrotic-range proteinuria result is clinically important because very heavy urinary protein loss can drive hypoalbuminemia, edema, altered lipid metabolism, and other systemic complications.
Albumin and Dipstick Findings
In classic nephrotic syndrome, a large portion of urinary protein is albumin. Damage to the glomerular filtration barrier increases permeability to albumin and other plasma proteins, allowing grams of protein to leave the bloodstream each day.
A standard urine dipstick is sensitive to albumin, so nephrotic-range glomerular proteinuria often produces a strongly positive result such as 3+ or 4+. However, dipstick grading is semiquantitative and depends on urine concentration. A concentrated specimen can look more strongly positive than a dilute specimen with similar daily protein excretion.
That is why a positive dipstick should be followed by a quantitative measurement. A 24-hour urine protein test directly measures daily protein if the collection is complete, while UPCR provides a convenient estimate from one specimen.
uACR may also be very high, but total protein is often more useful for following established nephrotic syndrome because large amounts of non-albumin plasma proteins can accompany albumin. The albumin-to-total-protein relationship can still provide clues. If total protein is extremely high but albumin is a small fraction, clinicians consider non-albumin causes such as monoclonal light chains rather than assuming classic glomerular nephrotic proteinuria.
Urine albumin loss helps explain low serum albumin, but the relationship is not one-to-one. Liver albumin synthesis, inflammation, nutritional status, protein distribution, and the duration of protein loss also influence the blood level.
Casts, Fat, and Urine Microscopy
Urine microscopy can add useful pattern recognition. Heavy proteinuria can be accompanied by lipiduria, including free lipid droplets, oval fat bodies, and fatty casts.
Oval fat bodies are usually lipid-filled renal tubular epithelial cells or macrophages. Under polarized light, cholesterol-containing droplets can produce a characteristic “Maltese cross” appearance. Fatty casts form when lipid-containing material becomes incorporated into the protein matrix of a urinary cast. A fatty cast finding supports heavy glomerular protein loss but is not specific for one histologic disease.
Hyaline casts may also appear, but they are nonspecific and can occur in healthy people after exercise or dehydration. Waxy casts can reflect chronic kidney disease or low-flow states in dilated nephrons but do not define nephrotic syndrome.
Red blood cells and dysmorphic red cells can occur in some glomerular diseases that also produce nephrotic proteinuria. Red blood cell casts, however, point toward glomerular inflammation and a nephritic component rather than uncomplicated nephrotic syndrome. White blood cell casts can suggest interstitial inflammation or infection depending on context.
A broader urinalysis for kidney disease can therefore help distinguish a bland nephrotic sediment from an active inflammatory sediment. This distinction may influence how urgently serologic testing or kidney biopsy is pursued.
What Causes the Nephrotic Pattern?
Nephrotic syndrome results from diseases that make the glomerular filtration barrier abnormally permeable to plasma proteins. In adults, the differential diagnosis includes both primary glomerular diseases and systemic disorders.
Important primary causes include:
- membranous nephropathy;
- focal segmental glomerulosclerosis (FSGS);
- minimal change disease;
- selected forms of membranoproliferative or other glomerular disease.
Important secondary causes include:
- diabetes mellitus;
- systemic lupus erythematosus;
- amyloidosis;
- monoclonal gammopathies and plasma-cell disorders;
- infections such as hepatitis B, hepatitis C, or HIV in appropriate settings;
- certain medications;
- malignancy-associated glomerular disease in selected cases.
The urine pattern does not reliably tell these diseases apart. For example, membranous nephropathy, FSGS, and minimal change disease can all produce very heavy albumin-rich proteinuria with relatively bland sediment. The clinical history, serologic tests, age, comorbidities, and sometimes kidney biopsy are needed for diagnosis.
Diabetes is a common secondary cause, but a person with diabetes and sudden nephrotic syndrome may still need evaluation for another glomerular disorder. Rapid onset, active sediment, a fast fall in eGFR, or systemic symptoms can make “ordinary diabetic kidney disease” less likely as the sole explanation.
Spot Ratio vs. 24-Hour Collection
A spot UPCR is generally easier and less error-prone than a 24-hour collection, which is why spot ratios are widely used to diagnose and monitor heavy proteinuria. A first-morning specimen can reduce some variability.
A 24-hour collection may still be useful when:
- the spot ratio varies widely;
- creatinine excretion is unusual because of very low or high muscle mass;
- a precise daily protein amount is needed for a specific decision;
- urine electrophoresis or another timed analysis is also being performed;
- a clinician wants to verify a surprising result.
The main weakness of a 24-hour collection is completeness. Missing one void can make protein excretion look falsely low, while collecting for longer than the instructed period can raise the total. A result that does not fit the clinical picture should prompt review of the collection before major conclusions are drawn.
Spot ratios have their own limitations. They assume urine creatinine provides a reasonable denominator and can vary with timing, posture, activity, and muscle mass. Serial measurements are most useful when samples are collected under similar conditions.
For monitoring known nephrotic syndrome, the same method should ideally be used consistently so trends reflect disease change rather than switching between testing approaches.
What Happens After the Urine Results?
Once nephrotic-range proteinuria is confirmed, the next task is to determine whether full nephrotic syndrome is present, identify the cause, and assess complications.
Blood tests commonly include serum albumin, creatinine and eGFR, electrolytes, lipid profile, complete blood count, and targeted serologic studies. Depending on the clinical setting, clinicians may test for diabetes, autoimmune disease, hepatitis, HIV, monoclonal proteins, or antibodies associated with specific glomerular diseases.
Kidney biopsy is often needed in adults when the cause is not already clear from clinical and serologic findings. Biopsy can distinguish minimal change disease, FSGS, membranous nephropathy, amyloidosis, diabetic lesions, and other diagnoses that require different treatment.
The clinician also checks for complications. Severe edema can affect mobility and breathing. Nephrotic syndrome increases the risk of venous thromboembolism, especially in certain diseases and when serum albumin is very low. Infection risk can rise, and acute kidney injury can occur from the disease itself, low effective circulating volume, medications, or other stressors.
Treatment depends on the underlying diagnosis but may include sodium restriction, carefully selected diuretics for edema, blood pressure and proteinuria reduction, disease-specific immunosuppression, and therapies that reduce kidney risk. Anticoagulation decisions are individualized rather than automatically based on proteinuria alone.
Seek urgent medical assessment for new shortness of breath, chest pain, one-sided leg swelling, severe generalized edema, very low urine output, rapidly rising creatinine, or symptoms of serious infection. These can represent complications that require prompt treatment.
How Common Urine Patterns Change the Differential Diagnosis
The urine panel can narrow the differential diagnosis before a kidney biopsy is performed. Heavy albumin-predominant proteinuria with a bland sediment is common in several classic nephrotic diseases, including minimal change disease, membranous nephropathy, and some forms of focal segmental glomerulosclerosis. The urine does not distinguish these disorders reliably, but the pattern supports a glomerular permeability problem rather than a purely tubular process.
Heavy proteinuria plus hematuria, dysmorphic red blood cells, or red-cell casts suggests that the glomerular lesion also has an inflammatory or capillary-injury component. That can shift attention toward proliferative glomerulonephritis, lupus nephritis, infection-related disease, or another nephritic-nephrotic process. The distinction is clinically important because rapidly declining kidney function with an active sediment may require faster serologic testing, nephrology evaluation, and biopsy.
A third pattern is heavy total protein with an unexpectedly small albumin fraction. That mismatch raises the possibility of non-albumin proteins, including monoclonal free light chains. In an older adult, especially one with anemia, bone pain, hypercalcemia, or unexplained kidney dysfunction, clinicians may add serum free light chains, serum and urine immunofixation, and electrophoresis. This is not the typical pattern of uncomplicated nephrotic syndrome, but it can mimic heavy renal protein loss on a total-protein measurement.
Fatty casts and oval fat bodies support substantial lipiduria and are associated with nephrotic-range glomerular protein loss, yet they are not required for diagnosis. Their absence does not exclude nephrotic syndrome. Likewise, hyaline casts are nonspecific and can appear with dehydration or exercise. Microscopy is most useful when the sediment contains findings that materially change the diagnostic direction.
What the Urine Panel Cannot Establish
Urine testing can show that protein loss is severe and can characterize the sediment, but it cannot by itself establish the underlying histologic diagnosis. Two patients with similar protein excretion can have different glomerular diseases and require different treatment. Age, diabetes history, medications, infections, autoimmune features, malignancy risk, family history, and serologic markers all influence the next step.
The urine panel also cannot diagnose full nephrotic syndrome without blood and clinical data. Nephrotic-range proteinuria is a key component, but clinicians also look for hypoalbuminemia, edema, and metabolic consequences such as hyperlipidemia. A person can have nephrotic-range proteinuria before all of these features become prominent, and another person can have edema for reasons unrelated to kidney protein loss.
Finally, the amount of protein does not by itself determine urgency. A stable patient with longstanding heavy proteinuria and preserved kidney function has a different immediate risk profile from someone whose creatinine is rising quickly, urine output is falling, or sediment shows red-cell casts. Severe shortness of breath, suspected thrombosis, marked edema, infection, or acute kidney injury should prompt timely clinical assessment regardless of the exact protein value.
Why Serum Albumin Does Not Always Match Urine Protein Exactly
Severe urinary protein loss commonly lowers serum albumin, but the relationship is not one-to-one. Liver albumin production, inflammation, nutritional status, fluid balance, and the duration of protein loss all affect the blood level. A patient with abrupt heavy proteinuria may still have a near-normal serum albumin early in the course, while another patient with chronic disease or inflammation may have a low serum albumin that is not explained by urine losses alone.
This is why the urine panel and blood tests are interpreted together. Nephrotic-range proteinuria establishes the scale of renal protein loss, while serum albumin helps show the systemic consequence. Edema also depends on sodium retention, vascular permeability, heart and liver function, medications, and volume status, so its severity may not mirror the exact gram amount of urinary protein.
Monitoring After Treatment Starts
Follow-up usually tracks both proteinuria and kidney function. A sustained fall in UPCR or 24-hour protein can indicate response, but clinicians also monitor serum albumin, creatinine, eGFR, blood pressure, edema, weight, and treatment toxicity. The desired degree and speed of protein reduction depend on the underlying glomerular disease.
Using the same urine method over time improves comparability. Switching back and forth between a 24-hour collection and spot ratios can make trends harder to read because each method has different sources of variability. When a result changes unexpectedly, confirmation under similar collection conditions is often appropriate before labeling the disease as relapsed or resistant.
Persistent nephrotic-range proteinuria despite treatment may lead to re-evaluation of adherence, diagnosis, secondary causes, or biopsy findings. A rapidly rising creatinine, new active sediment, thrombosis, infection, or severe edema changes the urgency even if the protein measurement itself has not changed dramatically.
References
– Ten tips for the diagnosis and management of nephrotic syndrome 2026 (Review) – Executive summary of the KDIGO 2021 Guideline for the Management of Glomerular Diseases 2021 (Guideline) – Nephrotic syndrome: pathophysiology and consequences 2023 (Review) – Renal and Urinary Conditions: Nephrotic Syndrome 2024 (Review) – Methods for Diagnosing Proteinuria-When to Use Which Test and Why: A Review 2025 (Review)
Disclaimer
This article provides general information about urine testing for nephrotic syndrome and is not a diagnosis or treatment recommendation. Heavy proteinuria requires interpretation with serum albumin, kidney function, symptoms, and the suspected underlying disease. Prompt medical evaluation is important when severe swelling, breathing difficulty, possible blood clots, infection, or rapidly worsening kidney function is present.