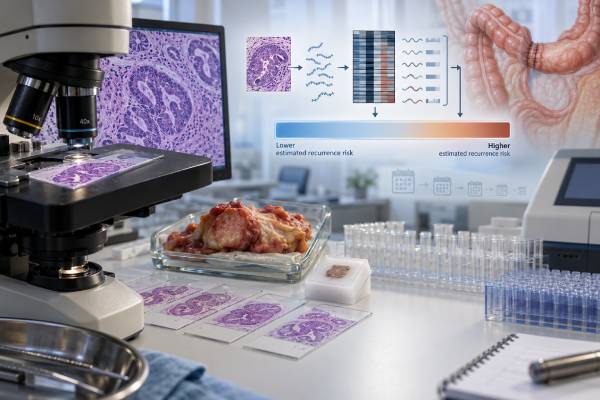
The Oncotype DX Colon Recurrence Score test is a 12-gene tumor assay designed to estimate the risk that certain resected colon cancers will recur after surgery. It analyzes gene expression in preserved tumor tissue and produces a Recurrence Score from 0 to 100. A higher score is associated with a higher recurrence risk, but the result is prognostic rather than a stand-alone predictor of chemotherapy benefit. That distinction is critical. The test does not diagnose colon cancer, determine whether margins are clear, replace TNM staging, or prove that chemotherapy will or will not work. Its most established use has been in selected stage II and some stage III colon cancers, particularly when the treatment decision is uncertain after standard clinical and pathology factors are reviewed. Mismatch repair status, T stage, number of lymph nodes examined, obstruction, perforation, lymphovascular or perineural invasion, tumor budding, age, health, and patient preferences remain important. The score is most useful as one additional piece of a shared adjuvant-treatment discussion.
- The Colon Recurrence Score ranges from 0 to 100; higher scores indicate higher estimated recurrence risk.
- The test is prognostic: it estimates recurrence risk but does not reliably identify a subgroup with a uniquely greater relative benefit from a specific chemotherapy regimen.
- Testing uses archived tumor tissue from surgery; no blood draw, fasting, or special preparation is usually required.
- The score should be interpreted with stage, T stage, mismatch repair status, lymph-node count, and other pathology risk factors.
- A low score does not mean zero recurrence risk, and a high score does not mean recurrence is certain.
Table of Contents
- What the Oncotype DX Colon Test Measures
- Who May Be Considered for Testing
- How the Recurrence Score Is Produced
- What Low, Intermediate, and High Scores Mean
- How the Score Relates to Chemotherapy Decisions
- How It Compares With Other Risk Information
- Limitations, Cost, and Questions to Ask
What the Oncotype DX Colon Test Measures
The Oncotype DX Colon Recurrence Score assay is a gene-expression test, not a DNA mutation panel. It measures the activity of a defined group of genes in the removed colon tumor using reverse-transcription polymerase chain reaction. The assay includes cancer-related genes involved in biological processes such as stromal response and cell-cycle signaling, together with reference genes used for normalization.
The laboratory combines the expression pattern through a prespecified algorithm to generate a Recurrence Score from 0 to 100. The score is continuous: recurrence risk generally rises as the score rises. Although reports and studies may group scores into categories for convenience, the number should not be viewed as a simple pass/fail threshold.
The test is performed on formalin-fixed, paraffin-embedded tumor tissue that was already removed during surgery. This means a patient generally does not undergo another biopsy. The pathology material is sent to the testing laboratory, which confirms that the specimen contains adequate invasive colon cancer and then performs the assay.
The purpose is to add biological information to conventional risk assessment. Two patients can both have stage II, T3, mismatch repair-proficient colon cancer with adequate lymph-node sampling yet have different gene-expression profiles and different estimated recurrence risks. The Recurrence Score aims to quantify some of that biological difference.
The test does not measure minimal residual disease. It does not look for circulating tumor DNA after surgery and is not repeated every few months to monitor recurrence. The tumor’s gene-expression score is generated once from the primary cancer. Surveillance still relies on the standard follow-up plan, which may include history, examination, CEA testing, imaging, and colonoscopy depending on stage and guidelines.
It also does not replace mismatch repair testing. MMR/MSI status carries independent prognostic and treatment information and should be known in resected colon cancer. Modern risk assessment integrates the genomic score with, rather than substitutes it for, established pathology.
Who May Be Considered for Testing
The assay has been clinically validated in selected stage II and stage III colon cancer populations. In practice, its greatest decision-making appeal has been for patients whose need for adjuvant chemotherapy is uncertain after surgery, especially stage II disease.
Stage II colon cancer has grown through the bowel wall to a defined extent but has no involved regional lymph nodes and no distant metastases. Many patients are cured by surgery alone. The challenge is identifying the minority with enough recurrence risk to justify chemotherapy despite its side effects.
ASCO guidance emphasizes standard high-risk features when deciding about stage II adjuvant therapy. These include T4 tumors, examination of fewer than 12 lymph nodes, lymphovascular or perineural invasion, obstruction, perforation, poor or undifferentiated histology in appropriate contexts, and high-grade tumor budding. MMR status is also important.
A genomic recurrence score may be most useful when these standard features leave genuine uncertainty. For example, a patient with a T3, MMR-proficient tumor, 20 negative lymph nodes, clear margins, and no obstruction or perforation may want more individualized information before deciding whether a modest potential chemotherapy benefit is worth the burden.
The test is not intended for every colon cancer patient. It is generally less useful when the clinical decision is already clear. A patient with very high-risk stage II disease may be advised to receive chemotherapy regardless of the score. A medically frail patient who cannot safely receive chemotherapy may gain little practical value from a test whose main purpose is to inform that decision.
For stage III disease, lymph nodes contain cancer and adjuvant chemotherapy is standard for most medically fit patients. A recurrence score can provide prognostic refinement, but it does not usually remove the fundamental stage III indication for adjuvant treatment.
The assay is for colon cancer, not a general interchangeable test for rectal cancer. Rectal cancer treatment often includes radiation and neoadjuvant strategies that change how recurrence risk is assessed. Although research has evaluated gene-expression scoring in rectal cancer, the clinical pathway is different.
How the Recurrence Score Is Produced
After surgery, a representative tumor block is selected from the pathology archive. The assay extracts RNA and measures expression of the 12-gene panel. A mathematical algorithm converts the gene-expression pattern into the Recurrence Score.
A patient does not need to prepare physically for the test. There is no fasting requirement and no special timing in relation to meals or medications. The practical steps are administrative and pathological: confirming that suitable tissue exists, arranging specimen transfer, and ensuring the oncologist has the result in time for the adjuvant-treatment decision.
Turnaround time can vary. Adjuvant chemotherapy decisions are usually made within weeks after colon surgery, so clinicians should order any genomic assay early enough that it does not unnecessarily delay treatment.
The score does not exist in a vacuum. Modern individualized risk estimates can combine the Recurrence Score with factors such as:
- stage II versus stage III;
- T3 versus T4 disease;
- mismatch repair status;
- number of lymph nodes examined; and
- whether chemotherapy is planned.
A 2022 patient-specific meta-analysis integrated the 12-gene score with clinical and pathology variables to provide more individualized recurrence estimates. This approach illustrates the correct philosophy: the genomic score refines baseline risk rather than replacing the variables that define baseline risk.
It is also important to separate analytical reproducibility from clinical utility. A laboratory can reliably produce the score, while clinicians still need to decide whether knowing the score will change management enough to justify ordering it. That decision depends on how uncertain the treatment choice was before testing.
What Low, Intermediate, and High Scores Mean
The Recurrence Score is continuous from 0 to 100. Lower values indicate lower estimated recurrence risk, while higher values indicate higher risk. Studies and reports have used score categories such as lower, intermediate, and higher risk, but the exact cut points and corresponding percentages depend on the patient population and clinical model.
A common mistake is to treat the number like a probability. A score of 25 does not mean there is exactly a 25% chance of recurrence. The score must be translated through validated risk models that also account for stage and other factors.
Another mistake is to assume that a low score means recurrence cannot happen. Even patients with favorable tumors have a nonzero risk because micrometastatic cancer can remain after surgery despite reassuring pathology. Conversely, a high score does not mean recurrence is inevitable. Many higher-risk patients remain cancer-free, especially when effective adjuvant therapy and surveillance are used.
Published validation studies have consistently shown that the score provides independent prognostic information. In other words, among patients who otherwise look similar by stage and pathology, the score can further separate lower- from higher-recurrence-risk groups.
The size of the absolute risk difference matters more than the category label. Suppose two patients have identical clinical factors but one has an estimated 5-year recurrence risk around 8% and the other around 18%. Even if both fall into broad labels such as “lower” and “higher,” the actual percentages are more useful for shared decision-making.
Patients should ask the oncologist to translate the score into an absolute recurrence-risk estimate that fits their stage, T stage, MMR status, and lymph-node evaluation. They can then compare that baseline risk with the expected absolute benefit and toxicity of chemotherapy.
How the Score Relates to Chemotherapy Decisions
The most important limitation of the Colon Recurrence Score is that it is primarily prognostic, not strongly predictive of relative chemotherapy benefit.
A predictive biomarker shows that one treatment works proportionally better in one biomarker-defined group than another. For example, RAS status predicts whether anti-EGFR antibodies are likely to benefit metastatic colorectal cancer. The Colon Recurrence Score does not have that same kind of validated interaction with fluoropyrimidine or oxaliplatin chemotherapy.
Earlier validation data showed that patients with higher scores have greater baseline recurrence risk, but the relative benefit of oxaliplatin was similar across the score range. This still creates an important practical effect: if chemotherapy produces a similar proportional risk reduction, a patient with higher baseline risk may receive a larger absolute benefit than a patient with very low baseline risk.
That difference between relative and absolute benefit is central. Imagine a treatment that reduces recurrence risk by 20% relative to baseline. Reducing a 20% baseline risk by one fifth yields a 4-percentage-point absolute reduction. Reducing a 5% baseline risk by one fifth yields only a 1-point reduction. The treatment works proportionally the same, but the high-risk patient has more to gain in absolute terms.
Real-world studies have found that receiving the 12-gene score can change treatment recommendations, often toward less chemotherapy for lower-risk results. A 2023 systematic review and meta-analysis reported that use of the assay influenced multidisciplinary treatment decisions in a meaningful minority of patients. A 2024 real-world analysis also supported the score’s prognostic value in stage II disease.
Still, the score should not override established high-risk pathology or MMR guidance. Stage II dMMR/MSI-H disease, for example, has a distinct evidence base regarding fluoropyrimidine-only adjuvant treatment. T4 disease carries substantial risk regardless of a reassuring genomic score.
For stage III cancer, chemotherapy remains the standard after complete resection for most medically fit patients. The score may refine prognosis but is not a validated tool for routinely withholding adjuvant treatment.
How It Compares With Other Risk Information
A recurrence score is only one layer of postoperative risk assessment.
TNM stage: This remains the foundation. T stage measures depth or extension of the primary tumor, while N stage measures regional lymph-node involvement. Stage is strongly associated with recurrence and survival.
Mismatch repair status: dMMR/MSI-H stage II tumors often have a favorable prognosis and different adjuvant-treatment implications compared with pMMR/MSS tumors. MMR status should be available independently of the recurrence score.
Lymph-node count: Examining at least 12 nodes is a common quality benchmark because inadequate nodal evaluation can lead to understaging and higher uncertainty.
High-risk pathology: T4 invasion, obstruction, perforation, lymphovascular invasion, perineural invasion, poor differentiation in relevant settings, and tumor budding can materially raise risk.
CEA: Carcinoembryonic antigen is a serum marker used mainly in postoperative surveillance and assessment of disease activity. It does not provide the same biological recurrence-risk information as a gene-expression assay.
ctDNA/MRD testing: Circulating tumor DNA assays look for evidence of molecular residual disease after surgery. A positive postoperative ctDNA result is a strong prognostic marker for recurrence. This is conceptually different from the Oncotype score, which is measured once in the removed tumor and estimates its biological recurrence potential.
The increasing availability of ctDNA has changed the conversation around postoperative biomarkers. ctDNA can provide dynamic information after surgery, while the 12-gene score provides static tumor biology. The evidence base, validation, access, and guideline recommendations differ, so the tests should not be assumed to be substitutes.
A useful framework is to ask four questions for any biomarker: What specimen is tested? What does the result measure? Is it prognostic or predictive? Will it change management? The Colon Recurrence Score answers: tumor tissue; gene expression; primarily prognostic; and potentially useful when the adjuvant decision is genuinely uncertain.
Limitations, Cost, and Questions to Ask
The assay has several practical and scientific limitations.
First, a recurrence score cannot account for every clinical factor. A patient’s age, frailty, neuropathy risk, kidney function, personal tolerance for risk, and competing health problems may matter more than a modest difference in recurrence estimate.
Second, the score does not directly identify residual cancer after surgery. A low score cannot confirm that all cancer cells are gone, and a high score cannot prove that microscopic disease remains.
Third, the assay’s strongest use case is narrower than the name may imply. It does not replace standard decisions in clearly high-risk stage II or routine stage III care. It should be ordered because the result could change a real decision, not simply because genomic testing sounds more precise.
Fourth, cost and insurance coverage vary. Patients can ask the testing company, oncology office, and insurer about prior authorization, estimated out-of-pocket cost, financial assistance, and whether the result is expected before the chemotherapy decision deadline.
Useful questions for the oncology visit include:
- Is my cancer stage II or stage III, and what is my T stage?
- Is the tumor MMR-proficient or MMR-deficient?
- How many lymph nodes were examined?
- Which high-risk pathology features are present?
- What decision would the Recurrence Score actually change?
- What is my estimated recurrence risk before and after the score is considered?
- Does the score predict chemotherapy benefit, or mainly recurrence risk?
- What absolute benefit might chemotherapy provide in my situation?
- What toxicities matter most for the proposed regimen?
- Would ctDNA testing provide different information, and is it appropriate in my case?
The best use of the test is not to produce a verdict but to make a gray-zone decision more quantitative. A score that is interpreted alongside stage, MMR, pathology, and patient preferences can make the adjuvant conversation clearer. A score interpreted alone can create false confidence.
References
- Treatments and clinical outcomes in stage II colon cancer patients with 12-gene Oncotype DX Colon Recurrence Score® assay-guided therapy: real-world data 2024 (Study)
- Impact of the 12-gene recurrence score in influencing adjuvant chemotherapy prescription in mismatch repair proficient stage II/III colonic carcinoma-a systematic review and meta-analysis. 2023 (Systematic Review)
- Patient-specific meta-analysis of 12-gene colon cancer recurrence score validation studies for recurrence risk assessment after surgery with or without 5FU and oxaliplatin 2022 (Meta-Analysis)
- Adjuvant Therapy for Stage II Colon Cancer: ASCO Guideline Update 2022 (Guideline)
- Oncotype DX Colon Recurrence Score® test 2026 (Official Test Information)
Disclaimer
This article is for general education and does not replace individualized oncology advice. A Colon Recurrence Score must be interpreted with stage, mismatch repair status, pathology risk features, overall health, and the expected benefits and risks of chemotherapy. Do not use a genomic score alone to start, stop, or refuse cancer treatment.