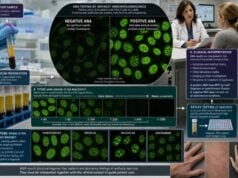
A thyroid antibody panel helps determine whether an overactive or underactive thyroid has an autoimmune cause. The main tests are thyroid peroxidase antibodies (TPOAb), thyroglobulin antibodies (TgAb), and thyrotropin receptor antibodies (TRAb), sometimes reported as thyroid-stimulating immunoglobulin (TSI). TPOAb and TgAb most often support Hashimoto thyroiditis, while TRAb or TSI supports Graves disease. These antibodies answer a different question from TSH, free T4, and T3: hormone tests show current thyroid function, while antibodies help identify the immune mechanism and selected future risks. A positive antibody result can occur while thyroid function is normal, and the antibody level alone usually does not determine whether treatment is needed. The panel is not standardized, and not everyone needs all three tests. TRAb has special uses in pregnancy, after previous Graves treatment, and when distinguishing Graves hyperthyroidism from thyroiditis or toxic nodules. TgAb also matters because it can interfere with thyroglobulin monitoring after differentiated thyroid cancer.
- TPOAb and TgAb support autoimmune thyroiditis: they do not measure how underactive the thyroid is.
- TRAb or TSI supports Graves disease: stimulating, blocking, and neutral receptor antibodies can have different effects.
- TSH and free T4 guide current treatment: antibody titers usually do not set the thyroid-hormone dose.
- Positive antibodies can occur with normal thyroid function: monitoring may be needed without immediate medication.
- Pregnancy changes the significance of TRAb: receptor antibodies can cross the placenta even after thyroid surgery or radioactive iodine.
- Repeated antibody testing is often unnecessary: the reason for ordering determines whether a repeat adds value.
Table of Contents
- What the Thyroid Antibody Panel Measures
- TPOAb and TgAb in Hashimoto Thyroiditis
- TRAb and TSI in Graves Disease
- Positive, Negative, and Mixed Result Patterns
- How Antibodies Fit With TSH, T4, T3, and Imaging
- Pregnancy, Fetal Risk, and Postpartum Thyroiditis
- Monitoring, Treatment Decisions, and Thyroid Cancer Follow-Up
- Preparation, Follow-Up, and Urgent Symptoms
What the Thyroid Antibody Panel Measures
The thyroid gland uses iodine and several proteins to make thyroxine (T4) and triiodothyronine (T3). Autoimmune thyroid disease develops when the immune system targets proteins involved in this process or the receptor that controls thyroid stimulation.
A panel may contain:
- Thyroid peroxidase antibody (TPOAb): targets thyroid peroxidase, an enzyme needed for thyroid-hormone synthesis.
- Thyroglobulin antibody (TgAb): targets thyroglobulin, the protein scaffold used to store and produce thyroid hormone.
- TSH receptor antibody (TRAb or TSHRAb): binds the receptor normally activated by thyroid-stimulating hormone.
- Thyroid-stimulating immunoglobulin (TSI): a functional or assay-specific measurement focused on receptor-stimulating activity.
Laboratories use different names and methods. A TRAb binding assay detects antibodies that bind the receptor but may not directly distinguish whether they stimulate or block it. A TSI or bioassay is designed to identify stimulating activity. Modern assays are highly useful for Graves disease, but the reference range and units are platform-specific.
The term “thyroid antibody panel” is not standardized. Some panels include only TPOAb and TgAb. Others add TRAb or TSI. A negative two-antibody autoimmune-thyroid panel therefore cannot be interpreted as a negative Graves evaluation if no receptor antibody was measured.
Thyroid antibodies are etiologic and risk markers, not thyroid hormones. They cannot tell whether a person is currently hypothyroid, hyperthyroid, or euthyroid. That requires TSH and free T4, with T3 added in selected hyperthyroid presentations.
No population-wide antibody screening is recommended simply to look for future thyroid disease. Testing is most useful when thyroid function is abnormal, symptoms or examination suggest autoimmune thyroid disease, pregnancy creates a specific risk question, or thyroglobulin monitoring requires assessment of interference.
Positive thyroid antibodies are common enough that clinical context matters. A person may have antibodies for years without abnormal TSH, while another develops progressive gland failure. Family history, other autoimmune disease, pregnancy, iodine exposure, medications, and baseline TSH influence the course.
Antibody reference intervals are not interchangeable. One assay may report IU/mL, another an index, and a TSI assay may express a percentage or specimen-to-reference ratio. The word “high” should therefore mean above that laboratory’s cutoff, not above a value copied from another report. Trends are interpretable only when the same analyte and method are used.
TPOAb and TgAb in Hashimoto Thyroiditis
Hashimoto thyroiditis is chronic autoimmune inflammation of the thyroid. It is a common cause of hypothyroidism. TPOAb is the most sensitive commonly used antibody marker, and TgAb provides additional support in some patients.
A typical Hashimoto pattern is elevated TSH, low or low-normal free T4 depending on disease stage, and positive TPOAb with or without TgAb. The gland may be enlarged and firm early, normal-sized later, or atrophic after longstanding destruction. Ultrasound can show diffuse heterogeneity and reduced echogenicity, but imaging is not required solely to confirm antibodies when the biochemical and clinical picture is clear.
Positive TPOAb can also occur in Graves disease, postpartum thyroiditis, painless thyroiditis, type 1 diabetes, celiac disease, other autoimmune conditions, and healthy individuals. TgAb has similar overlap and is generally less sensitive than TPOAb for classic Hashimoto thyroiditis. Neither result is perfectly disease-specific.
High antibody levels
A result far above the laboratory cutoff supports thyroid autoimmunity more strongly than a borderline result, but the exact height does not translate into a predictable amount of thyroid damage. Two people with similar TPOAb values can have very different TSH, symptoms, gland size, and progression.
Antibody concentrations can fluctuate substantially and may remain elevated after thyroid function stabilizes. Lowering TPOAb is not an established treatment target. Levothyroxine is adjusted to TSH and free T4 goals, symptoms, age, pregnancy status, cardiac risk, and clinical circumstances—not to the antibody number.
Normal thyroid function with positive TPOAb or TgAb
A person with normal TSH and free T4 is euthyroid even if TPOAb or TgAb is positive. Medication is not automatically indicated. The result signals a greater future risk of hypothyroidism, so periodic TSH monitoring may be appropriate. The interval depends on baseline TSH, symptoms, age, pregnancy plans, and other risk factors.
Symptoms commonly attributed to hypothyroidism—fatigue, weight change, dry skin, constipation, low mood, or hair loss—are nonspecific. When TSH and free T4 are normal, the antibody does not prove that the thyroid is causing every symptom. Sleep disorders, anemia, medication effects, depression, nutritional problems, and other conditions may need evaluation.
Negative TPOAb and TgAb
Negative antibodies reduce the likelihood of autoimmune thyroiditis but do not completely exclude it. Some patients have seronegative chronic autoimmune thyroiditis based on thyroid function, ultrasound, pathology, and exclusion of other causes. Hypothyroidism can also result from thyroid surgery, radioactive iodine, medications, congenital disease, pituitary disorders, severe iodine imbalance, or nonautoimmune thyroiditis.
TRAb and TSI in Graves Disease
Graves disease occurs when stimulating antibodies activate the TSH receptor, causing diffuse thyroid-hormone overproduction. The usual biochemical pattern is suppressed TSH with elevated free T4 and/or T3. Clinical clues include diffuse goiter, thyroid bruit, tremor, heat intolerance, weight loss, rapid pulse, and thyroid eye disease.
TRAb testing is especially useful when:
- The cause of hyperthyroidism is uncertain
- Radioactive iodine uptake scanning is unavailable, contraindicated, or undesirable
- Pregnancy prevents a radioactive iodine uptake test
- Thyroiditis, toxic nodules, and Graves disease are being distinguished
- A person has thyroid eye disease with mild or atypical hormone abnormalities
- Relapse risk is being assessed near the end of antithyroid-drug therapy
- Pregnancy follow-up is needed in current or previous Graves disease
A positive TRAb in a patient with biochemical hyperthyroidism strongly supports Graves disease. A negative modern assay lowers the probability but does not make Graves impossible. Very mild disease, treatment, assay differences, or an uncommon antibody profile can produce a negative result.
Stimulating and blocking receptor antibodies
TSH receptor antibodies are biologically diverse. Stimulating antibodies increase hormone production and cause Graves hyperthyroidism. Blocking antibodies inhibit receptor signaling and can contribute to hypothyroidism. Neutral antibodies bind without clearly stimulating or blocking in routine interpretation.
The balance can change over time or after treatment. Rarely, a patient transitions between hyperthyroid and hypothyroid states because the dominant receptor-antibody activity changes. A routine binding TRAb result may not reveal this functional balance, so hormone results remain essential.
TRAb after treatment
Antithyroid drugs reduce hormone synthesis and can be followed by a decline in TRAb. Persistently elevated TRAb near treatment withdrawal is associated with a higher relapse risk, but it does not guarantee relapse. A low or negative result improves the probability of remission but does not guarantee it.
Radioactive iodine or thyroid surgery controls the thyroid source but does not immediately erase the immune response. TRAb can remain elevated, and levels may rise temporarily after radioactive iodine. This matters particularly for thyroid eye disease and pregnancy. A person who no longer has a functioning thyroid can still have circulating receptor antibodies.
Positive, Negative, and Mixed Result Patterns
The panel should be interpreted as a pattern alongside thyroid function.
| Laboratory pattern | Common interpretation | Important next question |
|---|---|---|
| High TSH, low free T4, TPOAb positive | Overt hypothyroidism likely caused by Hashimoto thyroiditis | Symptoms, pregnancy, severity, medication and replacement plan |
| High TSH, normal free T4, TPOAb positive | Subclinical autoimmune hypothyroidism | TSH level, persistence, age, symptoms, pregnancy and cardiac risk |
| Normal TSH and free T4, TPOAb or TgAb positive | Euthyroid thyroid autoimmunity | Appropriate interval for future TSH monitoring |
| Suppressed TSH, high free T4 or T3, TRAb positive | Graves hyperthyroidism strongly supported | Severity, eye disease, pregnancy, treatment choice |
| Suppressed TSH, high hormones, TRAb negative | Graves remains possible, but thyroiditis, toxic nodule, toxic multinodular goiter, iodine or medication causes need review | Imaging, uptake testing when safe, ultrasound blood flow, medication and iodine history |
| TPOAb/TgAb and TRAb positive | Overlapping thyroid autoimmunity is possible | Current hormone state and receptor-antibody effect determine management |
Mixed antibodies are not contradictory. Many people with Graves disease also have TPOAb or TgAb. Some later become hypothyroid because of treatment, destructive autoimmunity, or blocking antibodies. The diagnostic label should follow current physiology and the overall course.
A borderline antibody may be real but has lower positive predictive value than a clearly elevated result. Repeating or confirming it can be reasonable when the result conflicts with TSH, hormones, examination, and imaging. Comparing exact numbers across assay manufacturers is not reliable.
Positive antibodies do not explain every thyroid nodule. Most nodules are not caused by Hashimoto or Graves disease, and cancer risk is assessed through ultrasound features, size, growth, lymph nodes, and cytology when indicated. Antibody positivity neither proves nor excludes thyroid cancer.
How Antibodies Fit With TSH, T4, T3, and Imaging
TSH is usually the first test for thyroid function. The pituitary raises TSH when circulating thyroid hormone is insufficient and suppresses it when hormone is excessive. Free T4 helps classify the severity and direction of dysfunction. T3 is especially useful when hyperthyroidism is suspected and T4 is normal or when T3-predominant Graves disease is possible.
Antibodies answer the cause question:
- Abnormal TSH identifies possible dysfunction.
- Free T4 and sometimes T3 define the biochemical state.
- TPOAb/TgAb or TRAb helps identify autoimmune etiology.
- Imaging is added only when it will distinguish causes or evaluate anatomy.
Ultrasound evaluates size, texture, blood flow, nodules, and lymph nodes. Hashimoto thyroiditis often appears heterogeneous and hypoechoic. Graves disease may show diffuse enlargement and increased vascularity. These findings are supportive but not perfectly specific.
A radioactive iodine uptake scan shows how actively and uniformly the gland takes up iodine. Diffuse high uptake supports Graves disease; focal uptake supports a toxic nodule; low uptake supports destructive thyroiditis, iodine exposure, or exogenous hormone. It is not performed during pregnancy or breastfeeding and may be unnecessary when TRAb and the clinical picture are definitive.
Medication and exposure history is important. Amiodarone, lithium, immune checkpoint inhibitors, interferon, excess iodine, thyroid hormone supplements, and some weight-loss or “thyroid support” products can alter function. Biotin can interfere with several thyroid immunoassays, often creating a falsely hyperthyroid pattern. The needed pause depends on dose and platform, so the laboratory or clinician should give specific instructions rather than relying on a universal interval.
Nonthyroidal illness and pituitary disease can create abnormal TSH or free T4 patterns that do not fit primary autoimmune thyroid disease. Antibodies may be incidental in these situations. When results are internally inconsistent, repeating tests after acute illness or using an alternate assay may clarify interference.
Pregnancy, Fetal Risk, and Postpartum Thyroiditis
Pregnancy changes thyroid-hormone requirements and the importance of selected antibodies. Maternal TPOAb or TgAb does not directly diagnose fetal thyroid disease. It identifies maternal autoimmunity and a greater risk of developing hypothyroidism during pregnancy or postpartum, so TSH monitoring may be intensified.
Treatment decisions for subclinical hypothyroidism in pregnancy depend on TSH, trimester-specific reference ranges, TPOAb status, prior pregnancy history, fertility treatment, symptoms, and current guideline recommendations. Antibody positivity alone is not a reason to self-start thyroid hormone.
TRAb has a different role because it crosses the placenta and can stimulate or block the fetal thyroid. Testing is considered in pregnant people with:
- Active Graves disease
- A history of Graves disease treated with radioactive iodine or thyroidectomy
- Previous infant or fetus affected by thyroid dysfunction
- Current antithyroid-drug treatment
- Prior elevated TRAb with a new pregnancy
A history of definitive Graves treatment remains relevant because antibodies may persist even when the mother is hypothyroid on levothyroxine. Significantly elevated TRAb can prompt repeat testing and maternal-fetal surveillance for fetal heart-rate change, growth problems, goiter, hydrops, or bone-maturation abnormalities. The exact schedule and thresholds should follow current obstetric and endocrine guidance.
Postpartum thyroiditis is a destructive autoimmune thyroiditis that can cause a temporary hyperthyroid phase, a hypothyroid phase, either phase alone, or permanent hypothyroidism. TPOAb and TgAb are often positive. TRAb helps distinguish postpartum Graves disease when hyperthyroidism is persistent or the clinical picture is unclear.
Destructive postpartum thyroiditis releases stored hormone; antithyroid drugs do not stop that release. Graves disease produces new hormone through receptor stimulation and may require antithyroid therapy. TSH, free T4, T3 pattern, TRAb, examination, ultrasound blood flow, timing, and breastfeeding constraints guide the distinction.
Neonatal thyroid dysfunction can occur from maternal receptor antibodies and may appear after birth as maternal medication clears. Coordination among endocrinology, maternal-fetal medicine, and pediatrics is important when TRAb is substantially elevated or fetal signs develop.
Monitoring, Treatment Decisions, and Thyroid Cancer Follow-Up
For Hashimoto hypothyroidism, levothyroxine replaces missing hormone. The dose is monitored with TSH and, in selected situations, free T4. TPOAb and TgAb are generally measured once to establish etiology; serial titers rarely change management.
Euthyroid people with positive TPOAb or TgAb may need periodic TSH, but the frequency is individualized. Testing sooner is appropriate when symptoms change, pregnancy begins, a medication affecting the thyroid is started, or the baseline TSH is near the upper limit.
Graves treatment may include antithyroid medication, radioactive iodine, or surgery. TRAb can help confirm diagnosis and estimate remission or relapse probability after a course of antithyroid drugs. It does not replace monitoring TSH, free T4, and T3, particularly early in treatment when TSH can remain suppressed after hormones improve.
Thyroid eye disease activity does not perfectly track thyroid-hormone levels or TRAb. Eye pain, redness, swelling, double vision, color desaturation, or visual loss requires direct ophthalmic assessment. Smoking strongly worsens thyroid eye disease risk and response, making cessation a high-priority intervention.
TgAb and thyroid cancer monitoring
After treatment for differentiated thyroid cancer, serum thyroglobulin can serve as a tumor marker because normal or malignant thyroid cells produce it. TgAb can interfere with thyroglobulin immunoassays, causing falsely low or otherwise misleading results. Laboratories therefore measure TgAb with thyroglobulin and interpret both trends together.
In this setting, TgAb is not simply evidence of Hashimoto thyroiditis. A changing TgAb trend can affect how clinicians interpret cancer surveillance, but it is not a stand-alone tumor marker. Ultrasound, imaging, pathology, treatment history, assay consistency, and thyroglobulin methodology all matter.
Repeated TPOAb has little role in thyroid cancer follow-up. TRAb is not a thyroid cancer marker. A thyroid antibody panel should not be marketed or interpreted as a cancer screen.
Dietary or supplement claims that promise to “erase” antibodies should be approached cautiously. Excess iodine can worsen autoimmune thyroid dysfunction, and unregulated products may contain thyroid hormone. Selenium has been studied for antibody changes in selected populations, but lowering an antibody without proven improvement in clinical outcomes is not equivalent to treating disease.
Preparation, Follow-Up, and Urgent Symptoms
The panel requires a standard blood draw. Fasting is usually unnecessary. Bring a list of thyroid medication, antithyroid drugs, amiodarone, lithium, supplements, recent iodine contrast, pregnancy status, and prior thyroid surgery or radioactive iodine. Take prescribed medication as directed unless the clinician provides test-specific instructions.
The time of levothyroxine dosing can affect free T4 more than antibodies. When several thyroid tests are drawn together, following the same dosing routine from one measurement to the next improves comparability. Do not stop levothyroxine or antithyroid medication to change an antibody result.
Follow-up depends on the pattern:
- Positive TPOAb/TgAb with normal function: periodic TSH, with earlier testing for pregnancy or new symptoms
- High TSH or low free T4: evaluate and treat hypothyroidism according to severity and context
- Suppressed TSH with positive TRAb: assess Graves severity, heart rhythm, eye disease, and treatment options
- Discordant antibodies and hormones: repeat or confirm assays and review medication, iodine, illness, and pituitary causes
- TgAb during thyroid cancer surveillance: use the same laboratory when possible and interpret with thyroglobulin and imaging
Seek urgent care for severe palpitations with chest pain, fainting, marked shortness of breath, high fever with agitation or confusion, profound weakness, or persistent vomiting in uncontrolled hyperthyroidism. These can signal severe thyrotoxicosis or another emergency. Severe drowsiness, hypothermia, slow breathing, confusion, or cardiovascular instability in profound hypothyroidism also requires emergency treatment.
New visual loss, color-vision change, inability to close the eyelids, or severe eye pain in Graves disease needs urgent ophthalmic assessment. During pregnancy, major palpitations, uncontrolled vomiting, reduced fetal movement, or concerns raised by fetal monitoring should be evaluated promptly.
The practical interpretation is simple in principle: use antibodies to identify autoimmune cause and selected risks, but use TSH, free T4, T3, symptoms, examination, pregnancy context, and organ-specific testing to make treatment decisions.
References
- Thyroid antibody tests 2023 (Official Patient Guidance)
- Hashimoto Thyroiditis 2025 (Clinical Review)
- 2022 Update on Clinical Management of Graves’ Disease and Thyroid Eye Disease 2022 (Clinical Review)
- Best practices in the laboratory diagnosis, prognostication, prediction, and monitoring of Graves’ disease: role of anti-TSH receptor antibodies 2024 (Review)
- Thyroiditis: Evaluation and Treatment 2021 (Clinical Review)
- Thyroid Antibodies: What They Are, Types, Levels & Tests 2025 (Official Clinical Guidance)
Disclaimer
Thyroid antibody results must be interpreted with TSH, free T4, T3 when indicated, symptoms, medications, pregnancy status, examination, and imaging. A positive antibody does not automatically require treatment, and a negative panel does not exclude every autoimmune thyroid disorder. Severe palpitations, chest pain, confusion, breathing difficulty, profound weakness, or new visual loss requires urgent medical care.