A flow cytometry immune panel identifies and counts immune-cell populations by detecting markers on or inside individual cells. A basic lymphocyte panel usually reports total T cells, CD4 helper T cells, CD8 cytotoxic T cells, B cells, natural killer cells, percentages, absolute counts, and sometimes the CD4/CD8 ratio. Expanded panels can examine naïve and memory T cells, switched memory B cells, activation markers, regulatory cells, protein expression, and immune-cell function. The test can reveal a pattern that supports immune deficiency, treatment-related depletion, infection-associated changes, or abnormal immune recovery, but it rarely supplies a complete diagnosis alone. Results depend strongly on age, current illness, medications, the complete blood count, specimen quality, laboratory markers, and local reference intervals. A normal major-subset panel also cannot exclude every inborn error of immunity because cells may be present but function abnormally. The most useful interpretation connects the cell pattern to the person’s infections, immune symptoms, treatment history, immunoglobulins, functional tests, and genetics.
- Flow cytometry classifies thousands of cells by their marker combinations.
- Absolute counts and percentages answer different questions and should be reviewed together.
- Pediatric reference intervals differ greatly from adult intervals.
- Normal cell numbers do not prove normal antibody or cellular function.
- Recent infection, steroids, chemotherapy, and biologic drugs can reshape the panel.
Table of Contents
- How flow cytometry identifies immune cells
- What a basic immune panel reports
- Why clinicians order the test
- What common T-, B-, and NK-cell patterns can mean
- What expanded flow cytometry can add
- How to interpret counts, percentages, and reference ranges
- Specimen and laboratory factors that affect accuracy
- What usually follows an abnormal or normal panel
How flow cytometry identifies immune cells
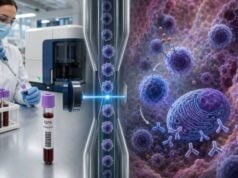
Flow cytometry analyzes cells one at a time while they move in a narrow stream through a laser. The laboratory adds antibodies linked to fluorescent dyes. Each antibody recognizes a particular cellular marker, often called a CD antigen. When laser light strikes the dyes, detectors record the pattern and intensity of fluorescence. Software then places cells into groups based on their size, internal complexity, and marker combinations.
The method is more precise than identifying lymphocytes by appearance under a microscope. A T cell, B cell, and natural killer cell can look similar morphologically, yet display different surface proteins. A typical strategy identifies leukocytes with CD45, separates lymphocytes by light-scatter properties, and then applies lineage markers. CD3 identifies mature T cells. CD4 and CD8 divide major T-cell subsets. CD19 or CD20 identifies most B cells. Natural killer cells are commonly CD3-negative and express CD16 and/or CD56.
No single marker always defines a clinically meaningful population. Laboratories use combinations and a process called gating. For example, CD4 appears on helper T cells but also on some monocytes. Counting CD4 only within a carefully selected CD3-positive lymphocyte gate avoids including the wrong cells. Likewise, CD56 can appear on activated T cells, so NK-cell identification normally includes absence of CD3.
A flow panel may use a dual-platform or single-platform counting approach. In a dual-platform method, percentages from flow cytometry are combined with lymphocyte counts from a separate hematology analyzer. In a single-platform method, counting beads or volumetric measurement allows the cytometer to calculate absolute counts directly. Each can perform well when validated, but methods should not be mixed casually when monitoring small changes over time.
Flow cytometry can measure more than presence or absence. Fluorescence intensity can show reduced protein expression, and multiple colors can divide broad lineages into developmental or functional subsets. Intracellular staining can detect proteins such as perforin, signaling molecules, or transcription factors after cells are fixed and permeabilized. Stimulation assays can measure phosphorylation, degranulation, oxidative burst, or cytokine production.
The result is an immunophenotype: a structured description of which immune cells are present and what markers they express. It is not the same as a genetic diagnosis, and it is not a picture of all immune cells in tissues. Most routine panels sample circulating cells in peripheral blood.
What a basic immune panel reports
A basic panel is often called a T-, B-, and NK-cell panel, lymphocyte subset panel, or immunodeficiency panel. The report usually contains both the percentage of lymphocytes and the absolute number of cells per microliter.
CD3-positive T cells represent the major circulating T-cell population. The total may be divided into CD4-positive helper T cells and CD8-positive cytotoxic T cells. Some T cells do not fit either major group, and a small population may express both markers. Therefore, CD4 plus CD8 does not always equal the total CD3 count exactly.
CD4 T cells coordinate immune responses, support B cells and macrophages, and are central to HIV monitoring. A CD4 count can be low because of HIV, other infections, medications, inherited conditions, severe illness, or temporary redistribution. A percentage helps when the absolute lymphocyte count is changing.
CD8 T cells participate in killing infected or abnormal cells and can expand during viral responses. A high or low CD8 count is not by itself a test of cytotoxic function.
The CD4/CD8 ratio summarizes the balance between these subsets. It can fall because CD4 cells are low, CD8 cells are high, or both. It can rise because CD4 cells are high, CD8 cells are low, or both. The component counts must always be checked before interpreting the CD4/CD8 ratio.
CD19-positive or CD20-positive B cells are cells capable of developing into antibody-producing plasma cells and memory populations. A basic B-cell count says how many circulating B cells are present, not how much useful antibody they make. CD20 can be absent after anti-CD20 therapy even when small numbers of early or plasma-lineage cells remain, while CD19 may provide a different view. A B-cell count must be paired with immunoglobulins and vaccine responses when humoral immunity is the concern.
Natural killer cells are commonly reported as CD3-negative, CD16-positive and/or CD56-positive lymphocytes. They contribute to early antiviral and antitumor defense. Enumeration does not establish that they can degranulate or kill target cells normally. A separate NK-cell function test may be required.
Some reports include total lymphocytes, white blood cells, or an absolute lymphocyte count imported from the complete blood count. Others show only flow-derived values. The clinician should check whether counts were calculated from the same blood draw because combining results from different dates can create inaccurate absolute numbers.
Why clinicians order the test
The panel is commonly used when symptoms or routine laboratory findings raise concern about immune-cell quantity. Recurrent, severe, persistent, or unusual infections can prompt testing, especially when accompanied by poor growth, chronic diarrhea, thrush, deep abscesses, difficult-to-treat viral disease, or a family history of immune deficiency.
In infants, a very low absolute lymphocyte count or an abnormal newborn screen for severe combined immunodeficiency requires rapid lymphocyte phenotyping. T-, B-, and NK-cell patterns help narrow the type of severe combined immunodeficiency and guide immediate precautions while functional and genetic testing proceeds. A normal total lymphocyte count does not fully exclude severe immune disease because the remaining cells may be abnormal or maternal cells may be present.
In older children and adults, testing may investigate inborn errors of immunity that present later with infection, autoimmunity, enlarged lymph nodes, splenomegaly, inflammatory bowel disease, lung damage, unusual viral susceptibility, or malignancy. Modern immune disorders are not limited to “weak immunity”; many cause both deficiency and excessive immune activation.
The panel is also used to monitor acquired immune deficiency. HIV care uses CD4 counts in specific clinical situations alongside viral load and treatment status. Chemotherapy, radiation, stem-cell transplantation, solid-organ transplantation, severe infection, malnutrition, and protein-losing conditions can reduce lymphocyte populations.
Targeted treatments create recognizable patterns. Anti-CD20 therapy can deplete B cells for months. Some multiple-sclerosis, leukemia, lymphoma, rheumatology, and transplant drugs affect T cells, B cells, or both. Clinicians may measure immune reconstitution before vaccination, retreatment, infection prophylaxis decisions, or immunoglobulin replacement review. The test should be timed according to the drug’s expected effect rather than ordered at arbitrary intervals.
A panel may be ordered when a complete blood count shows lymphopenia or an unusual lymphocyte population. It can also help distinguish reactive lymphocytes from a possible leukemia or lymphoma, but a routine immune-deficiency panel is not the same as a comprehensive leukemia/lymphoma immunophenotyping study. Suspected malignancy may require a larger marker set, morphology, bone marrow or tissue biopsy, cytogenetics, and molecular testing.
Finally, flow cytometry can monitor immune recovery after hematopoietic stem-cell transplantation, gene therapy, or treatment of an immune disorder. Recovery of cell numbers does not always equal recovery of diversity and function. Naïve T-cell output, memory B-cell development, immunoglobulin production, and vaccine response may recover on different schedules.
What common T-, B-, and NK-cell patterns can mean
Pattern recognition is more useful than reading each cell count in isolation. A specialist first asks which lineages are reduced, preserved, or expanded, then checks whether the pattern is expected for age, illness, and treatment.
A T-low, B-positive, NK-positive pattern can occur in some forms of severe combined immunodeficiency caused by defective cytokine signaling, T-cell receptor development, or other pathways. A T-low, B-positive, NK-low pattern suggests a different group of molecular defects. A T-low, B-low, NK-positive pattern can point toward problems in early lymphocyte development, while a T-low, B-low, NK-low pattern may indicate a broader developmental defect. These shorthand categories guide urgent evaluation but are not diagnoses by themselves.
A low T-cell count with reduced naïve T cells may indicate impaired thymic production, severe combined immunodeficiency, thymic developmental disorders, post-transplant delay, or treatment effect. In adults, aging naturally lowers naïve T-cell proportions, so age-specific interpretation is essential. Recent viral illness and corticosteroids can transiently change distribution.
An isolated or dominant CD4 reduction may occur with HIV, idiopathic CD4 lymphocytopenia, medications, malignancy, infection, or systemic illness. Confirmation requires repeat testing and evaluation of causes. A low CD4 percentage with a normal absolute count, or the reverse, should be interpreted with the total lymphocyte count and clinical setting.
A CD8 expansion commonly accompanies viral infection and immune activation. Persistent marked expansions may be reactive, treatment-related, or clonal. Flow cytometry can identify unusual marker loss or a skewed population, but clonality testing and hematopathology review may be needed.
A B-low or B-absent pattern can follow anti-CD20 treatment or occur in disorders such as X-linked agammaglobulinemia. B cells may be present in common variable immunodeficiency, where the major problem is differentiation into effective memory and antibody-producing cells. Thus, a normal total B-cell count does not exclude serious antibody deficiency.
A low NK-cell count can occur in combined immune disorders, after treatment, or transiently during illness. An isolated low result should be repeated when clinically appropriate because NK percentages fluctuate as other lymphocyte populations change. Conversely, a normal NK count does not rule out defective cytotoxicity.
High percentages can be misleading. If one lineage is depleted, the remaining lineages occupy a larger percentage even when their absolute counts are normal or low. For example, a high B-cell percentage after profound T-cell loss does not necessarily mean B-cell expansion. Absolute counts reveal the actual number of cells in circulation.
Patterns also change during recovery. After B-cell depletion, early transitional B cells may return before mature memory B cells. After transplantation, NK cells often recover before T-cell diversity. A single snapshot may therefore be less informative than a well-timed series using the same laboratory.
What expanded flow cytometry can add
When the basic panel is normal or only partly explanatory, expanded immunophenotyping can test a more specific hypothesis.
Naïve and memory T-cell analysis commonly uses CD45RA, CD45RO, CCR7, CD27, or related markers. It helps estimate whether the T-cell pool includes recent or less-differentiated cells rather than mostly memory cells. In infants with suspected severe combined immunodeficiency, naïve CD4 and CD8 populations can be especially important. Recent thymic emigrant markers may add evidence of thymic output.
T-cell receptor subsets can identify alpha-beta and gamma-delta T cells or abnormal double-negative alpha-beta T cells. Expansion of particular populations can support selected immune-dysregulation syndromes, but the pattern requires specialized interpretation.
B-cell subset analysis divides transitional, naïve, nonswitched memory, class-switched memory, plasmablast, and atypical populations. Reduced switched memory B cells can support classification of common variable immunodeficiency and related disorders. The result should be interpreted with IgG, IgA, IgM, vaccine responses, age, infection, and immunosuppressive therapy.
Protein-expression assays can rapidly show absence or reduction of a protein associated with a genetic disorder. Examples include BTK in X-linked agammaglobulinemia, WAS protein, DOCK8, XIAP, SAP, CTLA-4, LRBA, and major histocompatibility complex proteins. Normal expression may not exclude a protein that is present but nonfunctional, and abnormal expression usually needs genetic or functional confirmation.
Activation and signaling assays measure events after cells are stimulated. Phosphorylated STAT proteins can assess cytokine signaling. CD107a mobilization measures degranulation by NK cells and cytotoxic T cells. Intracellular perforin and granzyme staining evaluates cytotoxic machinery. These tests require fresh, viable cells and carefully controlled conditions.
Regulatory T-cell panels use CD4, CD25, CD127, and intracellular FOXP3, among other markers. They can support evaluation of immune-dysregulation disorders, but activated conventional T cells can mimic parts of the phenotype. A regulatory T-cell test is not a general test for autoimmune disease severity.
Flow cytometry also measures granulocyte and monocyte function. Dihydrorhodamine oxidative-burst testing evaluates neutrophil production of reactive oxygen species for chronic granulomatous disease. It is technically distinct from lymphocyte subset enumeration even though the instrument is the same.
Expanded testing works best as a sequence: clinical phenotype, basic screening, targeted flow assay, and confirmatory molecular or functional testing. Ordering very large panels without a focused question increases incidental findings and complicates interpretation.
How to interpret counts, percentages, and reference ranges
A result should be compared with the laboratory’s age-appropriate interval. Infants normally have higher absolute lymphocyte and subset counts than adults. Values shift rapidly during the first years of life, then continue to change through adolescence and older age. Using an adult range for an infant can miss severe disease or create a false abnormality.
Reference intervals also vary by population and method. Differences in ethnicity, sex, smoking, altitude, infection exposure, specimen handling, antibodies, gating, and counting platform can influence results. A published range from another country or laboratory is not automatically superior to a well-validated local interval.
Absolute count estimates how many cells of a subset are present per microliter. It is influenced by the total white-cell and lymphocyte counts. Dehydration, acute illness, stress hormones, and laboratory variation can change it. Absolute counts are usually central when deciding whether a population is truly depleted.
Percentage shows the subset’s share of the lymphocyte gate. It can be more stable when total lymphocyte numbers fluctuate, but it is relative. An increase in one population can make another percentage look low without changing its absolute count.
The two measures can disagree. Consider a person with a low total lymphocyte count: CD4 cells may represent a normal percentage but have a low absolute count. In another person, the absolute CD4 count may be adequate while the percentage is low because CD8 cells expanded. Neither measure should automatically overrule the other.
Borderline results often warrant repeat testing after an acute illness resolves. A single mild deviation in an otherwise well person is different from profound lymphopenia in an infant with opportunistic infection. The laboratory flag indicates statistical comparison, not diagnostic certainty.
The report may contain sums that do not match exactly. Biological overlap, small double-positive or double-negative T-cell populations, gating boundaries, rounding, and analytic variation explain many minor differences. Large discrepancies may require laboratory review for specimen quality or an unusual population.
Trends are most reliable when the same specimen type, laboratory, and panel are used. A change should be assessed against expected analytic and biological variation, not merely whether the arrow changed from “low” to “normal.”
Specimen and laboratory factors that affect accuracy
Flow cytometry requires intact, identifiable cells. Most lymphocyte panels use fresh peripheral blood collected in an anticoagulant tube. The laboratory specifies acceptable tube type, temperature, and transport time. Delayed testing can reduce viability, change marker expression, and selectively lose fragile populations.
Extreme heat or cold during transport can damage cells. Clotted specimens may trap lymphocytes and produce unreliable counts. Hemolysis, contamination, underfilled tubes, or improper mixing can also affect analysis. A sample received outside the validated stability period may be rejected or reported with a caution.
Recent transfusion, stem-cell transplant, or cellular therapy can create mixed cell populations. In infants, maternal T cells can circulate and make the total T-cell count look less abnormal than the infant’s own production. Chimerism studies may be needed to identify cell origin.
Medications are a major interpretive factor. Corticosteroids can redistribute lymphocytes. Chemotherapy can suppress several lineages. Anti-CD20 antibodies interfere with CD20-based B-cell detection and deplete cells. Other monoclonal antibodies may mask the exact marker used by the assay. Laboratories can choose alternative markers when the treatment history is known.
Technical quality depends on instrument calibration, compensation between fluorescent dyes, validated antibody panels, controls, and expert gating. Rare populations are harder to quantify because few events are collected. Debris, dead cells, monocytes, or nonspecific binding can be mistaken for lymphocytes if gating is weak.
Clinical laboratories use quality systems and proficiency testing to reduce variation, but complete standardization remains difficult. An apparent change after switching laboratories may reflect method rather than biology. The report’s comments and the clinical flow cytometrist’s interpretation can be as important as the numeric table.
Flow cytometry also samples blood, not the entire immune system. Lymphocytes continuously move among blood, lymph nodes, spleen, marrow, skin, gut, and lungs. A low circulating count can reflect redistribution into tissue, while tissue disease may exist despite normal blood subsets.
What usually follows an abnormal or normal panel
After an abnormal result, the clinician first confirms whether the pattern is severe, persistent, and clinically plausible. Urgent findings—such as profound T-cell deficiency in an infant—trigger immediate immune precautions and specialist care. Mild abnormalities during a viral illness may be repeated after recovery.
Common follow-up tests include a complete blood count with differential, quantitative immunoglobulins, HIV testing when appropriate, vaccine-specific antibody responses, complement studies, and lymphocyte proliferation. A lymphocyte proliferation test asks whether T cells respond to mitogens or antigens, which a count cannot show.
The next test should target the observed pattern. Low B cells may prompt immunoglobulins, BTK expression, and genetics. Normal B-cell numbers with low IgG may prompt B-cell subsets and vaccine-response testing. Low T cells may prompt naïve/memory phenotyping, T-cell receptor studies, proliferation, thymic evaluation, infection testing, and genetics. Abnormal NK findings may prompt degranulation, cytotoxicity, perforin, or related assays.
Genetic testing has become central to inborn errors of immunity. A panel, exome, or genome result can confirm the molecular cause, guide targeted treatment, clarify inheritance, and inform family testing. Flow cytometry remains valuable because it can provide a rapid functional or protein-level clue and help determine whether a genetic variant actually affects cells.
A normal basic panel narrows the possibilities but does not end the evaluation when symptoms are convincing. Antibody deficiency, complement deficiency, neutrophil dysfunction, innate signaling defects, and many immune-dysregulation disorders can occur with normal major lymphocyte counts. Functional and disease-specific tests may still be required.
Patients can improve the interpretation by supplying a clear history: age at first serious infection, organisms, infection sites, hospitalizations, antibiotic courses, vaccine complications, autoimmune disease, unusual rashes, chronic diarrhea, lung disease, family history, and all immune-active medications. Results drawn during fever or shortly after treatment should be identified as such.
The panel’s purpose is to transform a broad concern—“could the immune system be abnormal?”—into a more focused question. It is strongest when cell counts, percentages, developmental subsets, functional evidence, and clinical history point in the same direction.
References
- European flow cytometry quality assurance guidelines for the diagnosis of primary immune deficiencies and assessment of immune reconstitution following B cell depletion therapies and transplantation 2024 (Clinical Guideline)
- Flow cytometry-based diagnostic approach for inborn errors of immunity: experience from Algeria 2024 (Clinical Study)
- Inborn Errors of Immunity: A Role for Functional Testing and Flow Cytometry in Aiding Clinical Diagnosis 2023 (Review)
- Primary Immunodeficiency Diseases – Immunoglobulin Disorders 2026 (Clinical Reference)
- Common Variable Immunodeficiency 2025 (Clinical Reference)
- Quantitative Lymphocyte Subsets: T, B, and Natural Killer Cells, Blood 2026 (Laboratory Test Reference)
Disclaimer
This article is for general educational use and is not a diagnosis or a substitute for an immunologist’s evaluation. Flow cytometry panels, markers, counting methods, and age-specific reference intervals differ by laboratory, and results must be interpreted with specimen quality, medications, infections, and functional testing. Infants or adults with severe, unusual, or rapidly worsening infections require prompt medical care.