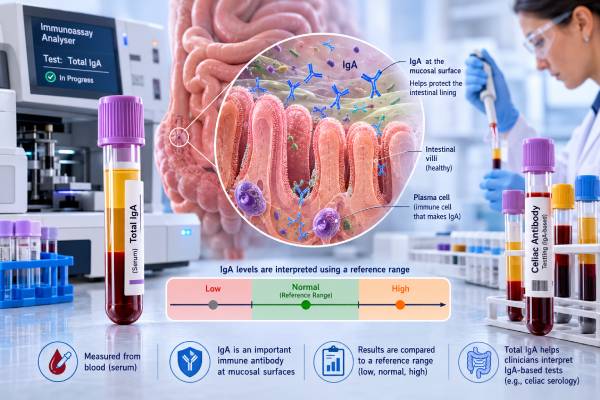
An IgA blood test measures immunoglobulin A, an antibody that helps protect surfaces exposed to the outside world, especially the respiratory and digestive tracts. Clinicians may order it when someone has recurrent sinus, ear, lung, or intestinal infections; unexplained inflammation; suspected immune deficiency; abnormal protein levels; or a celiac disease evaluation. The result is interpreted against an age- and laboratory-specific reference range. Low IgA can be mild and incidental, or it can point to selective IgA deficiency or a broader antibody disorder. High IgA more often reflects ongoing immune stimulation from liver disease, chronic infection, inflammation, or autoimmune disease, although a monoclonal plasma-cell disorder is an uncommon but important possibility. Total IgA does not identify what the antibody is reacting to, and it is not the same as an IgA autoantibody test. Its special role in celiac screening is practical: too little total IgA can make tTG-IgA and other IgA-based celiac tests falsely negative.
- IgA protects mucosal surfaces: blood testing measures total circulating IgA, not a specific infection or food reaction.
- Adult reference ranges often span roughly 70–400 mg/dL: the exact interval varies by age, method, and laboratory.
- Very low IgA can invalidate IgA-based celiac tests: IgG-based testing may be needed instead.
- High IgA is usually nonspecific: liver disease, inflammation, infection, autoimmune disease, and plasma-cell disorders are possible causes.
- No fasting is usually required: the result is commonly interpreted with IgG, IgM, liver tests, kidney tests, and protein studies.
Table of Contents
- What IgA Does in the Immune System
- Normal Range, Units, and Age Differences
- Low IgA and Selective IgA Deficiency
- High IgA and What It May Indicate
- IgA in Celiac Disease Testing
- Test Preparation and Reading the Report
- Follow-Up and When to Seek Care
What IgA Does in the Immune System
IgA is one of five major immunoglobulin classes, alongside IgG, IgM, IgE, and IgD. Plasma cells make these antibodies after B cells are activated. Each class has a different distribution and immune role.
Most IgA in the body is not circulating in blood. It is secreted onto mucosal surfaces and into fluids such as saliva, tears, breast milk, and intestinal secretions. Secretory IgA helps prevent bacteria, viruses, and toxins from attaching to and crossing the lining of the nose, lungs, and gastrointestinal tract. It often neutralizes threats without creating the intense inflammation that would damage delicate mucosal tissue.
Serum IgA—the form measured by a routine blood test—is mostly monomeric, meaning it circulates as a single antibody unit. Secretory IgA is usually dimeric and carries a protective secretory component. A normal blood level does not perfectly measure the amount or performance of IgA at every mucosal surface, but it is a useful screening marker of antibody production.
A total IgA test answers one narrow question: how much IgA is present in the sample? It does not show whether the IgA recognizes gluten, bacteria, the body’s own tissues, or any other target. Tests such as tTG-IgA, endomysial IgA, or pathogen-specific IgA measure selected antibody specificities and should not be confused with total IgA.
Serum IgA also has two subclasses, IgA1 and IgA2. IgA1 is more abundant in blood, while IgA2 is proportionally more common in some mucosal secretions and is relatively resistant to bacterial enzymes. Routine total IgA testing combines both subclasses. Subclass testing is uncommon and is usually reserved for specialized immunology or research questions.
A normal total value does not prove that every IgA molecule works normally or that mucosal defense is perfect. People can have recurrent infections for reasons unrelated to IgA quantity, including poor vaccine responses, ciliary disorders, airway damage, asthma, reflux, or frequent exposure. The result should therefore be used as one part of an immune assessment rather than a stand-alone clearance test.
Clinicians often order total IgA as part of an immunoglobulin panel. Looking at IgG, IgA, and IgM together helps distinguish an isolated IgA abnormality from a broader disorder of antibody production or a generalized increase in immune proteins.
Normal Range, Units, and Age Differences
IgA is commonly reported in milligrams per deciliter (mg/dL) or grams per liter (g/L). To convert mg/dL to g/L, divide by 100. For example, 200 mg/dL equals 2.0 g/L.
Many adult laboratories use a range near 70–400 mg/dL, but intervals can be narrower or wider. One laboratory may list 61–356 mg/dL, while another uses 90–450 mg/dL. The method, population, and calibration system affect the boundaries. The reference range printed on the report is the correct comparison for that result.
Children need age-specific interpretation. IgA is low in infancy and rises gradually through childhood. An adult cutoff applied to a young child can incorrectly suggest deficiency. Selective IgA deficiency is generally not diagnosed before age 4 because immune development is still changing and some children’s levels normalize with time.
| Result | Broad meaning | Questions that shape interpretation |
|---|---|---|
| Within the age-specific range | Circulating IgA quantity is broadly typical | Are infections or celiac symptoms still present? Are IgG and IgM normal? |
| Below range but detectable | Partial IgA deficiency, transient reduction, medication effect, protein loss, or broader immune disorder | Is the result persistent? How old is the patient? Are other immunoglobulins low? |
| Very low or undetectable | Possible selective IgA deficiency or combined antibody problem | Is IgA below 7 mg/dL after age 4? Are IgG and IgM preserved? |
| Above range | Polyclonal immune stimulation or, less often, a monoclonal IgA protein | Are liver tests, kidney findings, inflammation markers, or protein electrophoresis abnormal? |
A result near a cutoff is not automatically disease. Hydration, biological variation, recent illness, laboratory imprecision, and age can shift a value modestly. Persistent and substantial abnormalities carry more weight than one mild outlier.
There is no accepted “optimal” IgA target above the normal range. More IgA is not necessarily better. A high value can reflect chronic immune activation and should not be interpreted as stronger immunity.
Pregnancy, hydration, acute illness, and laboratory platform differences can modestly affect measured concentrations. Results are therefore most useful when interpreted as a pattern rather than a single decimal point. A person whose IgA has been stable just below the range for years and who has few infections is different from someone whose level has fallen sharply along with IgG, weight loss, diarrhea, or recurrent pneumonia.
The laboratory flag also does not determine treatment. Clinicians treat the cause and the clinical consequences, not the number itself. This distinction prevents unnecessary supplements or restrictive diets marketed as ways to “raise IgA,” none of which should replace an evidence-based immune or gastrointestinal evaluation.
Low IgA and Selective IgA Deficiency
Low IgA has a wide spectrum. Many people with an isolated low level feel well and discover it during celiac testing or a routine immune workup. Others have recurrent infections, autoimmune disease, allergies, or gastrointestinal problems.
Selective IgA deficiency
Selective IgA deficiency is generally defined as serum IgA below 7 mg/dL in a person older than 4 years, with normal IgG and IgM and no secondary cause. “Selective” means the main quantitative defect is IgA rather than all immunoglobulin classes.
The condition varies greatly. Some people remain asymptomatic throughout life. Others experience recurrent sinusitis, ear infections, bronchitis, pneumonia, chronic diarrhea, or giardiasis. The infection pattern often reflects reduced protection at respiratory and intestinal surfaces.
Associated conditions can include:
- Celiac disease
- Autoimmune thyroid disease
- Rheumatoid arthritis or lupus-like disease
- Allergic rhinitis, asthma, or other atopic conditions
- Chronic gastrointestinal infection or inflammation
- Progression in a minority of patients to a broader antibody deficiency such as common variable immunodeficiency
A low IgA level does not prove that every infection is caused by immune deficiency. Smoking, asthma, structural sinus disease, reflux, exposure to young children, and inadequate vaccination can contribute. Clinicians examine the frequency, severity, organisms, need for antibiotics, hospitalizations, and response to vaccines.
Partial or transient low IgA
A detectable level below the reference range is often called partial IgA deficiency. Its significance depends on symptoms and the rest of the immune evaluation. Children may have transient low levels that rise with age. Adults can have low IgA due to medications, protein loss, lymphoid disease, severe illness, or another immune disorder.
Potential secondary causes include some antiseizure medicines and immune-modifying therapies, nephrotic protein loss, intestinal protein-losing conditions, and hematologic disease. The medication list and timing of illness should be reviewed before labeling the finding as inherited.
Blood products and transfusion reactions
A small subset of people with severe IgA deficiency develops anti-IgA antibodies. Rarely, these antibodies contribute to serious reactions to plasma-containing blood products. Most people with low IgA do not have such reactions, and routine anti-IgA screening is not needed for everyone.
Anyone with known severe IgA deficiency and a previous transfusion reaction should tell clinicians and blood-bank staff before receiving blood products. The transfusion service can select washed cellular products or IgA-reduced components when appropriate. Emergency transfusion should not be delayed without specialist guidance.
Treatment of low IgA
There is no standard IgA replacement product that simply restores mucosal IgA. Management focuses on the person’s actual problems: prompt treatment of infections, vaccination, management of asthma or sinus disease, celiac treatment when present, and evaluation for broader antibody dysfunction. Immunoglobulin replacement may be considered only when there is an additional clinically important IgG antibody defect, not for isolated asymptomatic low IgA alone.
Vaccination remains important because protection can often be built through intact IgG responses even when IgA is very low. An immunologist may measure antibodies before and after pneumococcal vaccination when recurrent bacterial infections suggest a functional antibody problem. A normal IgG concentration does not guarantee normal vaccine response, so this functional testing can reveal an additional defect that changes management.
People with low IgA do not need to avoid ordinary social contact, travel, school, or work solely because of the laboratory result. Preventive plans should be based on actual infection burden and comorbid conditions. Recurrent pneumonia, bronchiectasis, chronic sinus disease, or unusually severe infections deserve more intensive assessment than an isolated low value in someone who rarely becomes ill.
High IgA and What It May Indicate
High IgA usually means the immune system has been stimulated over time. The test is nonspecific, so the size of the increase and accompanying results determine the next step.
Polyclonal elevation
A polyclonal increase means many different plasma-cell groups are producing IgA. Common settings include chronic liver disease, chronic infection, inflammatory bowel disease, autoimmune disease, and some kidney or skin disorders. Alcohol-related cirrhosis and advanced chronic liver inflammation can produce prominent IgA elevation.
Other possible associations include:
- IgA nephropathy or IgA vasculitis
- Rheumatoid arthritis, lupus, or other systemic inflammation
- Chronic pulmonary or gastrointestinal infection
- HIV and selected chronic infections
- Inflammatory bowel disease
- Chronic liver disease, cirrhosis, or portal hypertension
A high serum IgA does not diagnose IgA nephropathy. Many people with IgA nephropathy have normal serum IgA, and many people with high IgA do not have kidney disease. Urinalysis, urine protein, kidney function, blood pressure, and sometimes kidney biopsy are more direct tests.
Likewise, a high result does not identify the cause of liver disease. Clinicians may check AST, ALT, alkaline phosphatase, bilirubin, albumin, clotting tests, hepatitis studies, alcohol history, metabolic risk, and imaging.
Monoclonal IgA
A monoclonal elevation comes from one clone of plasma cells producing a single antibody protein. Possible causes include monoclonal gammopathy of undetermined significance, smoldering myeloma, multiple myeloma, or another plasma-cell disorder. Total IgA alone cannot distinguish polyclonal from monoclonal elevation.
Features that may prompt serum protein electrophoresis, immunofixation, and free light-chain testing include a marked or persistent increase, high total protein or globulin, anemia, kidney dysfunction, high calcium, bone pain, unexplained weight loss, neuropathy, or recurrent infections.
Most mildly elevated IgA results are not myeloma. The goal of follow-up is to separate a broad inflammatory rise from a discrete monoclonal protein without causing unnecessary alarm.
Mild isolated elevation
A small increase with normal blood counts, kidney function, liver tests, and protein studies may be rechecked after several months. Recent infection or temporary inflammation can resolve. A rising trend, a large elevation, or new symptoms deserves earlier evaluation.
The ratio between albumin and globulin can offer an early clue. High total protein with low albumin-to-globulin ratio may reflect increased immunoglobulins, but it still cannot show whether the rise is polyclonal or monoclonal. SPEP displays the distribution of serum proteins, immunofixation identifies the immunoglobulin type, and free light-chain testing assesses kappa and lambda production. These tests answer different questions and are often interpreted together.
IgA in Celiac Disease Testing
Total IgA has a critical supporting role in celiac screening. The preferred first-line antibody in most patients is tissue transglutaminase IgA, or tTG-IgA. This test works well only if the patient can make enough IgA.
A common screening strategy measures both:
- tTG-IgA, which detects an autoimmune response associated with celiac disease
- Total serum IgA, which checks whether IgA deficiency could make the tTG-IgA result falsely low or negative
If total IgA is clearly deficient, clinicians use IgG-based celiac tests such as tTG-IgG or deamidated gliadin peptide IgG. Endomysial IgA is also unreliable when total IgA is severely low.
| Total IgA | tTG-IgA | General interpretation |
|---|---|---|
| Normal | Negative | Celiac disease is less likely, though not impossible if suspicion is high |
| Normal | Positive | Supports celiac disease and usually leads to guideline-directed confirmation |
| Low or deficient | Negative | The negative IgA result may be unreliable; use IgG-based serology |
| Low or deficient | Positive | Can still be meaningful, but the complete serologic and clinical picture needs review |
Celiac blood tests should generally be performed while the person is eating gluten. Starting a gluten-free diet before testing can lower antibodies and produce a false-negative result. Anyone who has already stopped gluten should discuss a supervised diagnostic plan rather than restarting large amounts without guidance, especially after a history of severe symptoms.
Selective IgA deficiency is more common among people with celiac disease than in the general population. This association is why total IgA is not merely an optional extra. It is a quality check that helps the laboratory choose the right antibody class.
A positive celiac antibody result is not the same as a completed diagnosis. Adults commonly proceed to upper endoscopy with duodenal biopsies. Some pediatric guidelines allow a no-biopsy diagnosis under strict conditions, including very high tTG-IgA and confirmatory endomysial antibodies, but those criteria should be applied by a pediatric gastroenterology team.
When symptoms are strong but both IgA- and IgG-based serology are negative, clinicians review gluten exposure, medication use, sampling quality, and alternative diagnoses. HLA-DQ2 and HLA-DQ8 testing cannot confirm celiac disease because these genes are common, but absence of both makes celiac disease very unlikely. Endoscopy may still be considered in selected high-risk cases, particularly when malabsorption, iron deficiency, or a close family history remains unexplained.
Test Preparation and Reading the Report
The IgA test uses a venous blood sample. No fasting is usually needed. If it is ordered with a metabolic panel, lipid test, or another study, preparation may follow the requirements of those tests.
Bring or provide a list of medicines, supplements, recent infections, immune therapies, and previous immunoglobulin results. Do not stop prescribed medication without instructions. Recent plasma or immunoglobulin products can affect some antibody measurements, so timing may matter in specialized evaluations.
The report may show:
- The IgA result and units
- An age-specific reference interval
- IgG and IgM values if a panel was ordered
- Total protein, albumin, or globulin values
- A comment about low IgA and celiac serology
When comparing results over time, use the same laboratory when practical. A shift from 85 to 75 mg/dL may reflect method differences rather than a meaningful immune change. The trend is more convincing when the units, reference interval, and assay remain consistent.
Total IgA should not be confused with secretory IgA stool or saliva tests sold in some wellness settings. Those tests answer different questions, have different validation standards, and cannot replace serum immunoglobulin testing for immune deficiency or guideline-based celiac evaluation.
Follow-Up and When to Seek Care
Follow-up begins by confirming whether the abnormality is isolated. Clinicians often review IgG, IgM, complete blood count, metabolic panel, liver tests, kidney function, urinalysis, and total protein. The next step then follows the clinical pattern.
For low IgA with recurrent infections, an immunology evaluation may include vaccine antibody responses, IgG subclasses, lymphocyte counts, infection records, and assessment for structural lung or sinus disease. Family history can be useful, but selective IgA deficiency may occur without known affected relatives.
For high IgA, testing may include inflammatory markers, liver evaluation, urinalysis, kidney studies, SPEP, immunofixation, or free light chains. The workup should be proportionate to the degree of elevation and symptoms.
For celiac symptoms, total IgA determines whether IgA-based serology is trustworthy. Persistent diarrhea, weight loss, iron deficiency, osteoporosis, unexplained elevated liver enzymes, dermatitis herpetiformis, or a strong family history can justify further evaluation even when initial serology is negative.
Seek prompt medical care for:
- Trouble breathing, facial swelling, or signs of a severe transfusion reaction
- High fever with confusion, stiff neck, or rapidly worsening illness
- Coughing blood, severe shortness of breath, or low oxygen
- Dark urine, marked swelling, reduced urine output, or high blood pressure
- Severe bone pain, weakness, or symptoms accompanying anemia or kidney dysfunction
Most isolated IgA abnormalities are not emergencies. Their meaning becomes clearer when the result is placed beside infection history, celiac serology, liver and kidney findings, and the rest of the immunoglobulin profile.
References
- European Society for the Study of Coeliac Disease 2025 Updated Guidelines on the Diagnosis and Management of Coeliac Disease in Adults. Part 1: Diagnostic Approach 2025 (Guideline)
- Immunoglobulins Blood Test 2025 (Official Page)
- Differential for elevated IgA 2024 (Official Page)
- Diagnostic Guidelines for Celiac Disease 2023 (Guideline)
- Immunoglobulin A Deficiency 2024 (Official Page)
- Selective deficiency of IgA 2026 (Official Page)
Disclaimer
IgA ranges vary by age and laboratory, and abnormal values require interpretation with symptoms, medications, IgG and IgM, organ tests, and celiac serology. Do not start a gluten-free diet or alter immune treatment solely because of an IgA result; urgent symptoms such as breathing difficulty, severe infection, or reduced urine need immediate medical care.