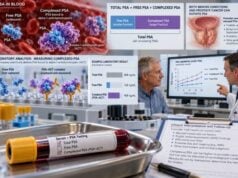
A prostate cancer biomarker panel is not one universal laboratory panel. In practice, clinicians combine selected blood or urine biomarkers with age, prostate exam findings, family history, prior biopsy results, and increasingly prostate MRI to estimate the chance of finding clinically significant prostate cancer. PSA is usually the starting point, while percent-free PSA, the Prostate Health Index (PHI), 4Kscore, PCA3, SelectMDx, and other tests can refine risk when the next step is uncertain. The goal is not simply to find more cancer. It is to identify cancers likely to matter while reducing avoidable biopsies and the diagnosis of very low-risk tumors that may never cause harm. No biomarker can confirm prostate cancer by itself, and a reassuring result does not reduce risk to zero. The most useful result is one that changes a real decision: repeat testing, obtain MRI, proceed to biopsy, or continue observation.
- PSA is the usual first-line blood marker, but a high PSA is not specific for cancer and can rise with benign prostate enlargement, inflammation, infection, or urinary retention.
- Percent-free PSA and PHI refine an elevated or borderline PSA by using different PSA forms to better separate benign conditions from cancer risk.
- 4Kscore estimates the probability of clinically significant prostate cancer using four kallikrein measurements plus clinical information rather than giving a simple positive or negative result.
- PCA3 is a urine RNA test collected after prostate manipulation and is mainly useful as an additional risk signal, especially when deciding whether another biopsy is worthwhile.
- Biomarker results should be interpreted with MRI and the full clinical picture; no single score should automatically trigger or cancel a biopsy.
Table of Contents
- What a Prostate Cancer Biomarker Panel Means
- PSA and Free PSA
- PHI, 4Kscore, and PCA3
- How Biomarker Results Are Combined
- Testing Process and Preparation
- Limitations and Common Mistakes
- What Happens After Biomarker Testing
What a Prostate Cancer Biomarker Panel Means
A prostate cancer biomarker panel is best understood as a risk-assessment pathway, not a single standardized bundle of tests. A person may start with PSA, then have one secondary biomarker if the PSA result leaves uncertainty about biopsy. Another person may go directly from PSA to prostate MRI. A third may need a different test because a previous biopsy was negative but suspicion remains.
The key clinical target is usually clinically significant prostate cancer, commonly defined as Grade Group 2 or higher. That distinction matters because prostate cancer ranges from slow-growing tumors that may be safely monitored to aggressive cancers that benefit from timely treatment. A good biomarker pathway tries to preserve sensitivity for important disease while lowering the number of unnecessary biopsies.
Biomarkers answer different questions. PSA reflects activity of prostate tissue but is not cancer-specific. Free PSA adds information about how PSA circulates in blood. PHI mathematically combines total PSA, free PSA, and p2PSA. The 4Kscore combines four kallikrein proteins with clinical variables. PCA3 measures prostate-cancer-associated RNA in urine. These tests therefore should not be treated as interchangeable measurements of the same substance.
Modern guidelines support selective use of blood or urine biomarkers when the result is likely to influence the biopsy decision. They also emphasize that biomarker testing should be integrated with established risk factors and imaging. A person who already has very high clinical suspicion may gain little from an extra biomarker, while someone at clearly low risk may not need one either.
It also helps to separate pre-biopsy biomarkers from tumor genomic classifiers used after cancer has already been diagnosed. Tests such as Decipher or Prolaris evaluate tumor biology for prognosis or treatment decisions; they do not serve the same purpose as a screening-oriented panel. For people with advanced disease, molecular testing can include inherited and tumor DNA changes, a separate topic covered in the prostate cancer HRR gene panel.
PSA and Free PSA
PSA, or prostate-specific antigen, is a protein made mainly by prostate cells. A blood PSA test is sensitive to many changes in the prostate, which is why it is useful but imperfect. Cancer can increase PSA, but so can benign prostatic hyperplasia, prostatitis, a urinary tract infection, urinary retention, and recent prostate instrumentation. PSA also tends to rise as the prostate grows with age.
There is no single PSA concentration that separates cancer from non-cancer. A value of 4.0 ng/mL was historically used as a common threshold, but contemporary practice relies more on age, repeat measurements, prostate volume, risk factors, and shared decision-making. A newly elevated PSA is often repeated before moving to a secondary test, MRI, or biopsy because temporary elevations can resolve.
The PSA test and its common benign causes are therefore the foundation for understanding every other PSA-derived marker.
Free PSA is the fraction of PSA circulating in blood without being bound to proteins. Laboratories often report percent-free PSA as:
percent-free PSA = free PSA ÷ total PSA × 100
When total PSA is in a borderline range, a lower percent-free PSA is generally associated with a higher probability of cancer, while a higher percentage is more reassuring. Common clinical reference points around 10%, 15%, 20%, and 25% are used, but they are not universal cutoffs. Age, total PSA, prostate size, assay method, and other risk factors still matter. The percent-free PSA test is most useful when it changes what happens next rather than when it is interpreted in isolation.
PSA can also be adjusted for prostate size. PSA density divides PSA by prostate volume, usually measured on ultrasound or MRI. A smaller prostate producing the same PSA as a much larger prostate generally raises more concern. Values around 0.15 ng/mL per mL have long been used as a practical reference point, although MRI-era studies support using the number as a continuous risk measure rather than a universal pass-fail boundary. More detail is available in the PSA density test.
PHI, 4Kscore, and PCA3
PHI, 4Kscore, and PCA3 are designed to improve specificity beyond total PSA, but each approaches the problem differently.
Prostate Health Index
PHI is a calculated blood result based on three PSA measurements:
PHI = (p2PSA ÷ free PSA) × √total PSA
p2PSA, also written [-2]proPSA, is a precursor form of PSA associated more strongly with prostate cancer than total PSA alone. In general, a higher PHI corresponds to a higher probability of prostate cancer and clinically significant disease. PHI is particularly useful in the PSA “gray zone,” where total PSA alone leaves substantial uncertainty. It can also be interpreted alongside MRI or PSA density.
PHI should be treated as a graded risk score, not a diagnosis. Laboratories and clinical pathways may use different decision thresholds. A value that prompts biopsy in one patient may reasonably lead to MRI or short-interval follow-up in another. See the Prostate Health Index test for its formula and result interpretation in more detail.
4Kscore
The 4Kscore is a blood-based model that measures total PSA, free PSA, intact PSA, and human kallikrein 2 (hK2). The laboratory algorithm combines these values with clinical information to estimate the percentage risk of finding clinically significant prostate cancer on biopsy. The exact model can incorporate factors such as age, prior biopsy status, and digital rectal examination information depending on the version and ordering context.
Unlike a standard PSA value, a 4Kscore is explicitly presented as a probability. A result of 8%, for example, means the model estimates an 8% risk for the specified endpoint in a patient with similar features; it does not mean the person is “8% cancer positive.” The decision threshold depends on how the patient and clinician weigh the risks of biopsy against the risks of delaying diagnosis. The 4Kscore test explains these components and probability-based results.
PCA3
PCA3, or prostate cancer antigen 3, is a noncoding RNA that is overexpressed in many prostate cancers. The test is performed on urine obtained after a clinician performs a prostate-directed digital rectal examination or massage that releases prostate cells into the urine. The assay compares PCA3 RNA with PSA RNA to generate a score.
A higher PCA3 score generally increases the likelihood of a positive biopsy, while a lower score is more reassuring. PCA3 has historically been used most often when considering a repeat biopsy after a previous negative biopsy, although MRI and newer biomarkers have changed how frequently it is used. PCA3 is not a measure of cancer stage and does not reliably tell how far a cancer has spread. The PCA3 urine test provides more detail on that role.
How Biomarker Results Are Combined
The most informative approach is to combine independent clues rather than search for one “best” number. Consider a 62-year-old with a PSA of 5.2 ng/mL. That value alone does not establish cancer. If repeat PSA remains elevated, the next risk estimate might incorporate prostate volume, percent-free PSA, family history, race or ancestry where clinically relevant, digital rectal examination, previous biopsy history, and MRI.
A practical decision sequence can look like this:
- Confirm the PSA signal. Repeat a newly elevated PSA when clinically appropriate and address obvious reversible causes such as infection or urinary retention.
- Estimate baseline risk. Include age, family history, examination findings, prior biopsy status, medication effects, and life expectancy.
- Use MRI and/or one secondary biomarker when uncertainty remains. PHI, 4Kscore, percent-free PSA, PCA3, SelectMDx, ExoDx, and other options may be considered depending on availability and the exact clinical question.
- Recalculate the biopsy tradeoff. Ask whether the combined evidence raises the likelihood of Grade Group 2 or higher cancer enough to justify biopsy.
- If biopsy is deferred, define follow-up. A low-risk biomarker result is not a permanent all-clear; repeat PSA, clinical review, or MRI may still be needed.
MRI and biomarkers can complement each other. A negative MRI reduces risk but does not eliminate it. PSA density or a secondary biomarker may be especially useful when MRI is negative yet other features remain concerning. Conversely, a suspicious MRI lesion may carry enough risk that another biomarker adds little.
The important principle is decision impact. Ordering several similar tests at once can produce conflicting probabilities without improving care. Evidence for sequentially stacking multiple biomarkers is much less established than evidence for using a selected biomarker to refine a defined decision.
Testing Process and Preparation
Preparation depends on which biomarker is ordered. Blood tests such as PSA, free PSA, PHI, and 4Kscore require a blood draw. PCA3 and SelectMDx are urine-based and may require a prostate-directed examination immediately before urine collection. Follow the laboratory’s specific instructions because specimen timing and handling can affect validity.
Before PSA-based testing, tell the clinician about recent urinary infection, prostatitis symptoms, urinary retention, catheterization, cystoscopy, prostate biopsy, or surgery. These can raise PSA temporarily. Ejaculation may cause a modest short-lived rise in some men, so some clinicians recommend avoiding it for about 24–48 hours before a test when a small change could affect a decision. Vigorous cycling has less consistent evidence but may also be avoided before a borderline repeat result.
Medications matter. Finasteride and dutasteride, used for benign prostate enlargement or hair loss, often lower PSA substantially after months of treatment. Clinicians interpret PSA differently in people taking these drugs; stopping them solely to “get a true PSA” is usually not necessary. Testosterone treatment, urinary medications, and recent prostate procedures should also be documented.
For serial testing, consistency improves interpretation. When practical, use the same laboratory and assay platform, especially when following small changes in PSA-derived values. Compare results over meaningful intervals rather than reacting to minor day-to-day variation.
If the test requires post-exam urine, collect the sample as instructed rather than substituting a random urine specimen. A negative urine biomarker from an improperly collected sample may be falsely reassuring or invalid.
Limitations and Common Mistakes
Every prostate biomarker trades sensitivity against specificity. A threshold that avoids more biopsies will also miss some clinically significant cancers. A threshold that captures nearly every important cancer will send more men without significant disease to biopsy. This is why laboratory scores should support, not replace, shared decision-making.
Common mistakes include:
- Calling a biomarker “positive for cancer.” Most pre-biopsy biomarkers estimate probability; pathology from biopsy establishes the diagnosis.
- Treating 4.0 ng/mL as a universal PSA boundary. Risk exists below 4.0, and benign conditions can produce values above it.
- Using one PHI or 4Kscore threshold for every patient. Test performance and acceptable risk depend on clinical context.
- Ignoring prostate volume. A PSA of 5 ng/mL means something different in a 30 mL prostate than in a 100 mL prostate.
- Using PSA velocity alone to trigger biopsy. Contemporary guidance specifically advises against using velocity as the sole indication; see the PSA velocity test for how trends should be interpreted.
- Assuming a negative MRI or low biomarker score means zero risk. Both can miss clinically significant disease.
- Ordering multiple secondary tests without a decision plan. More numbers can create more uncertainty if the clinician cannot say what result would change management.
Cost and coverage are also practical limitations. Commercial biomarkers may not be covered by every insurer, and performance can differ among populations. Risk models developed in one cohort may not be calibrated perfectly for another. These factors are reasons to focus on absolute risk, confidence in the test, and the consequences of each possible decision.
What Happens After Biomarker Testing
The next step depends on the combined probability of clinically significant cancer, not on whether one value is above a printed reference range.
A reassuring secondary biomarker result may support repeating PSA at an agreed interval, obtaining MRI before biopsy, or continuing surveillance if other risk features are also favorable. A higher-risk result may strengthen the case for MRI, targeted plus systematic biopsy, or repeat biopsy after a previous negative procedure. If MRI shows a suspicious lesion, targeted sampling can help determine whether cancer is present and what Grade Group it carries.
A prostate biopsy has real downsides, including bleeding, discomfort, urinary symptoms, infection risk, and the possibility of identifying a very low-risk tumor that creates anxiety or leads to unnecessary treatment. Avoiding biopsy when the chance of significant cancer is low is therefore valuable. At the same time, deferring biopsy requires a follow-up plan so that a missed or developing cancer is not ignored.
Seek prompt medical evaluation rather than relying on a scheduled biomarker test if you have fever with urinary symptoms, inability to urinate, severe pelvic pain, or signs of systemic infection. These problems can both raise PSA and require treatment on their own.
For most people, the best question after a biomarker result is not “Is this normal?” but “How did this result change my estimated risk, and what action does that risk justify?” That framing keeps the test connected to its clinical purpose and helps avoid both unnecessary procedures and false reassurance.
References
- Early Detection of Prostate Cancer: AUA/SUO Guideline Part II: Considerations for a Prostate Biopsy 2023 (Guideline)
- Molecular Biomarkers for the Detection of Clinically Significant Prostate Cancer: A Systematic Review and Meta-analysis 2022 (Systematic Review)
- Diagnostic Accuracy of Liquid Biomarkers for Clinically Significant Prostate Cancer Detection: A Systematic Review and Diagnostic Meta-analysis of Multiple Thresholds 2023 (Systematic Review)
- Prostate tumor markers: diagnosis, prognosis and management 2024 (Review)
- Blood- and urine-based biomarkers for the detection of clinically significant prostate cancer: a contemporary review 2025 (Review)
- Blood and urine-based biomarkers in prostate cancer: Current advances, clinical applications, and future directions 2025 (Review)
Disclaimer
This article provides general information about prostate cancer biomarkers and does not diagnose cancer or replace individualized medical advice. Biomarker thresholds, test availability, and biopsy decisions vary by laboratory, age, health history, MRI findings, and personal preferences. Discuss abnormal or changing results with a qualified clinician who can interpret them in context.