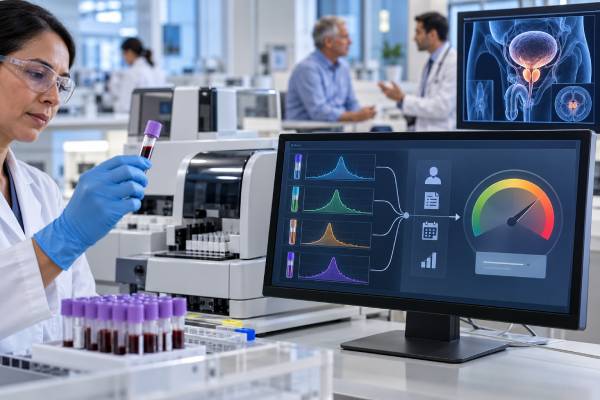
The 4Kscore test is a blood test used to estimate the chance that a man has clinically significant prostate cancer, usually defined as Grade Group 2 or higher cancer that may be more likely to need treatment. It is most useful after an elevated PSA or another concerning finding, when the next question is whether prostate biopsy or further evaluation is warranted. Rather than measuring one marker, the test combines four kallikrein proteins related to PSA with clinical information to produce a percentage risk score. A higher score means a higher estimated probability of finding significant cancer on biopsy, but it is not a diagnosis. Doctors interpret the result together with age, PSA history, prostate MRI, prostate size, family history, prior biopsy results, examination findings, overall health, and personal preferences. The test can help some men avoid an unnecessary biopsy while identifying others who may benefit from prompt tissue sampling.
- The 4Kscore estimates the percentage risk of Grade Group 2 or higher prostate cancer on biopsy; it does not confirm or rule out cancer by itself.
- The test measures total PSA, free PSA, intact PSA, and human kallikrein 2, then combines them with clinical information in a risk algorithm.
- Lower scores generally support a more conservative approach, while higher scores strengthen the case for MRI, biopsy, or closer evaluation.
- A 7.5% threshold is commonly studied, but there is no single cutoff that is correct for every patient.
- Recent prostate procedures, some medications, and the timing of a digital rectal exam can affect whether testing is appropriate.
Table of Contents
- What the 4Kscore Test Measures
- Who May Benefit From 4Kscore Testing
- How to Prepare and What to Expect
- How to Interpret a 4Kscore Result
- How 4Kscore Fits With MRI and Biopsy
- Limitations and Common Misunderstandings
- Questions to Discuss After Your Result
What the 4Kscore Test Measures
The 4Kscore is a risk-estimation test, not a stand-alone cancer test. Its purpose is to refine the information provided by a conventional prostate-specific antigen test when the decision about biopsy is uncertain.
The “4K” refers to four kallikrein proteins measured in blood:
- Total PSA, which includes the major forms of prostate-specific antigen circulating in blood.
- Free PSA, the portion of PSA not bound to blood proteins.
- Intact PSA, a specific molecular form of free PSA.
- Human kallikrein 2, or hK2, an enzyme closely related to PSA and produced mainly by prostate tissue.
The laboratory combines these measurements with clinical variables in a proprietary algorithm. Depending on the current test version and clinical setting, factors may include age and prior biopsy history, with digital rectal examination information used in some versions or workflows. The result is reported as a percentage probability of finding Grade Group 2 or higher prostate cancer if a biopsy is performed.
Grade Group 2 corresponds to Gleason score 3+4=7. This threshold matters because Grade Group 1 cancer often behaves indolently and may be managed with active surveillance, while Grade Group 2 or higher disease is more likely to influence treatment decisions.
The 4Kscore differs from a simple percent free PSA test. Percent free PSA uses the relationship between free and total PSA, whereas 4Kscore incorporates multiple kallikrein forms and clinical data. It is also different from the Prostate Health Index, which combines total PSA, free PSA, and p2PSA into a different calculation.
A useful way to think about 4Kscore is as a decision-support layer between an abnormal screening result and an invasive biopsy. It does not replace clinical judgment, and it does not describe the location, size, or stage of a tumor.
Who May Benefit From 4Kscore Testing
The test is generally considered when a man has an elevated or otherwise concerning PSA result and the need for prostate biopsy is not obvious. It may also be useful after a previous negative biopsy when PSA or other risk indicators remain concerning.
Situations in which a clinician may consider 4Kscore include:
- A persistently elevated PSA without a clear benign explanation.
- A PSA result that falls into a gray zone where biopsy benefits and harms are closely balanced.
- A previous negative biopsy with ongoing suspicion for clinically significant cancer.
- An equivocal prostate MRI or a situation in which MRI access is limited.
- A need for additional risk information before choosing surveillance versus biopsy.
The test is not meant to replace basic evaluation. Before ordering it, clinicians often review the PSA trend, urinary symptoms, evidence of prostatitis or urinary infection, prostate size, medications, recent procedures, and family history. A markedly abnormal PSA, a clearly suspicious MRI lesion, or other high-risk findings may already justify biopsy without an additional biomarker.
Professional guidelines increasingly place secondary blood and urine biomarkers within a broader risk-assessment process. The central principle is that a biomarker should be ordered only when the result could realistically change what happens next. If a patient and clinician have already decided to proceed with biopsy regardless of the result, the added test may provide little value. The same is true when both would decline biopsy regardless of the score.
Risk assessment can also incorporate PSA density, which adjusts PSA for prostate volume. A large benign prostate can produce more PSA, so prostate size sometimes changes how an elevated PSA or borderline 4Kscore is viewed.
Men with a strong family history, known inherited cancer-risk mutation, or other high-risk features may have a lower threshold for MRI, biopsy, or genetic evaluation even when a blood-based risk score appears reassuring. The result should always be interpreted in the context of the person rather than as a universal pass-or-fail number.
How to Prepare and What to Expect
The 4Kscore is performed on a blood sample. No prostate tissue is needed, and the blood draw itself is similar to other routine laboratory testing.
Preparation matters because events that change PSA or prostate biology can make the result less representative. Current manufacturer information advises that the test is not indicated immediately after certain prostate-related procedures or under specific medication conditions. Examples include a recent prostate biopsy, urinary catheterization, cystoscopy, transurethral prostate surgery, or other instrumentation. Use of a 5-alpha-reductase inhibitor such as finasteride or dutasteride can also alter PSA biology and may affect eligibility for testing depending on timing.
A digital rectal exam can temporarily influence some kallikrein measurements. Current test instructions specify avoiding a DRE within the preceding 96 hours when applicable. Because laboratory requirements can change, the ordering clinician should verify the latest collection instructions rather than relying on an old checklist.
Before the blood draw, tell the clinician about:
- Recent prostate or urinary procedures.
- Current or recent finasteride or dutasteride use.
- Symptoms of urinary tract infection or prostatitis.
- Recent urinary retention or catheter placement.
- Any recent biopsy or prostate treatment.
- The dates and values of prior PSA tests.
Fasting is not usually the central issue; the more important preparation involves avoiding conditions that can distort prostate-marker interpretation. The sample is sent to the designated laboratory, and the report returns a numerical risk percentage.
The 4Kscore is not a screening test for everyone with a prostate. It is usually a secondary test after a screening or clinical concern has already been identified. In that role, it can help reduce uncertainty before deciding on MRI or biopsy.
How to Interpret a 4Kscore Result
A 4Kscore result is reported as a percentage risk, not as “positive” or “negative” in the same way as some laboratory tests. A result of 8%, for example, means the algorithm estimates about an 8% probability of finding Grade Group 2 or higher prostate cancer on biopsy in a person with that profile. It does not mean that 8% of the prostate is cancerous, that there is an 8% lifetime cancer risk, or that cancer has already been confirmed.
There is no universally correct cutoff for every patient. The current 2026 package insert states that a 4Kscore below 5.0 is associated with a decreased likelihood of Gleason score 7 or higher cancer on biopsy. Earlier prospective studies widely evaluated a 7.5% cutoff as a low-risk decision threshold; in pooled data, that approach reduced biopsies while maintaining high sensitivity for Grade Group 2 or higher disease. More recent screening research has also used 7.5% as a reflex-test threshold after elevated PSA. These figures come from different versions and clinical settings, so the current laboratory report and the patient’s overall risk should guide interpretation.
In clinical practice, scores are often discussed in broad risk bands rather than as a rigid binary rule:
| Result pattern | General interpretation | Possible next step |
|---|---|---|
| Lower estimated risk | Clinically significant cancer is less likely, but not impossible | Repeat PSA, surveillance, MRI, or deferred biopsy depending on other risk factors |
| Intermediate estimated risk | Result may not settle the decision by itself | Combine with MRI, PSA density, family history, age, and preferences |
| Higher estimated risk | Greater probability of Grade Group 2 or higher cancer | Biopsy is more strongly considered, often guided by MRI findings |
A higher score does not reveal cancer stage, whether disease has spread, or whether treatment is necessary. Those questions require pathology, imaging, and clinical staging if cancer is found.
A low score also does not guarantee that biopsy can safely be skipped forever. Prostate cancer risk changes with time. Continued PSA follow-up may still be appropriate, especially when other risk factors are present. This is why the 4Kscore belongs within a broader prostate cancer biomarker assessment rather than being treated as a final answer.
How 4Kscore Fits With MRI and Biopsy
Modern prostate evaluation often combines biomarkers with multiparametric MRI rather than choosing one or the other. The best sequence depends on local practice, test availability, baseline risk, and how likely each result is to change the biopsy decision.
MRI can show suspicious areas within the prostate and can guide targeted biopsy. The 4Kscore provides a different kind of information: a blood-based estimate of the probability of clinically significant cancer. These tools can be complementary.
For example, a man with a mildly elevated PSA, low 4Kscore, low PSA density, and no suspicious MRI lesion may reasonably discuss delaying biopsy with structured follow-up. In contrast, a high 4Kscore plus a PI-RADS 4 or 5 MRI lesion usually creates a stronger case for biopsy. A discordant result—such as a high 4Kscore with a negative MRI—requires more individualized discussion because neither test is perfect.
Research from the GÖTEBORG-2 screening trial found that using 4Kscore after elevated PSA could reduce MRI use and biopsies, while a small number of clinically significant cancers would have their diagnosis delayed. That tradeoff illustrates the purpose of risk-stratification tests: they reduce unnecessary procedures by accepting a small possibility that some cancers will be detected later rather than immediately.
Biopsy remains the standard method for confirming prostate cancer and assigning Grade Group. A biomarker cannot substitute for tissue diagnosis when confirmation is needed. If biopsy is performed, MRI-targeted cores may be combined with systematic sampling depending on the clinical situation.
The decision is especially important because prostate biopsy has real downsides, including discomfort, bleeding, urinary symptoms, infection risk, and detection of low-grade cancers that may never cause harm. A good secondary biomarker strategy aims to reduce these harms without missing too many cancers that matter.
Limitations and Common Misunderstandings
The 4Kscore is useful, but several limitations are important.
It is a probability estimate, not a diagnosis. A score cannot prove that cancer is present or absent. Some men with low scores will still have clinically significant cancer, and some with high scores will have benign findings or low-grade disease on biopsy.
The score depends on the population and clinical context. Predictive performance can differ by age, prostate volume, PSA range, prior biopsy history, MRI pathway, and prevalence of significant cancer in the tested population. A threshold that performs well in a screening study may not be ideal for every specialty clinic.
Benign prostate enlargement can complicate interpretation. Because PSA-related proteins contribute to the algorithm, larger benign prostates may affect risk estimates. Newer research has explored adjusting the score for prostate volume, but “4K density” remains an emerging approach rather than a universally established standard.
A low score can create false reassurance if follow-up stops. The test estimates risk at a point in time. A patient with ongoing PSA elevation, changing examination findings, or new MRI abnormalities may need repeat evaluation even after a reassuring result.
A high score does not automatically mean aggressive treatment. Treatment is never selected from 4Kscore alone. If biopsy confirms cancer, management depends on Grade Group, stage, PSA, imaging, tumor volume, life expectancy, comorbidities, and patient preference.
The test is not interchangeable with every other biomarker. PHI, free PSA, urine tests, MRI, PSA density, and risk calculators answer overlapping but not identical questions. Ordering multiple tests without a clear plan can produce conflicting results and more confusion rather than better care.
Pre-test conditions matter. Recent instrumentation, prostate procedures, medication effects, and inflammatory conditions can interfere with PSA-based assessment. Confirm that the timing of the test is appropriate.
The most useful question is not “Is my 4Kscore good or bad?” but “How much does this score change my estimated risk, and does it change what I should do next?”
A useful interpretation also considers the consequence of being wrong. A younger, healthy man with a long life expectancy and several other high-risk features may reasonably choose biopsy at a lower estimated probability than an older man with serious competing health problems. Conversely, a very low score can be more reassuring when MRI, PSA density, examination, and family history are also favorable than when several of those features remain concerning.
The score should therefore be used to set a personalized biopsy threshold rather than to apply a universal pass-or-fail rule. When a result falls close to the threshold a patient and clinician had already discussed, repeating an abnormal PSA under standardized conditions or obtaining MRI may be more informative than treating a small numerical difference as decisive.
Questions to Discuss After Your Result
A good follow-up conversation turns the percentage on the report into a practical plan. Consider asking:
- What cancer grade does this score estimate the risk for?
- How does my 4Kscore compare with my PSA trend and prostate size?
- Does my family history or ancestry change how much weight we should give the result?
- Have recent procedures, infection, urinary retention, or medications affected the test?
- Should I have a prostate MRI before deciding on biopsy?
- If my MRI is negative, would this score still justify biopsy?
- If we defer biopsy, when should PSA or other testing be repeated?
- What specific change in PSA, MRI, symptoms, or examination would trigger biopsy later?
The answer can be different for two people with the same numerical score. A healthy 52-year-old with a strong family history and steadily rising PSA may accept a lower biopsy threshold than an older man with major health problems and a stable PSA pattern. Shared decision-making matters because the consequences of both action and inaction differ from person to person.
If the result is unexpectedly high, it usually calls for timely urologic review rather than panic. The next step is often MRI and/or biopsy, not immediate cancer treatment. If the score is low, confirm the follow-up plan instead of assuming that no further prostate monitoring is needed.
The 4Kscore works best when it narrows uncertainty. Used alongside PSA history, clinical risk factors, MRI, and an informed discussion about biopsy, it can help focus invasive testing on men most likely to have clinically significant disease while allowing some lower-risk men to avoid or postpone biopsy.
References
- Updates to Early Detection of Prostate Cancer: AUA/SUO Guideline (2026) 2026 (Guideline)
- Diagnostic Evaluation – EAU Guidelines on Prostate Cancer 2026 (Guideline)
- 4K density: Adjusting the 4Kscore for prostate volume to improve risk stratification of clinically significant prostate cancer in men undergoing prostate biopsy 2025
- Performance of 4Kscore as a Reflex Test to Prostate-specific Antigen in the GÖTEBORG-2 Prostate Cancer Screening Trial 2024
- The 4Kscore® Test Package Insert 2026
Disclaimer
This article provides general information about 4Kscore testing and does not replace medical advice from a urologist or other qualified clinician. A 4Kscore result should be interpreted with PSA history, examination findings, imaging, prior biopsy results, medications, and individual cancer risk. Seek prompt medical care for severe urinary symptoms, fever after a urinary or prostate procedure, or other urgent concerns.