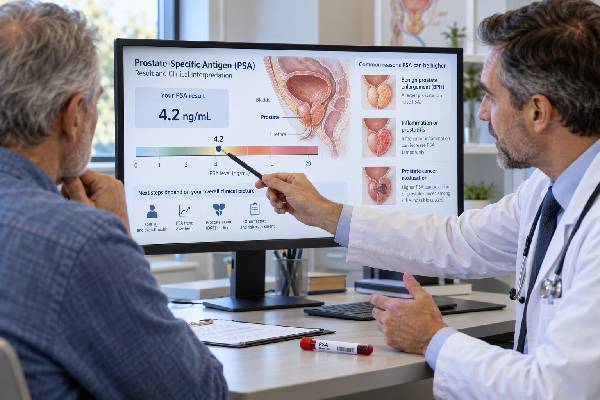
A prostate-specific antigen, or PSA, test measures the concentration of PSA in blood. PSA is produced mainly by prostate tissue, so it is useful for prostate cancer screening and follow-up, but it is not cancer-specific. Benign prostate enlargement, prostatitis, urinary infection, urinary retention, ejaculation, and recent prostate procedures can all raise PSA. There is also no single PSA value that cleanly separates cancer from non-cancer. A result below 4 ng/mL can occur in someone with prostate cancer, while a result above 4 ng/mL may be caused by a benign condition. Modern interpretation therefore focuses on age, repeat testing, prostate size, percent-free PSA, PSA density, family history, examination findings, MRI, and personal preferences. A newly elevated PSA is often repeated before MRI, a secondary biomarker, or biopsy because temporary elevations are common. For screening, the central question is not simply whether PSA is “normal,” but whether the result changes the estimated risk of clinically significant cancer enough to justify further evaluation.
- There is no universal normal PSA cutoff; 4 ng/mL is a historical reference point, not a reliable cancer/no-cancer boundary.
- A high PSA does not mean cancer is present and commonly rises with benign prostate enlargement, prostatitis, infection, urinary retention, or recent prostate manipulation.
- A newly elevated PSA is often repeated before biopsy or advanced testing because a meaningful proportion of elevations fall on repeat measurement.
- PSA screening works best through shared decision-making, with age, health, family history, ancestry, and the consequences of overdiagnosis considered before testing.
- PSA trends, percent-free PSA, PSA density, MRI, and secondary biomarkers can refine risk, but PSA velocity should not be used alone to trigger biopsy.
Table of Contents
- What PSA Measures
- Normal and High PSA Levels
- Benign Causes of High PSA
- PSA Screening by Age and Risk
- How Doctors Refine an Elevated PSA
- Preparation and Repeat Testing
- PSA After Prostate Cancer Treatment
What PSA Measures
PSA is a serine protease made by epithelial cells in the prostate. Its normal biological role is to help liquefy semen, but a small amount enters the bloodstream. A laboratory measures serum PSA in nanograms per milliliter (ng/mL).
PSA is often described as a tumor marker, but a more accurate description is prostate-associated marker. Both benign and malignant prostate cells produce it. Cancer can disrupt normal tissue architecture and increase the amount entering blood, but benign growth and inflammation can do the same. That explains why PSA is sensitive enough to be useful for screening but not specific enough to diagnose cancer.
The test has several major uses:
- screening people without known prostate cancer;
- evaluating a prostate cancer risk signal, such as an abnormal digital rectal examination;
- monitoring known prostate cancer during active surveillance;
- checking response after surgery, radiation, hormone therapy, or systemic treatment;
- detecting biochemical recurrence after definitive treatment.
The meaning of a PSA value changes across these settings. A PSA of 1.0 ng/mL in a healthy screening patient is interpreted very differently from a PSA of 1.0 ng/mL after radical prostatectomy, where the prostate has been removed and PSA is expected to become very low or undetectable.
Total PSA is the standard measurement, but laboratories can also measure the amount circulating freely rather than bound to proteins. That forms the basis of the percent-free PSA test, which can refine cancer risk when total PSA is in a borderline range.
Normal and High PSA Levels
There is no universal normal PSA range that applies to every person. Historically, 4.0 ng/mL became a commonly used threshold, but prostate cancer can occur below 4.0 and benign disease can produce much higher values. Current screening strategies increasingly use age, baseline PSA, repeated measurements, and individualized risk rather than one cutoff.
Age-specific PSA thresholds are sometimes used because prostate volume and PSA tend to rise with age. Commonly cited reference values are around 2.5 ng/mL in the 40s, 3.5 ng/mL in the 50s, 4.5 ng/mL in the 60s, and 6.5 ng/mL in the 70s, although these should not be treated as universal laboratory “normal ranges.” They are clinical risk thresholds derived from population data, not biological guarantees.
A practical way to think about PSA is:
| Pattern | What it may mean | Typical next consideration |
|---|---|---|
| Low and stable | Lower current prostate cancer risk | Repeat screening at an interval based on age and risk |
| New mild elevation | Could be temporary, benign, or cancer-related | Repeat PSA and review reversible causes |
| Persistent moderate elevation | Greater need for risk refinement | Prostate volume, free PSA, MRI, or secondary biomarker |
| Marked elevation | Higher cancer probability, but benign causes remain possible | Prompt urologic evaluation and staging as appropriate |
The absolute number matters, but so does context. A PSA of 5 ng/mL in a person with a 100 mL prostate may be less concerning than the same PSA in a 25 mL prostate. This is the logic behind PSA density.
Small changes should not be overinterpreted. PSA varies biologically and analytically. A rise from 3.8 to 4.1 ng/mL does not automatically mean the prostate has developed cancer during the interval. The trend needs confirmation and context.
Benign Causes of High PSA
A high PSA can come from several non-cancer conditions, and identifying these is an essential part of avoiding unnecessary procedures.
Benign prostatic hyperplasia (BPH) is one of the most common causes. As the prostate enlarges with age, there are simply more PSA-producing cells. BPH can cause urinary hesitancy, weak stream, nocturia, and incomplete emptying, but some men with large prostates have few symptoms.
Prostatitis and urinary tract infection can raise PSA substantially. Acute bacterial prostatitis can cause fever, chills, painful urination, pelvic or perineal pain, and urinary difficulty. PSA should not be used as the main diagnostic test for infection, and an elevated value during active infection is difficult to interpret for cancer risk.
Urinary retention can increase PSA because pressure and inflammation affect prostate tissue. A catheter placed because of retention may occur in the same clinical episode, making the timing of subsequent testing important.
Prostate manipulation and procedures can raise PSA temporarily. Prostate biopsy, transurethral procedures, cystoscopy, and some catheter-related situations may affect levels. A routine digital rectal examination has a much smaller effect and usually does not cause a clinically important PSA rise.
Ejaculation may cause a modest temporary increase, particularly in men with borderline PSA values. For this reason, clinicians sometimes advise avoiding ejaculation for 24–48 hours before repeat testing when a small difference could alter management.
Cycling and vigorous perineal pressure have less consistent evidence, but avoiding intense cycling for a day or two before a borderline repeat test is sometimes recommended as a practical precaution.
Medication can lower rather than raise PSA. Finasteride and dutasteride, 5-alpha-reductase inhibitors used for BPH or hair loss, often reduce PSA by roughly half after months of treatment. Clinicians account for this effect when interpreting cancer risk. A seemingly “normal” PSA in someone taking one of these drugs cannot be interpreted with the same assumptions as an untreated value.
PSA Screening by Age and Risk
PSA screening can reduce the chance of dying from prostate cancer in some populations, but it also creates harms: false-positive results, biopsy complications, overdiagnosis of low-risk cancer, and treatment of tumors that might never have caused symptoms. This is why modern screening emphasizes shared decision-making rather than automatic annual testing for everyone.
The 2023 AUA/SUO guideline recommends offering regular screening every 2–4 years to people aged 50–69 who choose screening after discussion of benefits and harms. It also supports offering screening starting around age 40–45 for people at increased risk, such as those with Black ancestry, strong family history, or germline mutations associated with prostate cancer.
Screening intervals can be personalized. Someone with a very low baseline PSA may reasonably wait longer between tests, while a higher baseline PSA or strong inherited risk may justify closer follow-up. Screening is less likely to provide benefit when life expectancy is limited by age or serious illness because prostate cancer often develops slowly and the harms of diagnosis and treatment occur sooner than any mortality benefit.
Family history deserves nuance. Risk is more concerning when multiple relatives are affected, diagnoses occurred at younger ages, relatives died from prostate cancer, or the family has cancers associated with hereditary syndromes. In selected families, genetic evaluation for BRCA1 and BRCA2 prostate cancer risk or other genes may be appropriate.
PSA screening is not the same as diagnosing symptomatic disease. A person with bone pain, urinary obstruction, blood in urine, unexplained weight loss, or an abnormal prostate examination may need diagnostic evaluation regardless of whether they fall inside a routine screening age range.
How Doctors Refine an Elevated PSA
A persistently elevated PSA is usually the beginning of a risk assessment, not an automatic biopsy order.
First, clinicians confirm the result and review temporary causes. If PSA remains elevated, they may use one or more refinements:
Percent-free PSA: A lower percentage of free PSA is associated with higher cancer probability in men with borderline total PSA.
PSA density: PSA is divided by prostate volume measured on MRI or ultrasound. A value around 0.15 ng/mL per mL is a widely used reference point, but the result should be treated as a continuous risk measure rather than a universal cutoff.
PHI: The Prostate Health Index combines p2PSA, free PSA, and total PSA into one score that generally improves discrimination for clinically significant cancer.
4Kscore: This blood test combines four kallikrein markers with clinical information to estimate the probability of Grade Group 2 or higher cancer.
Urine biomarkers: PCA3, SelectMDx, ExoDx, and other assays can add molecular information in selected biopsy decisions.
Multiparametric MRI: MRI can identify suspicious prostate lesions, estimate prostate volume, and guide targeted biopsy. A negative MRI reduces but does not eliminate the risk of clinically significant cancer.
Risk calculators: Validated calculators can integrate age, PSA, family history, digital rectal examination, free PSA, prior biopsy, and other variables.
PSA velocity—the rate of PSA change over time—can add context, but contemporary guidance states that it should not be the sole indication for a secondary biomarker, MRI, or biopsy. The PSA velocity test is more useful when interpreted within a larger clinical pattern.
Preparation and Repeat Testing
No fasting is required for a standard PSA blood test. Preparation is mainly about timing and documenting factors that can change the result.
Before testing, tell the clinician about:
- fever, burning urination, pelvic pain, or other infection symptoms;
- recent urinary retention;
- catheterization, cystoscopy, prostate biopsy, or prostate surgery;
- ejaculation within the previous day or two if the result is borderline;
- finasteride, dutasteride, testosterone therapy, or prostate cancer treatment;
- a recent major change in urinary symptoms.
A newly elevated PSA should often be repeated before ordering a secondary biomarker, MRI, or biopsy. The repeat interval can range from weeks to a few months depending on the value and suspected cause. If there is an infection, clinicians generally wait until it has resolved before using PSA for cancer risk assessment.
Antibiotics should not be prescribed simply to lower an asymptomatic elevated PSA. Treating documented infection is appropriate; using antibiotics as a diagnostic trial without evidence of infection can create side effects, antibiotic resistance, and false reassurance.
For serial monitoring, using the same laboratory can reduce assay-related variation. The important change is one that persists and makes biological sense, not a single small fluctuation.
Seek prompt care for inability to urinate, high fever with urinary symptoms, severe pelvic pain, or systemic illness. Those problems may raise PSA but require immediate evaluation for reasons unrelated to cancer screening.
PSA After Prostate Cancer Treatment
PSA becomes an even more sensitive marker once prostate cancer has been diagnosed and treated, but interpretation depends on the treatment.
After radical prostatectomy, essentially all prostate tissue is removed, so PSA should fall to a very low or undetectable level. A confirmed rise afterward can indicate biochemical recurrence. Definitions vary by guideline and clinical context, and ultrasensitive PSA assays can detect tiny values before they meet a formal recurrence threshold.
After radiation therapy, the prostate remains in place. PSA usually declines gradually rather than becoming undetectable, and it can take months or years to reach a nadir. A temporary PSA bounce may occur after radiation or brachytherapy and does not necessarily mean recurrence. Biochemical recurrence after radiation is commonly defined using the Phoenix criterion: PSA rising 2 ng/mL or more above the post-treatment nadir.
During active surveillance, PSA is monitored along with repeat imaging, examination, and biopsy information. A faster rise can prompt reassessment, but treatment decisions should not rely on PSA kinetics alone because benign variation can mimic progression.
In metastatic prostate cancer, PSA trends can help show treatment response or progression, but some aggressive cancers produce relatively little PSA. Symptoms, imaging, alkaline phosphatase, blood counts, and other disease markers may therefore be important as well. For selected patients, PSMA imaging can localize disease when standard PSA information is not enough.
The central principle is consistent across screening and treatment: PSA is powerful when interpreted as part of a clinical system. It is much less reliable when reduced to one “normal” number.
Another practical issue is what to do when PSA remains mildly elevated for years without a clear cause. Persistent elevation does not necessarily mean repeated biopsy is required. If a prior biopsy was negative, clinicians can reassess the quality and date of that biopsy, repeat MRI when appropriate, calculate PSA density from current prostate volume, and use a validated secondary biomarker when the result would change management. The risk of a missed clinically significant cancer generally matters more than the mere fact that PSA is above a historical threshold.
PSA interpretation should also account for the assay and baseline history. Different laboratory platforms can produce modestly different values, so a small step-up after changing laboratories may not represent a biological change. Likewise, an individual whose PSA has been 5–6 ng/mL and stable for many years may have a different risk profile from someone whose PSA has newly risen to the same level. Clinicians look for persistent patterns rather than treating every value as an isolated event.
Finally, PSA screening decisions can be revisited over time. A person who declines screening at age 50 may choose it later, while someone who has screened for years may reasonably stop when competing health risks or limited life expectancy make the harms of additional testing more likely to outweigh benefit. Shared decision-making is an ongoing process, not a one-time consent to annual PSA testing forever.
References
- Early Detection of Prostate Cancer: AUA/SUO Guideline Part I: Prostate Cancer Screening 2023 (Guideline)
- Early Detection of Prostate Cancer: AUA/SUO Guideline Part II: Considerations for a Prostate Biopsy 2023 (Guideline)
- Prostate-specific antigen screening for prostate cancer: Diagnostic performance, clinical thresholds, and strategies for refinement 2024 (Review)
- The evolving role of PSA in prostate cancer screening: revisiting the evidence in the era of personalized medicine 2026 (Review)
- Prostate-specific antigen (PSA) test for prostate cancer screening 2026 (Systematic Review)
- Blood- and urine-based biomarkers for the detection of clinically significant prostate cancer: a contemporary review 2025 (Review)
Disclaimer
This article is for general education and does not replace individualized screening advice or medical evaluation. PSA interpretation depends on age, health, prostate size, medications, symptoms, prior results, family history, and treatment history. Contact a qualified clinician for a persistently elevated PSA, concerning symptoms, or decisions about MRI, biopsy, or prostate cancer treatment.