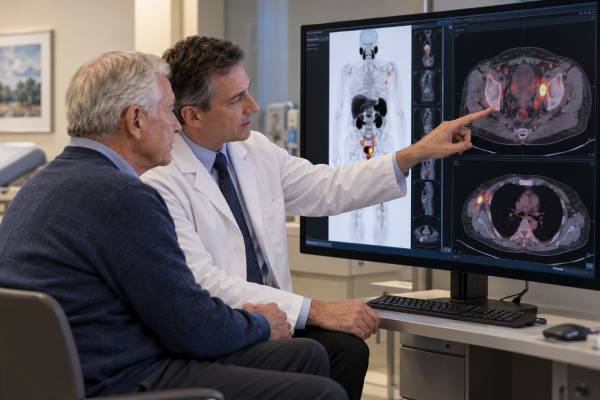
A PSMA test usually refers to imaging that targets prostate-specific membrane antigen (PSMA), a cell-surface protein highly expressed by many prostate cancers. The most common clinical form is PSMA PET, performed with a radioactive tracer such as gallium-68 PSMA-11 or fluorine-18 DCFPyL. PSMA PET can detect prostate cancer in lymph nodes, bones, and other sites that may be missed by conventional CT or bone scanning, making it especially useful for staging higher-risk disease and evaluating biochemical recurrence after treatment. PSMA is not perfectly prostate-specific: normal salivary glands, kidneys, bowel, sympathetic ganglia, and some benign or non-prostate tumors can also show tracer uptake. A negative scan does not rule out cancer because some tumors have low or heterogeneous PSMA expression and very small lesions may remain below PET resolution. PSMA imaging can also help determine eligibility for PSMA-targeted radioligand therapy in selected metastatic patients. It is an imaging biomarker, not a routine blood screening test and not a replacement for biopsy when tissue diagnosis is required.
- PSMA PET is an imaging test, not a standard blood test, and uses a radioactive tracer that binds to PSMA-expressing cells.
- The test is widely used for biochemical recurrence and staging higher-risk prostate cancer, where it can detect disease outside the prostate more sensitively than older imaging in many settings.
- A positive PSMA focus is not automatically prostate cancer because benign structures and other tumors can take up PSMA tracers.
- Detection generally improves as PSA rises in biochemical recurrence, but PSMA PET can still identify disease at relatively low PSA levels in some patients.
- PSMA PET may be used to select patients for PSMA-targeted radioligand therapy, but exact treatment eligibility depends on the tracer, disease setting, prior therapy, and current criteria.
Table of Contents
- What PSMA Is
- How PSMA PET Works
- When PSMA Imaging Is Used
- How to Interpret PSMA PET Results
- PSA Level and Detection Rate
- Preparation, Radiation, and Safety
- PSMA-Targeted Treatment and Limitations
What PSMA Is
PSMA stands for prostate-specific membrane antigen. Despite its name, PSMA is not an antigen unique to the prostate. It is a transmembrane protein also known as glutamate carboxypeptidase II or folate hydrolase 1, encoded by the FOLH1 gene. Normal prostate tissue expresses it, but many prostate cancers express much larger amounts on the surface of tumor cells.
PSMA expression often increases in higher-grade, metastatic, and castration-resistant disease. That makes it an attractive molecular target: if a radioactive molecule binds to PSMA, clinicians can visualize where PSMA-expressing cells are located. The same targeting concept can be used to deliver therapeutic radiation.
This is different from PSA. PSA is a protein measured in blood and is used for screening and monitoring. PSMA is mainly exploited as a cell-surface imaging and treatment target. A patient can have a low PSA but a PSMA-positive lesion, or a rising PSA with little PSMA expression.
PSMA also appears in the blood vessels of some non-prostate cancers and in several benign tissues. Physiologic uptake is normally seen in salivary and lacrimal glands, kidneys, urinary tract, liver, spleen, and bowel depending on the tracer. Sympathetic ganglia can also show uptake and are a common source of interpretation errors.
Because PSMA expression is heterogeneous, not every prostate cancer cell is equally visible. Small lesions, poorly differentiated tumors, and some neuroendocrine prostate cancers may express little PSMA. That is one reason a negative scan cannot be treated as proof that cancer is absent.
How PSMA PET Works
PSMA PET uses a radiotracer: a PSMA-binding molecule attached to a positron-emitting isotope. After intravenous injection, the tracer circulates and binds to PSMA-rich tissue. A PET scanner detects the radiation produced as the isotope decays and creates a three-dimensional map of tracer activity.
Commonly used tracers include 68Ga-PSMA-11 and 18F-DCFPyL. Other fluorine-18 tracers, such as 18F-PSMA-1007, are used in some regions. Tracers differ in production, half-life, normal biodistribution, and urinary clearance, which can affect image interpretation.
PET is typically combined with CT, producing PSMA PET/CT. The CT component gives anatomic information so an area of tracer uptake can be matched to a lymph node, bone, organ, or soft-tissue structure. Some centers use PSMA PET/MRI, which combines molecular information with high-resolution MRI.
The scan produces images and semi-quantitative measures such as standardized uptake value, or SUV. A higher SUV can indicate stronger tracer accumulation, but there is no single SUV cutoff that defines cancer across all tracers and organs. Interpretation relies on lesion location, uptake pattern, comparison with normal background, CT or MRI findings, and the patient’s known disease.
For recurrence, PSMA PET can identify small-volume disease that conventional imaging misses. For primary staging, it can reveal lymph-node or distant metastases before definitive surgery or radiation. For selected advanced cancers, a PSMA PET scan also evaluates whether there is enough target expression for PSMA-directed radioligand therapy.
When PSMA Imaging Is Used
PSMA PET is most established in three clinical situations: initial staging of higher-risk prostate cancer, biochemical recurrence, and treatment selection in advanced disease.
Initial staging
After prostate cancer is diagnosed by biopsy, patients with unfavorable intermediate-risk or high-risk features may need imaging to determine whether cancer has spread outside the prostate. PSMA PET is more sensitive than conventional CT and bone scan for many metastatic sites, particularly small lymph-node and bone lesions.
However, PSMA PET does not replace local staging MRI or pathology. A scan can miss microscopic lymph-node disease, and sensitivity for small nodal metastases remains imperfect. A negative scan therefore does not automatically eliminate the need for pelvic lymph-node dissection when surgical risk calculations otherwise support it.
Biochemical recurrence
After radical prostatectomy or radiation, PSA can rise before conventional imaging shows a lesion. This is called biochemical recurrence. PSMA PET has become one of the most useful imaging methods in this setting because it can localize recurrent disease at relatively low PSA levels.
Finding one pelvic lymph node may lead to a very different treatment plan than finding widespread bone metastases. Meta-analyses show PSMA PET changes management in a substantial proportion of patients with biochemical recurrence, often more than half in pooled studies.
Advanced and metastatic disease
In metastatic castration-resistant prostate cancer, PSMA imaging can evaluate the distribution and intensity of target expression. This is important before therapies such as lutetium-177–PSMA-617 in patients who meet treatment criteria.
A PSMA scan is therefore not simply “a better cancer scan.” Its value depends on whether the result can change staging, radiation fields, surgery, systemic treatment, or radioligand eligibility.
How to Interpret PSMA PET Results
A PSMA PET report usually describes where uptake is seen, how intense it is, and whether the pattern is suspicious for prostate cancer. The interpreting physician compares tracer activity with normal structures and the CT or MRI appearance.
Common suspicious sites include the prostate or prostate bed, pelvic and retroperitoneal lymph nodes, bones, lungs, liver, and other soft tissues. Uptake outside expected physiologic locations is not automatically malignant. Common pitfalls include:
- sympathetic ganglia, particularly celiac and sacral ganglia, which can resemble small nodes;
- healing fractures, degenerative bone changes, or benign bone lesions with certain tracers;
- salivary glands, kidneys, bowel, and urinary tract, where physiologic activity is expected;
- inflammation or benign tumors that can show PSMA uptake;
- other cancers, because PSMA can be expressed in tumor neovasculature.
A “PSMA-positive” lesion means the tracer accumulated there; pathology or follow-up may still be needed when location or appearance is atypical.
False-negative scans also occur. Reasons include very small lesion size, low tumor volume, low PSMA expression, certain histologic variants, and prior treatment effects. Neuroendocrine differentiation is particularly important because some aggressive tumors lose PSMA expression while increasing glucose metabolism, making FDG PET informative in selected advanced cases.
The report should be interpreted together with the broader metastatic prostate cancer biomarker profile, pathology, symptoms, and prior imaging. Molecular imaging is powerful because it adds information, not because it makes other evidence unnecessary.
PSA Level and Detection Rate
In biochemical recurrence, the chance of a positive PSMA PET scan generally rises with the PSA level. A 2023 meta-analysis of prospective studies found pooled detection rates of roughly 44% when PSA was 0–0.5 ng/mL, 63% at 0.5–1.0, 82% at 1–2, and 94% above 2 ng/mL. Exact rates vary by tracer, study population, prior treatment, PSA doubling time, and scan technology.
These numbers should not be interpreted as probabilities that an individual patient has recurrence. Biochemical recurrence is often already established by PSA criteria; the detection rate describes how often PSMA PET can localize disease at a given PSA range.
A negative scan at PSA 0.2 ng/mL is therefore not surprising and does not necessarily mean there is no recurrent cancer. The lesion may simply be too small or weakly PSMA-expressing to detect. If PSA continues to rise, repeating imaging later may become informative.
PSA kinetics can also matter. Shorter PSA doubling time and higher PSA velocity may increase the likelihood that recurrent disease will be detected, although these factors should be used as part of a broader risk model. The PSA velocity test explains why trends should not be interpreted in isolation.
Timing is especially important when salvage radiation after prostatectomy is being considered. Waiting for a scan to become positive at a higher PSA can delay potentially curative treatment. A negative PSMA PET should therefore not automatically postpone salvage radiation when clinical evidence supports early therapy.
Preparation, Radiation, and Safety
Preparation varies by tracer and imaging center, but PSMA PET is generally straightforward. Patients receive an intravenous injection and then wait while the tracer distributes through the body before imaging begins.
Fasting is not always required for PSMA PET, unlike FDG PET, but the center’s instructions should be followed exactly. Hydration is often encouraged because many tracers are cleared through the kidneys. Patients may be asked to urinate shortly before scanning to reduce activity in the bladder and improve visualization of the pelvis.
Tell the imaging team about:
- current medications and prostate cancer treatments;
- kidney problems or difficulty urinating;
- recent imaging or radiopharmaceutical procedures;
- inability to lie still or severe pain;
- allergies if contrast-enhanced CT is planned;
- prior surgery or radiation that may alter anatomy.
The PET radiotracer exposes the body to a relatively small amount of ionizing radiation. Additional exposure comes from the CT component, especially if a diagnostic contrast CT is performed. The radiation risk is generally considered acceptable when the scan is clinically indicated, particularly in patients with known cancer, but unnecessary repeated imaging should still be avoided.
Serious reactions to PSMA radiotracers are uncommon. The main immediate issues are the intravenous injection and the practical demands of lying still during imaging. Contrast-related risks apply only if iodinated CT contrast or gadolinium MRI contrast is also used.
Because radioactive material is excreted for a short period, imaging centers may provide temporary instructions about hydration, urination hygiene, and close contact with pregnant people or small children. Follow the facility’s specific radiation-safety advice.
PSMA-Targeted Treatment and Limitations
The same PSMA target used for imaging can be used to deliver therapeutic radiation. Lutetium-177–PSMA-617, also called lutetium-177 vipivotide tetraxetan, binds PSMA and emits beta radiation that damages nearby tumor cells. In the VISION phase 3 trial, adding this therapy to standard care improved radiographic progression-free survival and overall survival in selected patients with PSMA-positive metastatic castration-resistant prostate cancer.
Imaging is central because treatment works only if enough tumor sites express the target. Eligibility criteria vary by indication and regulatory label. Some treatment pathways require demonstrating PSMA-positive disease without certain large PSMA-negative lesions; newer disease settings may use different criteria. Patients should not assume that “any positive PSMA scan” automatically qualifies them.
PSMA-directed treatment also has limitations. Salivary glands, kidneys, bone marrow, and other normal tissues receive some radiation. Dry mouth, fatigue, nausea, blood-count suppression, and kidney effects are among issues that may require monitoring. Tumors can also contain mixed cell populations: some lesions may be strongly PSMA-positive while others are weak or negative, which can lead to treatment resistance.
PSMA PET itself has important limitations:
- it cannot replace biopsy when a tissue diagnosis is required;
- it can miss microscopic nodal disease;
- false-positive uptake can occur in benign conditions and other cancers;
- different tracers have different normal uptake patterns and pitfalls;
- a negative scan at low PSA does not exclude recurrence;
- access, cost, and insurance coverage vary by region.
For primary diagnosis in someone who has never had a biopsy, MRI remains the standard imaging foundation in most pathways, while PSMA PET is being studied as an additional tool. Recent systematic reviews show promising diagnostic performance, particularly when PSMA PET is combined with MRI, but routine pre-biopsy use is still evolving.
The most useful way to think about PSMA is as a molecular address label that many prostate cancers display. PET uses that address to find disease; radioligand therapy uses the same address to deliver radiation. Neither application is perfect, but together they have changed how metastatic and recurrent prostate cancer is staged and treated.
PSMA PET can also create a problem called stage migration. A patient who would once have been classified as having localized disease based on CT and bone scan may be found to have a tiny PSMA-positive lymph node or bone lesion. The scan has not made the cancer worse; it has made the staging more sensitive. Treatment recommendations based on older trials using conventional imaging may therefore require careful interpretation when PSMA PET detects very small-volume metastatic disease.
Another practical issue is incidental uptake. Because PSMA tracers can highlight benign bone changes, ganglia, inflammation, and non-prostate tumors, an unexpected isolated focus may lead to targeted CT, MRI, follow-up imaging, or biopsy before a major treatment decision is made. This is especially important with lesions in unusual locations or with an appearance that does not fit the patient’s known prostate cancer pattern.
PSMA expression can also change under treatment pressure. Androgen-receptor signaling, tumor differentiation, and prior systemic therapy can influence target expression, so a scan obtained years earlier may not perfectly represent current metastatic biology. In advanced disease, repeat molecular imaging may be considered when a new PSMA-targeted treatment decision depends on current expression.
In practical terms, the most useful PSMA report is one interpreted in context rather than as a simple positive-or-negative test. The clinician should compare the distribution and intensity of uptake with the PSA history, prior treatment fields, conventional imaging, symptoms, and the specific decision being considered. That approach helps distinguish findings that genuinely change management from small or uncertain abnormalities that need confirmation.
References
- Appropriate Use Criteria for Prostate-Specific Membrane Antigen PET Imaging 2022 (Guideline)
- Histopathologically Validated Diagnostic Accuracy of PSMA-PET/CT in the Primary and Secondary Staging of Prostate Cancer and the Impact of PSMA-PET/CT on Clinical Management: A Systematic Review and Meta-analysis 2023 (Systematic Review)
- Detection Rate of PSMA PET Using Different Ligands in Men with Biochemical Recurrent Prostate Cancer Following Radical Treatment: A Systematic Review and Meta-analysis of Prospective Studies 2024 (Systematic Review)
- A Comprehensive Systematic Review and Meta-analysis of the Role of Prostate-specific Membrane Antigen Positron Emission Tomography for Prostate Cancer Diagnosis and Primary Staging before Definitive Treatment 2025 (Systematic Review)
- A systematic review and meta-analysis to evaluate the diagnostic accuracy of PSMA PET/CT in the initial staging of prostate cancer 2025 (Systematic Review)
- Health-related quality of life and pain outcomes with [177Lu]Lu-PSMA-617 plus standard of care versus standard of care in patients with metastatic castration-resistant prostate cancer (VISION): a multicentre, open-label, randomised, phase 3 trial 2023 (RCT)
Disclaimer
This article is for general education and does not replace individualized imaging, oncology, or nuclear medicine advice. PSMA PET indications, tracer availability, scan interpretation, and radioligand treatment criteria vary by country, cancer stage, prior therapy, and current guidelines. A positive or negative scan should be reviewed with the clinician managing the prostate cancer.