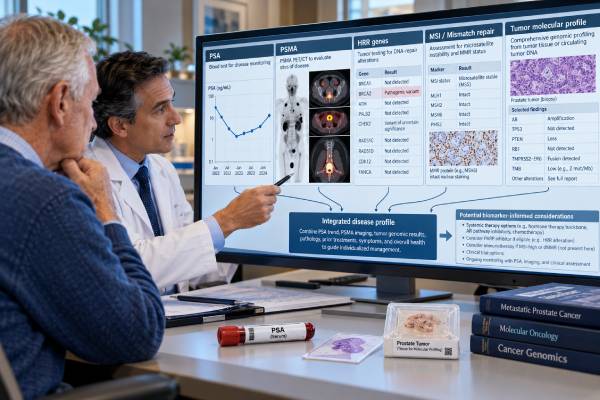
A metastatic prostate cancer biomarker panel is not one single laboratory test. It is a coordinated set of blood tests, molecular tests, pathology findings, and imaging biomarkers used to define the cancer’s current behavior and identify treatment options. PSA helps track disease activity over time; PSMA PET shows whether tumors express enough prostate-specific membrane antigen for sensitive imaging and, in selected patients, PSMA-targeted radioligand treatment; germline and somatic DNA testing looks for homologous recombination repair (HRR) alterations such as BRCA1 or BRCA2 that may guide PARP-inhibitor therapy; and MSI-high or mismatch-repair deficiency can identify a small subgroup with potential sensitivity to immune checkpoint treatment. A broader tumor profile may also report alterations in genes such as PTEN, TP53, RB1, CDK12, and androgen-receptor pathway genes. The most useful “panel” therefore changes over the course of metastatic disease. It should be updated when prior testing was incomplete, tissue quality was poor, or the cancer’s biology changes after treatment.
- PSA: Best used as a trend marker for response and progression; PSA alone cannot show every site of disease or determine treatment eligibility.
- PSMA: PSMA PET measures tumor PSMA expression and location and can determine eligibility for PSMA-targeted radioligand therapy when the treatment label requires a positive scan.
- HRR genes: Metastatic prostate cancer patients should generally receive both germline and somatic panel testing; BRCA1/2 alterations have the strongest established predictive value for PARP-based therapy.
- MSI/dMMR: MSI-high or mismatch-repair-deficient prostate cancer is uncommon but clinically important because it may support checkpoint immunotherapy.
- Retesting: A negative or uninformative old result may need reassessment with metastatic tissue or circulating tumor DNA if disease status changes.
Table of Contents
- What a metastatic prostate cancer biomarker panel includes
- PSA as a monitoring biomarker
- PSMA for imaging and radioligand treatment
- HRR genes, germline testing, and PARP therapy
- MSI, mismatch repair, and the broader tumor profile
- Tissue biopsy versus circulating tumor DNA
- How biomarker results guide treatment and follow-up
What a metastatic prostate cancer biomarker panel includes
A complete metastatic workup usually combines clinical biomarkers, imaging biomarkers, and genomic biomarkers because each answers a different question. No single result can describe the entire disease.
At minimum, the biomarker picture often includes:
- serum PSA and testosterone;
- standard laboratory measures relevant to disease burden and treatment safety, such as blood counts, alkaline phosphatase, kidney function, and liver tests;
- pathology review confirming prostate cancer subtype when tissue is available;
- PSMA PET when clinically indicated for staging, restaging, or treatment selection;
- germline hereditary cancer testing;
- somatic tumor sequencing from tissue or circulating tumor DNA;
- assessment of HRR genes and other actionable DNA-repair alterations;
- MSI or mismatch-repair status, often with tumor mutational burden reported on comprehensive profiles;
- selected additional biomarkers based on disease phenotype, prior therapies, and available targeted treatments or clinical trials.
The panel is best viewed as a living tumor profile rather than a one-time checklist. A person diagnosed with metastatic hormone-sensitive disease may need inherited and tumor genomic testing early, while someone whose cancer later becomes metastatic castration-resistant prostate cancer may need updated sequencing or PSMA imaging before choosing the next therapy.
This differs from an early-detection prostate cancer biomarker panel. Tests such as free PSA, PHI, 4Kscore, and urine biomarkers mainly help decide whether a biopsy is needed before cancer is diagnosed. In metastatic disease, the central questions are disease burden, treatment response, molecular vulnerabilities, and resistance.
The terminology can also be confusing. A “germline panel” uses normal DNA from blood or saliva to identify inherited variants. A “somatic panel” analyzes the tumor’s acquired mutations. A “comprehensive genomic profile” may report mutations, insertions and deletions, copy-number changes, rearrangements, MSI, and sometimes tumor mutational burden. These reports overlap but are not interchangeable.
PSA as a monitoring biomarker
PSA is the most familiar biomarker for following metastatic prostate cancer, but it is a response marker rather than a complete map of disease. Serial PSA values can show whether androgen-deprivation therapy, an androgen-receptor pathway inhibitor, chemotherapy, radioligand therapy, or another treatment is suppressing prostate-cancer activity.
The pattern over time matters more than one isolated number. A large PSA decline after treatment is often reassuring, while a sustained rise can suggest emerging resistance. The exact interpretation depends on treatment type, baseline disease burden, imaging, symptoms, and whether the tumor continues to produce PSA.
In metastatic castration-resistant prostate cancer, progression cannot be defined from PSA alone. Guidelines and clinical trials typically integrate PSA with radiographic progression, clinical deterioration, and symptoms. A patient can have radiographic progression with only a modest PSA change, and occasionally PSA may rise transiently before later falling depending on the treatment and timing.
The PSA test also has a different meaning once metastatic cancer is established. There is no “normal PSA range” that determines whether metastatic disease is controlled. The useful comparison is usually the patient’s own baseline and treatment-related trend.
Some advanced cancers become less dependent on androgen-receptor signaling and produce relatively little PSA despite increasing tumor burden. This can occur with aggressive-variant or neuroendocrine transformation. Clues include rapidly progressive visceral metastases, lytic bone lesions, a disproportionately low PSA for the amount of disease, or rising non-PSA markers in a changing clinical picture. Such changes can prompt repeat biopsy and a broader pathology or genomic reassessment.
Testosterone is commonly checked alongside PSA in castration-resistant disease because the definition requires progression despite castrate androgen levels. If testosterone is not adequately suppressed, the first problem may be incomplete hormonal suppression rather than true resistance.
PSMA for imaging and radioligand treatment
PSMA is both an imaging biomarker and a treatment-selection biomarker. Prostate-specific membrane antigen is a cell-surface protein expressed at high levels in most prostate cancers, particularly many advanced tumors. Radiolabeled molecules that bind PSMA make disease visible on PET scans and can also deliver therapeutic radiation.
A PSMA PET scan can detect metastatic lesions in lymph nodes, bone, and soft tissue with high sensitivity. In metastatic disease, its role may include staging, evaluating suspected progression, clarifying equivocal conventional imaging, and selecting patients for PSMA-targeted radioligand therapy.
The PSMA test is therefore not a serum concentration like PSA. “PSMA-positive” generally refers to sufficient uptake on an approved PSMA PET study under the criteria used for a specific clinical purpose or treatment.
This distinction is especially important for lutetium-177 PSMA therapy. In the United States, PSMA-positive status is established with an approved PSMA PET imaging agent when required by the treatment indication. As of 2026, PSMA-targeted lutetium-177 therapy has moved earlier in the treatment pathway: the FDA expanded use in 2025 for selected PSMA-positive metastatic castration-resistant prostate cancer after an androgen-receptor pathway inhibitor when delaying taxane chemotherapy is appropriate, and in July 2026 approved combination use with an androgen-receptor pathway inhibitor for PSMA-positive metastatic androgen-pathway-modulation-naïve or -sensitive disease.
Not every metastasis expresses PSMA equally. Tumor heterogeneity matters. A person may have strongly PSMA-avid bone disease but a liver lesion with little PSMA expression. Discordant disease can reduce confidence that PSMA-directed therapy will control every clone and may prompt additional imaging or biopsy.
PSMA can also decrease when prostate cancer undergoes lineage plasticity or neuroendocrine transformation. A previously PSMA-positive cancer is therefore not guaranteed to remain uniformly positive forever.
HRR genes, germline testing, and PARP therapy
Both germline and somatic DNA sequencing are recommended for metastatic prostate cancer because inherited and tumor-acquired HRR alterations can affect treatment and family counseling. The 2025 ASCO genomic-testing guideline specifically recommends panel-based germline and somatic testing for patients with metastatic disease.
Homologous recombination repair is a DNA-repair pathway. Important genes include BRCA2, BRCA1, PALB2, ATM, CHEK2, CDK12, RAD51-family genes, and others depending on the assay and drug label. Loss of key repair functions can make tumor cells more dependent on alternative repair mechanisms, creating vulnerability to PARP inhibition.
BRCA2 is the most consistently actionable gene in prostate cancer. Across trials and guidelines, BRCA1/2 alterations have the strongest evidence for benefit from PARP-based strategies. Evidence for other HRR genes is more variable. A report that lists an “HRR mutation” should therefore be read gene by gene rather than treating every alteration as equivalent.
The prostate cancer HRR gene panel also has family implications. A BRCA2 variant found in tumor tissue could be somatic only or could represent an inherited germline variant. Confirmatory germline testing can determine whether relatives may also be at risk.
Current treatment choices depend on disease state, prior therapy, the exact gene, zygosity or functional significance, regulatory approval, and drug-specific companion diagnostic requirements. By 2026, PARP-based treatment has expanded beyond a single late-line setting, including combinations with androgen-receptor pathway inhibitors and, for specific molecular groups, use in metastatic hormone-sensitive disease. Because indications evolve quickly, the exact report should be reviewed against the current label and guideline rather than an older list of “PARP-eligible genes.”
A negative HRR panel does not mean genomic testing was useless. It may still reveal MSI, PTEN-pathway changes, CDK12 alterations, aggressive tumor-suppressor patterns, or a clinical-trial target.
MSI, mismatch repair, and the broader tumor profile
MSI-high and mismatch-repair deficiency are uncommon in prostate cancer, but they are important because they can predict benefit from immune checkpoint therapy. Mismatch-repair proteins normally correct DNA replication errors. When this system fails, repetitive DNA regions called microsatellites accumulate errors, producing an MSI-high phenotype.
Testing may be reported as:
- MSI-H from DNA-based analysis;
- dMMR from loss of mismatch-repair proteins on immunohistochemistry or from pathogenic mismatch-repair gene alterations;
- a related high tumor mutational burden value on some comprehensive genomic profiles.
The microsatellite instability test is relevant because tumor-agnostic immune checkpoint indications can apply to prostate cancer when the required biomarker is present. A mismatch-repair gene alteration may also raise the possibility of Lynch syndrome, so germline confirmation can be important for both the patient and family.
A broad tumor profile often reports additional alterations. These may not all have an approved prostate-cancer treatment, but they can define biology and clinical-trial options:
- PTEN loss or PI3K/AKT pathway changes can identify a biologically distinct subgroup and are increasingly relevant as AKT-targeted strategies move through clinical development and treatment pathways.
- TP53 and RB1 loss can suggest aggressive biology, especially when combined, and may support concern for lineage plasticity.
- CDK12 alterations create a distinct genomic subtype with different immune and DNA-repair features from BRCA-deficient disease.
- Androgen-receptor amplification, mutation, or splice variants can reflect resistance to androgen-receptor-directed treatment.
- Neuroendocrine markers on pathology may become important if the cancer changes phenotype.
The practical rule is to separate prognostic information from predictive information. A marker may indicate more aggressive cancer without identifying a proven drug. Conversely, a predictive marker such as BRCA2 or PSMA can directly affect therapy selection.
A broader tumor profile can also reveal alterations such as PTEN loss, TP53 or RB1 changes, CDK12 alterations, and androgen-receptor pathway changes. These findings can help explain tumor biology, identify clinical-trial options, or add prognostic context, but not every detected alteration has an approved targeted treatment. That distinction is important: a report may contain many “actionable-looking” variants, yet only a smaller subset are linked to treatments supported by prostate cancer evidence and current regulatory indications.
Tumor phenotype can also change over time under treatment pressure. A cancer that becomes unusually aggressive with a low or discordant PSA, visceral metastases, or other atypical features may require repeat tissue evaluation for treatment-emergent neuroendocrine or small-cell transformation. In that situation, pathology and clinical behavior can be more informative than simply repeating the original DNA panel.
Tissue biopsy versus circulating tumor DNA
Tumor tissue and circulating tumor DNA are complementary sources of somatic genomic information, and neither is perfect in every patient. ASCO recommends considering metastatic tissue or ctDNA when earlier testing is negative, uninformative, or outdated after a meaningful clinical change.
Archived primary prostate tissue is often the easiest specimen to retrieve. It can identify stable driver alterations that were present early in the cancer. The limitation is age and sampling: a prostate biopsy from years earlier may not capture resistance mechanisms that emerged under treatment.
A metastatic biopsy samples current disease directly and allows both genomic testing and pathology review. It can be particularly valuable when there is concern for neuroendocrine transformation or another histologic change. The downside is that bone lesions can be technically difficult to biopsy and decalcification may damage DNA or RNA.
Circulating tumor DNA, or ctDNA, uses blood to sample tumor-derived DNA fragments. It can capture alterations from multiple metastatic sites and avoids an invasive biopsy. It is especially useful when tissue is unavailable or unsafe to obtain.
The major limitation is low tumor fraction. If very little tumor DNA is circulating, a negative liquid-biopsy result may be a false negative. This is why an “insufficient” or low-shedding result should not be treated as proof that no actionable alteration exists. A tissue test may still be needed.
Another challenge is clonal hematopoiesis—age-related mutations in blood-forming cells that can appear in plasma DNA and mimic tumor mutations. High-quality assays and matched normal controls help distinguish these signals.
How biomarker results guide treatment and follow-up
The value of a metastatic biomarker panel is that it converts tumor biology into specific decisions: what to treat with, what to monitor, what to retest, and what relatives may need to know. The result should be reviewed as a coordinated profile rather than a stack of unrelated laboratory values.
A practical interpretation might look like this:
| Biomarker | Main question | Potential action |
|---|---|---|
| PSA and testosterone | Is disease responding or progressing under adequate androgen suppression? | Trend with symptoms and imaging; confirm castrate testosterone in resistant disease |
| PSMA PET | Where is disease and is it sufficiently PSMA-positive? | Stage/restage and assess eligibility for PSMA-targeted radioligand therapy |
| BRCA1/2 or other HRR alteration | Is there a DNA-repair vulnerability? | Consider guideline- and label-appropriate PARP-based therapy |
| MSI-H/dMMR | Is the tumor hypermutated through mismatch-repair failure? | Consider checkpoint immunotherapy and evaluate possible hereditary implications |
| Broad tumor profile | Are there resistance markers, aggressive subtypes, or trial targets? | Refine prognosis, prompt biopsy, or identify clinical trials |
The order of treatments still depends on far more than biomarkers. Symptoms, prior therapies, sites of metastasis, marrow reserve, kidney and liver function, neuropathy, cardiovascular health, patient goals, drug access, and expected toxicities all matter.
Patients should ask whether both germline and somatic testing have been completed, whether the tumor fraction was adequate, whether older testing covered today’s clinically relevant genes, and whether a PSMA PET result is current enough for the contemplated therapy. They should also ask whether a pathogenic germline result requires family counseling.
The key advantage of a biomarker-guided approach is not that it produces one perfect treatment sequence. It identifies choices that would otherwise be missed and helps avoid therapies unlikely to fit the tumor’s biology. Because metastatic prostate cancer evolves under treatment pressure, reassessment at major transitions is often as important as the original molecular profile.
References
- Advanced and metastatic prostate cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up 2026 (Guideline)
- Systemic Therapy in Patients with Metastatic Castration-Resistant Prostate Cancer: ASCO Living Guideline, Version 2026.1.4. 2026 (Guideline)
- Germline and Somatic Genomic Testing for Metastatic Prostate Cancer: ASCO Guideline 2025 (Guideline)
- State of the Art: Personalizing Treatment for Patients With Metastatic Castration-Resistant Prostate Cancer. 2025 (Review)
- Circulating Biomarkers Predictive of Treatment Response in Patients with Hormone-sensitive or Castration-resistant Metastatic Prostate Cancer: A Systematic Review 2024 (Systematic Review)
- FDA approves lutetium Lu 177 vipivotide tetraxetan with androgen receptor pathway inhibitor therapy for metastatic androgen pathway modulation-naïve or -sensitive prostate cancer 2026
Disclaimer
This article provides general education about biomarkers used in metastatic prostate cancer and does not replace oncology care or current prescribing information. Treatment eligibility changes as evidence, drug approvals, and guidelines evolve, and every genomic result must be interpreted in the context of the exact gene, variant, specimen quality, disease state, prior therapies, and patient health. People with metastatic prostate cancer should review biomarker testing and treatment sequencing with a qualified oncology team and genetics professional when hereditary findings are present.