A microsatellite instability (MSI) test evaluates whether a tumor has accumulated abnormal length changes in short repetitive DNA sequences because the DNA mismatch repair system is not working properly. The result is commonly reported as MSI-high (MSI-H), microsatellite stable (MSS), or sometimes MSI-low, depending on the method. MSI-H can be important for two different reasons: it may identify a tumor that could respond to immune checkpoint therapy, and it can serve as a screening clue for Lynch syndrome. Those meanings should not be confused. Many MSI-H cancers are caused by acquired tumor changes rather than an inherited mismatch repair gene mutation, especially colorectal and endometrial cancers with MLH1 promoter hypermethylation. Conversely, some Lynch syndrome tumors can produce borderline or discordant results. Correct interpretation combines MSI with mismatch repair immunohistochemistry, tumor type, MLH1 methylation when relevant, germline testing, and the clinical setting.
- MSI-H means the tumor shows instability at enough microsatellite markers to meet the assay’s high-instability threshold and usually reflects deficient mismatch repair.
- MSS means the tested microsatellites are stable; it lowers the likelihood of mismatch repair deficiency but does not rule out every hereditary cancer syndrome.
- MSI-H is a tumor biomarker, not a diagnosis of Lynch syndrome; sporadic tumors can also be MSI-H.
- MSI-H or dMMR can predict benefit from immune checkpoint inhibitors in several cancer types and treatment settings.
- When MSI-H suggests Lynch syndrome, follow-up may include MMR immunohistochemistry, MLH1 promoter methylation, and germline testing rather than assuming the result is inherited.
Table of Contents
- What Microsatellites and Mismatch Repair Are
- How MSI Testing Is Performed
- What MSI-H, MSS, and MSI-Low Mean
- MSI and Lynch Syndrome
- MSI and Cancer Treatment
- Discordant and Borderline Results
- Practical Next Steps
What Microsatellites and Mismatch Repair Are
Microsatellites are short stretches of DNA in which one or a few bases repeat many times. These repetitive regions are especially prone to small copying errors when cells divide. A healthy mismatch repair (MMR) system corrects many of those errors.
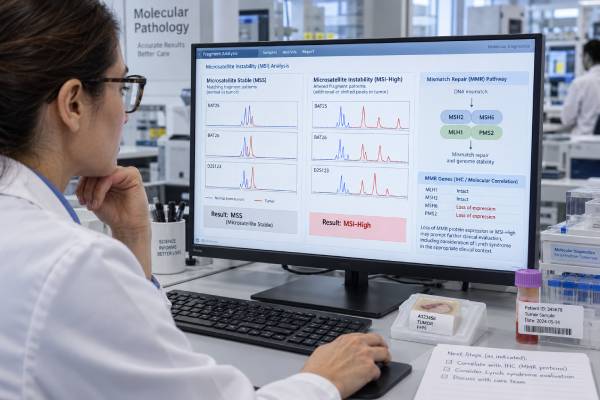
The core MMR proteins commonly assessed in cancer are MLH1, PMS2, MSH2, and MSH6. MSH2 and MSH6 help recognize mismatches, while MLH1 and PMS2 help coordinate the repair process. When the pathway is disabled, insertion and deletion errors accumulate at microsatellites, causing their lengths to become unstable.
A tumor with widespread instability is described as MSI-high. This molecular phenotype often corresponds to deficient mismatch repair, shortened to dMMR. The two terms are closely related but arise from different tests. MSI measures DNA instability. MMR immunohistochemistry measures whether the relevant repair proteins are expressed in tumor-cell nuclei.
This distinction is useful because the tests can complement one another. If IHC shows loss of MSH2 and MSH6, the pattern suggests an MSH2-pathway defect. MSI testing tells whether that protein loss is producing the expected functional instability. If the results disagree, repeat or alternative testing may be needed.
How MSI Testing Is Performed
MSI can be assessed with PCR-based testing or next-generation sequencing (NGS). The optimal method depends partly on tumor type and laboratory validation.
PCR-based MSI testing
PCR assays amplify selected microsatellite markers from tumor DNA. Many methods compare tumor DNA with normal DNA from the same patient, although mononucleotide panels can sometimes work without a matched normal sample. The laboratory determines how many loci show abnormal length shifts.
If enough markers are unstable, the tumor is classified as MSI-H. If none or very few are unstable, it is classified as MSS or, in some older systems, MSI-low. Cutoffs depend on the panel.
NGS-based MSI testing
Large tumor-sequencing panels can estimate MSI by examining many microsatellite loci across the genome. NGS is efficient because the same test can also identify mutations, copy-number changes, fusions, tumor mutational burden, and other biomarkers.
NGS-derived MSI calls are assay-specific. A validated NGS result is useful, but a numerical MSI score from one platform should not be compared directly with another platform’s cutoff.
Immunohistochemistry is related but different
MMR IHC stains for MLH1, PMS2, MSH2, and MSH6. Normal cells on the slide act as internal controls. Loss of nuclear staining in tumor cells, with retained staining in normal cells, supports MMR deficiency.
For colorectal cancer, PCR, NGS, and MMR IHC are all accepted approaches in appropriate settings. For endometrial cancer, MMR IHC is particularly useful because isolated protein-loss patterns can identify which gene needs further evaluation and because some endometrial tumors can be difficult for certain MSI assays.
No special patient preparation is needed for MSI testing itself. It is usually performed on tissue already obtained for diagnosis or surgery.
What MSI-H, MSS, and MSI-Low Mean
MSI-high
MSI-H means instability exceeds the laboratory’s validated high threshold. In many colorectal, endometrial, gastric, and other cancers, MSI-H strongly suggests a biologically meaningful defect in DNA mismatch repair.
The result can have both hereditary and treatment implications. It may prompt a Lynch syndrome workup, and in advanced cancer it may identify sensitivity to immune checkpoint blockade.
MSI-H does not indicate cancer stage, tumor size, or whether the disease has spread. It describes a molecular phenotype.
Microsatellite stable
MSS means the tested microsatellite markers did not show significant instability. Most cancers are MSS. An MSS result generally argues against classic dMMR but does not rule out all inherited cancer risk.
A patient can have a hereditary syndrome unrelated to MMR, such as familial adenomatous polyposis or a BRCA-associated syndrome, and still have an MSS tumor. Rare Lynch-associated tumors may also produce discordant results because of tumor type, particular gene defects, technical limitations, or low tumor content.
MSI-low
MSI-low is an older intermediate category used by some PCR systems when a small fraction of markers is unstable. In most routine clinical decisions, MSI-low is treated more like MSS than MSI-H. It should not automatically be used to diagnose dMMR or select immunotherapy.
If an MSI-low result conflicts with abnormal MMR IHC or a strong hereditary history, the discrepancy deserves review rather than casual dismissal.
MSI and Lynch Syndrome
Lynch syndrome is caused by an inherited pathogenic variant in MLH1, MSH2, MSH6, PMS2, or by certain EPCAM deletions that silence MSH2. People with Lynch syndrome inherit one altered copy of an MMR gene; tumor formation often follows loss of the remaining functional copy.
That mechanism frequently produces dMMR and MSI-H, which is why tumor screening is effective for finding patients who may have Lynch syndrome.
MSI-H does not equal Lynch syndrome
The most common reason for this misconception is sporadic MLH1 promoter hypermethylation. In many colorectal and endometrial cancers, MLH1 is turned off by an acquired methylation event in the tumor. MLH1 and PMS2 protein staining is lost, and the tumor becomes MSI-H, but the patient does not necessarily carry an inherited MLH1 mutation.
When a colorectal tumor shows MLH1/PMS2 loss, MLH1 promoter methylation and/or BRAF V600E testing can help distinguish a likely sporadic pathway from a hereditary one. In endometrial cancer, MLH1 methylation testing is used, but BRAF does not have the same triage role.
Loss of MSH2/MSH6, isolated MSH6 loss, or isolated PMS2 loss is generally more suspicious for Lynch syndrome and usually leads to germline evaluation after clinical review.
Double-somatic MMR defects
Some tumors that look exactly like Lynch syndrome by MSI and IHC are caused by two acquired somatic hits in an MMR gene rather than an inherited mutation. Tumor sequencing can identify this explanation in some patients whose germline testing is negative.
This matters for relatives. A confirmed germline pathogenic variant may justify cascade testing of family members, while a clearly double-somatic tumor generally does not create the same inherited risk.
Germline testing confirms inherited risk
MSI is a screening or tumor-characterization test. Germline testing from blood or another non-tumor specimen is what determines whether a pathogenic Lynch syndrome variant is inherited. A VUS in an MMR gene does not confirm Lynch syndrome.
MSI and Cancer Treatment
MSI-H/dMMR tumors often contain many mutations and abnormal proteins that the immune system can recognize. This makes the phenotype an important predictive biomarker for immune checkpoint inhibitors.
Checkpoint therapy has established roles in MSI-H/dMMR colorectal cancer, endometrial cancer, gastric and gastroesophageal cancer, small-bowel cancer, and other advanced solid tumors depending on stage, prior treatment, regulatory indication, and other biomarkers.
The precise treatment context matters. A positive MSI-H result does not mean every patient should immediately receive immunotherapy. Localized cancers may be cured with surgery, and some stages have different standard approaches. In metastatic colorectal cancer, dMMR/MSI-H status can strongly influence first-line systemic therapy. In other cancers, checkpoint blockade may be used in later lines or as part of a disease-specific regimen.
MSI in colon cancer prognosis
In localized colorectal cancer, MSI-H can also provide prognostic information. Stage II MSI-H colon cancers often have a relatively favorable prognosis and may derive limited benefit from fluoropyrimidine-only adjuvant chemotherapy compared with MSS tumors. However, high-risk pathologic features, stage III disease, age, comorbidities, and evolving immunotherapy data require individualized decisions.
Treatment biomarker versus hereditary marker
The same MSI-H result can trigger two parallel actions: oncology may use it for therapy selection, while genetics may evaluate whether it reflects Lynch syndrome. One action should not replace the other.
A patient with sporadic MLH1-methylated MSI-H cancer may still benefit from immunotherapy in an appropriate setting even though the tumor is not hereditary. Conversely, a Lynch syndrome carrier’s tumor should be tested rather than assumed to be MSI-H solely because of the germline diagnosis.
Discordant and Borderline Results
MSI and MMR IHC agree in most classic cases, but discordance occurs. Possible reasons include technical error, poor fixation, low tumor content, unusual MMR variants that preserve protein staining, heterogeneous protein loss, treatment effect, or tumor-type differences.
An MSI-H/IHC-intact tumor may contain a missense MMR mutation that produces an antigenically detectable but nonfunctional protein. It can also reflect an NGS or PCR false-positive call. Review of the raw data, pathology, and sequencing can clarify the result.
An MSS/dMMR tumor can occur when the tissue type develops relatively few detectable microsatellite shifts, when the particular MMR defect creates a weaker MSI phenotype, or when the assay panel is not optimized for that cancer. MSH6-associated tumors are one setting in which lower-level instability can occur.
Borderline tumor content is another issue. Normal cells dilute the abnormal DNA signal, potentially masking instability. Macrodissection of tumor-rich areas or repeat testing on a different block can improve sensitivity.
A result should be repeated or confirmed with an orthogonal method when it is internally inconsistent and the answer would change treatment or hereditary counseling.
Practical Next Steps
A useful way to interpret an MSI result is to identify its purpose.
If the purpose is immunotherapy selection, confirm that the assay is validated for the tumor type and treatment setting and review MMR IHC, stage, prior therapy, and other biomarkers.
If the purpose is Lynch syndrome screening, review the MMR IHC pattern. MLH1/PMS2 loss usually leads to MLH1 methylation testing and colorectal-specific BRAF triage where appropriate. MSH2/MSH6 loss, isolated MSH6 loss, or isolated PMS2 loss generally prompts germline genetics evaluation.
If the patient already has a germline Lynch syndrome diagnosis, MSI can characterize the tumor but does not replace gene-specific surveillance for future cancers.
Helpful questions for the pathology or oncology team include:
- Was MSI tested by PCR or NGS, and what was the validated cutoff?
- Was MMR immunohistochemistry also performed?
- If MLH1/PMS2 were lost, was MLH1 promoter methylation assessed?
- Is germline testing indicated based on the tumor pattern and family history?
- Does the tumor’s MSI status create a treatment option at the current stage?
- Are the MSI and IHC results concordant?
MSI is most powerful when it is treated as a bridge between pathology, oncology, and hereditary-risk assessment rather than as a stand-alone label.
Practical result combinations
A colorectal cancer that is MSI-H and shows MLH1/PMS2 loss on IHC still needs a cause assigned. If MLH1 promoter methylation is present and BRAF V600E is also detected, a sporadic pathway becomes much more likely. The MSI-H result can still matter for treatment, but the family may not have Lynch syndrome. In contrast, an MSI-H tumor with loss of MSH2/MSH6 and a pathogenic germline MSH2 variant supports both an immunotherapy-relevant phenotype and an inherited cancer predisposition.
Another scenario is an endometrial cancer with intact MMR IHC but an NGS panel that calls MSI-H. The result should be checked for tumor purity, assay quality, and other genomic features. Neither test should be casually discarded. Some tumors contain functional defects despite retained protein expression, while occasional NGS calls can be false positive. Orthogonal confirmation is especially important when the result will determine major treatment or hereditary decisions.
Why tumor type affects the preferred test
MMR biology is shared across cancers, but assay performance is not identical in every tumor type. Colorectal cancer has the deepest evidence base for both MSI and IHC. Endometrial cancers can show unusual patterns and may be better characterized initially with IHC in many laboratories. For less common tumors, the best method depends on validation data for that cancer type and platform.
This matters for tissue-agnostic treatment claims. A laboratory should not simply apply a colorectal-validated MSI cutoff to every tumor without evidence that the assay performs appropriately. The pathology report or test documentation should state the validated specimen types and tumor indications.
MSI is not the same as tumor mutational burden
MSI-H tumors often have high tumor mutational burden, but the biomarkers are not interchangeable. A cancer can have high tumor mutational burden for reasons unrelated to mismatch repair, and an MSI test directly measures microsatellite instability. Professional guidelines do not recommend using tumor mutational burden as a surrogate for MMR deficiency when a validated MMR or MSI assay is available.
For patients, the practical takeaway is to keep the exact wording of the result. “MSI-H,” “dMMR,” and “TMB-high” are separate laboratory findings. They may overlap and all can be clinically important, but they should not be collapsed into one label.
For pathology records, the exact specimen also matters. A primary tumor and a metastasis usually share the core MMR phenotype, but heterogeneous or treatment-selected changes can occur. If an older result is being used to make a new systemic-treatment decision years later, clinicians may review whether the original specimen and assay remain adequate or whether repeat testing on a more recent sample would add useful information.
When available tissue is very limited, the pathology team may prioritize a test that answers several questions at once, but preserving material for confirmatory testing remains important if the initial MSI result is unexpected or borderline.
References
- Mismatch Repair and Microsatellite Instability Testing for Immune Checkpoint Inhibitor Therapy: Guideline From the College of American Pathologists in Collaboration With the Association for Molecular Pathology and Fight Colorectal Cancer 2022 (Guideline)
- Mismatch Repair and Microsatellite Instability Testing for Immune Checkpoint Inhibitor Therapy: ASCO Endorsement of College of American Pathologists Guideline 2023 (Guideline)
- Testing for deficient mismatch repair and microsatellite instability : A focused update 2023 (Review)
- The guidelines for clinical practice for carriers of germline mutations in the Lynch syndrome predisposition genes MLH1, MSH2, MSH6, PMS2 and large deletions of EPCAM (4.2024) 2024 (Guideline)
- Cancer risks in Lynch syndrome carriers: a systematic review and meta-analysis 2026 (Systematic Review)
- Clinical Molecular Immunohistochemistry Mismatch Repair Mutations in Lynch Syndrome in Patients Under 50 Years: A Systematic Review 2025 (Systematic Review)
Disclaimer
MSI is a tumor biomarker and should be interpreted with MMR immunohistochemistry, tumor type, pathology, family history, and the treatment setting. This article is educational and does not replace cancer treatment advice or hereditary-risk assessment from oncology, pathology, gastroenterology, or genetics professionals.