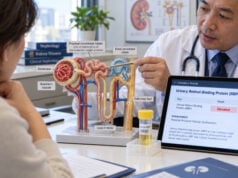
A spot urine albumin test checks how much albumin is present in a single urine sample. Albumin is a major blood protein that healthy kidneys largely keep out of urine, so increased urinary albumin can be an early sign of kidney filter damage. In practice, the most useful spot test is usually the urine albumin-to-creatinine ratio (uACR), because it adjusts the albumin result for how concentrated or dilute the urine is. A random sample is convenient for screening, while a first-morning sample is often preferred when an abnormal result needs confirmation. Albuminuria can appear before the estimated glomerular filtration rate (eGFR) falls, making it especially valuable for detecting early chronic kidney disease in people with diabetes, high blood pressure, cardiovascular disease, or other kidney risks. One high result does not always mean chronic disease, because exercise, infection, fever, marked hyperglycemia, and other temporary factors can raise albumin excretion.
- A spot uACR below 30 mg/g is generally normal to mildly increased; 30–300 mg/g is moderately increased, and above 300 mg/g is severely increased.
- A first-morning sample is useful for confirmation because it reduces variation from posture, activity, and hydration.
- Albuminuria can be an early CKD marker even when eGFR is still normal.
- Temporary increases can occur with exercise, fever, infection, marked hyperglycemia, heart failure, menstruation, or severe hypertension.
- Persistent albuminuria, rapidly rising values, blood in the urine, swelling, or falling eGFR should prompt medical follow-up.
Table of Contents
- What a Spot Urine Albumin Test Measures
- Why uACR Is Usually Preferred
- Normal and High Albumin Results
- Causes of High Urine Albumin
- How to Prepare and Avoid False-High Results
- What Happens After an Abnormal Result
- Albuminuria, CKD Risk, and Monitoring
What a Spot Urine Albumin Test Measures
Albumin is produced by the liver and circulates in blood, where it helps maintain fluid balance and carries hormones, fatty acids, medications, and other molecules. The glomeruli—the kidney’s microscopic filtering units—normally prevent most albumin from entering urine.
When the glomerular filtration barrier becomes more permeable, albumin can leak into urine. The increase may be small at first and invisible on a standard urine protein dipstick. A laboratory albumin assay is more sensitive and can detect lower levels that matter for chronic kidney disease risk.
A spot urine albumin test can be ordered as albumin concentration alone, but concentration is strongly affected by hydration. A very dilute urine can make albumin concentration look deceptively low, while a concentrated urine can make it look high. That is why clinicians usually prefer a ratio that includes urine creatinine.
The test is particularly important in people with diabetes because albuminuria can be one of the earliest clinically detectable kidney abnormalities. It is also useful in hypertension, cardiovascular disease, known CKD, and other conditions associated with glomerular damage.
Albumin testing does not replace eGFR. These markers describe different dimensions of kidney health: eGFR estimates filtration capacity, while albuminuria reflects kidney damage and barrier dysfunction. A person can have a normal eGFR with significant albuminuria, or a reduced eGFR with little albuminuria.
Why uACR Is Usually Preferred
The urine albumin-to-creatinine ratio divides urine albumin by urine creatinine in the same specimen. It is usually reported as milligrams of albumin per gram of creatinine (mg/g) or milligrams per millimole (mg/mmol).
Creatinine is released from muscle metabolism at a relatively steady rate over the day. Using it as a denominator partly corrects for whether the sample is concentrated or dilute. The ratio is not perfect—creatinine excretion varies with muscle mass, age, sex, diet, and body size—but it is much more useful than albumin concentration alone for most outpatient testing.
A random spot uACR is convenient and is recommended for routine screening in many settings. For confirmation, a first-morning void is often better because overnight collection reduces variation from posture, physical activity, and short-term hydration.
A spot urine albumin test and a 24-hour urine collection are not competing methods so much as tools for different situations. Timed collections can directly measure albumin excretion per day, but they are more burdensome and vulnerable to missed or extra urine collections. For most screening and monitoring, uACR is preferred.
The older term “microalbumin test” refers to sensitive measurement of small but abnormal amounts of albumin, not to a different smaller form of albumin. Current terminology favors “moderately increased albuminuria” rather than “microalbuminuria.”
Normal and High Albumin Results
Albuminuria is categorized by uACR because risk rises progressively as the ratio increases.
| Category | uACR | Meaning |
|---|---|---|
| A1 | <30 mg/g (<3 mg/mmol) | Normal to mildly increased |
| A2 | 30–300 mg/g (3–30 mg/mmol) | Moderately increased albuminuria |
| A3 | >300 mg/g (>30 mg/mmol) | Severely increased albuminuria |
These categories help stage CKD risk, but uACR is a continuous marker. A value of 25 mg/g and one of 5 mg/g both fall in A1, yet they do not necessarily carry identical long-term risk. Likewise, a person moving from 700 mg/g to 350 mg/g has improved substantially even though both results remain in A3.
A single uACR of 30 mg/g or higher does not automatically establish chronic kidney disease. Albumin excretion varies from day to day, and a temporary trigger can cause an abnormal value. In many situations, clinicians confirm persistent albuminuria with repeat measurements over several months. For people with diabetes, guidance commonly recommends that at least two of three samples collected over about three to six months be abnormal before classifying persistent moderately or severely increased albuminuria.
Very high albumin levels can approach nephrotic ranges. When there is massive albumin loss, low blood albumin, and edema, clinicians evaluate for nephrotic-range proteinuria and nephrotic syndrome rather than treating the result as routine early CKD screening.
Causes of High Urine Albumin
Persistent albuminuria most often reflects glomerular kidney damage, but the cause varies.
Diabetes is a major cause. Chronic hyperglycemia, altered intraglomerular pressure, inflammation, and structural changes in the glomerulus can lead to increasing albumin leakage. This is why uACR is part of routine kidney assessment in diabetes.
High blood pressure can damage small kidney vessels and glomeruli, while kidney disease can also worsen hypertension. Persistent albuminuria in a person with hypertension increases concern for kidney and cardiovascular risk.
Primary glomerular diseases such as focal segmental glomerulosclerosis, membranous nephropathy, IgA nephropathy, and minimal change disease can produce albuminuria ranging from modest to very heavy.
Systemic autoimmune diseases such as lupus can inflame the glomeruli. Albuminuria accompanied by blood in urine, cellular casts, low complement, or systemic symptoms may point toward inflammatory glomerular disease rather than uncomplicated diabetic or hypertensive CKD.
Other causes include heart failure, severe obesity-related glomerular stress, some infections, pregnancy-related kidney disorders, hereditary kidney diseases, and medication-related kidney injury.
Not all high albumin results represent persistent structural damage. Temporary albuminuria can occur during febrile illness, after vigorous exercise, during a urinary infection, with marked hyperglycemia, severe uncontrolled blood pressure, or acute heart failure. Menstrual contamination can also affect a urine specimen.
How to Prepare and Avoid False-High Results
Most spot urine albumin tests require no fasting and no special diet. The biggest opportunity to improve accuracy is to collect the sample under stable conditions.
When possible, avoid strenuous exercise for about 24 hours before a confirmatory test because exercise can transiently raise urinary albumin. If you have a fever, active urinary infection, major acute illness, or severe hyperglycemia, the clinician may prefer to repeat the test after the temporary problem has resolved.
For a first-morning sample:
- Follow the laboratory’s instructions about whether to empty the bladder before sleep.
- Collect the first urine after waking, before prolonged walking or exercise.
- Use a clean container and, when instructed, collect a midstream specimen.
- Avoid contaminating the sample with menstrual blood or stool.
- Deliver or refrigerate the sample according to the laboratory’s instructions.
Hydration should be normal rather than deliberately excessive or restricted. One advantage of uACR is that it corrects partly for urine concentration, but extreme dilution or concentration can still add variability.
If serial results are being compared, consistency helps. Testing at a similar time of day and under similar activity conditions can make trends easier to interpret.
What Happens After an Abnormal Result
The first step is usually confirmation rather than immediate diagnosis. A clinician will consider the absolute uACR, previous values, eGFR, medical history, current illness, medications, and whether there are symptoms or other urine abnormalities.
Common follow-up includes:
- Repeat uACR, often with a first-morning sample
- Serum creatinine and eGFR
- Blood pressure measurement
- Urinalysis with microscopy
- Blood glucose or HbA1c if diabetes is relevant
- Serum electrolytes
- Additional testing for systemic or glomerular disease when indicated
If total urinary protein seems much higher than the albumin result would suggest, the clinician may order a spot urine protein test or studies for non-albumin proteins. This mismatch can occur with tubular proteinuria or monoclonal light chains.
A rapidly increasing uACR, active urine sediment, nephrotic-range protein, or falling eGFR may lead to nephrology referral and sometimes kidney biopsy. In contrast, stable moderately increased albuminuria in a person with long-standing diabetes and typical features may be managed initially with risk-factor control and guideline-directed kidney-protective therapy.
The clinician may also compare albuminuria with eGFR. CKD classification combines both because prognosis is more accurate when filtration and albumin leakage are considered together.
Albuminuria, CKD Risk, and Monitoring
Persistent albuminuria matters even when a person feels well. Higher uACR is associated with greater risk of CKD progression, cardiovascular disease, and mortality across a broad range of eGFR values.
For people with diabetes, current guidance recommends periodic uACR and eGFR testing. Those with established CKD may be monitored from about once yearly to several times per year depending on CKD stage, albuminuria, treatment changes, and clinical stability.
Changes over time can be clinically meaningful. A substantial fall in albuminuria after treatment often indicates reduced kidney stress, while a large sustained increase may signal progression, poor blood pressure or glucose control, medication issues, or a superimposed kidney problem. Because biological variability is high, clinicians focus on repeated trends rather than minor fluctuations.
Treatment depends on the cause and patient profile. It may include improved blood pressure control, glucose management, renin-angiotensin system blockade, sodium-glucose cotransporter-2 inhibitors, mineralocorticoid receptor antagonists in selected patients, smoking cessation, weight management, and other cardiovascular risk reduction. These therapies are chosen based on the whole clinical picture rather than the uACR alone.
Seek prompt evaluation if high albumin is accompanied by rapidly worsening swelling, markedly reduced urine output, shortness of breath, visible blood in the urine, very high blood pressure with symptoms, or a rapid decline in kidney function. For most asymptomatic abnormal screening results, the next best step is a planned repeat test and clinical review.
A spot urine albumin test is valuable because it can reveal kidney damage at a stage when intervention may still meaningfully reduce future risk. The result is most useful when it is measured as uACR, confirmed when appropriate, and followed as a trend rather than treated as a single isolated number.
Why repeat testing is built into albuminuria diagnosis
Urinary albumin has substantial biological variation even when kidney disease is stable. Hydration, blood pressure, glucose levels, exercise, and short-term hemodynamic changes can all move the result. For that reason, clinicians do not usually react to a small change from one visit to the next as if it represents true progression.
A better approach is to look for a sustained pattern. Repeated values that stay in A2 or A3, or a clear multi-fold rise from a previous baseline, are more meaningful than a single borderline measurement. When a high result is found during an obvious temporary stressor, repeating the test after that stressor resolves can prevent misclassification.
The same principle applies to treatment response. A single lower uACR after starting therapy is encouraging but not definitive. Several measurements over time provide stronger evidence that albuminuria has genuinely fallen.
Why creatinine correction is helpful but not perfect
Using creatinine in the denominator makes a spot test practical, but the correction assumes that urine creatinine excretion is reasonably stable. In reality, creatinine generation varies with muscle mass. A very muscular person may have more creatinine in urine, lowering the uACR for a given amount of albumin. A frail person with low muscle mass may have less urine creatinine, making the ratio relatively higher.
These effects usually do not outweigh the convenience and usefulness of uACR, but they matter when a result seems inconsistent with the rest of the clinical picture. In unusual cases, repeat first-morning testing or a timed collection can help clarify the amount of albumin being excreted.
Using uACR together with eGFR
The strongest interpretation comes from looking at both kidney dimensions at once. Someone with eGFR 80 mL/min/1.73 m² and uACR 450 mg/g has preserved filtration but substantial kidney damage and elevated future risk. Someone with eGFR 45 and uACR 8 mg/g has reduced filtration but little albumin leakage. Both may have CKD, but the likely causes, risk patterns, and monitoring needs can differ.
The combination also helps explain why “normal creatinine” does not rule out early kidney disease. Serum creatinine may stay within a population reference range until a meaningful amount of filtration capacity has been lost, while albumin leakage can appear earlier.
For patients, a useful way to follow results is to record the date, uACR, eGFR, blood pressure, and any temporary factors such as infection or strenuous exercise. This makes the pattern easier to discuss at follow-up visits and reduces the temptation to focus on one isolated number.
Age and muscle mass can subtly influence interpretation because creatinine appears in the denominator. Older adults with low muscle mass may have lower urine creatinine excretion, which can push uACR upward for the same absolute albumin excretion. This does not make the test unreliable, but it is one reason clinicians interpret borderline results in context and repeat them when needed.
Pregnancy also requires a distinct clinical framework. Albuminuria or proteinuria can predate pregnancy in someone with CKD, or it can develop with pregnancy complications. New hypertension and proteinuria during pregnancy should be assessed using obstetric guidance rather than routine outpatient CKD screening rules alone.
For people without symptoms, a high uACR is often a risk marker rather than a cause of discomfort. Albuminuria itself does not usually hurt or change urine color. This is why screening matters: by the time edema or other symptoms appear, protein loss may already be substantial. Detecting a persistent rise earlier creates an opportunity to address blood pressure, diabetes, smoking, medication choices, and other modifiable risks.
References
- KDIGO 2024 CKD Guideline 2024 (Guideline)
- Urine Albumin Measurements in Clinical Diagnostics 2024 (Review)
- Developments in albuminuria testing: A key biomarker for detection, prognosis and surveillance of kidney and cardiovascular disease-A practical update for clinicians 2025 (Review)
- Measuring albuminuria or proteinuria: does one answer fit all? 2023 (Review)
- Recommendations for pre-analytical urine sample handling to allow optimal assessment of albuminuria and proteinuria. 2026 (Review)
- 11. Chronic Kidney Disease and Risk Management: Standards of Care in Diabetes—2026 2026 (Guideline)
Disclaimer
A high spot urine albumin result can have temporary or persistent causes and should not be used alone to diagnose a specific kidney disease. Repeat testing and interpretation with eGFR, blood pressure, urinalysis, diabetes status, and medical history are often necessary. Seek medical care promptly for severe swelling, breathing difficulty, reduced urine output, or other acute symptoms.