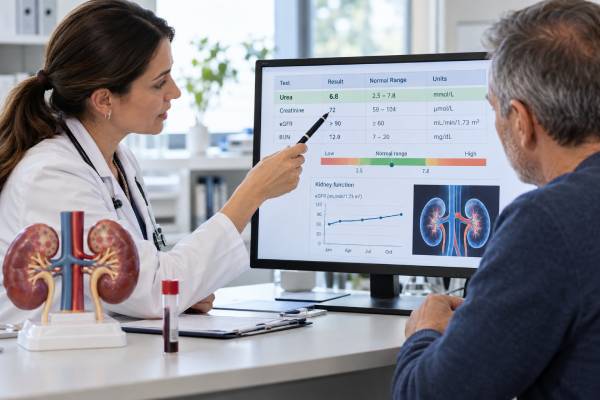
A urea blood test measures a nitrogen-containing waste product made when the liver processes amino acids from protein. Urea travels in the bloodstream to the kidneys, where it is filtered and partly reabsorbed before leaving the body in urine. Because kidney filtration affects urea clearance, blood urea often rises when kidney function falls. However, hydration, protein intake, gastrointestinal bleeding, liver function, medicines, and tissue breakdown can also change the result.
Laboratories may report urea itself or blood urea nitrogen (BUN), which measures only the nitrogen portion of the urea molecule. These are related but use different numbers and units. A common adult BUN range is about 7–20 mg/dL, which corresponds roughly to urea of 15–43 mg/dL or 2.5–7.1 mmol/L. The laboratory’s own reference interval should always be used. Urea is most informative when interpreted with creatinine, estimated glomerular filtration rate (eGFR), electrolytes, urine albumin, symptoms, and previous results rather than as a stand-alone kidney test.
- Urea is produced in the liver from protein metabolism and removed mainly through the kidneys.
- Many U.S. laboratories report BUN rather than total urea; about 7–20 mg/dL BUN is a common adult range.
- High urea can result from reduced kidney filtration, dehydration, gastrointestinal bleeding, high protein intake, or increased tissue breakdown.
- Low urea can occur with low protein intake, severe liver dysfunction, overhydration, or other states of reduced urea production.
- Urea alone cannot diagnose kidney disease or determine whether reduced kidney function is acute or chronic.
Table of Contents
- What the Urea Blood Test Measures
- Urea Normal Range and BUN Conversion
- Causes of High Urea Levels
- Causes of Low Urea Levels
- Urea, Creatinine, and Kidney Function
- Uremia and Dialysis Monitoring
- How to Interpret a Urea Result
What the Urea Blood Test Measures
Urea is the main nitrogen-containing end product of human protein metabolism. When dietary protein and body proteins are broken down, amino groups are converted to ammonia. Because ammonia is toxic, the liver converts much of it into urea through the urea cycle. Urea is then released into the blood.
The kidneys filter urea freely at the glomerulus. Unlike creatinine, however, a substantial amount of filtered urea can move back into the bloodstream through the kidney tubules. The amount reabsorbed changes with urine flow and hydration. During dehydration or reduced kidney blood flow, the kidneys conserve water and more urea can be reabsorbed, causing blood urea to rise disproportionately.
This physiology explains why urea is a useful but imperfect kidney marker. A high level may reflect reduced filtration, but it can also reflect increased urea production or increased tubular reabsorption. A normal level does not guarantee normal kidneys, especially in someone with low protein intake or reduced urea production.
In the United States, the test is commonly reported as blood urea nitrogen. BUN measures only the nitrogen atoms within urea rather than the mass of the entire urea molecule. Many laboratories outside the United States report total urea in mmol/L. Both measurements describe the same metabolic waste product, but the numbers are not directly interchangeable without conversion.
Urea is often part of a renal function panel, basic metabolic panel, or comprehensive metabolic panel. In those settings, it is read alongside creatinine, sodium, potassium, bicarbonate, and glucose. That context is more valuable than looking at urea alone.
Urea Normal Range and BUN Conversion
Reference ranges vary by laboratory, age, method, hydration, and local reporting convention. A commonly used adult BUN range is approximately 7–20 mg/dL. Expressed as total urea, that is roughly 15–43 mg/dL or 2.5–7.1 mmol/L.
Some laboratories use slightly wider intervals. Older adults may have somewhat higher BUN values, while children and pregnant people can have different expected ranges. A result should therefore be classified as high or low using the specific reference interval printed on the laboratory report.
The conversions are useful when comparing reports from different systems:
| Reported measurement | Approximate conversion |
|---|---|
| BUN in mg/dL to urea in mg/dL | Multiply BUN by 2.14 |
| Urea in mg/dL to BUN in mg/dL | Multiply urea by 0.467 |
| BUN in mg/dL to urea in mmol/L | Multiply BUN by 0.357 |
| Urea in mmol/L to BUN in mg/dL | Multiply urea by about 2.8 |
For example, a BUN of 20 mg/dL corresponds to approximately 43 mg/dL total urea or 7.1 mmol/L urea. This does not change the biology; it only changes how the laboratory expresses the concentration.
The degree of elevation does not map perfectly to a specific stage of kidney disease. A dehydrated person with otherwise normal kidneys can have a clearly high BUN, while someone with significant CKD and low protein intake may have a less dramatic rise. The eGFR is more directly tied to filtration assessment and CKD staging.
Causes of High Urea Levels
High blood urea, often called azotemia when nitrogenous waste products accumulate, has several major mechanisms: reduced kidney clearance, increased urea production, or increased tubular reabsorption.
Reduced kidney filtration
Both acute kidney injury (AKI) and CKD can raise urea. In AKI, the increase may develop over hours to days after dehydration, infection, low blood pressure, urinary obstruction, kidney inflammation, or exposure to a nephrotoxic medicine. In CKD, urea tends to rise as filtration declines over time, although the relationship varies widely among individuals.
A high urea result with rising creatinine and falling eGFR makes reduced filtration more likely. If urine output has also fallen, the change may require urgent assessment.
Dehydration and reduced kidney blood flow
Dehydration is one of the most common non-structural reasons BUN rises. When blood volume or kidney perfusion falls, tubular flow slows and more urea is reabsorbed. This can produce a larger relative rise in BUN than in creatinine.
Vomiting, diarrhea, fever, poor fluid intake, excessive diuretic effect, bleeding, and severe heart failure can all reduce effective kidney perfusion. These conditions do not all respond to simple fluid intake, so the underlying cause matters.
High protein load and tissue breakdown
A high-protein diet or large protein meal can increase urea production. Severe infection, fever, trauma, burns, corticosteroid exposure, and other catabolic states can also increase breakdown of body proteins and raise urea.
This is particularly relevant in hospitalized or critically ill patients, where a high urea-to-creatinine ratio may reflect catabolism as well as dehydration or kidney dysfunction.
Gastrointestinal bleeding
Blood in the upper gastrointestinal tract is digested as a protein source. Absorbed amino acids are then metabolized by the liver, increasing urea production. This can cause a relatively high BUN-to-creatinine ratio. Recent evidence suggests that the ratio may support, but cannot reliably prove, an upper GI source because its sensitivity and specificity are only moderate.
Black stools, vomiting blood, dizziness, fainting, or unexplained anemia require medical evaluation regardless of the BUN value.
Medicines and other causes
Corticosteroids can increase protein catabolism. Some medicines can reduce kidney perfusion or filtration and raise both BUN and creatinine. Urinary obstruction can also increase nitrogenous waste levels. Because there are many pathways to a high result, medication history and clinical findings are essential.
Causes of Low Urea Levels
Low urea is less commonly used as a kidney warning sign. It usually reflects reduced urea production or dilution rather than unusually strong kidney function.
A low-protein diet can reduce the amount of nitrogen available for urea formation. This can be intentional, but it can also occur with poor appetite, malnutrition, swallowing difficulty, severe illness, or other conditions that reduce protein intake.
Severe liver dysfunction can lower urea because the liver is responsible for converting ammonia into urea. In advanced liver disease, a low BUN may therefore occur even when kidney function is impaired. This is one reason BUN can underestimate the degree of renal dysfunction in some patients with liver failure.
Excess body water or overhydration can dilute urea concentration. The same process may also lower sodium. Pregnancy can be associated with lower BUN because plasma volume expands and GFR increases, although pregnancy-specific laboratory interpretation should be used.
Small or modestly low values are often less urgent than very high values, but the surrounding pattern matters. Low urea plus low albumin, weight loss, and poor intake may raise concern for inadequate nutrition. Low urea with abnormal liver tests and signs of liver dysfunction suggests a different problem.
A low result should not be “corrected” by increasing protein intake without understanding the cause. People with advanced CKD, liver disease, malnutrition, or other complex conditions may need individualized nutrition advice.
Urea, Creatinine, and Kidney Function
Urea and creatinine are both waste markers affected by kidney clearance, but they behave differently. Creatinine is produced largely from muscle metabolism and undergoes relatively little tubular reabsorption. Urea production varies with protein metabolism, and its tubular reabsorption changes with urine flow.
For that reason, creatinine-based eGFR is generally more useful for estimating filtration than urea alone. Urea still adds context. A high BUN with high creatinine can support reduced clearance. A BUN rising much more than creatinine may suggest dehydration, upper GI bleeding, high protein load, or catabolism.
The BUN-to-creatinine ratio is often taught as a clue to “prerenal” versus intrinsic kidney injury. A ratio above about 20:1 in conventional mg/dL units has historically been associated with reduced kidney perfusion. However, current evidence shows that the ratio is not sufficiently accurate to determine AKI cause by itself.
Several factors can distort the ratio. Low muscle mass can lower creatinine and make the ratio look high. Liver disease or low protein intake can lower BUN and make the ratio look low. GI bleeding and corticosteroids can increase BUN without a primary change in GFR. A muscular person may have higher creatinine for non-kidney reasons.
Modern kidney assessment therefore uses multiple measures. Creatinine and eGFR estimate filtration, while urine albumin-creatinine ratio helps detect kidney damage. Cystatin C can improve filtration estimates when creatinine is unreliable. Electrolytes and bicarbonate show complications of reduced kidney function.
Persistent kidney disease is not diagnosed from urea or BUN alone. CKD generally requires an abnormality of kidney structure or function present for at least three months. A one-time high urea result during dehydration may completely normalize when the acute problem resolves.
Uremia and Dialysis Monitoring
Uremia is not simply a high urea number. It is a clinical syndrome caused by the accumulation of multiple retained substances and the metabolic consequences of severe kidney failure. Symptoms can include nausea, loss of appetite, itching, fatigue, cognitive changes, sleep problems, pericarditis, bleeding tendency, or other systemic complications.
Urea contributes to the biochemical picture but is not considered the only uremic toxin. Two people with the same BUN can have very different symptoms and treatment needs. For this reason, there is no single BUN threshold at which every person should start dialysis.
Dialysis decisions are based on the overall clinical situation, including refractory hyperkalemia, severe metabolic acidosis, pulmonary edema or uncontrolled fluid overload, certain toxin exposures, pericarditis, encephalopathy, severe uremic symptoms, and the broader kidney failure trajectory.
Urea does have an important role once a person is receiving hemodialysis. Pre- and post-dialysis BUN measurements are used to calculate measures of dialysis dose such as the urea reduction ratio (URR) and Kt/V. These calculations estimate how effectively a dialysis treatment removes urea from the bloodstream.
Even in dialysis care, urea kinetics are only one part of adequacy. Nutrition, fluid management, blood pressure, potassium, phosphorus, anemia, vascular access, symptoms, and treatment tolerance also matter. A satisfactory urea reduction does not guarantee that every aspect of kidney replacement therapy is optimal.
How to Interpret a Urea Result
First, identify what the report actually measures. “Urea” in mmol/L, total urea in mg/dL, and BUN in mg/dL use different numeric scales. Compare the result only with the reference interval printed for that measurement.
Second, check creatinine and eGFR from the same or nearby blood draw. A high urea with stable creatinine may suggest dehydration, high protein intake, GI bleeding, or catabolism more strongly than progressive filtration loss. High urea plus rising creatinine and falling eGFR raises more concern for reduced kidney clearance.
Third, review recent events. Vomiting, diarrhea, fever, poor fluid intake, heavy protein intake, GI bleeding, corticosteroid treatment, surgery, infection, and acute illness can all affect urea. Previous results help determine whether the change is new or chronic.
Fourth, look at other kidney-related values. Potassium, bicarbonate, sodium, phosphorus, and urine albumin can reveal problems that urea cannot. A person with normal urea can still have dangerous hyperkalemia or significant albuminuria.
Mild isolated abnormalities often lead to repeat testing rather than an immediate diagnosis. More urgent assessment is appropriate when a high urea result is accompanied by rapidly rising creatinine, very low urine output, severe dehydration, black or bloody stools, vomiting blood, confusion, chest pain, severe shortness of breath, marked swelling, or dangerous electrolyte abnormalities.
Preparation for repeat testing is usually simple. Urea or BUN alone generally does not require fasting, but another test drawn at the same time may. Follow the laboratory’s instructions and keep normal hydration unless a clinician has given a fluid restriction. Avoid deliberately drinking excessive water to lower the number. Tell the clinician about recent high-protein meals, protein supplements, corticosteroids, diuretics, and any episode of vomiting, diarrhea, fever, or bleeding because these details can explain a result that otherwise appears to reflect worsening kidney function.
When results change over time, compare measurements made under similar conditions when possible. A BUN that rises from 14 to 28 mg/dL during several days of poor intake may have a different meaning from a gradual rise accompanied by a persistent fall in eGFR. Likewise, a high urea value that quickly normalizes after an acute illness does not by itself establish CKD. Chronic kidney disease requires persistent evidence of reduced kidney function or kidney damage, not one temporary waste-product elevation.
For long-term kidney monitoring, focus on the whole pattern rather than trying to drive urea into a particular number. Blood pressure control, diabetes management, appropriate medications, avoiding unnecessary nephrotoxins, and monitoring eGFR and urine albumin generally matter more for CKD outcomes than an isolated urea value.
The urea blood test is useful because it reflects the interaction between protein metabolism, liver production, hydration, and kidney clearance. That same complexity is why it must be interpreted in context. High or low urea can provide an important clue, but it is rarely the final answer by itself.
References
- Blood urea nitrogen (BUN) test for kidney disease 2026
- Blood urea nitrogen (BUN) test 2026
- Blood Urea Nitrogen-to-Creatinine Ratio to Differentiate Upper From Lower Gastrointestinal Bleeding: A Systematic Review and Meta-Analysis 2026 (Systematic Review and Meta-Analysis)
- The urea-to-creatinine ratio as an emerging biomarker in critical care: a scoping review and meta-analysis 2025 (Review and Meta-Analysis)
- Utility of fractional excretion of urea in acute kidney injury with comparison to fractional excretion of sodium: A systematic review and meta-analysis 2024 (Systematic Review and Meta-Analysis)
- BUN (Blood Urea Nitrogen): MedlinePlus Medical Test 2024
Disclaimer
Urea and BUN results should be interpreted with the laboratory’s reference interval, creatinine, eGFR, symptoms, hydration, diet, medications, and other kidney tests. Do not make major changes to protein intake, fluid intake, or prescription medicines based only on one urea result. Seek urgent medical care for severe dehydration, very low urine output, confusion, vomiting blood or black stools, severe shortness of breath, or rapidly worsening kidney test results.