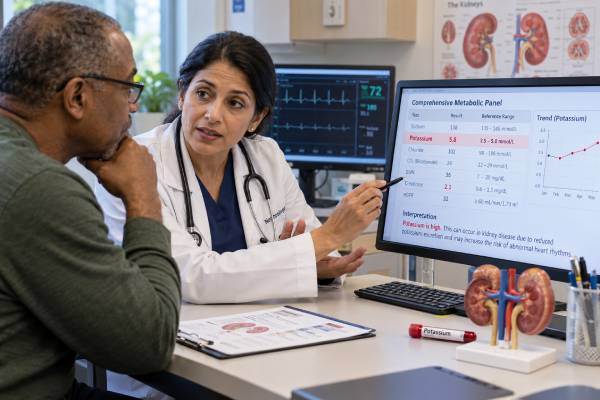
A potassium blood test measures the amount of potassium circulating in the blood. In kidney disease, it is one of the most important safety tests because the kidneys remove much of the body’s excess potassium. When kidney function falls, potassium can accumulate, especially during acute kidney injury (AKI), advanced chronic kidney disease (CKD), or treatment with medicines that reduce potassium excretion. Very high potassium can disrupt the heart’s electrical system and cause dangerous arrhythmias, sometimes before a person feels severely ill.
Low potassium also matters. Diuretics, vomiting, diarrhea, poor intake, magnesium deficiency, and some kidney disorders can lower potassium enough to cause weakness or abnormal heart rhythms. A potassium result should therefore be interpreted in both directions and in context. The exact “normal” range varies by laboratory, but many adult labs use about 3.5–5.0 mmol/L. Unexpected high results should sometimes be repeated because hemolysis during blood collection can falsely raise potassium.
- A common adult potassium reference range is about 3.5–5.0 mmol/L, although the laboratory’s own range should be used.
- Hyperkalemia is often defined as potassium above about 5.0–5.5 mmol/L, with risk increasing as the level rises and when ECG changes are present.
- Potassium around 6.0 mmol/L or higher can require urgent assessment, especially with CKD, weakness, palpitations, chest symptoms, or ECG abnormalities.
- A falsely high result is possible after a difficult or hemolyzed blood draw, so an unexpected value may need rapid confirmation.
- Low potassium below about 3.5 mmol/L can also affect muscles and heart rhythm, particularly when the level is below 3.0 mmol/L or magnesium is low.
Table of Contents
- What the Potassium Blood Test Measures
- Normal, High, and Low Potassium Levels
- Why Kidney Disease Affects Potassium
- Causes of High Potassium in Kidney Disease
- Causes of Low Potassium in Kidney Disease
- Potassium, Heart Risk, and When It Is Urgent
- Diet, Medications, and Follow-Up Testing
What the Potassium Blood Test Measures
Potassium is an electrolyte that helps nerves fire, muscles contract, and heart cells maintain normal electrical activity. About 98% of the body’s potassium is inside cells. Only a small fraction circulates in the blood, which is why relatively small changes in serum potassium can have important effects.
The kidneys maintain potassium balance by adjusting how much potassium is excreted in urine. Aldosterone, a hormone produced by the adrenal glands, is an important part of this system. It signals cells in the distal nephron to exchange sodium for potassium, allowing potassium to leave the body in urine. This process also depends on enough sodium and water reaching the distal nephron. Low blood flow to the kidneys, severe volume depletion, or very low urine output can therefore reduce potassium excretion even when aldosterone is present. The colon also contributes to potassium excretion, particularly in advanced CKD.
Potassium is also controlled by rapid movement between the blood and cells. Insulin and beta-adrenergic activity move potassium into cells after meals. Acidosis, insulin deficiency, and major tissue injury can shift potassium out of cells. These shifts can change the blood potassium level without representing a major change in total-body potassium. This is one reason a potassium result must be interpreted alongside glucose, bicarbonate, acid-base status, recent illness, and medications.
Potassium is commonly included in a renal function panel, basic metabolic panel, or comprehensive metabolic panel. It is often monitored alongside creatinine, eGFR, bicarbonate, sodium, glucose, and other electrolytes because these results help explain why potassium is abnormal.
Serum and plasma potassium are close but not always identical. The laboratory’s reference interval is specific to the specimen and method. Most clinicians focus less on tiny differences within the normal range and more on trends, the degree of abnormality, symptoms, kidney function, and the ECG when hyperkalemia is significant.
Normal, High, and Low Potassium Levels
Many adult laboratories use a normal potassium range near 3.5–5.0 mmol/L, which is numerically the same as mEq/L for potassium. Some laboratories set the upper limit at 5.1 or 5.2 mmol/L.
Definitions of hyperkalemia vary. A practical framework is:
| Potassium level | General interpretation | Typical concern |
|---|---|---|
| 3.5–5.0 mmol/L | Common reference range | Interpret against the laboratory range and trend |
| 5.1–5.5 mmol/L | Mild elevation in many systems | Confirm cause, review medicines and kidney function |
| 5.6–5.9 mmol/L | Moderate hyperkalemia | Prompt clinical review; urgency depends on context and ECG |
| ≥6.0 mmol/L | Potentially severe hyperkalemia | Often requires urgent assessment and repeat/ECG confirmation |
| 3.0–3.4 mmol/L | Mild hypokalemia | Look for losses, medicines, and magnesium deficiency |
| <3.0 mmol/L | Moderate to severe hypokalemia | Greater muscle and arrhythmia risk; prompt correction may be needed |
These categories are only guides. A potassium of 5.8 mmol/L in a stable outpatient with no ECG changes is not identical to 5.8 mmol/L in someone with rapidly worsening AKI, acidosis, and chest symptoms. Likewise, a potassium of 3.2 mmol/L may be more concerning in a person taking digoxin or with significant heart disease.
A single unexpected high result should be checked for pseudohyperkalemia. Potassium can leak from blood cells when the sample is hemolyzed, when a tourniquet is left on too long, after repeated fist clenching, or when the sample is delayed in processing. Very high platelet or white blood cell counts can also cause spurious results in some specimen types. Many laboratory reports flag a visibly or analytically hemolyzed specimen, but a false elevation can still be suspected when the potassium value does not fit the person’s kidney function, medications, symptoms, or prior trend.
When pseudohyperkalemia is possible, repeat collection should be done promptly and with careful technique rather than assuming the first result is harmless. The repeat sample may be drawn without fist pumping and processed quickly. In selected cases, clinicians compare serum and plasma potassium or use a rapidly analyzed whole-blood sample. However, a potentially dangerous result should never be dismissed solely because hemolysis is possible; the urgency of confirmation depends on the potassium level and the person’s clinical condition.
Why Kidney Disease Affects Potassium
Healthy kidneys can increase potassium excretion when dietary intake rises. CKD reduces the number of functioning nephrons, but the remaining nephrons adapt and excrete more potassium per nephron. This compensation explains why many people with moderate CKD still have normal potassium.
Hyperkalemia becomes more likely when kidney function is lower or when another stressor is added. A decline in eGFR reduces renal potassium reserve. Then medications, acidosis, constipation, dehydration, uncontrolled diabetes, or acute illness can push potassium above the normal range.
AKI creates an even more abrupt problem. A rapid fall in filtration and tubular secretion can allow potassium to rise over hours. Tissue breakdown, acidosis, and reduced urine output may worsen the rise. For this reason, potassium is a core part of an acute kidney injury blood test panel.
Advanced CKD does not guarantee hyperkalemia. Some patients remain in range because of preserved distal sodium delivery, diuretic use, gastrointestinal potassium excretion, and dietary patterns. Others develop recurrent hyperkalemia at higher eGFR because of diabetes, low aldosterone activity, or interacting medications.
Causes of High Potassium in Kidney Disease
High potassium usually results from one or more of three mechanisms: reduced excretion, movement of potassium out of cells, or excess potassium load that exceeds the body’s ability to eliminate it.
Reduced kidney excretion
The most common CKD-related mechanism is impaired renal excretion. Risk rises with advanced CKD, AKI, low urine output, and conditions that reduce aldosterone activity.
Medicines can be important contributors. Examples include:
- ACE inhibitors and angiotensin receptor blockers;
- mineralocorticoid receptor antagonists such as spironolactone, eplerenone, and finerenone;
- potassium-sparing diuretics such as amiloride and triamterene;
- NSAIDs;
- trimethoprim-containing antibiotics;
- calcineurin inhibitors;
- some beta-blockers and heparin in susceptible patients.
Many of these drugs provide major kidney or cardiovascular benefits. Hyperkalemia therefore does not automatically mean they should be permanently stopped. Current CKD guidance emphasizes treating contributing factors and, when possible, maintaining evidence-based renin-angiotensin-aldosterone system therapy.
Potassium shifting out of cells
Metabolic acidosis can move potassium from cells into the bloodstream. Severe insulin deficiency and hyperglycemia can do the same. Cell breakdown from rhabdomyolysis, tumor lysis, major trauma, or hemolysis releases intracellular potassium directly.
Diet and hidden potassium sources
Diet can contribute, but the relationship is more complex than older “high-potassium food” lists suggest. Potassium chloride in salt substitutes and potassium additives in processed foods can deliver highly available potassium. Large amounts may be especially risky in advanced CKD or recurrent hyperkalemia.
Whole plant foods also contain potassium, but their potassium bioavailability, fiber content, and overall health effects differ from concentrated potassium salts. Diet changes should focus on the actual cause of hyperkalemia rather than automatically eliminating fruits and vegetables.
Causes of Low Potassium in Kidney Disease
CKD is commonly associated with high potassium, but hypokalemia can occur and may carry its own risks. Common causes include:
- loop or thiazide diuretics;
- vomiting or diarrhea;
- poor dietary intake or malnutrition;
- excessive laxative use;
- high-dose insulin or rapid correction of hyperglycemia;
- metabolic alkalosis;
- low magnesium;
- certain kidney tubular disorders;
- high aldosterone states;
- dialysis-related potassium removal.
Low magnesium can make hypokalemia difficult to correct because the kidneys continue to waste potassium. When both are low, replacing potassium without addressing magnesium may produce only a temporary improvement.
People on diuretics may show a combination of low potassium, metabolic alkalosis, and changes in sodium or magnesium. A basic metabolic panel can help show the broader electrolyte pattern.
Very low potassium can cause muscle cramps, constipation, weakness, paralysis, palpitations, or arrhythmias. Symptoms can be mild even when the value is clinically important, so laboratory follow-up matters.
Potassium, Heart Risk, and When It Is Urgent
Potassium changes the electrical voltage across heart-cell membranes. When potassium is too high or too low, conduction can become unstable. Hyperkalemia can produce peaked T waves, PR prolongation, QRS widening, loss of P waves, sine-wave patterns, ventricular arrhythmias, or cardiac arrest. Hypokalemia can produce ST depression, flattened T waves, U waves, and arrhythmias.
There is no potassium number that perfectly predicts ECG danger. Some people develop important ECG changes at modest elevations, while others with severe hyperkalemia have few obvious changes. That is why clinicians consider both the potassium level and the clinical setting.
A result around 6.0 mmol/L or higher is generally treated as potentially urgent, especially if it is new, rising, associated with reduced kidney function, or accompanied by symptoms. Levels around 6.5 mmol/L or higher are often considered severe and usually demand emergency evaluation, although local protocols vary.
Seek urgent medical care for:
- chest pain or pressure;
- new palpitations, fainting, or near-fainting;
- severe muscle weakness or paralysis;
- marked shortness of breath;
- confusion;
- little or no urine in someone with kidney disease;
- a confirmed very high potassium result, particularly around 6.0 mmol/L or above.
Emergency treatment for severe hyperkalemia may include intravenous calcium to stabilize the heart, insulin with glucose to shift potassium into cells, inhaled beta-agonist therapy, bicarbonate in selected acidotic patients, diuretics when urine production is adequate, potassium binders, and dialysis when necessary. These treatments address different parts of the problem and are chosen according to severity.
Diet, Medications, and Follow-Up Testing
The safest approach is to identify why potassium is abnormal before making broad changes. For recurrent hyperkalemia, clinicians often review kidney function, bicarbonate, glucose, constipation, medications, supplements, salt substitutes, and dietary potassium sources.
Dietary management has become more individualized. Rather than automatically restricting every fruit, vegetable, bean, or whole grain, a renal dietitian may focus first on:
- potassium chloride salt substitutes;
- potassium additives in processed foods;
- very large portions of concentrated potassium foods;
- cooking methods that can reduce potassium when needed;
- constipation, which can reduce gastrointestinal potassium elimination;
- overall fiber and nutritional quality.
This matters because overly restrictive low-potassium diets can reduce fiber and limit foods that support cardiovascular health. The appropriate level of restriction depends on actual blood potassium, CKD stage, medications, and recurrence pattern.
Medication review is equally important. If a kidney-protective ACE inhibitor or ARB contributes to hyperkalemia, the preferred strategy may be to correct acidosis, optimize diuretics, remove unnecessary potassium sources, or use a potassium binder rather than automatically abandoning beneficial therapy. CKD monitoring should include repeat potassium after medication changes.
Monitoring is especially important when starting or increasing medicines that can raise potassium. Clinicians commonly check potassium and kidney function soon after a dose change in higher-risk patients, then space testing out once values are stable. The exact interval depends on CKD stage, baseline potassium, the medication, blood pressure, other illnesses, and whether the person recently had dehydration, infection, surgery, or another event that could change kidney function. A result that was safe several months ago does not guarantee that potassium is safe after an acute illness or medication change.
Interpretation also benefits from comparing potassium with creatinine and bicarbonate. A rising creatinine plus rising potassium may indicate declining kidney filtration or an acute hemodynamic change. A low bicarbonate can point toward metabolic acidosis as an additional driver of hyperkalemia. In contrast, an isolated high potassium with stable creatinine, normal bicarbonate, no risk medicines, and a hemolyzed specimen raises more suspicion for a collection artifact. These patterns do not establish a diagnosis by themselves, but they help determine how quickly the result should be repeated and what causes should be investigated first.
For low potassium, follow-up usually focuses on stopping unnecessary losses, adjusting diuretics when appropriate, replacing potassium carefully, and correcting magnesium. Potassium supplements can be dangerous in CKD if kidney function changes, so dosing should be supervised.
The timing of repeat testing depends on severity. A mildly abnormal result in a stable outpatient may be repeated within days or according to the treatment plan. A rapidly rising value, severe abnormality, or result after a high-risk medication change may need reassessment within hours or much sooner.
The most important principle is that potassium is a dynamic safety marker. A trend from 4.6 to 5.1 to 5.7 mmol/L tells a different story from a stable value near 5.1. In kidney disease, repeat testing and context often matter as much as the single number.
Home symptoms are not reliable enough to track potassium. Mild and even severe hyperkalemia can be silent, while muscle cramps or palpitations can have many other causes. People with recurrent abnormalities should follow the testing schedule set by their clinician rather than waiting for symptoms. It is also useful to keep an updated list of prescription drugs, over-the-counter pain relievers, supplements, and salt substitutes, because several products can change potassium without being obvious from a food list. When illness causes vomiting, diarrhea, poor intake, or dehydration, kidney function and potassium can change quickly and may need earlier reassessment.
References
- EMCREG-International Multidisciplinary Consensus Panel on Management of Hyperkalemia in Chronic Kidney Disease and Heart Failure 2025 (Position Statement)
- Novel Potassium Binders in Reduction of Hyperkalemia and Optimization of RAAS Inhibitors Treatment in Patients with Chronic Kidney Disease or Heart Failure: A Systematic Review and Meta-analysis 2025 (Systematic Review)
- Associations Between Dietary Potassium Intake From Different Food Sources and Hyperkalemia in Patients With Chronic Kidney Disease 2024
- Pathophysiology and clinical management of hyperkalemia in chronic kidney disease 2023 (Review)
- CKD Evaluation and Management 2024 (Guideline)
Disclaimer
Potassium abnormalities can become dangerous quickly, especially with kidney disease, heart disease, or acute illness. Do not change prescription medicines, potassium supplements, salt substitutes, or major dietary patterns based only on a single result without clinical guidance. A confirmed potassium around 6.0 mmol/L or higher, significant symptoms, or ECG changes warrants urgent medical evaluation according to local clinical protocols.