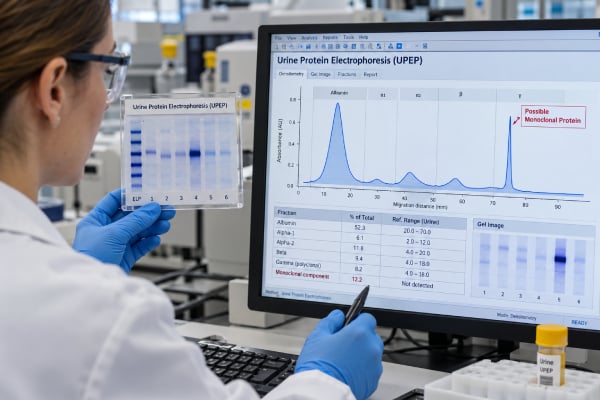
Urine protein electrophoresis (UPEP) separates proteins in a urine sample according to their electrical properties, creating a pattern that can reveal whether an abnormal monoclonal protein is present. The test is best known for detecting and quantifying monoclonal immunoglobulin light chains in plasma cell disorders such as multiple myeloma, but it can also show broader patterns of albumin and globulin proteins. UPEP is not a stand-alone myeloma screening test. Modern evaluation of suspected monoclonal gammopathy usually combines serum protein electrophoresis, serum immunofixation, serum free light-chain testing, and selected urine studies. Urine immunofixation is more sensitive for identifying the type of a small monoclonal protein, while UPEP is useful for showing the distribution and amount of urinary protein and for quantifying a measurable urine M-protein. A positive M-spike can occur in several plasma cell or B-cell conditions, so the result must be interpreted with symptoms, kidney function, blood counts, calcium, imaging, and sometimes bone marrow or kidney biopsy findings.
- UPEP separates urine proteins and can show a narrow monoclonal peak or band called an M-protein or M-spike.
- Urine immunofixation is usually added to confirm and type a suspected monoclonal kappa or lambda protein.
- A positive UPEP does not by itself diagnose multiple myeloma; MGUS, AL amyloidosis, MGRS, and other clonal disorders can also produce monoclonal protein.
- A 24-hour urine collection may be used when the amount of monoclonal protein excreted per day needs to be measured.
- Serum free light chains and serum electrophoresis are central to current monoclonal gammopathy evaluation and can detect disease not obvious on UPEP.
Table of Contents
- What UPEP measures
- Protein patterns and the M-spike
- UPEP versus urine immunofixation
- Role in myeloma screening and diagnosis
- Kidney disease and light-chain proteinuria
- Collection and result reporting
- Next steps after an abnormal UPEP
What UPEP measures
UPEP is an electrophoresis test. The laboratory places urine proteins into a medium and applies an electric field. Proteins migrate at different rates based on factors such as charge and size. The result is a visual or instrument-generated pattern of protein fractions.
In ordinary kidney disease, albumin may dominate the abnormal urine protein pattern. In a monoclonal gammopathy, one clone can produce a large amount of a single immunoglobulin component, often a free light chain. That restricted protein can appear as a discrete band or peak rather than a broad mixture.
UPEP can therefore answer two useful questions: what does the urine protein distribution look like, and is there a measurable restricted component? The test is different from a simple urine total protein measurement, which gives the overall amount but not the electrophoretic pattern.
UPEP also differs from uACR and UPCR. Those ratios quantify albumin or total protein relative to creatinine and are designed mainly for kidney disease assessment. They do not identify monoclonal protein. UPEP is a pattern-based test used when the protein type matters.
Protein patterns and the M-spike
A normal or nonspecific UPEP pattern may show low-level albumin and other proteins without a narrow restricted peak. In glomerular disease, albumin can become prominent. In tubular disease, lower-molecular-weight proteins can increase and create a different distribution.
A monoclonal protein, often called an M-protein, can create a narrow band or spike. In urine, the monoclonal component is often a free kappa or lambda light chain. The laboratory may quantify the peak as a concentration or, when paired with a 24-hour urine volume, as an amount excreted per 24 hours.
The size of an M-spike does not by itself identify the disease. A small monoclonal protein can occur in MGUS. A low-burden clone can still cause serious kidney disease in MGRS. Conversely, some myeloma patients have little or no quantifiable urine M-spike because the abnormal protein is mainly in serum or is detected more sensitively by other methods.
Polyclonal patterns are broader and can reflect inflammation or multiple immunoglobulin populations. Electrophoresis alone can sometimes have difficulty distinguishing a faint monoclonal band from background protein. That is why immunofixation is commonly used for confirmation.
UPEP versus urine immunofixation
UPEP and urine immunofixation are complementary. UPEP is better suited to showing and quantifying the overall electrophoretic pattern; immunofixation is more sensitive and specific for identifying the immunoglobulin type.
If UPEP shows a suspicious restricted band, urine immunofixation can determine whether it is a monoclonal kappa light chain, lambda light chain, or another immunoglobulin component. Immunofixation can also detect small monoclonal proteins that do not form a large measurable peak on routine electrophoresis.
This difference explains a common reporting pattern: “UPEP: no quantifiable M-spike; urine immunofixation: monoclonal free lambda detected.” Those two statements are not contradictory. The amount may be below reliable electrophoretic quantification while still detectable with a more sensitive typing method.
Quantitative urine free light-chain assays provide another kind of information but are not substitutes for electrophoresis or immunofixation. They measure kappa and lambda concentrations, while electrophoretic methods demonstrate clonality more directly through a restricted pattern.
The best test depends on the question. For CKD screening, use uACR. For overall protein burden, use UPCR or 24-hour total protein. For a monoclonal protein pattern, use electrophoresis and immunofixation with serum free light-chain testing.
Role in myeloma screening and diagnosis
UPEP was historically central to myeloma testing because monoclonal urinary light chains are common in light-chain secretory disease. Modern serum assays have changed the workflow. Serum free light-chain measurement is highly sensitive for excess kappa or lambda, and serum immunofixation can detect small serum monoclonal proteins.
Current laboratory recommendations commonly use serum protein electrophoresis, serum immunofixation, and serum free light chains as the core initial panel for suspected monoclonal gammopathy. Urine studies remain important when AL amyloidosis is suspected, when a renal presentation raises concern for monoclonal light chains, when a known urine M-protein needs quantification, or when a specialist is monitoring disease using established response criteria.
A positive UPEP cannot establish multiple myeloma alone. Myeloma diagnosis requires evidence of a clonal plasma cell process plus specific myeloma-defining features or biomarkers. Evaluation usually includes complete blood count, creatinine, calcium, serum monoclonal protein studies, bone marrow assessment, and modern imaging.
A negative UPEP also cannot rule out myeloma. Some patients have serum-dominant disease, very low-level secretion, or abnormalities detected only by serum free light chains and immunofixation. If clinical suspicion remains high, the broader monoclonal protein workup matters more than one urine test.
The Bence Jones protein concept refers specifically to monoclonal free light chains in urine; UPEP and immunofixation are modern ways to detect and characterize them.
Kidney disease and light-chain proteinuria
Monoclonal light chains are important in nephrology because they are not merely markers. Certain light chains can directly injure the kidney.
In myeloma cast nephropathy, a high filtered load of monoclonal light chains interacts with tubular proteins and forms obstructing casts. Patients can develop rapid acute kidney injury, particularly with dehydration, hypercalcemia, infection, or nephrotoxic exposures. This situation requires urgent medical management.
Other monoclonal proteins cause AL amyloidosis, monoclonal immunoglobulin deposition disease, light-chain proximal tubulopathy, and other MGRS lesions. These disorders may present with albuminuria, nephrotic syndrome, tubular dysfunction, hematuria, or progressive CKD rather than classic cast nephropathy.
One practical clue is discordance between total protein and albumin. A high UPCR with a relatively low uACR suggests that much of the urine protein is non-albumin. Monoclonal light chains are one possible explanation, although tubular proteins and urinary tract proteins can produce similar discordance.
MGRS is especially important because the underlying clone can be small. A patient may not meet criteria for multiple myeloma yet still have kidney damage caused by a monoclonal immunoglobulin. UPEP and immunofixation help identify the protein, but kidney biopsy often determines whether and how it is injuring the kidney.
Collection and result reporting
UPEP can be performed on a random urine sample, but a 24-hour collection is often used when quantitative daily monoclonal protein excretion is needed. The laboratory measures total urine volume, protein concentration, electrophoretic fractions, and the M-protein fraction if one is measurable.
Correct 24-hour collection is essential. The usual process is to discard the first void at the starting time, collect every subsequent void for exactly 24 hours, and include the final void at the end time. Missed urine leads to underestimation; collecting beyond the interval can overestimate output.
Reports vary. Common phrases include:
- “No monoclonal protein detected.”
- “Restricted band present; immunofixation recommended.”
- “M-spike detected and quantified.”
- “Monoclonal free kappa light chain identified.”
- “Polyclonal increase” or “mixed protein pattern.”
If a random sample is used, the report may give the monoclonal component as a concentration. If a 24-hour collection is used, the amount can be calculated in mg/24 hours. The numerical value should be interpreted with collection completeness and the total protein result.
No special diet is generally required. Normal hydration is appropriate unless a clinician gives different instructions. If the collection is for a known monoclonal gammopathy, follow the laboratory’s container, storage, and timing directions exactly.
Next steps after an abnormal UPEP
After an abnormal UPEP, the key task is to confirm the monoclonal protein and determine whether it is causing disease. Urine immunofixation is often added if it has not already been performed. Serum protein electrophoresis, serum immunofixation, and serum free light chains are typically reviewed or ordered.
The clinician then looks for organ involvement. Complete blood count can identify anemia. Serum calcium can show hypercalcemia. Creatinine and eGFR assess kidney function. Imaging evaluates bone lesions when myeloma is suspected. Bone marrow biopsy determines clonal plasma cell burden and provides cytogenetic information that can affect diagnosis and risk assessment.
When kidney disease is prominent, nephrology assessment may be needed. A kidney biopsy can distinguish cast nephropathy from amyloidosis, deposition disease, or another MGRS lesion. This distinction matters because treatment urgency and strategy differ.
A small M-protein without organ injury may be monitored as MGUS or another precursor state. A similar-sized monoclonal protein associated with a proven nephrotoxic lesion can require clone-directed therapy under the MGRS framework. The amount alone does not define clinical significance.
Monitoring after diagnosis is individualized. Serum free light chains may be particularly useful in light-chain myeloma. UPEP can remain useful when a measurable urine M-protein was present at baseline or when response criteria call for urine quantification.
Urgent assessment is warranted when a suspected monoclonal protein is accompanied by rapidly worsening kidney function, severe dehydration, confusion, hypercalcemia symptoms, major weakness, or very low urine output. UPEP is a powerful protein-pattern test, but its result becomes meaningful only within the full hematologic and renal evaluation.
Examples of UPEP result patterns
A UPEP report may show predominantly albumin without a monoclonal spike. In a patient with diabetes and heavy albuminuria, that pattern can fit glomerular protein loss. The test does not identify the exact glomerular disease, but the absence of a restricted M-protein makes a large urinary monoclonal component less likely.
A second report may show a narrow restricted peak comprising a measurable fraction of total urine protein. If urine immunofixation identifies the peak as free lambda light chain and serum studies show the same clonal pattern, a monoclonal gammopathy becomes much more likely. The next question is not merely how large the peak is, but whether the clone is associated with myeloma-defining events, amyloidosis, kidney injury, or another clinically significant disorder.
A third report may state that no M-spike can be quantified while immunofixation detects a faint monoclonal kappa band. This can happen when the amount is too low for accurate electrophoretic quantification. It illustrates why UPEP and immunofixation are complementary rather than competing tests.
UPEP can also be misleading if the collection is incomplete. A 24-hour specimen that misses several voids can substantially underestimate daily monoclonal protein excretion. Creatinine excretion, total volume, and collection history may help the clinician judge whether the sample is plausible. When accuracy is doubtful, repeating the collection is often better than making a major treatment decision from a questionable total.
Another pitfall is assuming a negative UPEP excludes AL amyloidosis or light-chain myeloma. Small monoclonal proteins may be easier to detect by serum free light-chain testing or immunofixation. For suspected AL amyloidosis, combining serum and urine immunofixation with serum free light chains improves sensitivity because missing a small clone can have major consequences.
Finally, UPEP is not the same as routine urine dipstick testing. A dipstick can be negative or only mildly positive when light chains make up most of the urine protein because standard reagent strips are most sensitive to albumin. If the clinical concern is monoclonal light-chain disease, electrophoresis and immunofixation are the appropriate protein-characterization tools.
UPEP can also contribute to response monitoring when a patient had measurable urinary M-protein at diagnosis. A large fall in the 24-hour monoclonal protein can support treatment response, but clinicians use formal disease-specific criteria rather than judging success from one percentage change. Serum free light chains, serum M-protein, bone marrow findings, and imaging may carry equal or greater weight depending on the myeloma subtype.
Urine concentration is another practical issue. Very dilute samples can make small protein bands difficult to visualize, while concentration procedures can enhance detection. Laboratories may therefore reject, concentrate, or annotate specimens that are not suitable for reliable interpretation. Following collection instructions improves the chance that a negative result is truly informative.
Finally, a monoclonal peak should be interpreted in the context of total urine protein. A small M-protein within otherwise heavy albuminuria may coexist with an unrelated glomerular disorder, while a large light-chain component can itself explain kidney injury. Establishing causality may require kidney biopsy, especially in suspected MGRS. Detecting the clone is only the first step; linking it to organ damage is the clinically decisive step.
Patients may also see the term “gamma region” or another electrophoretic region on a report. The location of a band helps the laboratory describe migration but is not itself a diagnosis. Immunofixation supplies the protein identity, and clinical evaluation determines significance. For that reason, a report should be read as a set of linked findings rather than as a single M-spike number.
In routine kidney care without suspicion of a monoclonal disorder, UPEP is not a substitute for uACR or UPCR. Electrophoresis is most valuable when the question is protein identity, while ratio tests are better for screening and serial quantification of common CKD protein patterns. Matching the test to the clinical question avoids unnecessary complexity.
References
- Multiple myeloma: 2024 update on diagnosis, risk-stratification, and management 2024 (Review)
- Diagnosis and Management of Multiple Myeloma: A Review 2022 (Review)
- A review of clinical guidelines, laboratory recommendations and external quality assurance programs for monoclonal gammopathy testing 2023 (Review)
- Recommendations for the study of monoclonal gammopathies in the clinical laboratory. A consensus of the Spanish Society of Laboratory Medicine and the Spanish Society of Hematology and Hemotherapy. Part I: Update on laboratory tests for the study of monoclonal gammopathies 2023 (Position Statement)
- Monoclonal gammopathies of renal significance 2023 (Review)
- Urine Protein Immunofixation Electrophoresis: Free Light Chain Urine Immunofixation Electrophoresis Is More Sensitive than Conventional Assays for Detecting Monoclonal Light Chains and Could Serve as a Marker of Minimal Residual Disease. 2023
Disclaimer
This article is for general education and cannot diagnose multiple myeloma, MGUS, AL amyloidosis, or MGRS. UPEP must be interpreted with serum monoclonal protein studies, urine immunofixation, kidney function, symptoms, and sometimes bone marrow or kidney biopsy findings. Rapid kidney deterioration, severe weakness, confusion, dehydration, marked swelling, or very low urine output needs prompt medical evaluation.