
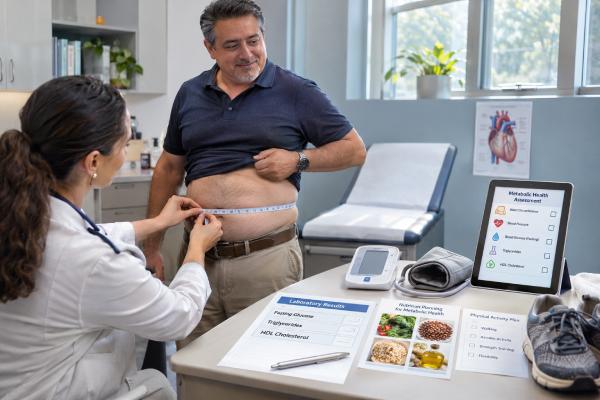
Metabolic syndrome is a cluster of health problems that tend to occur together: excess abdominal fat, high blood pressure, high blood sugar, high triglycerides, and low HDL cholesterol. Having at least three of these features raises the risk of type 2 diabetes, cardiovascular disease, fatty liver disease, and other complications. The tricky part is that metabolic syndrome often causes no obvious symptoms. You may feel completely well while your waist measurement, blood pressure, glucose, and lipid panel show that risk is building. The good news is that the syndrome is highly responsive to treatment. Weight loss when needed, regular activity, better sleep, and a high-fiber, minimally processed eating pattern can improve several components at the same time. Medications may also be needed for blood pressure, cholesterol, triglycerides, glucose, or obesity. “Reversing” metabolic syndrome usually means bringing enough of its components below diagnostic thresholds—not becoming permanently immune to the same risks.
Table of Contents
- What Metabolic Syndrome Is
- The Five Diagnostic Features
- Symptoms and Warning Signs
- Risk Factors and Why It Develops
- Why Metabolic Syndrome Matters
- How to Reverse or Improve Metabolic Syndrome
- Testing, Follow-Up, and When to Get Help
What Metabolic Syndrome Is
Metabolic syndrome is not one disease. It is a practical clinical label for a pattern of cardiometabolic risk factors that frequently share the same underlying drivers, especially insulin resistance and excess visceral fat. Visceral fat is the fat stored deep in the abdomen around internal organs. It behaves differently from fat stored mainly under the skin and is strongly linked with abnormal glucose regulation, inflammation, high triglycerides, and blood pressure problems.
A person can have one or two metabolic abnormalities without meeting the usual definition of metabolic syndrome. Once at least three qualifying features are present, the cluster signals a higher overall risk than any single number should be viewed in isolation. That is why treatment needs to address the whole pattern rather than, for example, trying only to raise HDL.
The syndrome overlaps heavily with prediabetes, type 2 diabetes, obesity, fatty liver disease, sleep apnea, and cardiovascular risk. It is also possible to have metabolic syndrome at a body mass index that does not look very high, particularly when fat is concentrated around the abdomen or when genetics and ethnicity increase susceptibility.
Insulin resistance is central for many people. When muscle, liver, and fat cells respond less effectively to insulin, the pancreas must release more insulin to keep glucose controlled. Over time, glucose may rise, liver triglyceride production can increase, and other metabolic changes follow. The guide to insulin resistance and heart risk explains this connection in more detail.
The Five Diagnostic Features
A commonly used definition identifies metabolic syndrome when three or more of five features are present. Exact criteria can vary slightly by guideline and population, especially waist circumference.
| Feature | Common clinical threshold | What it reflects |
|---|---|---|
| Large waist circumference | Often more than 40 in (102 cm) in men or 35 in (88 cm) in women in U.S. criteria; ethnicity-specific cutoffs may be lower | Central or visceral adiposity |
| High triglycerides | 150 mg/dL or higher, or treatment for elevated triglycerides | Abnormal fat metabolism |
| Low HDL cholesterol | Below 40 mg/dL in men or 50 mg/dL in women, or treatment for low HDL | Part of the atherogenic lipid pattern |
| Elevated blood pressure | 130/85 mmHg or higher, or treatment for hypertension | Increased vascular pressure and cardiovascular risk |
| Elevated fasting glucose | 100 mg/dL or higher, or treatment for elevated glucose | Impaired glucose regulation |
These cutoffs are diagnostic tools, not magical lines separating “safe” from “unsafe.” Risk changes continuously. A fasting glucose of 99 mg/dL and 101 mg/dL are biologically very close, for example, even though only one crosses a criterion. The same principle applies to blood pressure and triglycerides.
Waist circumference is worth measuring correctly because it can add information that body weight alone misses. Use a flexible tape held level around the abdomen, without pulling it tight or measuring over thick clothing. Follow the measurement method recommended by your clinician because protocols differ slightly. For more detail, see waist circumference and heart risk.
A diagnosis should come from actual measurements and laboratory testing rather than appearance. Someone who looks lean can still have high glucose, high triglycerides, or elevated blood pressure, while someone in a larger body may not meet three criteria.
Symptoms and Warning Signs
Most people with metabolic syndrome do not have a specific symptom caused by the syndrome itself. That is one reason screening matters. High blood pressure and abnormal lipids are often silent, and mildly elevated glucose may not feel different at all.
When symptoms are present, they usually come from one of the individual components or a related condition rather than from “metabolic syndrome” as a single illness.
Possible clues include:
- Increasing waist size, especially when weight is accumulating around the abdomen.
- Darkened, thickened, velvety skin around the neck, armpits, or groin, called acanthosis nigricans, which can be associated with insulin resistance.
- Increased thirst and urination, blurry vision, or unexplained fatigue when blood glucose becomes high enough.
- Headaches or dizziness can occur with markedly elevated blood pressure, although most hypertension produces no symptoms.
- Snoring, witnessed pauses in breathing, and daytime sleepiness, which can suggest obstructive sleep apnea—a condition that often travels with obesity, insulin resistance, and hypertension.
Do not use symptoms to decide whether your blood pressure or glucose is “probably fine.” Measure them. A home cuff can help clarify blood pressure patterns, and laboratory tests can identify glucose and lipid abnormalities before complications develop.
If you have chest pressure, severe shortness of breath, fainting, new one-sided weakness, difficulty speaking, or other possible heart attack or stroke symptoms, treat that as an emergency rather than as a routine metabolic syndrome issue.
Risk Factors and Why It Develops
Metabolic syndrome develops through a mix of genetics, body-fat distribution, activity, diet, sleep, medications, hormones, age, and social or environmental conditions. It is rarely explained by one “bad habit.”
Visceral fat and excess weight
Excess abdominal fat is one of the strongest drivers. Visceral fat releases fatty acids and signaling molecules that can worsen insulin sensitivity and contribute to inflammation. The risk generally rises as waist circumference increases, although the amount of visceral fat associated with risk varies between individuals and populations.
Physical inactivity
Muscle is a major site for glucose disposal. Regular activity improves insulin sensitivity, helps control weight, and can lower blood pressure and triglycerides. Long periods of sitting can work against those benefits, so both planned exercise and ordinary movement matter.
Diet pattern
High intakes of sugary drinks, refined grains, highly processed foods, excess calories, sodium, and saturated fat can push multiple components in the wrong direction. A diet low in fiber and minimally processed plant foods also makes appetite and lipid control harder. The problem is the repeated pattern, not an occasional dessert or restaurant meal.
Sleep and sleep apnea
Short sleep, irregular sleep, and untreated obstructive sleep apnea can worsen appetite regulation, insulin resistance, and blood pressure. Loud snoring plus daytime sleepiness or witnessed breathing pauses deserves medical evaluation rather than simply trying to “sleep more.”
Age, genetics, and ethnicity
Risk increases with age, but metabolic syndrome is not limited to older adults. Family history of type 2 diabetes, hypertension, abnormal lipids, or early cardiovascular disease can signal increased susceptibility. Some ethnic groups develop metabolic risk at lower waist circumference or body mass index, which is why universal waist cutoffs can miss risk.
Medical conditions and medicines
Polycystic ovary syndrome, fatty liver disease, and some endocrine disorders may be associated with insulin resistance. Certain medicines—including some antipsychotics, glucocorticoids, and other drugs—can promote weight gain, raise glucose, or alter lipids. Never stop a prescribed medication on your own; ask whether monitoring or alternatives are appropriate.
Why Metabolic Syndrome Matters
The label matters because the cluster predicts a higher chance of future disease. Metabolic syndrome is strongly associated with type 2 diabetes and cardiovascular disease, and risk generally rises as more components become abnormal or as the abnormalities become more severe.
High triglycerides, low HDL, elevated glucose, and abdominal obesity often signal a broader pattern of atherogenic particles and insulin resistance. LDL cholesterol can still be important even when it is not one of the five diagnostic criteria. In other words, “my LDL is normal” does not cancel the risk from high blood pressure, smoking, diabetes, or other factors.
Metabolic syndrome is also closely linked with metabolic dysfunction-associated steatotic liver disease, formerly commonly called nonalcoholic fatty liver disease. Fat accumulation in the liver can occur alongside insulin resistance and may progress in some people to inflammation and fibrosis.
The condition should therefore prompt a wider risk review: smoking status, family history, kidney function, LDL and non-HDL cholesterol, A1C, liver health, physical activity, sleep, and—in appropriate patients—overall cardiovascular risk. A useful practical approach is to track blood pressure, lipids, A1C, and other heart numbers together rather than treating each result as unrelated.
Importantly, the diagnosis is not a prediction that disease is inevitable. It is a signal that several modifiable risk pathways are active at the same time, which makes intervention especially worthwhile.
How to Reverse or Improve Metabolic Syndrome
“Reversal” is possible for many people in the practical sense that, after treatment, fewer than three criteria remain above the diagnostic thresholds. But the tendency can return if weight is regained, activity falls, sleep worsens, medications change, or age and other risks progress. Think of reversal as improved control, not a permanent cure certificate.
1. Lose weight if you have excess weight or a high waist circumference
A modest loss can improve several components together. You do not need dramatic weight loss before health benefits start. A first goal around 5% of starting weight is often clinically useful, with additional benefit possible as loss approaches 10% or more when appropriate. The guide to how much weight loss can lower blood pressure gives useful context for one of the most responsive markers.
Focus on an eating pattern you can sustain: vegetables, fruit, beans, whole grains, nuts, seeds, fish or other lean proteins, and unsaturated fats. Reduce sugary drinks, refined carbohydrates, processed meats, excess sodium, and highly processed snack foods. The companion metabolic syndrome meal plan turns those principles into meals and portions.
2. Build toward regular aerobic and resistance activity
A common long-term target is at least 150 minutes of moderate-intensity aerobic activity each week, plus muscle-strengthening work on two or more days, adjusted for your health and fitness. If you are sedentary, start much smaller. Ten-minute walks are useful. Walking after meals can also blunt post-meal glucose in many people.
Do not make exercise contingent on weight loss. Physical activity improves fitness, insulin sensitivity, blood pressure, and metabolic health even when the scale moves slowly.
3. Treat sleep as part of metabolic care
Aim for adequate, regular sleep and seek evaluation for likely sleep apnea. Treating sleep-disordered breathing may improve daytime function and can help with blood pressure management. Avoid relying on caffeine to compensate for chronic sleep deprivation while leaving the cause untreated.
4. Address each abnormal number directly
Lifestyle is foundational, but medication is often appropriate. Depending on your situation, treatment may include antihypertensive drugs, statins or other lipid-lowering therapy, glucose-lowering medication, or evidence-based anti-obesity treatment. High triglycerides may require specific management, especially when levels become very high because pancreatitis risk rises.
Do not focus on raising HDL with supplements or alcohol. Current prevention strategies emphasize lowering overall cardiovascular risk—especially LDL-related risk, blood pressure, glucose, smoking, and excess adiposity—rather than treating low HDL as an isolated target.
What a practical first 12 weeks can look like
Trying to change every habit on the same Monday often fails. A staged plan makes progress easier to measure. During the first two weeks, collect baseline information: several properly taken home blood pressure readings, body weight, waist circumference, usual step count, and current laboratory results if available. At the same time, remove one or two obvious drivers such as sugary drinks and routine late-night snacking.
During weeks 3 through 6, build meals around a consistent structure. Put vegetables or fruit in most meals, choose a protein source each time you eat, and replace refined grains with beans or higher-fiber whole grains more often. Plan at least one repeatable breakfast and two repeatable lunches so healthy eating does not require daily decisions. Gradually increase walking or another aerobic activity toward a level you can maintain. If you are starting from very little activity, adding 1,000 to 2,000 steps a day may be more realistic than immediately aiming for 10,000.
During weeks 7 through 12, add resistance training if it is safe for you, review portion sizes, and identify the behavior that still creates the most friction. That might be restaurant food, alcohol, poor sleep, weekend overeating, or a medication that promotes weight gain. Work on the largest remaining issue instead of adding minor supplements.
At the end of this period, compare trends rather than demanding that every criterion normalize. A smaller waist, lower average home blood pressure, improved fasting glucose, or lower triglycerides all count as meaningful progress. If the response is limited despite consistent effort, that is useful information—not a failure. It may mean that medication, a sleep apnea evaluation, a more structured weight-management program, or a review for secondary causes is appropriate.
5. Remove high-impact exposures
Stopping smoking, limiting or avoiding alcohol when it worsens triglycerides or blood pressure, and replacing sugary drinks can produce an outsized benefit compared with small “superfood” changes. If stress drives overeating or sleep loss, stress management is useful because it changes the behaviors and physiology that feed the syndrome.
Testing, Follow-Up, and When to Get Help
If metabolic syndrome is suspected, the basic evaluation is straightforward: waist circumference, blood pressure, fasting lipids, and fasting glucose. A1C is often helpful as well, even though it is not one of the classic five criteria. Clinicians may add liver enzymes, kidney tests, thyroid testing, or other studies based on your history.
Follow-up intervals depend on how abnormal the results are and whether treatment changes. Home blood pressure can be checked more often; A1C typically reflects roughly the previous two to three months; lipid changes can often be reassessed after weeks to a few months following a meaningful treatment adjustment. Your clinician may choose a different schedule.
Ask for medical review if:
- fasting glucose, A1C, blood pressure, or triglycerides are repeatedly high;
- your waist or weight is rising quickly without an obvious reason;
- you have symptoms of high glucose, sleep apnea, or medication side effects;
- you have a strong family history of early heart disease or diabetes;
- lifestyle changes are not producing enough improvement;
- you want to discuss anti-obesity medication, diabetes prevention, or lipid-lowering therapy.
Very high triglycerides, severe hypertension, or symptoms suggesting a cardiovascular emergency need faster evaluation. A blood pressure around or above 180/120 mmHg with chest pain, shortness of breath, neurologic symptoms, severe headache, confusion, or vision change warrants urgent emergency care.
Metabolic syndrome is best handled as a set of measurable risks with a coordinated plan. Improve food quality, reduce excess abdominal fat when possible, move more, protect sleep, stop smoking, and treat persistent abnormalities with medication when indicated. Then remeasure. The goal is not merely to lose the label; it is to reduce the long-term chance of diabetes, heart attack, stroke, and other complications.
References
- Metabolic syndrome 2024 (Review)
- Metabolic Syndrome: An Updated Review on Diagnosis and Treatment for Primary Care Clinicians 2024 (Review)
- Etiology, Pathophysiology, and Treatment Strategies in the Prevention and Management of Metabolic Syndrome 2024 (Review)
- Time-Restricted Eating in Adults With Metabolic Syndrome : A Randomized Controlled Trial 2024 (RCT)
- Comparison of the Mediterranean Diet and Other Therapeutic Strategies in Metabolic Syndrome: A Systematic Review and Meta-Analysis 2025 (Systematic Review and Meta-Analysis)
Disclaimer
This article is for general education and does not diagnose or treat metabolic syndrome. Diagnostic cutoffs and treatment targets can differ by guideline, ethnicity, age, pregnancy status, and medical history. Work with a qualified clinician to interpret your measurements and to decide whether lifestyle changes, medication, or additional testing are appropriate.





