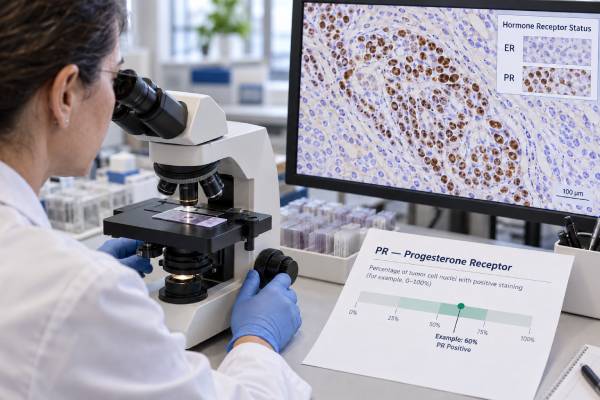
The progesterone receptor, or PR, test is an immunohistochemistry test performed on breast cancer tissue to determine whether tumor-cell nuclei contain progesterone receptor protein. PR is usually tested together with estrogen receptor, or ER, because both are part of the standard hormone receptor profile. Under current ASCO/CAP guidance, invasive breast cancer is considered PR-positive when 1% or more of tumor-cell nuclei stain for PR and PR-negative when fewer than 1% stain. The report should also describe the percentage and intensity of staining. PR is especially useful as a prognostic marker in ER-positive breast cancer: strong PR expression often reflects a more intact estrogen-regulated pathway, while absent PR can be associated with more aggressive biology. ER, however, remains the main validated receptor for predicting endocrine-therapy benefit. A PR result should therefore never be interpreted in isolation. ER status, HER2 status, tumor grade, Ki-67, stage, genomic tests when appropriate, and the clinical setting all influence what the result means for treatment and prognosis.
- PR is measured by immunohistochemistry on breast tumor tissue and is reported as nuclear staining.
- PR is positive when at least 1% of tumor-cell nuclei stain; less than 1% is negative under ASCO/CAP criteria.
- PR is mainly a prognostic marker within ER-positive invasive breast cancer rather than the primary predictor of endocrine benefit.
- A low PR percentage is not the same formal category as “ER Low Positive”; that special label applies to ER, not PR.
- ER-negative/PR-positive results are uncommon and may need careful pathology review if they appear biologically or technically discordant.
Table of Contents
- What the progesterone receptor test measures
- What counts as PR-positive or PR-negative
- How PR is interpreted with estrogen receptor status
- What PR means for prognosis and treatment
- How PR testing is performed and reported
- Discordant results and receptor changes over time
- Questions to ask after receiving a PR result
What the progesterone receptor test measures
Progesterone receptor is a nuclear hormone receptor. In normal breast tissue and many breast cancers, PR expression is influenced by estrogen signaling through the estrogen receptor. This relationship is one reason PR can provide useful information about the biological state of an ER-positive tumor.
The clinical test does not measure progesterone hormone in the blood. Instead, a pathologist applies an antibody to a thin section of tumor tissue and evaluates whether the nuclei of invasive cancer cells stain for PR. The result describes receptor protein expression in that tumor sample.
PR is part of the standard pathology profile for invasive breast cancer. It is usually reported alongside the estrogen receptor test and HER2 status. These markers help classify the tumor and guide systemic treatment.
A tumor is often called hormone receptor-positive if ER and/or PR is positive. In practice, ER status carries the strongest evidence for predicting response to endocrine therapy. The current ASCO/CAP guideline describes PR as being used largely for prognostic purposes in ER-positive invasive breast cancer.
That distinction matters. A PR-positive result can support the picture of a hormone-responsive tumor, but it is not a substitute for ER. Similarly, PR-negative disease does not automatically mean endocrine therapy will not work when ER is clearly positive.
PR expression also differs from gene-expression assays. A genomic test may incorporate genes related to hormone signaling as part of a recurrence algorithm, but the routine PR IHC result is a direct pathology measurement of receptor protein. Both can be useful, yet they answer different questions.
What counts as PR-positive or PR-negative
ASCO/CAP guidance uses the percentage of invasive tumor-cell nuclei that show specific PR staining. The key threshold is 1%.
| PR result | Interpretation | General meaning |
|---|---|---|
| 1% to 100% nuclear staining | PR-positive | Progesterone receptor is detected in at least a small proportion of invasive tumor cells |
| <1% or 0% nuclear staining | PR-negative | Does not meet the guideline threshold for PR positivity |
| Uninterpretable | Result cannot be reliably assigned | May occur with inadequate tissue, severe artifact, failed controls, or problematic preanalytic conditions |
The report should ideally include both the percentage of positive tumor nuclei and staining intensity. Some laboratories may also provide an Allred score or H-score. These composite scores combine the amount and strength of staining, but the core clinical positive-versus-negative interpretation still rests on validated IHC methods and the 1% nuclear-staining threshold.
There is no universal “normal PR level” for breast cancer. The result is not interpreted like a blood laboratory range. A tumor with 5% PR staining and a tumor with 90% PR staining are both technically PR-positive, but they may not have identical biology.
Higher PR expression in an ER-positive tumor is often associated with more favorable luminal biology, while low or absent PR can accompany higher proliferation, higher grade, and a less favorable prognosis. That relationship is statistical and should not be turned into a rigid treatment rule from the percentage alone.
A frequent source of confusion is the phrase “low positive.” The 2020 ASCO/CAP guideline created a specific “ER Low Positive” reporting category for ER staining of 1% to 10% because endocrine responsiveness is less certain in that group. The same special reporting category was not created for PR. A PR result of 1% to 10% is PR-positive, and the actual percentage and intensity should be reported so clinicians can interpret it in context.
If the result is close to the cutoff or unexpected for the tumor’s appearance, quality-control review can be important. Tissue fixation, delayed placement in fixative, decalcification, very small tumor samples, and failed internal controls can all affect receptor staining.
How PR is interpreted with estrogen receptor status
PR becomes most informative when it is read together with ER. The four basic combinations are ER-positive/PR-positive, ER-positive/PR-negative, ER-negative/PR-negative, and the uncommon ER-negative/PR-positive pattern.
ER-positive and PR-positive
This is a common hormone receptor pattern. It usually supports active estrogen-regulated signaling and is often associated with endocrine-responsive disease. Treatment decisions still depend on HER2 status, stage, menopausal status, tumor grade, and recurrence risk.
ER-positive and PR-negative
An ER-positive/PR-negative tumor remains ER-positive and may still benefit from endocrine therapy. Loss or absence of PR can signal altered ER-pathway biology and is associated in many studies with higher grade, greater proliferation, and less favorable outcomes than ER-positive/PR-positive disease.
The difference is prognostic rather than a simple yes-or-no predictor of endocrine response. A person with strongly ER-positive, PR-negative breast cancer should not conclude that endocrine therapy is useless. Current treatment decisions continue to rely heavily on ER expression and the broader disease profile.
ER-negative and PR-negative
If both ER and PR are below 1%, the cancer is hormone receptor-negative. If HER2 is also negative, the tumor meets the receptor definition of triple-negative breast cancer. Endocrine therapy generally does not have a role when both hormone receptors are truly negative.
ER-negative and PR-positive
This pattern is uncommon. Because PR is usually regulated by ER, an ER-negative/PR-positive result can reflect unusual biology, tumor heterogeneity, or technical problems. Modern pathology studies suggest a genuine small subgroup may exist, but an unexpected result deserves careful review.
A pathology team may check internal controls, repeat staining on another block, review fixation, or correlate with tumor morphology. The goal is not to force the tumor into a common pattern but to make sure a treatment-changing receptor result is technically reliable.
The combined interpretation of ER and PR is more informative than either percentage alone. A hormone receptor-positive breast cancer biomarker profile may later include ESR1 or PIK3CA testing in advanced disease, but those molecular markers do not replace the original ER and PR pathology classification.
What PR means for prognosis and treatment
PR is mainly useful as a prognostic marker in ER-positive invasive breast cancer. Prognostic means the result is associated with how the disease tends to behave. Predictive means a marker identifies the likelihood of benefit from a particular treatment. ER has the strongest validated predictive role for endocrine therapy, while PR adds biological and prognostic context.
In broad terms, ER-positive/PR-positive tumors often have more favorable features than ER-positive/PR-negative tumors. Studies have associated PR loss with higher tumor grade, higher proliferation, more advanced presentation, and worse disease-specific outcomes. Research in advanced ER-positive/HER2-negative disease also continues to find that PR-negative tumors can have shorter outcomes than PR-high tumors, even with modern endocrine therapy plus CDK4/6 inhibition.
These findings do not make PR a stand-alone treatment selector. A PR-negative result does not automatically require chemotherapy, and a highly PR-positive result does not prove chemotherapy can be omitted. Adjuvant chemotherapy decisions may incorporate tumor size, nodes, grade, age, comorbidities, and validated genomic assays such as Oncotype DX, MammaPrint, Prosigna, or EndoPredict in the appropriate population.
PR can contribute to surrogate luminal classifications used in some settings. Lower PR and higher Ki-67 may be associated with luminal B-like features, whereas strong ER/PR expression and lower proliferation are more typical of luminal A-like disease. These IHC patterns are useful approximations but are not identical to intrinsic molecular subtypes measured by gene-expression profiling.
For endocrine treatment, the main question remains whether the cancer is meaningfully driven by estrogen-receptor signaling. In invasive cancer, ER positivity generally supports endocrine therapy unless there is a specific reason not to use it. PR can strengthen or weaken confidence about the tumor’s hormone-regulated biology, but it should not override ER by itself.
In metastatic breast cancer, current treatment decisions often depend on additional acquired biomarkers. An ER-positive cancer may later be tested for ESR1 mutations or PIK3CA alterations because these can guide specific endocrine or targeted therapies. PR status still provides context, but it is not the principal biomarker for choosing those agents.
How PR testing is performed and reported
PR testing is normally performed on the same formalin-fixed, paraffin-embedded tissue used for the rest of the pathology workup. The specimen may be a core-needle biopsy, lumpectomy, mastectomy, lymph-node sample, or metastatic biopsy.
The tissue first goes through fixation and processing. Thin sections are placed on slides and stained with a validated antibody. A pathologist then evaluates nuclear staining in the invasive tumor while checking positive controls and, when present, normal internal breast tissue.
Several preanalytic and analytic factors can affect accuracy:
- how quickly the tissue was placed in fixative;
- how long it remained in fixative;
- whether the specimen was decalcified;
- whether there is enough invasive tumor;
- the validated antibody and detection system;
- control staining; and
- accurate distinction between invasive cancer, in situ disease, and normal cells.
The report may include a line such as “PR positive: 80%, strong nuclear staining” or “PR negative: less than 1%.” Some reports provide only a category plus an Allred or H-score. If the result affects treatment and the percentage is missing, asking the pathology team for the quantitative staining details can be helpful.
For ductal carcinoma in situ, or DCIS, the ASCO/CAP guideline recommends ER testing to help assess the potential benefit of endocrine therapy for reducing future breast events. PR testing in DCIS is considered optional. This differs from invasive breast cancer, for which both ER and PR testing are recommended.
PR is not routinely measured with a blood test. Serum progesterone levels reflect hormone physiology and do not establish tumor PR status. Similarly, symptoms, menopausal status, or use of hormonal medicines cannot substitute for direct tumor testing.
Discordant results and receptor changes over time
Breast cancers are biologically heterogeneous, and receptor status can differ between samples. A core biopsy and later surgery specimen may not be perfectly identical, and a metastatic recurrence can have a different ER or PR profile from the original primary tumor.
Some differences are biological. Treatment can select resistant tumor-cell populations, and cancer can evolve over years. Other differences are technical, particularly when tissue quality, fixation, or sampling differs. That is why a surprising receptor change should be interpreted by the oncology and pathology teams rather than assumed to be unquestionably true or false.
Meta-analyses of primary and recurrent breast cancers have documented PR discordance and have associated loss of PR at recurrence with poorer outcomes compared with persistent receptor positivity. This supports reassessing receptors in recurrent or metastatic disease when a safe biopsy is clinically appropriate and the result could alter treatment.
A new metastatic biopsy commonly reevaluates ER, PR, and HER2. If the recurrence remains ER-positive but loses PR, endocrine treatment may still be appropriate because ER is still the primary endocrine predictive marker. The oncology team may also order current molecular testing for acquired resistance markers.
Neoadjuvant therapy can also alter measured receptor expression. A residual tumor after systemic treatment may not exactly match the pretreatment biopsy. Pathologists interpret such changes alongside specimen adequacy and treatment effect.
An unusual ER-negative/PR-positive result deserves special attention because it can potentially change whether a tumor is labeled hormone receptor-positive. If controls or morphology raise concern, repeat testing on another suitable block may help resolve the discrepancy.
The aim of retesting is not to search for a preferred result. It is to characterize the tumor that is actually being treated now with the most reliable available specimen.
Questions to ask after receiving a PR result
A PR percentage becomes useful when it is connected to ER status, HER2 status, and the treatment decision. Useful questions include:
- What percentage of invasive tumor-cell nuclei were PR-positive?
- What was the staining intensity, and was an Allred or H-score reported?
- Is the result clearly positive, negative, or technically uncertain?
- What is my ER result, and how does the ER/PR combination affect interpretation?
- Is HER2 positive, negative, or HER2-low within a HER2-negative category?
- Does my PR result change the recommendation for endocrine therapy, or is ER the main driver of that decision?
- Does low or absent PR add prognostic information when combined with grade and Ki-67?
- Would a genomic recurrence assay add more useful information for an early-stage chemotherapy decision?
- If this is a recurrence, were ER, PR, and HER2 repeated on the new biopsy?
- If the result is ER-negative/PR-positive or otherwise unusual, was the staining reviewed or repeated?
The key is to avoid treating PR as a stand-alone score. A result of 5%, 50%, or 95% carries information, but its meaning depends on the rest of the tumor profile. PR is best used to refine understanding of hormone-receptor biology, especially within ER-positive breast cancer, while treatment decisions remain based on the complete clinical and pathologic picture.
PR can also vary within a tumor and between specimens. A core biopsy samples only part of a cancer, while a surgical specimen samples a much larger area. Treatment can add another source of change, and a later recurrence may not have the same receptor pattern as the original tumor. When a new PR result is unexpected, the useful response is not to choose whichever result looks more favorable. The pathology team can confirm that invasive cancer was tested, review controls and fixation, compare ER and HER2 findings, and decide whether another specimen adds useful information.
This is particularly important when a report contains a small amount of weak PR staining near the cutoff. The percentage, staining intensity, specimen type, and laboratory interpretation all provide more context than the word “positive” alone. PR is generally most informative as part of the hormone-receptor profile, especially alongside ER. It should not be used by itself to predict a precise recurrence percentage or to decide that a specific endocrine drug will or will not work.
References
- Estrogen And Progesterone Receptor Testing In Breast Cancer Guideline Update 2026 (Active Guideline)
- Estrogen and Progesterone Receptor Testing in Breast Cancer: ASCO/CAP Guideline Update 2020 (Guideline)
- Biomarkers in breast cancer 2024: an updated consensus statement by the Spanish Society of Medical Oncology and the Spanish Society of Pathology 2024 (Consensus)
- Hormone receptors in breast cancer: An update on the uncommon subtypes 2023 (Review)
- Prognostic significance of receptor expression discordance between primary and recurrent breast cancers: a meta-analysis 2021 (Meta-analysis)
- Effect of PR status on the prognosis of advanced ER-high HER2-negative breast cancer patients receiving CDK4/6 inhibitor combined with endocrine as first-line therapy 2024
Disclaimer
This article is for general education and does not replace interpretation by a pathologist or breast oncology team. PR results should be read together with ER, HER2, tumor grade, stage, treatment history, and specimen quality. Do not start, stop, or decline endocrine therapy or chemotherapy based on the PR percentage alone.