A triple-negative breast cancer biomarker workup starts by proving what the tumor does not express: estrogen receptor (ER), progesterone receptor (PR), and HER2 at levels that define hormone receptor-positive or HER2-positive breast cancer. But those three results are only the beginning. Depending on the stage and treatment decision, PD-L1 testing, germline BRCA1/2 testing, review of the exact HER2 IHC score, and broader tumor profiling can reveal treatment options that the words “triple-negative” alone do not show. The most useful panel is therefore not one fixed bundle of tests for every patient. It is a sequence of tests chosen for the clinical situation. A new early-stage diagnosis, residual disease after preoperative therapy, and a metastatic recurrence may each call for different biomarkers. Results also need to be read with the specimen, assay, cutoff, and timing in mind because a borderline receptor result or a later biopsy can change how the cancer is classified and treated.
- Triple-negative means ER-negative, PR-negative, and HER2-negative by validated pathology testing; it does not mean the tumor has no measurable biomarkers.
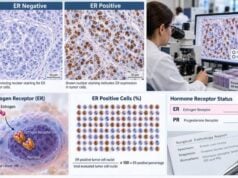
- ER or PR staining of 1% or more is generally reported as receptor-positive; ER staining from 1% to 10% is specifically reported as ER Low Positive rather than strictly ER-negative.
- PD-L1 CPS ≥10 can identify eligible patients with locally recurrent inoperable or metastatic TNBC for pembrolizumab plus chemotherapy, using the approved assay and clinical setting.
- Germline BRCA1/2 testing can affect treatment and inherited-risk counseling; a tumor-only BRCA result cannot by itself establish hereditary risk.
- A HER2-negative TNBC can still be HER2-low, such as IHC 1+ or IHC 2+/ISH-negative, which may matter for treatment in metastatic disease.
Table of Contents
- What Defines Triple-Negative Breast Cancer?
- ER, PR, and HER2: The Core Tests
- PD-L1 Testing and the CPS Score
- BRCA and Hereditary-Risk Testing
- Tumor Profiling Beyond the Basic Panel
- When to Test and Retest Biomarkers
- How to Read a TNBC Biomarker Report
What Defines Triple-Negative Breast Cancer?
Triple-negative breast cancer, or TNBC, is defined by pathology results rather than by one unique gene mutation. In practical terms, the invasive cancer lacks clinically significant ER and PR expression and does not meet criteria for HER2-positive disease. These findings matter because they remove endocrine therapy and standard HER2-positive treatment pathways from the usual starting strategy.
The word “negative” can sound absolute, but each marker has a laboratory definition. ER and PR are measured by immunohistochemistry, or IHC, which stains proteins in tumor-cell nuclei. HER2 is first assessed by protein expression with IHC and, when needed, by in situ hybridization (ISH) to determine whether the HER2 gene is amplified. A complete breast cancer biomarker panel therefore includes the actual scores and interpretation, not just a shorthand subtype label.
TNBC is also biologically diverse. Two cancers can both be ER-negative, PR-negative, and HER2-negative yet carry different inherited variants, immune features, DNA-repair defects, or genomic alterations. This is why additional biomarkers may become important once the basic subtype is known.
A useful distinction is classification versus treatment selection. ER, PR, and HER2 establish the standard clinical subtype. PD-L1, germline BRCA1/2 status, and selected genomic findings may then help choose specific systemic treatments. The tests should not be collapsed into one “positive” or “negative” verdict.
Borderline results deserve special attention. Under current ASCO/CAP guidance, an invasive cancer with ER staining in 1% to 10% of tumor-cell nuclei is reported as ER Low Positive, not ER-negative. These tumors can have biology and treatment questions that overlap with TNBC, but the pathology classification is not the same as a tumor with ER below 1%. If a report uses an older cutoff or simply says “triple-negative” without the individual receptor scores, reviewing the original pathology report is worthwhile.
ER, PR, and HER2: The Core Tests
ER, PR, and HER2 are the foundation of breast cancer biomarker testing because they define major treatment pathways. They are usually tested on tissue from a core needle biopsy or surgical specimen.
ER and PR results
ER and PR IHC reports usually state the percentage of invasive tumor-cell nuclei that stain and may also describe staining intensity. For ER, 1% to 100% staining is considered positive under ASCO/CAP guidance, while less than 1% is negative. ER results from 1% to 10% should carry an ER Low Positive interpretation because evidence for endocrine benefit is more limited than for strongly ER-positive disease. Similar validated IHC principles apply to PR.
For a strict TNBC classification, the report should support ER-negative and PR-negative status. A reader who wants more detail on how nuclear staining is reported can compare the dedicated ER test and PR test explanations.
A low or unexpected result can require quality review. Pathologists consider whether the specimen contained enough viable invasive cancer, whether internal controls worked, and whether pre-analytic factors such as delayed fixation could have affected staining. If the result conflicts with the tumor’s appearance or prior testing, repeat testing on another block or specimen may be reasonable.
HER2 IHC and ISH
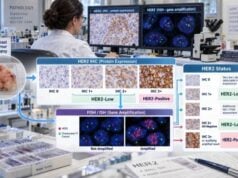
HER2 IHC is commonly reported as 0, 1+, 2+, or 3+. IHC 3+ supports HER2-positive disease. IHC 2+ is equivocal and generally requires ISH or another guideline-directed workup to determine whether HER2 is amplified. IHC 0 or 1+, and IHC 2+ without amplification, are not HER2-positive by the standard classification used to define TNBC.
The exact IHC score should still be preserved. A cancer can be “HER2-negative” for subtype purposes but have HER2-low expression, commonly IHC 1+ or IHC 2+/ISH-negative. That distinction can matter in unresectable or metastatic disease because trastuzumab deruxtecan has a treatment indication for certain HER2-low breast cancers after prior chemotherapy. The HER2-low test is therefore a treatment-selection concept inside the broader HER2-negative group, not a fourth component that changes TNBC into HER2-positive disease.
PD-L1 Testing and the CPS Score
PD-L1 is an immune-related biomarker that can guide immunotherapy in advanced TNBC, but its role depends strongly on stage. It should not be treated as a universal pass/fail marker for every newly diagnosed TNBC.
For previously untreated locally recurrent inoperable or metastatic TNBC, pembrolizumab plus chemotherapy is an established option for eligible tumors with PD-L1 expression meeting the approved cutoff. The relevant test uses the PD-L1 IHC 22C3 pharmDx assay and reports a Combined Positive Score (CPS). A CPS of 10 or more is the key treatment-selection threshold for this setting.
CPS is not simply the percentage of tumor cells that stain. The calculation includes PD-L1-staining tumor cells, lymphocytes, and macrophages, divided by the number of viable tumor cells and multiplied by 100. Because immune cells count, a report that lists only a tumor-cell percentage is not automatically interchangeable with a CPS result. The exact assay and scoring method matter. A detailed PD-L1 breast cancer test report should identify both.
KEYNOTE-355 showed why the CPS ≥10 group matters: in that subgroup, adding pembrolizumab to chemotherapy improved median overall survival compared with chemotherapy alone. The result is predictive in that specific clinical setting; it is not a general prognosis score for all TNBC.
Early-stage TNBC follows a different rule. For eligible patients with high-risk early-stage disease, pembrolizumab may be used with neoadjuvant chemotherapy and then continued after surgery based on the treatment regimen and disease features. FDA review of KEYNOTE-522 found event-free survival benefit regardless of tumor PD-L1 status. Therefore, a PD-L1-negative early-stage tumor does not by itself rule out the approved early-stage pembrolizumab approach.
This stage difference is one of the most common interpretation mistakes. The question should be, “What treatment decision is this PD-L1 result being used for?” rather than “Is PD-L1 good or bad?”
BRCA and Hereditary-Risk Testing
BRCA testing in TNBC can answer two separate questions: whether a patient has an inherited cancer-predisposition variant and whether that finding affects treatment. These are related, but they are not the same as sequencing a tumor for acquired mutations.
A germline BRCA1 or BRCA2 test looks for a pathogenic or likely pathogenic variant present in the person’s inherited DNA, usually using blood or saliva. A confirmed germline result can matter for the patient’s breast and ovarian cancer risk, future screening or risk-reducing decisions, treatment eligibility, and testing of biologic relatives. Modern ASCO/SSO guidance recommends offering BRCA1/2 testing broadly to newly diagnosed patients age 65 or younger and selectively to older patients based on factors such as personal history, family history, ancestry, and PARP-inhibitor eligibility. TNBC remains an especially important context because BRCA1-associated breast cancers are often triple-negative.
Many hereditary panels include additional genes such as PALB2, CHEK2, and ATM. The choice between BRCA-only testing and a broader hereditary breast cancer gene panel depends on personal and family history and how the result would be used. A pathogenic PALB2 variant, for example, has important hereditary implications, but it should not be assumed to have exactly the same breast cancer drug indication as a germline BRCA1/2 variant.
Treatment relevance is substantial. In high-risk, HER2-negative early breast cancer with a germline pathogenic or likely pathogenic BRCA1/2 variant, the OlympiA trial showed benefit from one year of adjuvant olaparib after local treatment and neoadjuvant or adjuvant chemotherapy when trial-based high-risk criteria were met. PARP inhibitors also have roles in selected metastatic HER2-negative breast cancers with germline BRCA mutations. Eligibility depends on the exact stage, prior therapy, mutation type, and current drug labeling; a positive BRCA result is not a stand-alone prescription.
A variant of uncertain significance (VUS) should not be managed as a harmful mutation. It does not establish inherited cancer risk and should not trigger irreversible risk-reducing surgery or predictive family testing as though it were pathogenic. Also, if tumor sequencing detects a BRCA1/2 alteration, germline confirmation may be needed because tumor-only testing cannot determine with certainty whether the variant was inherited.
Tumor Profiling Beyond the Basic Panel
Broader tumor profiling can be useful in TNBC, especially when disease is recurrent or metastatic, but it is not one mandatory test with one standard list of genes. The most useful panel is the one that answers a treatment or clinical-trial question.
Next-generation sequencing (NGS) can test many tumor genes at once and may also report genomic signatures such as microsatellite instability, tumor mutational burden, or gene fusions. In metastatic breast cancer, ASCO guidance supports testing selected candidates for biomarkers that can open tissue-agnostic treatment options, including mismatch-repair deficiency or microsatellite instability-high status, high tumor mutational burden, and NTRK fusions. These findings are uncommon in breast cancer, so their value is mainly that a rare positive result can be actionable.
Broad profiling also helps separate a useful finding from a merely detectable one. A tumor report may list TP53 alterations, PI3K-pathway changes, homologous-recombination features, or experimental markers. Detection does not automatically mean an FDA-approved breast cancer therapy exists for that alteration. The report should be interpreted against the patient’s stage, previous treatment, available drugs, and clinical trials.
HER2 expression is another example of why the original pathology details matter. A metastatic TNBC that remains ER-negative and PR-negative can still fall into a HER2-low treatment group. Reviewing the actual HER2 IHC score, rather than relying only on “HER2-negative,” can reveal this option.
Tumor sequencing and hereditary testing also answer different questions. Tumor NGS studies cancer cells and may find acquired variants that are not present in the rest of the body. Germline testing studies inherited DNA. A tumor profile may suggest a possible hereditary variant, but a dedicated germline test is generally required before using that finding for relatives or hereditary-risk decisions.
Blood-based liquid biopsy testing can sometimes provide tumor genomic information in advanced disease when tissue is difficult to obtain or when a rapid molecular result is needed. A negative plasma result can be uninformative when little tumor DNA is shedding into the blood, so tissue testing may still be needed when the result would change management.
When to Test and Retest Biomarkers
The best time to test depends on what decision comes next. A sensible sequence avoids both undertesting and ordering every possible assay without a clinical purpose.
At the initial diagnosis, ER, PR, and HER2 should be established on invasive cancer tissue. These results define the standard subtype and guide systemic treatment planning. Germline testing can also be appropriate early because a BRCA1/2 result may affect treatment, surgery discussions, and family counseling.
Before or during treatment for high-risk early-stage TNBC, PD-L1 testing is not required to decide whether a patient meets the approved early-stage pembrolizumab pathway. Treatment selection instead depends on stage, tumor size, nodal status, health factors, and the full oncology plan. If surgery follows neoadjuvant therapy, the amount of residual invasive cancer can become important for subsequent treatment decisions even though residual disease itself is not a new biomarker assay.
At metastatic recurrence, obtaining a biopsy of a safely accessible lesion is often valuable when feasible. Repeating ER, PR, and HER2 can confirm the current phenotype because receptor expression can differ between the original tumor and a recurrence. The exact HER2 IHC score should be recorded, not just the positive/negative label. PD-L1 testing becomes relevant for first-line pembrolizumab selection in eligible advanced TNBC, and broader genomic profiling may identify less common actionable findings.
Retesting is especially reasonable when the old report is incomplete, the specimen had technical limitations, or a result is close to a cutoff. It can also matter when a new therapy uses a biomarker category that was not reported years earlier. For example, an older pathology report may only say “HER2-negative” without distinguishing IHC 0 from 1+.
Not every biomarker must be repeated at every progression. The value of a new test depends on whether the result could change treatment. A medical oncologist and pathologist can often identify the highest-yield specimen and avoid using scarce tissue on tests that will not affect the current decision.
How to Read a TNBC Biomarker Report
A complete TNBC biomarker interpretation should connect each result to its purpose instead of treating the report as one composite score. Start with the core pathology and then add stage-specific markers.
A practical review looks like this:
- Confirm the specimen and diagnosis. Note whether the test came from the original breast tumor, a lymph node, residual cancer after therapy, or a metastatic site. Confirm that invasive carcinoma was actually tested.
- Read the ER and PR percentages. For a strict TNBC label, both should support receptor-negative status. If ER is 1% to 10%, look for the ER Low Positive comment and discuss how that affects treatment classification.
- Read the full HER2 result. Record IHC 0, 1+, 2+, or 3+ and any ISH result. IHC 2+ alone is not a final HER2 classification. If disease is metastatic, ask whether an IHC 1+ or 2+/ISH-negative result creates a HER2-low treatment option.
- Match PD-L1 to the clinical setting. In advanced TNBC, confirm that the result is a CPS from the appropriate validated assay and whether it meets the treatment cutoff. Do not apply the metastatic CPS rule to early-stage pembrolizumab eligibility.
- Separate germline from tumor findings. A germline BRCA1/2 pathogenic variant has inherited-risk implications; a tumor-only variant may not. A VUS is not equivalent to a positive hereditary result.
- Review tumor-profile findings for actionability. Ask which alterations have an approved therapy now, which are relevant only to a clinical trial, and which are currently descriptive rather than actionable.
One useful question for every abnormal result is, “What decision changes because of this result?” That keeps testing connected to care. A biomarker can define a subtype, select a drug, estimate inherited risk, or suggest a trial, but those are different jobs.
If results appear inconsistent, ask whether they came from different specimens or dates. A primary tumor might have one HER2 score while a later metastasis has another. Pathologists can also review slides when a value is near a cutoff or when the report conflicts with the cancer’s morphology. The goal is not to force every result into the original label; it is to use the most reliable current evidence for the treatment decision in front of the patient.
References
- Estrogen and Progesterone Receptor Testing in Breast Cancer: ASCO/CAP Guideline Update 2020 (Guideline)
- HER2 Testing in Breast Cancer – 2023 Guideline Update 2023 (Guideline)
- Biomarkers for Systemic Therapy in Metastatic Breast Cancer: ASCO Guideline Update 2022 (Guideline)
- Pembrolizumab plus Chemotherapy in Advanced Triple-Negative Breast Cancer 2022 (RCT)
- FDA Approval Summary: Pembrolizumab for Neoadjuvant and Adjuvant Treatment of Patients with High-Risk Early-Stage Triple-Negative Breast Cancer 2022 (Review)
- Overall survival in the OlympiA phase III trial of adjuvant olaparib in patients with germline pathogenic variants in BRCA1/2 and high-risk, early breast cancer 2022 (RCT)
Disclaimer
Breast cancer biomarker results must be interpreted with the tumor stage, pathology specimen, assay method, treatment history, and current drug labeling. This article is for general education and cannot determine whether a specific person has TNBC or is eligible for immunotherapy, a PARP inhibitor, HER2-directed therapy, genetic testing, or another treatment. Discuss individual results with the oncology, pathology, and genetics professionals involved in your care.