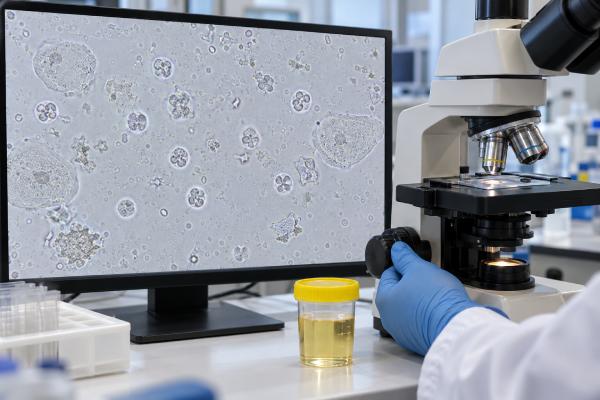
White blood cells in urine are a sign of inflammation somewhere in the urinary tract, but they do not automatically mean a bacterial urinary tract infection (UTI) is present. The finding is called pyuria. Laboratories may report urine WBCs as cells per high-power field on microscopy, cells per microliter on automated analysis, or indirectly through a positive leukocyte esterase dipstick. Many laboratories consider more than about 5–10 WBCs per high-power field abnormal, but methods and reference ranges differ. A symptomatic bacterial UTI commonly causes pyuria, yet stones, sexually transmitted infections, kidney inflammation, urinary catheters, contamination, and other conditions can do the same. The most useful interpretation combines the WBC result with urinary symptoms, nitrite, bacteria, epithelial cells, culture, and patient-specific risk factors. In many settings, an absence of pyuria makes bacterial UTI less likely, while pyuria alone has limited specificity.
- White blood cells in urine mean urinary inflammation; UTI is common but not the only cause.
- Pyuria thresholds vary by laboratory, commonly around more than 5–10 WBCs per high-power field or an equivalent automated count.
- Positive WBCs plus nitrite or a compatible urine culture make bacterial UTI more likely when symptoms are present.
- Sterile pyuria means WBCs are present but routine culture does not show a typical bacterial cause.
- Persistent pyuria, pregnancy, recurrent symptoms, fever, or flank pain may require culture or evaluation for causes beyond simple cystitis.
Table of Contents
- What white blood cells in urine mean
- Normal ranges and pyuria thresholds
- Pyuria and UTI
- Sterile pyuria and non-UTI causes
- WBC, leukocyte esterase, nitrite, and culture
- Sample quality and false results
- When to follow up
- Common pyuria questions
What white blood cells in urine mean
White blood cells, or leukocytes, are immune cells that move into tissues when the body detects infection, irritation, or inflammation. When increased numbers appear in urine, the finding is called pyuria. Neutrophils are the predominant leukocyte in most bacterial UTIs.
Urine WBCs can be measured directly by microscopy or automated particle analyzers. A dipstick gives an indirect measure by detecting leukocyte esterase, an enzyme released by white blood cells. These methods correlate but are not identical, so a dipstick and microscopic count can occasionally disagree.
Pyuria is common in cystitis and pyelonephritis because bacteria trigger an inflammatory response in the urinary lining. It is also common around urinary catheters and can occur with stones, sexually transmitted infections, renal inflammatory disease, or contamination from vaginal leukocytes.
The presence of WBCs therefore answers “is there inflammation?” more reliably than “what caused it?” A culture can add evidence of viable bacteria, while symptom pattern tells whether that bacterial finding is clinically meaningful.
If a report shows WBCs together with bacteria and nitrite in a person with dysuria and frequency, UTI becomes much more likely. If WBCs are elevated but culture is repeatedly negative and symptoms are atypical, a broader diagnostic approach is needed.
Normal ranges and pyuria thresholds
Laboratories use different methods and reference intervals. A common microscopic reference is roughly 0–5 WBCs per high-power field, while some definitions of pyuria use more than 5 or more than 10 WBCs per high-power field. Automated analyzers may report WBC/µL and use instrument-specific cutoffs.
These thresholds are not interchangeable without knowing the method. A high-power field depends on microscope optics and sample preparation. Automated flow cytometers count cells in a measured volume. For that reason, use the reference range printed on your own laboratory report rather than converting numbers from an unrelated source.
The degree of pyuria also does not provide a reliable severity scale. More WBCs can increase the probability of urinary inflammation, but a count of 100 WBCs per high-power field does not necessarily mean a more dangerous infection than 20 WBCs per field. Clinical severity depends on fever, flank pain, systemic signs, obstruction, kidney function, and other factors.
In some populations, lower WBC thresholds produce many false positives. Older women and catheterized patients frequently have pyuria without symptomatic UTI. Recent research has shown that urinalysis performance varies by age and sex, reinforcing the need to interpret the number in context.
The related leukocyte esterase test provides a fast screening estimate of white-cell activity, but microscopy gives more direct cell information.
Pyuria and UTI
Most symptomatic bacterial UTIs produce pyuria, so WBCs are a useful part of the diagnostic picture. In a person with new dysuria, frequency, urgency, or suprapubic pain, elevated urine WBCs support cystitis. In someone with fever, flank pain, nausea, or vomiting, pyuria can support pyelonephritis when the overall syndrome fits.
The absence of pyuria often lowers the probability of bacterial UTI. This can be especially useful in diagnostic stewardship: if there are no WBCs, no leukocyte esterase, and symptoms are not typical, clinicians should question whether a UTI diagnosis fits before prescribing antibiotics.
Exceptions exist. Very early infection, severe immune suppression, very dilute urine, or recent antibiotics can reduce the inflammatory signal. A patient with high-risk symptoms should not be dismissed solely because the WBC count is low.
Pyuria also does not distinguish symptomatic UTI from asymptomatic bacteriuria. A person can have bacteria and WBCs in urine without urinary symptoms, particularly with chronic catheters or advanced age. Treating those laboratory findings as infection can cause unnecessary antibiotic exposure.
The strongest evidence comes from concordance: symptoms fit UTI, WBCs are elevated, and culture grows a plausible pathogen. The urine culture result then helps determine whether viable bacteria are present and may guide therapy.
Sterile pyuria and non-UTI causes
Sterile pyuria means white blood cells are present but a routine bacterial culture is negative or does not explain the inflammation. “Sterile” does not mean there is definitely no infection. It means standard culture did not recover a typical bacterial cause.
Recent antibiotic use is one common explanation. Even a short course can suppress bacterial growth while inflammation persists. Sexually transmitted infections such as chlamydia or gonorrhea can cause urethral inflammation and urinary WBCs but require nucleic-acid testing rather than routine urine culture.
Kidney stones can irritate the urinary lining and produce both WBCs and blood. Interstitial nephritis, an inflammatory kidney condition sometimes triggered by medications, can also cause pyuria. Less common causes include urinary tuberculosis in appropriate epidemiologic settings, inflammatory bladder disorders, and nearby pelvic inflammation.
Contamination from vaginal secretions is another frequent reason, particularly when a clean-catch sample is difficult to obtain. If the specimen contains many squamous epithelial cells, clinicians may question its quality, although epithelial cells are not a perfect contamination marker.
Persistent sterile pyuria deserves a reasoned evaluation rather than repeated empiric antibiotics. The next test should follow the history: STI testing for sexual exposure, imaging for stone symptoms, kidney evaluation for systemic or medication-related features, or repeat clean-catch culture when contamination is suspected.
WBC, leukocyte esterase, nitrite, and culture
Urinary WBCs are most informative when paired with other markers. Leukocyte esterase is a chemical proxy for white-cell activity. Nitrite is a bacterial metabolism marker. Culture detects viable organisms and can identify them.
| Finding | What it mainly reflects | Main limitation |
|---|---|---|
| Urine WBCs | Inflammation | Not specific for bacterial UTI |
| Leukocyte esterase | White-cell enzyme activity | Indirect and affected by sample/test conditions |
| Nitrite | Nitrate-reducing bacteria | Many UTIs remain nitrite negative |
| Bacteria on microscopy | Visible organisms | Can reflect contamination |
| Urine culture | Viable organism growth | Slower; may be affected by antibiotics and contamination |
A WBC-positive, nitrite-positive pattern in a symptomatic patient strongly supports UTI. WBC-positive, nitrite-negative urine still may be UTI because organisms such as Enterococcus may not produce nitrite or the bladder dwell time may have been short.
WBC-negative urine with a positive culture requires closer thought. It can represent asymptomatic bacteriuria, contamination, early infection, immune suppression, or a true infection with a limited inflammatory response. Clinical symptoms determine how much weight to give each possibility.
For a full overview of these combinations, see urinalysis for UTI. The value of the panel lies in the pattern, not in declaring one marker the “gold standard.”
Sample quality and false results
A poorly collected urine specimen can create misleading WBC results. Vaginal secretions contain leukocytes and can raise the measured count in a midstream sample. Menstrual blood can also make the overall urinalysis harder to interpret.
For clean-catch collection, follow the laboratory’s cleansing instructions, begin urinating first, and collect the midstream portion without touching the container’s inside. Deliver the specimen promptly or use recommended refrigeration or preservative if transport is delayed.
Urine concentration matters. Very dilute urine can cause cells to lyse, potentially lowering intact WBC counts while leukocyte esterase remains positive. Concentrated urine can change dipstick chemistry and the apparent concentration of cells. This helps explain occasional mismatches between microscopy and dipstick.
Delay in processing can also alter cells and bacterial numbers. A fresh specimen generally gives the most reliable microscopy. Automated analyzers can improve standardization, but their thresholds and flags still require laboratory-specific interpretation.
If a result does not fit the symptoms, repeating a clean sample is often more useful than treating the number. This is especially true when there are many epithelial cells, mixed bacterial flora, or borderline pyuria without a clear clinical syndrome.
When to follow up
Follow up when pyuria is accompanied by significant urinary symptoms, when symptoms persist despite treatment, when infections recur, or when the patient has risk factors for complicated UTI. Pregnancy, urinary catheters, male UTI, urinary tract abnormalities, immune suppression, and suspected kidney infection all lower the threshold for culture and clinical review.
If WBCs are present but culture is negative, the next step should be tailored rather than automatic. Consider whether antibiotics were taken before the sample, whether STI testing is appropriate, whether stone symptoms are present, and whether the specimen may have been contaminated.
If WBCs are repeatedly elevated with no symptoms, ask whether the finding actually needs treatment. In many patients, asymptomatic pyuria or bacteriuria should not trigger antibiotics. Treatment decisions differ in selected circumstances such as pregnancy or before certain invasive urologic procedures.
Seek prompt care for fever, flank pain, shaking chills, persistent vomiting, confusion, low blood pressure, or rapidly worsening weakness. These can signal pyelonephritis, obstruction, or sepsis. Visible blood, inability to urinate, or severe colicky pain also warrants timely evaluation.
The most useful interpretation is straightforward: WBCs show an immune response in urine. They strengthen a UTI diagnosis when symptoms and microbiology agree, but they are not a stand-alone infection test. The cause of pyuria—not just the count—is what determines the next step.
Common pyuria questions
Can dehydration cause high urine WBCs?
Dehydration can concentrate urine and make cells appear more concentrated per unit volume, but it does not create urinary inflammation by itself. If the sample is very concentrated, clinicians interpret WBCs with specific gravity, symptoms, and repeat testing when necessary.
Can pyuria continue after a UTI is treated?
Yes. White blood cells may remain temporarily while urinary inflammation resolves, even after bacterial counts fall. Persistent or recurrent symptoms matter more than a single post-treatment WBC value. Repeating tests without a clinical reason can detect residual abnormalities that do not require more antibiotics.
What does “too numerous to count” mean?
Some laboratories use this phrase when WBCs are so abundant that a precise microscopic count is impractical. It indicates marked pyuria, but it still does not determine the cause or severity. A heavy WBC burden can occur with bacterial infection, severe inflammation, or contamination.
Are WBC clumps important?
WBC clumps can reflect intense inflammation and may appear in significant urinary infection, including upper-tract disease, but they are not specific enough to diagnose pyelonephritis by themselves. Symptoms such as fever and flank pain carry greater clinical weight.
Why do older adults often have pyuria?
Baseline bacteriuria, urinary retention, incontinence, genitourinary changes, and catheter use become more common with age. As a result, pyuria has lower positive predictive value for symptomatic UTI in older adults. New urinary symptoms or systemic signs are essential before attributing nonspecific illness to the urine finding.
When should persistent pyuria be investigated?
Investigation is reasonable when pyuria is repeatedly present with ongoing symptoms, blood in the urine, stone-like pain, kidney dysfunction, relevant medication exposure, or risk factors for sexually transmitted or unusual infections. The workup should target the likely cause rather than simply repeating antibiotics.
Can menstruation affect the WBC count?
Yes. Menstrual blood and vaginal secretions can introduce leukocytes and red blood cells into a voided specimen. If the result is unexpected and there is no urgency to test, repeating a clean-catch sample after menstruation may improve clarity. When symptoms are significant, however, evaluation should not be postponed solely because of menstruation; the clinician can interpret the sample with its collection limitations.
Does pyuria mean antibiotics are needed?
No. Antibiotics treat susceptible bacterial infection, not white blood cells themselves. Pyuria can occur with asymptomatic bacteriuria, catheters, stones, sexually transmitted infections, and inflammatory conditions. Treatment decisions should be based on a symptomatic infection syndrome and, when appropriate, microbiologic evidence rather than a WBC threshold alone.
If pyuria appears only once in an otherwise well person, the most useful response may be to confirm that the specimen was collected properly and decide whether there is any clinical reason to repeat it. Persistent abnormalities deserve more attention than an isolated borderline count, particularly when they are accompanied by urinary symptoms, blood in the urine, kidney dysfunction, or systemic signs.
A borderline WBC result is therefore best treated as a clue, not a verdict. Trend, symptoms, and specimen quality determine whether it matters.
References
- Accuracy of leukocyte esterase and nitrite tests for diagnosing bacteriuria in older adults: a systematic review and meta-analysis 2026 (Systematic Review)
- Performance of Urinalysis Parameters in Predicting Urinary Tract Infection: Does One Size Fit All? 2024 (Review)
- The EFLM European Urinalysis Guideline 2023 2024 (Guideline)
- Urinary Tract Infections: Core Curriculum 2024 2024 (Review)
- Revisiting approaches to and considerations for urinalysis and urine culture reflexive testing 2021 (Review)
Disclaimer
This article provides general information about white blood cells in urine and pyuria and does not replace medical evaluation. WBC counts should be interpreted using the laboratory’s own reference range together with symptoms, urinalysis, culture, and individual risk factors. Seek urgent care for fever with flank pain, vomiting, confusion, or other signs of severe infection.