A 24-hour urine potassium test measures how much potassium your kidneys remove in urine over a full day. It is most useful when a blood potassium result is abnormal and the clinician needs to know whether the kidneys are appropriately conserving potassium or losing too much. The test can also help assess potassium handling in kidney disease, blood pressure disorders, suspected hormone excess, and some inherited tubule disorders.
The number is not interpreted by itself. A high urine potassium value can be normal after a potassium-rich diet, but it may be inappropriate when blood potassium is low. Likewise, a low urine potassium value can be an appropriate kidney response to potassium deficiency or gastrointestinal losses. Collection accuracy, medications, kidney function, acid-base status, and the serum potassium level during the collection all matter. For that reason, the most useful interpretation combines the 24-hour result with blood tests and the clinical situation.
- What it measures: the total amount of potassium excreted in urine during a complete 24-hour collection, usually reported in mmol/24 hours or mEq/24 hours.
- A common adult reference interval: one major laboratory lists 16–105 mmol/24 hours, but ranges vary by laboratory and diet.
- During hypokalemia: urine potassium above about 30 mEq/day may indicate inappropriate renal potassium loss, while lower excretion suggests the kidneys are conserving potassium.
- High urine potassium does not automatically mean disease: diet, diuretics, aldosterone activity, urine flow, and potassium supplements can all increase excretion.
- Collection quality matters: missed urine, extra collection time, or an incorrect start or stop time can make the result misleading.
Table of Contents
- What the 24-Hour Urine Potassium Test Measures
- Normal Range and How to Interpret the Result
- What High 24-Hour Urine Potassium Can Mean
- What Low 24-Hour Urine Potassium Can Mean
- Using the Test to Evaluate Hypokalemia and Kidney Potassium Loss
- How to Prepare and Collect a 24-Hour Urine Sample
- Follow-Up Tests and When Results Need Prompt Attention
What the 24-Hour Urine Potassium Test Measures
The test measures total potassium excretion rather than the concentration in a single urine sample. That distinction matters because urine concentration changes throughout the day with fluid intake, sweating, meals, medications, and hormone signals. By collecting every void for 24 hours, the laboratory can estimate the amount of potassium the kidneys actually eliminated over that period.
Potassium is the main positively charged ion inside cells. Only a small fraction is present in the blood, yet that small extracellular fraction is essential for normal nerve signaling, skeletal muscle function, and the electrical activity of the heart. The body therefore regulates blood potassium within a narrow range. Insulin and other signals can move potassium into or out of cells over minutes to hours, while the kidneys provide longer-term control by adjusting urinary potassium excretion.
Most filtered potassium is reabsorbed earlier in the nephron. The distal nephron then adjusts final excretion according to potassium intake, aldosterone activity, sodium delivery, urine flow, and acid-base status. This is why urinary potassium can change substantially even when serum potassium moves only slightly.
A 24-hour collection may be ordered when a clinician is investigating unexplained low blood potassium, less commonly high blood potassium, hypertension with suspected mineralocorticoid excess, kidney tubular disorders, or a broader urine electrolyte evaluation. It may also be included in metabolic urine testing when several urinary minerals and electrolytes are measured together.
The test is different from a spot urine potassium test. A spot sample is easier to obtain and can be useful when an immediate answer is needed, but it reflects one moment. A complete 24-hour collection better captures total daily excretion and is especially useful when potassium intake and excretion vary across meals and overnight.
Normal Range and How to Interpret the Result
There is no single universal “normal” 24-hour urine potassium value. One major reference laboratory uses an adult interval of 16–105 mmol/24 hours. Because potassium has a charge of +1, mmol and mEq are numerically equivalent for potassium: 30 mmol of potassium equals 30 mEq.
The laboratory’s own reference interval should take priority. Urinary potassium is strongly influenced by recent intake, so a healthy person eating a potassium-rich diet may excrete much more potassium than someone eating a low-potassium diet. Kidney function, medications, gastrointestinal losses, hormones, and the blood potassium concentration also affect what should be considered appropriate.
A useful way to read the result is to ask two questions:
- What was the blood potassium during the collection? The same urine result can have very different meaning in hypokalemia, normal serum potassium, and hyperkalemia.
- Was the kidney response appropriate? If blood potassium is low, healthy kidneys should reduce urinary potassium excretion. If they continue to excrete a substantial amount, renal potassium wasting becomes more likely.
For example, a 24-hour urine potassium of 55 mEq/day may fall inside a laboratory reference interval. In a person with normal blood potassium and an ordinary diet, that may simply reflect normal balance. In a person with persistent serum potassium of 2.8 mmol/L, however, the same 55 mEq/day is inappropriately high because the kidneys should be conserving potassium.
Daily excretion is also a rough reflection of recent potassium intake when a person is in steady balance and kidney function is adequate, but it is not a precise dietary intake test. Potassium can shift between cells and blood, stool losses may change, and the kidneys may temporarily retain or release potassium while the body adapts. For that reason, a single 24-hour value should not be converted directly into an estimate of how much potassium someone ate. Repeated collections under usual eating conditions are more informative when the clinical question concerns habitual intake or long-term balance.
A result near the edge of the laboratory range is therefore not automatically abnormal. The key issue is whether the excretion makes physiologic sense for the person’s serum potassium, recent intake, and treatment. Clinicians may repeat the collection if the value conflicts with the rest of the picture, especially when a missed void or unusual diet is possible.
The result is also interpreted in relation to creatinine and total urine volume. Urine creatinine can help assess whether a 24-hour collection appears plausible, although it is not a perfect completeness check because creatinine excretion varies with age, sex, muscle mass, diet, and activity. If collection accuracy is uncertain, clinicians may review a 24-hour urine collection error pattern before drawing conclusions from the potassium value.
What High 24-Hour Urine Potassium Can Mean
A high value means the kidneys excreted a large amount of potassium during the collection. Whether that is abnormal depends on the blood potassium level and the circumstances.
High intake is one common explanation. Potassium-rich foods, potassium-containing salt substitutes, oral potassium supplements, and intravenous potassium can increase urinary excretion when kidney function is intact. This is a normal homeostatic response rather than evidence that the kidneys are “leaking” potassium.
When blood potassium is low, however, high urinary excretion may indicate renal potassium wasting. Common causes include:
- Loop and thiazide diuretics. These increase sodium and fluid delivery to the distal nephron, which can increase potassium secretion.
- Mineralocorticoid excess. Excess aldosterone or aldosterone-like activity promotes sodium retention and potassium secretion. Primary aldosteronism is a classic consideration in a person with hypertension and hypokalemia.
- High cortisol states. Severe cortisol excess can activate mineralocorticoid pathways and contribute to potassium wasting.
- Renal tubular disorders. Bartter syndrome, Gitelman syndrome, some renal tubular acidoses, and other inherited or acquired tubule conditions can cause inappropriate urinary potassium loss.
- Certain medications and toxins. Some drugs affect kidney tubular handling directly or indirectly. Medication review is therefore essential.
- Recovery from some kidney injuries or periods of high urine flow. Potassium losses may increase during a diuretic phase.
Acid-base status often narrows the differential. Hypokalemia with metabolic alkalosis suggests a different group of causes than hypokalemia with metabolic acidosis. Urine chloride, blood pressure, renin, aldosterone, magnesium, bicarbonate, and medication history are often used alongside potassium excretion. A clinician may also calculate the fractional excretion of potassium when a timed 24-hour collection is unavailable or when additional context is needed.
High urine potassium can also occur when blood potassium is high and the kidneys are responding appropriately by excreting the excess. In that setting, the important question is not whether urine potassium is “high,” but whether excretion is sufficient for the degree of hyperkalemia, kidney function, and potassium intake.
What Low 24-Hour Urine Potassium Can Mean
Low urinary potassium often means the kidneys are conserving potassium. That can be appropriate or inappropriate depending on the serum potassium level.
During hypokalemia, low urine potassium generally supports a nonrenal cause or reduced intake because the kidneys are doing what they should: minimizing potassium loss. Common possibilities include diarrhea, vomiting after the urinary effect of alkalosis has resolved, very low dietary intake, or a shift of potassium from blood into cells. A low result therefore does not necessarily mean poor kidney function.
If blood potassium is high, low urinary potassium can be more concerning. It may reflect impaired potassium excretion due to reduced kidney filtration, low distal sodium delivery, reduced aldosterone production or action, or medications that limit the renin-angiotensin-aldosterone system. Advanced chronic kidney disease can reduce the kidney’s ability to excrete a potassium load, although remaining nephrons often adapt substantially until kidney function becomes more impaired.
Medication effects are especially important. ACE inhibitors, angiotensin receptor blockers, mineralocorticoid receptor antagonists, potassium-sparing diuretics, trimethoprim, and some other drugs can reduce renal potassium excretion or increase the risk of hyperkalemia. A low urine potassium value should never be interpreted as a reason to stop prescribed therapy without medical guidance.
Low urinary potassium also needs context from urine volume. A very low total urine output can reduce total potassium excretion even when the urine potassium concentration is not low. Measuring urine sodium, urine chloride, creatinine, and osmolality can help clarify whether low excretion reflects kidney conservation, reduced filtration, low intake, or volume-related physiology.
Using the Test to Evaluate Hypokalemia and Kidney Potassium Loss
The 24-hour urine potassium test is particularly useful when serum potassium is low because it helps separate renal potassium loss from extrarenal loss or redistribution.
A commonly used clinical rule is that, during true hypokalemia, urinary potassium excretion below roughly 20–30 mEq/day suggests appropriate renal conservation, while excretion above about 30 mEq/day suggests that the kidneys are contributing to potassium loss. These are practical decision thresholds, not universal laboratory reference limits. Potassium replacement given during the collection, changing serum potassium, kidney impairment, and incomplete urine collection can all affect the result.
The next step depends heavily on blood pressure and acid-base status. A typical diagnostic pattern looks like this:
- Confirm true hypokalemia with a repeat serum potassium when needed and check for hemolysis or other preanalytical issues.
- Assess urinary potassium loss. A 24-hour collection is one option; a spot potassium-to-creatinine ratio or fractional excretion may be used when a full-day collection is impractical.
- Check serum bicarbonate or blood gas information. Metabolic alkalosis and metabolic acidosis point toward different causes.
- Review blood pressure and medications. Hypertension plus renal potassium loss raises concern for mineralocorticoid excess or related states, while normal or low blood pressure can fit diuretic use, vomiting, Bartter syndrome, or Gitelman syndrome.
- Check magnesium when appropriate. Magnesium deficiency can promote renal potassium wasting and make hypokalemia difficult to correct.
Urine chloride can be especially useful in hypokalemic metabolic alkalosis. It helps distinguish chloride-responsive states such as vomiting or remote diuretic exposure from conditions associated with ongoing renal chloride and potassium loss. The broader urine chloride result is therefore often interpreted with urine potassium rather than separately.
The transtubular potassium gradient, or TTKG, has historically been used to estimate distal potassium secretion, but it has important assumptions and limitations. Modern evaluation often relies more on direct urine potassium measurements, potassium-to-creatinine ratios, fractional excretion, acid-base findings, and clinical context. If a TTKG is reported, it should be interpreted cautiously and in the setting in which the calculation is valid.
How to Prepare and Collect a 24-Hour Urine Sample
A correct collection is essential because the laboratory calculates daily excretion from the total urine volume and measured concentration. Missing even one substantial void can falsely lower the result.
Unless your clinician gives different instructions, the basic process is:
- Choose a normal collection day. Do not intentionally change your potassium intake, fluid intake, or activity unless the ordering clinician specifically asks you to.
- Start by emptying your bladder. On the first morning, urinate into the toilet and record that time. This urine is not kept.
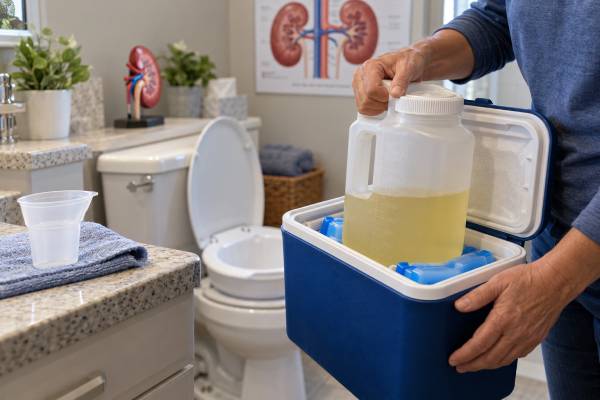
- Collect every urine sample after that. Save all urine passed for the next 24 hours in the supplied container or as directed by the laboratory.
- Finish at the same time the next day. At the recorded stop time, empty your bladder one final time and add that urine to the collection.
- Store the specimen as instructed. Many collections need refrigeration or another specified storage method.
Do not extend the collection because you missed a sample; that creates an overcollection and can distort the result. Instead, contact the laboratory or clinician for instructions. A general 24-hour urine collection guide can help explain the timing and handling steps.
Tell the ordering clinician about prescription drugs, over-the-counter medicines, supplements, electrolyte powders, and potassium-containing salt substitutes. Do not stop medications on your own. Diuretics, potassium supplements, mineralocorticoid-blocking medicines, and several blood pressure drugs can substantially change the result, but sometimes the purpose of the test is to measure potassium handling while you are taking them.
Follow-Up Tests and When Results Need Prompt Attention
A 24-hour urine potassium result rarely establishes a diagnosis by itself. Follow-up commonly includes serum potassium, sodium, bicarbonate, chloride, magnesium, creatinine, and estimated glomerular filtration rate. Depending on the pattern, clinicians may add renin and aldosterone testing, cortisol-related testing, urine chloride, or evaluation for renal tubular disorders.
If a broader kidney assessment is needed, serum creatinine and eGFR are usually more practical measures of filtration than urine potassium. A creatinine clearance test may be used in selected situations when measured clearance is useful, although collection error can affect it too.
For persistent hypokalemia, clinicians also look for ongoing gastrointestinal losses, laxative use, eating disorders, medication effects, high aldosterone states, magnesium deficiency, and genetic tubule disorders. For hyperkalemia, the focus shifts toward kidney function, medications, acid-base status, insulin deficiency, cell breakdown, and whether the potassium result itself could be falsely elevated.
The urine test is not the main determinant of urgency. The blood potassium level, symptoms, electrocardiogram findings, and rate of change matter more. Severe hypokalemia can cause weakness, paralysis, muscle breakdown, and dangerous arrhythmias. Severe hyperkalemia can also cause life-threatening cardiac conduction problems, sometimes with few symptoms beforehand.
Seek urgent medical care for significant muscle weakness, paralysis, fainting, severe palpitations, chest symptoms, or if a clinician tells you that your serum potassium is at a dangerous level. A urine result can help identify why the disturbance occurred, but treatment decisions for dangerous potassium abnormalities are based primarily on the serum result and the person’s clinical condition.
References
- Potassium Homeostasis 2024 (Review)
- Potassium homeostasis – Physiology and pharmacology in a clinical context 2023 (Review)
- A New Understanding of Potassium’s Influence Upon Human Health and Renal Physiology. 2023 (Review)
- Potassium homeostasis: sensors, mediators, and targets 2022 (Review)
- KUR – Overview: Potassium, 24 Hour, Urine 2026
Disclaimer
A 24-hour urine potassium test must be interpreted with the serum potassium level, kidney function, medications, diet, and collection quality. Do not change potassium supplements, salt substitutes, diuretics, or prescription medicines based on a urine result alone. Markedly abnormal blood potassium or symptoms such as severe weakness, paralysis, fainting, or palpitations require prompt medical assessment.