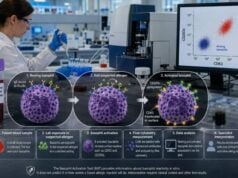
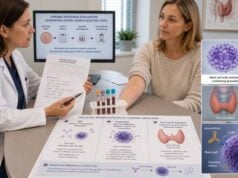
A food allergy IgE panel is a blood test that measures immunoglobulin E antibodies to several foods at once. Panels commonly include milk, egg, peanut, tree nuts, wheat, soy, fish, shellfish, sesame, or other locally selected foods. The test can support the diagnosis of an immediate IgE-mediated food allergy when a specific food caused hives, swelling, vomiting, wheezing, low blood pressure, or another compatible reaction soon after it was eaten. It should not be used as a general screen for unexplained symptoms or as a list of foods to avoid. A positive result means sensitization, not necessarily clinical allergy, and broad panels often produce irrelevant positives in people with eczema, pollen allergy, or high total IgE. A negative result lowers the probability of IgE-mediated allergy but does not answer every clinical question. Accurate diagnosis combines a focused history with targeted specific IgE or skin testing, and a medically supervised oral food challenge when uncertainty remains.
- Food-specific IgE detects sensitization, not automatic allergy or intolerance.
- Testing should be limited to foods suggested by the reaction history, not every food available on a panel.
- Higher values generally increase the probability of allergy but do not predict exact reaction severity.
- A food that is eaten regularly without symptoms should not usually be removed because of an isolated positive result.
- IgG food panels, hair tests, electrodermal tests, and similar “intolerance” screens do not diagnose IgE-mediated food allergy.
- Oral food challenge is the reference standard when history and testing do not provide a clear answer.
Table of Contents
- What a Food IgE Panel Measures
- Which Foods Should Be Tested
- How to Read Positive and Negative Results
- Cross-Reactivity and Component Testing
- Symptoms the Panel Cannot Explain
- Skin Tests, Food Challenges, and Diagnosis
- Avoiding Harm and Planning Next Steps
What a Food IgE Panel Measures
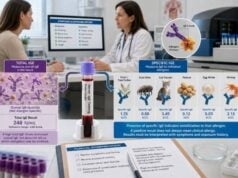
The laboratory mixes a patient’s serum with extracts from selected foods. If IgE antibodies bind to an extract, the instrument reports a concentration, often in kUA/L. Some reports group values into classes. The continuous number, assay, and clinical context are more useful than the class label.
IgE-mediated food allergy develops when food-specific IgE attaches to mast cells and basophils. After the food is eaten, allergen proteins can link those antibodies and trigger release of histamine, tryptase, and other mediators. Symptoms usually begin within minutes to about two hours, although timing can differ with certain syndromes, preparation, dose, and cofactors.
A positive blood result shows immune recognition. It does not reproduce eating the food and therefore cannot prove that symptoms will occur. Sensitization is common, especially among people with eczema or other allergic disease. Many sensitized people tolerate the tested food.
The panel also cannot determine how much food will cause symptoms. Threshold dose varies among patients and can change with illness, exercise, alcohol, sleep loss, menstruation, medications, and the food matrix. Nor can the result predict whether the next reaction will involve only skin or progress to anaphylaxis.
Blood testing has practical advantages. It does not expose the patient to food, antihistamines usually do not affect it, and severe eczema or dermatographism does not prevent collection. Several targeted foods can be tested from one sample. Results take longer than skin testing and can be costly, especially when many unnecessary items are ordered.
Total IgE may be reported with the panel. It reflects the overall amount of IgE, not a particular food. High total IgE can accompany eczema, allergic disease, parasites, and other conditions. It may make multiple low-level specific results harder to interpret but does not confirm food allergy.
The test is sometimes still called a RAST, although modern laboratories commonly use other immunoassay methods. The brand or platform matters because numerical values and available allergens differ. Trends should be followed on the same platform when possible.
Which Foods Should Be Tested
The best panel is built from the history. The clinician identifies the suspected meal, exact ingredients, amount, preparation, timing, symptoms, treatment, and foods tolerated before and after the event.
Testing is reasonable when an immediate reaction followed a specific food or when a patient has never eaten a high-risk food but has a clinical circumstance that makes targeted assessment appropriate. The goal is to answer a defined question such as, “Did peanut likely cause this reaction?” or “Has a child with known milk allergy become a candidate for challenge?”
Broad screening is harmful because every additional test creates another chance of a false or clinically irrelevant positive. If 20 foods are ordered in a person with no convincing reactions, several low positives may appear by chance or cross-reactivity. The resulting avoidance can reduce nutrition, increase cost, create anxiety, and make later reintroduction difficult.
Common panel foods do not all need testing simply because they cause many allergies in the population. A person who eats wheat, soy, milk, and egg regularly without symptoms has already demonstrated clinically meaningful tolerance. Testing those foods adds little.
A focused history should document:
- Exact food and ingredients, including sauces, garnishes, and cross-contact
- Raw, cooked, baked, fermented, or processed form
- Estimated amount eaten
- Time to first symptom
- Skin, breathing, gastrointestinal, neurologic, and circulation symptoms
- Exercise, alcohol, infection, or medication around the event
- Previous and later tolerance of the same food
- Emergency treatment and any tryptase result
A restaurant reaction may require testing several plausible ingredients, but the selection should remain strategic. For example, a reaction after a mixed dessert might involve nuts, milk, egg, sesame, or an additive. The recipe and allergy history narrow the list better than a standard “100-food” panel.
Cross-contact should be considered separately from recipe ingredients. A meal can contain trace peanut, tree nut, shellfish, milk, or sesame from shared equipment even when the menu does not list it. Testing every common allergen is still not the first response. The clinician reconstructs the kitchen setting, other foods eaten, and prior tolerance, then selects the few sources that could realistically explain the timing. Obtaining the ingredient label or contacting the manufacturer may be more informative than expanding the panel.
Infants with moderate or severe eczema may need individualized evaluation before introduction of selected foods, but routine panels are not a substitute for prevention guidance. The more foods included without a history, the more likely unnecessary avoidance becomes.
Testing should also reflect age and diet. Cow’s milk and egg are common in young children; shellfish and tree nut questions may become more prominent later. Regional foods and cultural diet matter more than a generic commercial list.
How to Read Positive and Negative Results
A positive specific IgE result increases the probability of allergy only when the pre-test history is compatible. Its meaning depends on the food, age, assay, population, and value.
Higher concentrations are generally associated with a greater chance of reacting during an oral food challenge. Published decision points can sometimes identify groups with a high probability of allergy to foods such as peanut, milk, egg, or fish. These thresholds are not universal. Studies use different referral populations, challenge protocols, and laboratory platforms.
A low positive can represent true allergy when the history is strong. A high value can occur in a tolerant patient. The number should never be treated as a severity scale. Severe reactions can occur at low values, while some patients with high values have only mild symptoms or no reaction on exposure.
Possible explanations for a positive result without clinical allergy include:
- Sensitization without symptoms
- Cross-reactive pollen or carbohydrate structures
- High total IgE and eczema
- Past allergy that has resolved while antibody remains
- Laboratory variation near the cutoff
- Testing a related food instead of the true culprit
A negative result makes IgE-mediated allergy less likely but does not guarantee safety. The extract may lack a relevant component, antibody may be below detection, or the wrong food may have been tested. A convincing immediate reaction still requires specialist assessment.
The result does not diagnose delayed non-IgE reactions. A child with food protein-induced enterocolitis syndrome can have repetitive vomiting one to four hours after a trigger with negative specific IgE. Celiac disease, lactose intolerance, irritable bowel syndrome, and many other conditions are not ruled in or out by an IgE panel.
Results should be kept as exact numbers with units and dates. “Positive to nuts” is too vague because peanut is a legume, tree nuts are separate species, and cross-reactivity varies. Each item needs its own clinical conclusion.
Values near the laboratory detection limit deserve restraint. Small analytical differences can move a result from “undetectable” to “positive” without a meaningful change in risk. Switching assay platforms can also create apparent rises or falls. When monitoring a known allergy, compare results from the same method when possible and focus on the overall trend rather than a single decimal place. A laboratory category should never erase a history of regular tolerance.
| Result and history | Likely meaning | Typical next step |
|---|---|---|
| Positive with a convincing immediate reaction | Supports IgE-mediated allergy | Confirm culprit, provide safety plan, consider components or future challenge |
| Positive to a food eaten without symptoms | Sensitization is more likely than allergy | Do not remove the food without clinical review |
| Negative with a vague history | IgE-mediated allergy is less likely | Consider other diagnoses or supervised introduction |
| Negative after a convincing immediate reaction | False negative, wrong target, or non-IgE mechanism is possible | Allergy specialist review and selected additional testing |
Cross-Reactivity and Component Testing
Food extracts contain many proteins. Some are stable during heating and digestion, while others are fragile. Some resemble proteins in pollens, latex, insects, or other foods. This can create a positive extract result that does not reflect the same clinical risk as primary sensitization to a stable food protein.
Pollen-food allergy syndrome is a common example. A person sensitized to birch or grass pollen may have IgE that cross-reacts with related proteins in raw fruits, vegetables, or nuts. Symptoms are often itching or tingling in the mouth and throat, and cooked forms may be tolerated. Stable proteins and cofactors can create broader risk in some patients, so the pattern still needs assessment.
Component-resolved diagnostics measure IgE to individual molecules. They can sometimes improve specificity or explain reaction patterns. Examples include peanut storage proteins, hazelnut storage proteins versus birch-related components, cashew and walnut components, milk casein, and egg ovomucoid.
An egg component IgE test, for example, can show recognition of heat-stable ovomucoid or more heat-sensitive ovalbumin. It may inform the probability of baked versus less-cooked egg reactivity but cannot prove tolerance.
Peanut component testing can help distinguish sensitization to stable storage proteins from some pollen-related patterns. It still does not provide a perfect severity forecast and should not be used without the history.
Cross-reactive carbohydrate determinants can bind IgE in laboratory assays and produce multiple plant or insect positives with little clinical relevance. Component patterns may help identify this, but not every laboratory offers the same markers.
Component testing should be selective. Ordering every available molecule recreates the same overtesting problem as a broad food panel. A result is valuable only when it changes the estimated probability, challenge decision, or counseling.
Not all foods have well-validated components, and the absence of a component result does not mean the food is safe. Even for peanut and selected tree nuts, component patterns overlap between allergic and tolerant patients. Geography matters because pollen exposure changes which cross-reactive proteins are common. The test should sharpen a specific question, not generate a molecular profile that has no clear clinical action.
Symptoms the Panel Cannot Explain
Food-related symptoms are common, but only a portion are IgE-mediated allergy. A panel cannot serve as a universal digestive or inflammation test.
Lactose intolerance results from reduced digestion of milk sugar and causes gas, bloating, cramps, or diarrhea. Milk-specific IgE tests immune sensitization to milk proteins and does not diagnose lactose intolerance.
Celiac disease is an autoimmune response to gluten that requires specific antibody tests and sometimes intestinal biopsy while gluten is being eaten. Wheat IgE evaluates immediate wheat allergy, a different condition.
Food protein-induced enterocolitis syndrome is a delayed non-IgE food allergy, often causing repetitive vomiting, lethargy, pallor, and sometimes diarrhea after a trigger. Diagnosis is clinical, with challenge in selected cases.
Eosinophilic esophagitis can be driven by foods, but IgE panels do not reliably identify the responsible foods. Symptoms, endoscopy, and biopsy are central. Broad panel-directed elimination can remove many foods without treating the actual disease.
Food poisoning, infection, reflux, migraine, pharmacologic effects, and irritable bowel syndrome can also follow meals. Timing, co-diners, reproducibility, dose, and symptom type help distinguish them.
Chronic hives are rarely caused by an ongoing hidden food allergy when individual hives recur for weeks without a consistent immediate food relationship. Broad testing often produces distracting positives. The evaluation follows a chronic urticaria testing approach rather than a food panel.
IgG or IgG4 food tests commonly show foods that have been eaten and tolerated. They are not validated to diagnose food allergy or intolerance. Results can lead to severe unnecessary restriction. Hair analysis, applied kinesiology, electrodermal testing, and unvalidated cellular assays have the same problem.
Skin Tests, Food Challenges, and Diagnosis
Skin prick testing places a small amount of food extract or fresh food on the skin and measures the wheal after several minutes. It is quick and often sensitive. Antihistamines, skin disease, technique, and extract quality can affect results.
Blood and skin tests both establish sensitization. One may be chosen because of age, eczema, medications, access, or the food involved. Performing both automatically does not always improve accuracy. Discordant results require interpretation rather than majority voting.
The oral food challenge is the reference standard when current allergy remains uncertain. Under medical supervision, measured doses are given over time while trained staff monitor for objective symptoms. The food form and total dose are selected for the question.
A challenge may be used to:
- Confirm or exclude allergy after inconclusive testing
- Determine whether a child has outgrown milk, egg, wheat, or another allergy
- Assess baked milk or baked egg tolerance
- Remove a label created by broad panel testing
- Clarify a food that has never been eaten but tests positive
Challenges carry a risk of reaction, including anaphylaxis, and should not be attempted at home after a suspected allergy unless a clinician has specifically judged home introduction appropriate. The facility must be prepared to treat symptoms.
A passed challenge demonstrates tolerance to the tested amount and preparation on that day. The clinician provides a plan for adding the food to the diet. Continued ingestion may be advised to maintain practical tolerance. A failed challenge defines current reactivity and can refine the avoidance threshold and emergency plan.
Challenge interpretation is preparation-specific. Passing baked milk does not automatically mean fresh milk is tolerated, and passing a small serving of one fish does not clear every fish species. The discharge plan should state the exact food, dose, form, and frequency. Families should also know what symptoms after leaving the clinic require contact or emergency care, because delayed symptoms can occasionally occur.
Basophil activation testing is a functional laboratory test available in selected centers. It may improve diagnostic specificity for some foods and reduce challenges, but standardization and access remain limited. It complements rather than replaces clinical judgment.
Avoiding Harm and Planning Next Steps
The greatest risk of an unfocused panel is not the blood draw. It is the cascade that follows: multiple food labels, restrictive diets, nutritional deficiency, social limitation, fear, higher grocery costs, and delayed introduction of foods that may have been tolerated.
Do not stop a regularly eaten food solely because a report marks it positive. Discuss the actual exposure history with an allergist. In some cases, continued normal intake is the clearest evidence of tolerance. Abrupt avoidance may create uncertainty and make reintroduction more difficult.
When allergy is confirmed, avoidance should be specific. “Nut allergy” may need to be separated into peanut, cashew, pistachio, walnut, pecan, hazelnut, almond, and other foods. Some patients can safely eat selected nuts, while others choose broader avoidance because of cross-contact or identification difficulties. The decision is individualized.
A dietitian can protect nutrition when milk, egg, wheat, soy, or multiple foods are removed. Children need monitoring of growth, protein, calories, calcium, vitamin D, iron, and other nutrients according to the excluded foods.
People at risk of systemic reactions should receive an emergency action plan and epinephrine when indicated. Antihistamines can help itching or hives but do not replace epinephrine for breathing difficulty, throat swelling, faintness, or a rapidly progressing multi-system reaction.
For follow-up, bring the complete panel, not a handwritten list of positives. Mark which foods are eaten safely, which caused immediate symptoms, and which have never been tried. This turns a confusing panel into a set of separate clinical questions.
The review may result in different actions for different foods. One result may support continued avoidance, another may lead to component testing, and a third may be dismissed because the food is eaten normally. A food never introduced may require a supervised challenge or structured introduction, depending on the value and risk factors. Treating the entire panel as one diagnosis loses these distinctions and can leave the patient with a longer allergy list than the evidence supports for safe, practical long-term care for each patient.
Repeat testing is not needed on a fixed schedule for every food. Trends can support reassessment for allergies that often resolve, but a falling number does not prove tolerance. Challenge timing depends on age, history, prior value, component pattern, skin testing, and family readiness.
A high-quality food allergy evaluation aims to identify the smallest accurate list of foods that truly need avoidance. That protects patients from reactions without sacrificing foods, nutrition, and daily life unnecessarily.
References
- EAACI guidelines on the diagnosis of IgE-mediated food allergy 2023 (Guideline)
- Systematic review and meta-analyses on the accuracy of diagnostic tests for IgE-mediated food allergy 2024 (Systematic Review)
- Diagnosing IgE-mediated food allergy: How to apply the latest guidelines in clinical practice 2025 (Review)
- EAACI guidelines on the management of IgE-mediated food allergy 2025 (Guideline)
- A review of food allergy panels and their consequences 2023 (Review)
- Novel diagnostics in food allergy 2025 (Review)
Disclaimer
This article is educational and does not diagnose food allergy or establish that a food is safe. Do not remove tolerated foods or perform a home challenge after a suspected reaction without individualized clinical advice. Use epinephrine as prescribed and seek emergency care for symptoms of anaphylaxis.