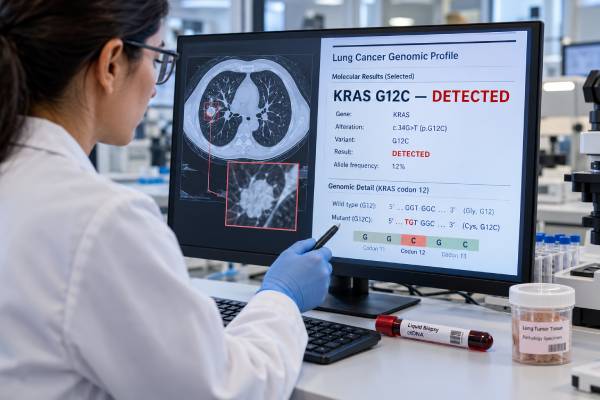
A KRAS G12C test looks for a specific tumor alteration that can help define the biology of non-small cell lung cancer (NSCLC) and, in many cases, guide treatment. The test does not measure how much cancer is present, and it is not a screening test for people without a lung-cancer diagnosis. Instead, it analyzes DNA, RNA, or a related molecular signal from a tumor sample or from circulating tumor DNA (ctDNA) in blood. The cysteine created by G12C forms a binding site for covalent inhibitors that preferentially trap KRAS G12C in its inactive GDP-bound state. The exact wording of the laboratory report matters because a gene can have many different alterations with different clinical meanings. A positive result can be highly informative, while a negative result must be interpreted in light of specimen quality, tumor content, assay coverage, and the rest of the biomarker profile. For advanced NSCLC, molecular results are best read together with histology, stage, PD-L1 testing, imaging, prior therapy, and the patient’s overall clinical situation.
- What it tests: a glycine-to-cysteine substitution at codon 12, usually reported as KRAS p.G12C.
- Positive result: A pathogenic KRAS G12C result defines a therapeutically relevant molecular subtype of NSCLC. It should not be confused with other KRAS variants such as G12D, G12V, or Q61 mutations.
- Negative result: A negative G12C result excludes that specific variant within the assay’s limits, not all KRAS mutations and not all actionable lung-cancer alterations.
- How it is tested: broad DNA NGS, targeted PCR, digital PCR, and plasma ctDNA NGS or targeted assays.
- No normal range: this is a mutation/fusion status test, so results are usually reported as detected/positive, not detected/negative, or occasionally indeterminate rather than as a blood concentration.
Table of Contents
- What the KRAS G12C test measures
- Why and when the test is ordered
- How testing is done: tissue, blood, and assay methods
- How to interpret positive, negative, and indeterminate results
- What the molecular result means for the cancer
- How the result can affect treatment and monitoring
- Limitations, false negatives, and discordant results
- Practical next steps after the result
What the KRAS G12C test measures
The test asks a molecular yes-or-no question: is a glycine-to-cysteine substitution at codon 12, usually reported as KRAS p.G12C present in the cancer cells represented by the specimen? This is different from a routine blood chemistry test. There is no healthy “target level” to reach and no numeric therapeutic range. The result is usually described with terms such as detected, positive, not detected, negative, pathogenic, likely pathogenic, or variant of uncertain significance.
KRAS G12C shifts signaling toward the active RAS-MAPK state. Co-mutations such as TP53, STK11, or KEAP1 can influence tumor biology but do not change the basic definition of a G12C-positive result. The cysteine created by G12C forms a binding site for covalent inhibitors that preferentially trap KRAS G12C in its inactive GDP-bound state. That is why the exact variant or fusion should appear in the report rather than only the gene name. Two tumors can both have an alteration in KRAS yet have different drug sensitivity, evidence levels, or resistance behavior.
In lung cancer, the alteration is usually somatic, meaning it developed in the tumor and is not automatically inherited. Tumor-only sequencing can occasionally identify a change that might also be present in the germline, but a tumor result by itself is not a hereditary-cancer diagnosis. If a molecular report raises a genuine germline concern, a clinician or genetics professional can decide whether testing blood or saliva with a dedicated hereditary-cancer assay is appropriate.
The alteration is found in around 13% of lung adenocarcinomas in many Western cohorts and roughly 35%–45% of KRAS-mutant NSCLC, with prevalence varying across populations. Prevalence estimates are useful for context, but they should never be used to decide that testing is unnecessary for an individual solely because of age, sex, smoking history, or ancestry. Modern NSCLC care increasingly relies on broad biomarker testing because clinically important drivers can occur outside their “typical” demographic patterns.
Why and when the test is ordered
The main reason to order the test is to identify a molecular feature that may change treatment selection. It is most commonly part of the initial workup for advanced non-squamous NSCLC and may also be relevant in selected earlier-stage disease, depending on the biomarker and treatment setting. Many centers now use lung cancer NGS testing rather than ordering one gene at a time because a single panel can evaluate multiple mutations, fusions, copy-number changes, and sometimes additional genomic features from the same limited biopsy.
Testing is also important because starting systemic treatment before key driver results are known can complicate sequencing. A tumor with an actionable oncogenic driver may have a preferred targeted treatment strategy that differs from the pathway used for a tumor without that driver. PD-L1 expression is useful for immunotherapy decisions, but high PD-L1 does not erase the significance of a strong oncogenic driver.
A second common reason to test is progression after targeted therapy. Cancer cells evolve under treatment pressure, and resistant subclones can become detectable. Resistance to KRAS G12C inhibition can involve new KRAS changes, pathway reactivation, bypass signaling, or histologic evolution. Broader repeat profiling can identify mechanisms that a single-gene G12C test would miss. In that setting, the laboratory question may be broader than simply “is the original driver still present?” A resistance-oriented panel can look for new on-target mutations, bypass signaling, gene amplification, and other changes that may explain why a once-effective drug stopped working.
Testing may also be repeated when the original sample was too small, had too little viable tumor, produced an indeterminate result, or was analyzed with an older limited assay. Repeating a technically weak negative result is different from repeating a high-quality comprehensive negative result; the former can correct an information gap, while the latter should be driven by a clear clinical reason.
How testing is done: tissue, blood, and assay methods
Most KRAS G12C testing starts with tumor tissue from a core biopsy, surgical specimen, cytology cell block, or another validated tumor sample. The pathology laboratory first confirms that the specimen contains enough cancer cells and enough DNA or RNA. Small lung biopsies are precious because the same tissue may be needed for diagnosis, immunohistochemistry, PD-L1, and broad molecular testing.
Common methods include broad DNA NGS, targeted PCR, digital PCR, and plasma ctDNA NGS or targeted assays. Broad NGS is useful at diagnosis because it shows the KRAS variant and co-mutations while also testing other driver genes. Targeted assays can rapidly answer whether G12C is present but provide less information about the rest of the tumor. Plasma testing can be helpful when tissue is insufficient, but a negative plasma result may need tissue confirmation. The method listed on the report is not a minor technical detail; it helps explain what the assay can detect and what a negative result truly means.
A blood-based PD-L1 testing analyzes cell-free DNA, a fraction of which may come from tumor cells. Blood collection is less invasive and can be faster than arranging another biopsy. It can also sample DNA shed from multiple tumor sites, which may reveal heterogeneity that one needle biopsy misses. However, the concentration of ctDNA varies. Some cancers shed abundant DNA into plasma; others shed little or none at a given time.
For that reason, a positive plasma result for a well-established pathogenic driver is often clinically useful, while a negative plasma result may need follow-up tissue testing when the pretest probability is meaningful and tissue can be safely obtained. Tissue has another advantage at progression: a pathologist can examine cell shape and architecture, making it possible to identify histologic transformation that plasma DNA alone cannot show.
Before testing, patients usually do not need to fast or stop medications for a tumor molecular assay. The more important preparation is logistical: confirming which specimen will be tested, whether the laboratory has adequate tumor content, and whether both DNA and RNA testing are needed for comprehensive coverage.
How to interpret positive, negative, and indeterminate results
A positive result means the laboratory detected a reportable alteration above its validated threshold. A pathogenic KRAS G12C result defines a therapeutically relevant molecular subtype of NSCLC. It should not be confused with other KRAS variants such as G12D, G12V, or Q61 mutations. The report should ideally include the gene, exact variant or fusion, classification, assay method, and a concise statement about clinical significance. For NGS, the report may also show variant allele frequency (VAF), but VAF is not the same as the percentage of cancer in the body and should not be interpreted as a tumor-burden score.
A negative result means the assay did not detect the alteration within its tested regions and sensitivity. A negative G12C result excludes that specific variant within the assay’s limits, not all KRAS mutations and not all actionable lung-cancer alterations. The most useful next question is not simply “negative or positive?” but “negative by what method, in what specimen, with what tumor content, and with what coverage?” A high-quality broad test on a tumor-rich specimen carries more confidence than a limited test on scant material.
An indeterminate, inconclusive, or quantity-not-sufficient result is not the same as a true negative. It may reflect degraded nucleic acid, insufficient tumor, low DNA/RNA yield, assay quality-control failure, or a borderline signal. The usual response is to consider another block, another specimen, a different method, or a blood assay depending on what is feasible.
A variant of uncertain significance (VUS) should not be treated as if it were an established driver. A VUS means current evidence is insufficient to classify the change as pathogenic or benign. Treatment decisions should be based on validated actionable alterations and the complete clinical picture. Reclassification can occur as databases and evidence mature.
When tissue and plasma disagree, timing matters. A plasma sample drawn months after a tissue biopsy can reflect a later molecular state. Conversely, a low-shedding tumor can be tissue-positive and plasma-negative. The goal is to reconcile the results biologically, not to assume one specimen type is always superior.
What the molecular result means for the cancer
The cysteine created by G12C forms a binding site for covalent inhibitors that preferentially trap KRAS G12C in its inactive GDP-bound state. In practical terms, an important molecular alteration can explain abnormal cancer growth or acquired drug resistance. It does not by itself tell how large the tumor is, whether it has spread, how fast it will grow in one individual, or exactly how long a treatment will work. Stage and imaging answer anatomic questions; molecular testing answers a different question about tumor biology.
KRAS G12C shifts signaling toward the active RAS-MAPK state. Co-mutations such as TP53, STK11, or KEAP1 can influence tumor biology but do not change the basic definition of a G12C-positive result. This distinction becomes important when a report lists several changes. A broad NGS panel may show a dominant driver plus tumor-suppressor mutations, copy-number changes, and uncertain variants. The clinically important task is to identify which findings are established therapeutic drivers, which are resistance markers, which are prognostic or investigational, and which should not influence care.
Most strong oncogenic drivers in untreated lung adenocarcinoma are relatively uncommon together, but “mutually exclusive” is not an absolute rule. Co-alterations can occur, especially after treatment or when one finding is subclonal. Unexpected combinations deserve careful review of the sequencing data, tumor purity, specimen timing, and sometimes confirmation by an alternative method.
A positive result also does not automatically predict response to every drug that targets the same gene in another cancer type. Drug sensitivity depends on tumor type, exact alteration, drug mechanism, evidence from clinical trials, regulatory approvals, and treatment line. Lung-cancer-specific evidence is therefore more useful than simply matching a gene name to a drug name.
How the result can affect treatment and monitoring
Direct KRAS G12C inhibitors have made this mutation actionable in advanced NSCLC. Treatment selection still depends on prior therapy, PD-L1 status, symptoms, disease burden, comorbidities, brain metastases, and current regulatory guidance rather than the mutation alone. The molecular report is one input to treatment choice, not a prescription by itself. Oncologists also consider stage, symptoms, performance status, organ function, brain metastases, previous therapy, drug interactions, toxicity risks, patient preferences, and whether a clinical trial is appropriate.
In advanced disease, a confirmed actionable molecular finding can change the order in which therapies are used. This is why comprehensive testing should ideally be completed before first-line systemic therapy whenever the clinical situation allows. If a patient is very symptomatic and treatment must begin quickly, clinicians may use bridging strategies while awaiting results, but the molecular profile should still be completed.
Monitoring after treatment usually relies on symptoms, examination, and imaging rather than repeatedly measuring the mutation as a simple blood “level.” ctDNA can sometimes provide additional information, but routine schedules and validated uses vary by disease stage and clinical setting. A fall in ctDNA can be encouraging, yet it is not a substitute for standard imaging unless the care plan specifically incorporates a validated molecular-monitoring approach.
At progression, Resistance to KRAS G12C inhibition can involve new KRAS changes, pathway reactivation, bypass signaling, or histologic evolution. Broader repeat profiling can identify mechanisms that a single-gene G12C test would miss. If the clinical question is acquired resistance, ctDNA testing may provide more value than a narrow single-gene assay. The best specimen depends on what needs to be learned: plasma is convenient for genomic changes, while tissue can reveal both genomics and histology.
Limitations, false negatives, and discordant results
Every molecular test has a limit of detection and a defined coverage map. A false negative can occur when the specimen contains too few tumor cells, DNA or RNA is degraded, the alteration lies outside the assay’s target regions, ctDNA concentration is below detection, or bioinformatic filters fail to call a complex event. These problems are especially important in small biopsies, decalcified bone samples, heavily treated tissue, and low-volume disease.
Pre-analytic handling matters. Strong-acid bone decalcification can damage nucleic acids. Long delays before fixation, over-fixation, very old blocks, and low cellularity can reduce test success. RNA is particularly vulnerable to degradation, which matters for fusion testing. Laboratories use quality-control metrics to decide whether a result is reportable; an assay failure should not be silently interpreted as biologic absence.
Different methods also have different strengths. A targeted assay can be exquisitely sensitive for a known hotspot yet blind to uncommon variants. DNA NGS can cover many mutations and copy-number changes but may have difficulty with certain gene fusions. RNA NGS can confirm an expressed fusion but requires adequate RNA. IHC can be a powerful protein-level surrogate for selected biomarkers but is not interchangeable with DNA sequencing for all genes.
A second limitation is clinical interpretation. The science evolves faster than many static reports. A variant classified as uncertain today may acquire evidence later, and treatment recommendations can change as new trials mature. For rapidly evolving targets, the care team should interpret the molecular result using current guidelines rather than relying only on an older report’s therapy list.
Finally, a molecular result cannot replace pathology. The diagnosis of lung adenocarcinoma, squamous carcinoma, small cell carcinoma, or another tumor type depends on morphology and immunophenotype. Molecular testing adds a biologic layer; it does not independently establish the entire diagnosis.
Practical next steps after the result
A useful result should lead to a short, concrete set of questions for the treating team. First, confirm the exact alteration and whether the laboratory classified it as pathogenic or actionable. Second, ask whether the specimen and assay were adequate enough to trust a negative result. Third, make sure the rest of the recommended NSCLC biomarkers have been completed rather than stopping after one positive or negative gene test.
If the result is positive, ask what treatment options are supported for the specific disease stage and line of therapy, and whether the recommendation is standard care or a clinical-trial option. If the result is negative or indeterminate, ask whether broader testing, RNA testing, another tissue block, or plasma testing would fill an important gap. When progression occurs, ask whether the next biopsy should be chosen to study resistance, histologic transformation, or both.
It is also worth keeping a copy of the full molecular report, not just the patient-portal summary. The full report contains the specimen date, tumor source, method, quality metrics, exact variant, and sometimes the assay’s limit of detection. Those details become valuable if care moves to another center or if a later result needs to be compared with the original tumor profile.
For a broader picture of how multiple drivers and PD-L1 fit together, NSCLC biomarker profiling can help explain why one molecular result is only part of the final treatment plan. Molecular testing is most useful when it is integrated with pathology, imaging, clinical history, and up-to-date treatment evidence rather than interpreted in isolation.
Questions to ask about the laboratory report
- Was the result obtained from tissue, cytology, or plasma ctDNA?
- What testing method was used, and did it cover the full alteration type of interest?
- Was tumor content adequate, and did the sample pass quality-control metrics?
- Is the finding pathogenic/actionable, uncertain, or likely benign?
- Were other recommended lung-cancer biomarkers tested at the same time?
- If the result is negative, would a second specimen or complementary method materially change confidence?
- If the cancer has progressed, does the current test address acquired resistance or only the original driver?
References
- KRASG12C Inhibitors in Non-Small Cell Lung Cancer: A Review 2024 (Review)
- Targeting KRASG12C in Non-Small-Cell Lung Cancer: Current Standards and Developments 2024 (Review)
- KRAS G12C-mutant driven non-small cell lung cancer (NSCLC) 2024 (Review)
- Literature review of advances and challenges in KRAS G12C mutant non-small cell lung cancer 2025 (Review)
- Therapy for Stage IV Non-Small Cell Lung Cancer With Driver Alterations: ASCO Living Guideline, Version 2026.3.3. 2026 (Guideline)
- Oncogene-addicted metastatic non-small-cell lung cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up 2023 (Guideline)
Disclaimer
This article provides general education about KRAS G12C testing in lung cancer and does not replace interpretation by an oncologist, pathologist, or molecular laboratory. Treatment choices and the significance of a positive or negative result depend on the exact variant, specimen, disease stage, prior therapy, current guidelines, and individual medical circumstances.