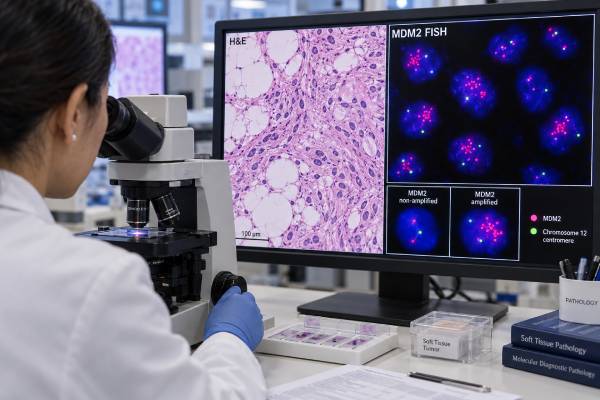
An MDM2 amplification test checks whether tumor cells contain many extra copies of the MDM2 gene. The test is especially useful when a pathologist needs to distinguish atypical lipomatous tumor/well-differentiated liposarcoma (ALT/WDLPS) or dedifferentiated liposarcoma (DDLPS) from benign fatty tumors and other sarcomas. Fluorescence in situ hybridization (FISH) is a widely used method because it can compare MDM2 signals with a chromosome 12 reference signal directly in tumor nuclei. A true focal amplification pattern strongly supports ALT/WDLPS or DDLPS in the appropriate morphologic and anatomic setting. However, increased MDM2 signal count alone is not enough: chromosome 12 polysomy can raise both MDM2 and control-probe signals without true amplification. The most reliable interpretation combines the MDM2-to-reference ratio, absolute signal pattern, tumor morphology, location, imaging, and specimen quality rather than treating any copy-number gain as diagnostic.
- A positive MDM2 amplification result strongly supports ALT/WDLPS or DDLPS when the tumor’s morphology and location fit those diagnoses.
- FISH usually compares MDM2 signals with a chromosome 12 control such as CEP12; extra signals without an increased ratio may represent polysomy rather than focal amplification.
- A negative MDM2 result makes ALT/WDLPS or DDLPS less likely but does not exclude every liposarcoma subtype, because myxoid and pleomorphic liposarcomas usually do not show MDM2 amplification.
- MDM2 immunohistochemistry is not identical to gene amplification testing and can be falsely positive or negative; FISH is often preferred in difficult adipocytic tumors.
- Borderline, heterogeneous, or technically poor FISH results may require recounting, testing another block, or using a second molecular method.
Table of Contents
- What MDM2 Amplification Means
- Why the Test Is Ordered
- How FISH and Other Methods Work
- How to Read MDM2 Results
- Liposarcoma Diagnosis and Differential
- Pitfalls, Borderline Results, and Heterogeneity
- What Happens After the Result
What MDM2 Amplification Means
MDM2 is an oncogene on chromosome 12q15. Its protein product negatively regulates the tumor-suppressor protein p53. When MDM2 is highly amplified, tumor cells may produce excess MDM2 protein, weakening p53-mediated cell-cycle arrest and apoptosis and helping abnormal cells survive.
The best-known tumors with MDM2 amplification are atypical lipomatous tumor/well-differentiated liposarcoma and dedifferentiated liposarcoma. These tumors often contain large ring or marker chromosomes derived from chromosome 12 and frequently co-amplify nearby genes such as CDK4. Because this molecular pattern is so characteristic, MDM2 amplification is an important diagnostic tool when microscopy alone is uncertain.
“Amplification” is more specific than simply having an increased copy number. Tumor cells can gain an entire chromosome or chromosome segment, producing additional MDM2 copies without the focal, high-level increase typical of ALT/WDLPS and DDLPS. FISH addresses this problem by comparing the number of MDM2 signals with a reference probe, commonly the centromeric region of chromosome 12.
The distinction matters because a deep-seated lipoma and an ALT/WDLPS can look very similar on imaging and histology but have different behavior and management. ALT/WDLPS is locally aggressive and can recur; the term “well-differentiated liposarcoma” is commonly used for tumors at sites such as the retroperitoneum where complete removal can be difficult. DDLPS contains a non-lipogenic sarcoma component and carries a greater risk of metastasis and disease-related mortality.
Why the Test Is Ordered
MDM2 testing is usually ordered because the pathologist is trying to resolve a specific diagnostic problem, not as a general cancer-screening test.
Common situations include a large deep fatty mass, a retroperitoneal or pelvic lipomatous tumor, a recurrent lesion previously called a lipoma, equivocal atypia on histology, or a high-grade sarcoma in which dedifferentiated liposarcoma is in the differential diagnosis. MDM2 testing can also be useful when a small biopsy samples only a non-lipogenic area and imaging suggests that a fatty component may be present elsewhere in the mass.
A classic example is a large retroperitoneal tumor. Benign lipomas are much less common in that location than in superficial soft tissue, and ALT/WDLPS or DDLPS must be considered. If the biopsy shows mature fat with only subtle nuclear atypia, MDM2 amplification can provide strong molecular support for the diagnosis.
Another example is a high-grade spindle-cell or pleomorphic sarcoma near a large fatty mass. DDLPS may lose obvious adipocytic differentiation in the high-grade component, so molecular confirmation can help distinguish it from other sarcoma types.
When testing may be unnecessary
Not every lipoma needs MDM2 FISH. A small, superficial, clinically typical lipoma with classic benign histology usually does not require molecular confirmation. Testing is most valuable when the clinical setting, tumor size, depth, location, recurrence, imaging, or microscopic features create genuine uncertainty.
MDM2 testing should also not be used to force every liposarcoma into the ALT/WDLPS or DDLPS category. Other liposarcoma subtypes have different defining molecular features. Myxoid liposarcoma, for example, is characterized by a DDIT3 rearrangement rather than MDM2 amplification.
How FISH and Other Methods Work
Fluorescence in situ hybridization (FISH) is widely used for MDM2 because it evaluates gene copy number directly in individual tumor cell nuclei. Thin sections of formalin-fixed, paraffin-embedded tissue are treated with fluorescent DNA probes. One probe binds the MDM2 locus and a second probe commonly binds a chromosome 12 centromeric reference region.
The technologist or pathologist counts signals in a defined number of tumor nuclei. The laboratory then calculates an MDM2-to-reference ratio and reviews the pattern. True high-level amplification often produces numerous MDM2 signals or dense signal clusters with relatively few reference signals.
There is no single universal cutoff used by every laboratory. Many assays consider a ratio around or above 2 to support amplification, but laboratories validate their own criteria, minimum nuclei counted, handling of clustered signals, and rules for equivocal cases. The report’s interpretation and method section therefore matter more than applying an outside cutoff to raw numbers.
Other methods
Copy-number amplification can also be assessed by NGS, array-based methods, digital PCR, or other molecular approaches. NGS has the advantage of evaluating many genes at once, but copy-number calls depend on tumor purity, assay design, normalization, and bioinformatic thresholds. A broad NGS panel may flag MDM2 amplification, while FISH can provide direct visual confirmation in a difficult tumor.
MDM2 immunohistochemistry detects protein expression, not gene copy number. It can be useful as a screening tool, often together with CDK4 and p16, but immunostaining is imperfect. Some true ALT/WDLPS or DDLPS cases may stain weakly or negatively, while benign or non-MDM2-amplified lesions can occasionally show misleading staining. In diagnostically important borderline cases, gene-level testing is more definitive.
How to Read MDM2 Results
The result should be interpreted as one of several patterns rather than simply “many signals” or “few signals.”
Amplified
An amplified result means the laboratory found a focal increase in MDM2 relative to the chromosome reference using its validated criteria. In a compatible adipocytic tumor, this strongly supports ALT/WDLPS or DDLPS.
The result does not by itself distinguish well-differentiated from dedifferentiated disease. That distinction is primarily morphologic: DDLPS contains a transition to non-lipogenic sarcoma of variable grade. Imaging and sampling can also matter because a core biopsy may miss the dedifferentiated component.
Not amplified
A nonamplified result means the test did not show the characteristic focal amplification pattern. In a tumor being considered as ALT/WDLPS, this finding should prompt reconsideration of the diagnosis, especially if the histology is only mildly atypical.
However, “MDM2 not amplified” does not mean “not liposarcoma.” Myxoid liposarcoma, pleomorphic liposarcoma, and other rare liposarcoma types generally lack MDM2 amplification. Their diagnosis depends on morphology and, when needed, different molecular tests.
Polysomy or increased copy number without amplification
One of the most important pitfalls is polysomy, in which tumor cells carry extra copies of chromosome 12. In this setting, both MDM2 and the centromeric reference probe may increase. The absolute MDM2 signal count can look impressive, but the ratio remains relatively balanced.
That pattern should not be called focal MDM2 amplification simply because more than two MDM2 signals are present. The distinction between polysomy and amplification is why the control probe and ratio are essential.
Equivocal or borderline
Borderline results may occur when ratios sit near the laboratory cutoff, signal clusters are difficult to count, tumor cells are sparse, or different areas show different patterns. An equivocal result is not the same as positive. The pathologist may recount more nuclei, test a different block, repeat FISH, or use another method.
Liposarcoma Diagnosis and Differential
MDM2 amplification is most useful when combined with morphology and anatomy.
ALT/WDLPS versus lipoma
A conventional lipoma is benign and lacks the characteristic MDM2 amplification of ALT/WDLPS. Histologically, ALT/WDLPS may show variation in adipocyte size, fibrous septa, and enlarged atypical stromal cell nuclei, but these features can be focal and subtle. Small biopsies may therefore be difficult.
Tumor location changes the diagnostic threshold. A superficial small fatty mass with classic benign features is much more likely to be an ordinary lipoma. A deep, large, recurrent, retroperitoneal, pelvic, or intra-abdominal fatty mass deserves greater scrutiny and often molecular confirmation when morphology is not definitive.
DDLPS versus other high-grade sarcomas
DDLPS can mimic undifferentiated pleomorphic sarcoma, myxofibrosarcoma, leiomyosarcoma, malignant peripheral nerve sheath tumor, and other high-grade sarcomas. Demonstrating MDM2 amplification can be decisive when imaging or histology suggests a well-differentiated lipomatous component.
Still, MDM2 amplification is not absolutely unique to liposarcoma. It can occur in a smaller number of other tumors, including some osteosarcomas and other malignancies. Therefore, a positive molecular result must fit the anatomic and morphologic context rather than replace pathology review.
ALT versus WDLPS terminology
ALT and WDLPS describe essentially the same molecular tumor family, but terminology reflects the ability to achieve complete local control. In surgically accessible extremity or superficial sites, the term atypical lipomatous tumor emphasizes its predominantly local behavior. In the retroperitoneum or other difficult sites, well-differentiated liposarcoma is often used because repeated local recurrence and dedifferentiation can create substantial morbidity and mortality.
Pitfalls, Borderline Results, and Heterogeneity
Technical and biologic factors can complicate MDM2 FISH.
Poor fixation, thick sections, nuclear truncation, overlapping nuclei, autofluorescence, and signal loss can make counts unreliable. The pathologist must ensure that the counted nuclei belong to the tumor rather than inflammatory cells, endothelial cells, or normal adipocytes.
Signal clusters also require judgment. In high-level amplification, individual MDM2 signals can merge into dense clusters that cannot be counted precisely. Laboratories may use standardized rules for assigning approximate counts or classifying clusters as amplification.
Tumor heterogeneity creates another challenge. A large DDLPS can contain well-differentiated fatty areas, dedifferentiated solid areas, necrosis, and regions with variable cellularity. Testing a nonrepresentative block can create an unhelpful result, especially if the biopsy contains little viable tumor. Correlation with imaging and gross pathology can guide block selection.
The MDM2/CEP12 ratio should also be interpreted with absolute copy number. Rare unusual patterns can produce discordant metrics, such as very high MDM2 counts accompanied by increased CEP12 or low reference signals caused by technical loss. When the numerical ratio and visual pattern disagree, molecular pathology review is appropriate.
Finally, MDM2 protein overexpression should not be substituted automatically for amplification. Negative immunostaining does not fully exclude amplification, and positive staining can occur without the characteristic gene-level change.
What Happens After the Result
If MDM2 is amplified and the pathology supports ALT/WDLPS or DDLPS, management usually focuses on tumor location, resectability, grade, recurrence risk, and metastatic status. Surgery is central for localized disease when feasible. Retroperitoneal tumors often require multidisciplinary planning because complete resection can involve adjacent organs and local recurrence is a major concern.
The molecular result is primarily diagnostic, not a stand-alone treatment prescription. MDM2 itself is an active therapeutic research target, and several MDM2-p53 pathway drugs have been studied, but an amplified result should not be interpreted as an automatic indication for an approved MDM2 inhibitor.
If the result is negative but clinical suspicion remains high, the next step depends on the differential diagnosis. The pathologist may review additional tumor sections, test another block, order DDIT3 testing for suspected myxoid liposarcoma, or use broader molecular profiling. A negative result can also support a benign diagnosis when morphology and imaging are reassuring.
For an equivocal result, useful questions include:
- What was the reported MDM2/reference ratio and absolute signal pattern?
- Did the laboratory describe polysomy, clustering, or technical limitations?
- Was the tested block representative of the suspicious tumor area?
- Does the morphology fit ALT/WDLPS or DDLPS?
- Would repeat testing or another method materially change management?
The final diagnosis should come from an integrated pathology report, not from the FISH number alone.
Practical examples of FISH interpretation
Imagine a tumor in which nuclei show an average of 12 MDM2 signals and 2 CEP12 signals. That pattern produces a high ratio and strongly suggests focal amplification. Now compare it with a tumor showing 8 MDM2 signals and 7 CEP12 signals. The absolute MDM2 count is still high, but the ratio is close to 1 because much of chromosome 12 has increased. The second pattern is more consistent with polysomy or broad chromosome gain than with classic focal MDM2 amplification. This is why simply reading the MDM2 copy number without the reference probe can be misleading.
Sampling can create another diagnostic trap. A large retroperitoneal DDLPS may contain a fatty well-differentiated component and a solid dedifferentiated component. A needle biopsy through the solid portion may look like an undifferentiated spindle-cell sarcoma with no visible fat. If imaging shows a large adjacent lipomatous mass, MDM2 FISH can reveal the underlying DDLPS biology. The reverse problem can also occur: a biopsy may capture only bland fat and miss the dedifferentiated component, so the pathologist still needs imaging and resection findings to grade the complete tumor accurately.
MDM2 amplification must also be interpreted in the right tumor family. A positive result in a retroperitoneal adipocytic or spindle-cell tumor is highly supportive of ALT/WDLPS or DDLPS. A positive result in a bone-forming tumor, however, can occur in a subset of osteosarcomas and should not be relabeled as liposarcoma. Molecular tests are strongest when they answer a focused differential diagnosis created by morphology and anatomy.
When FISH is technically borderline, repeating the same count without reconsidering the specimen may not solve the problem. A better approach can be to select a block with higher tumor cellularity, review the area marked for scoring, confirm that the reference probe performed normally, and compare with MDM2 copy-number information from NGS or another validated method. Discordant results should be resolved by the pathologist who can see both the slide and the molecular data.
A final reporting detail is the difference between a test result and the signed-out diagnosis. The molecular laboratory may report “MDM2 amplified,” while the surgical pathology diagnosis remains dependent on the tumor examined. If the specimen contains only a tiny atypical fatty focus, the pathologist may request more tissue before assigning a definitive grade or subtype. Molecular confirmation strengthens the diagnosis but does not replace adequate sampling.
References
- FISH Diagnostic Assessment of MDM2 Amplification in Liposarcoma: Potential Pitfalls and Troubleshooting Recommendations 2023
- Diagnosis and management of dedifferentiated liposarcoma: A multidisciplinary position statement 2024 (Position Statement)
- MDM2-p53 in liposarcoma: The need for targeted therapies with novel mechanisms of action 2024 (Review)
- Criteria for MDM2 fluorescence in situ hybridization testing in the diagnosis of well-differentiated adipocytic neoplasms: a retrospective utilization review of 1151 cases 2025
- Biology and Management of Deep-seated Atypical Lipomatous Tumor of the Extremities 2023 (Review)
- Negative MDM2/CDK4 immunoreactivity does not fully exclude MDM2/CDK4 amplification in a subset of atypical lipomatous tumor/ well differentiated liposarcoma 2022
Disclaimer
MDM2 amplification testing is a pathology tool and should be interpreted with tumor morphology, location, imaging, specimen quality, and the laboratory’s validated FISH criteria. This article is educational and does not replace a diagnosis or treatment plan from a sarcoma pathologist, surgical oncologist, medical oncologist, or multidisciplinary sarcoma team.