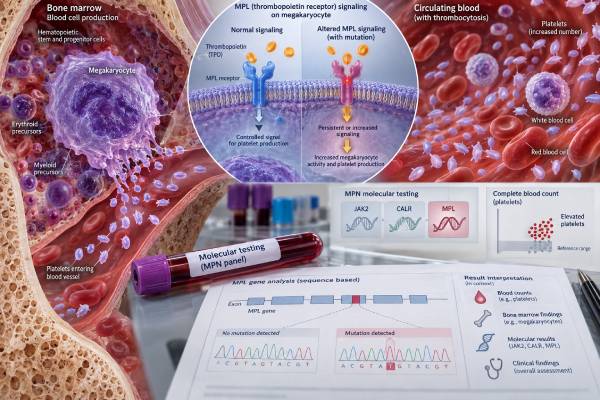
An MPL mutation test looks for activating changes in the MPL gene, which encodes the thrombopoietin receptor that helps control platelet production and blood-cell stem-cell signaling. MPL mutations are most relevant in myeloproliferative neoplasms (MPNs), especially essential thrombocythemia (ET) and primary myelofibrosis (PMF). A pathogenic MPL mutation supports a clonal myeloid disorder when the blood counts, bone marrow, and clinical findings fit, but it does not by itself distinguish ET from prefibrotic or overt PMF. The most familiar acquired variants affect codon W515 in exon 10, although other pathogenic variants occur. MPL testing is usually interpreted together with JAK2 and CALR because these three driver genes account for most classic BCR::ABL1-negative MPNs. A positive result can help establish clonality, while a negative result does not exclude MPN because some patients are “triple negative” or carry less common drivers that require broader testing.
- A positive somatic MPL mutation supports a clonal myeloproliferative neoplasm, most often ET or PMF, when clinical and bone-marrow findings agree.
- MPL W515L and W515K are classic driver mutations, but assays may detect additional pathogenic exon 10 variants.
- MPL positivity does not by itself separate ET from prefibrotic PMF; bone-marrow morphology and the complete blood picture remain essential.
- MPL mutations are uncommon compared with JAK2 or CALR and occur in only a small percentage of ET cases.
- A negative MPL result does not rule out an MPN; JAK2, CALR, broader myeloid sequencing, and nonclonal causes of thrombocytosis may still need evaluation.
Table of Contents
- What MPL Does
- Why MPL Testing Is Ordered
- How the Test Is Performed
- Positive, Negative, and Uncertain Results
- MPL in Essential Thrombocythemia
- MPL in Primary Myelofibrosis
- Limitations, Prognosis, and Next Steps
What MPL Does
MPL encodes the receptor for thrombopoietin, a hormone that regulates megakaryocytes and platelet production and also supports hematopoietic stem cells. When thrombopoietin binds MPL, the receptor activates intracellular pathways, especially JAK-STAT signaling, that tell cells to survive, proliferate, and mature.
An activating MPL mutation can keep this signaling pathway turned on without normal control. In a hematopoietic stem-cell clone, persistent signaling can produce excess megakaryocytes, abnormal platelet production, marrow fibrosis, or other features of an MPN.
The classic acquired mutations occur in exon 10, especially at codon 515. Common examples include MPL W515L and MPL W515K. Other substitutions at or near this region can also be pathogenic. The exact assay matters because an older hotspot test may detect only a few variants, whereas next-generation sequencing (NGS) can identify a broader spectrum.
Most clinically detected MPL mutations in ET and PMF are somatic, meaning they arose in the abnormal blood-cell clone and were not inherited. Rare germline MPL variants can cause hereditary thrombocytosis or other inherited platelet disorders, so an unusual result, very high allele fraction, or strong multigenerational family history may require separate germline evaluation.
Why MPL Testing Is Ordered
MPL testing is most commonly ordered during evaluation of persistent thrombocytosis, suspected myelofibrosis, or another possible BCR::ABL1-negative MPN.
A platelet count of at least 450 × 10^9/L is part of the diagnostic framework for essential thrombocythemia, but a high platelet count alone does not establish ET. Reactive thrombocytosis is common and can result from iron deficiency, infection, inflammation, surgery, splenectomy, tissue injury, or cancer. The first goal is therefore to determine whether the elevated platelet count is reactive or clonal.
Molecular testing helps because classic MPNs frequently carry one of three major driver abnormalities: JAK2, CALR, or MPL. In ET, JAK2 is the most common driver, CALR is next, and MPL accounts for only a small minority. In PMF, the same three genes are central to diagnosis, although additional mutations can affect prognosis.
Testing strategies vary. Some laboratories use a reflex sequence: JAK2 V617F first, then CALR and MPL if JAK2 is negative. Others use an NGS panel that tests all relevant genes at once. Both approaches can be appropriate depending on turnaround time, cost, and the clinical question.
MPL testing may also be ordered when a bone marrow biopsy suggests an MPN but JAK2 and CALR are negative, or when the clinician wants to establish clonality in a patient whose platelet elevation could otherwise be explained by a reactive process.
How the Test Is Performed
MPL testing usually uses DNA from peripheral blood or bone marrow. A standard blood draw is often sufficient, and no fasting is required. Bone marrow is generally obtained for morphologic diagnosis rather than because MPL specifically requires marrow.
Targeted PCR assays can detect common exon 10 variants quickly. Sanger sequencing covers a broader region but has lower sensitivity for small mutant clones. NGS panels can detect multiple MPN-associated genes at low variant allele frequencies and are useful when the initial driver tests are negative or when prognostic information is needed.
The report may include the exact variant, the exon, a pathogenicity classification, and a variant allele frequency (VAF). VAF is the fraction of sequencing reads with the mutation. A VAF around 50% can occur with a heterozygous mutation in a large clone, but the number is affected by clone size, copy-neutral loss of heterozygosity, normal-cell admixture, and other genomic events.
Somatic versus germline questions
A peripheral-blood result reflects blood cells, so it cannot automatically distinguish a somatic blood-cell mutation from a germline variant present throughout the body. For common MPN driver variants such as W515L or W515K in the appropriate setting, a somatic origin is usually expected. If hereditary thrombocytosis is suspected, germline confirmation should use a nonhematopoietic specimen selected by a genetics or hematology team.
Saliva can contain blood-derived leukocytes and may not be an ideal “normal” sample for some hematologic malignancy questions. Cultured skin fibroblasts or another validated nonhematopoietic source may be preferred in specialized workups.
Positive, Negative, and Uncertain Results
Positive pathogenic MPL mutation
A pathogenic MPL mutation provides molecular evidence of clonality. In a patient with sustained thrombocytosis or myelofibrosis features, it supports an MPN diagnosis.
The mutation alone is not enough to name the MPN. ET and PMF can both carry MPL mutations. Polycythemia vera is overwhelmingly associated with JAK2 rather than MPL. The final diagnosis requires integration of blood counts, bone-marrow morphology, splenomegaly, lactate dehydrogenase, anemia, leukoerythroblastosis, fibrosis grade, and exclusion of other myeloid neoplasms.
Negative result
A negative MPL test means no reportable mutation was found within the tested regions and sensitivity. It does not exclude ET or PMF. Many patients carry JAK2 or CALR instead, and a minority lack all three classic drivers.
Patients negative for JAK2, CALR, and MPL are often described as triple-negative. This is a molecular description, not a separate diagnosis. Broader NGS may identify other clonal mutations, but age-related clonal hematopoiesis can also produce mutations in genes such as TET2, DNMT3A, or ASXL1 without proving a specific MPN. Morphology remains crucial.
Variant of uncertain significance
An MPL VUS should not be treated as a confirmed driver. Some rare variants near the transmembrane or juxtamembrane region may later prove functional, but classification requires laboratory evidence, population data, published cases, and disease context.
A VUS can be especially difficult in patients with mild thrombocytosis. The safest approach is to interpret the blood counts and marrow independently rather than allowing an uncertain DNA change to force an MPN diagnosis.
MPL in Essential Thrombocythemia
Essential thrombocythemia is a chronic MPN characterized by sustained thrombocytosis and a proliferation of mature enlarged megakaryocytes in the bone marrow. The diagnosis requires exclusion of other myeloid neoplasms and reactive causes.
MPL mutations are found in roughly 3% to 5% of ET, although exact frequencies vary by cohort and assay. The finding supports clonality and activates the same broad JAK-STAT signaling network used by JAK2 and CALR-mutant disease.
Platelet count and symptoms
The mutation does not predict a specific platelet count. Some patients have modest thrombocytosis, while others have counts well above 1,000 × 10^9/L. Clinical risk is not determined by the count alone.
The major long-term clinical concern in ET is thrombosis, including arterial events such as stroke and myocardial infarction and venous events such as deep-vein thrombosis or splanchnic-vein thrombosis. Bleeding can also occur, particularly with extreme thrombocytosis and acquired von Willebrand disease.
Current thrombosis-risk models give particular weight to age, prior thrombosis, and JAK2 status. MPL is not used in exactly the same way as JAK2 for thrombosis-risk assignment. Some studies associate MPL with greater risk of later fibrotic transformation, but this is not a stand-alone treatment rule.
ET versus prefibrotic PMF
One of the most important interpretation points is that MPL positivity does not prove ET. Prefibrotic primary myelofibrosis can present with thrombocytosis and an MPL mutation but has different marrow morphology and prognosis. Expert bone-marrow review looks at megakaryocyte shape and clustering, cellularity, granulocytic proliferation, erythropoiesis, fibrosis, and accompanying clinical features.
Calling an MPL-positive patient “ET” without adequate marrow assessment can therefore miss prefibrotic PMF.
MPL in Primary Myelofibrosis
Primary myelofibrosis is an MPN characterized by abnormal megakaryocytic proliferation and, in overt disease, progressive marrow fibrosis. Patients may develop anemia, constitutional symptoms, enlarged spleen, circulating immature blood cells, and reduced marrow function.
MPL mutations are present in a minority of PMF cases. As in ET, the finding establishes a major clonal driver but does not determine disease stage or prognosis by itself.
Prognostic models for PMF incorporate clinical variables, cytogenetics, and additional molecular abnormalities. High-risk mutations in genes such as ASXL1, SRSF2, EZH2, IDH1, IDH2, and others may influence survival or leukemic transformation risk depending on the model used. Therefore, an NGS panel can provide information beyond the primary driver mutation.
The presence of MPL does not imply that a drug directly targeting MPL is standard therapy. MPN treatment often targets downstream JAK signaling and disease manifestations. JAK inhibitors can improve splenomegaly and symptoms in appropriate patients regardless of whether the driver is JAK2, CALR, or MPL.
For transplant decisions, the full disease-risk profile, age, comorbidities, donor availability, symptoms, blood counts, and molecular features matter far more than MPL status alone.
Limitations, Prognosis, and Next Steps
The main limitation of MPL testing is overinterpretation. A positive result is strong evidence of a clonal myeloid process, but it is not a complete diagnosis or risk score. A negative result is also incomplete unless the rest of the MPN molecular workup and marrow findings are known.
Common pitfalls include:
- ordering only a narrow W515 hotspot assay and assuming all other MPL variants were excluded;
- diagnosing ET from an MPL mutation without considering prefibrotic PMF;
- treating a VUS as a pathogenic driver;
- assuming the VAF equals the percentage of abnormal marrow cells; and
- overlooking reactive thrombocytosis when a low-level incidental clone is present.
If MPL is positive, the next steps usually include review of the bone marrow, blood-count trend, iron studies and inflammatory causes, JAK2/CALR results, splenic findings, and other myeloid mutations. If MPL is negative and suspicion for an MPN remains strong, broader NGS and expert hematopathology review can be useful.
When a rare MPL variant or unusually high VAF raises the possibility of hereditary thrombocytosis, family history and germline testing may be appropriate. Hereditary thrombocytosis has different implications for relatives and may not carry the same clonal-evolution risks as an acquired MPN.
Putting the MPL result into the thrombocytosis workup
Consider a patient with a platelet count of 700 × 10^9/L. If iron studies show severe iron deficiency and platelets normalize after iron replacement, a tiny incidental clone would be interpreted differently from persistent thrombocytosis with an MPL W515L mutation and characteristic megakaryocytes in the bone marrow. The molecular result supports clonality, but the entire pattern determines whether the patient has ET, prefibrotic PMF, or another myeloid disorder.
Bone-marrow morphology is especially important when the platelet count is the main abnormality. ET typically shows enlarged, mature megakaryocytes with hyperlobulated nuclei and relatively little granulocytic or erythroid proliferation. Prefibrotic PMF tends to show atypical megakaryocyte clustering and additional marrow features. Both can carry MPL mutations, so the same positive molecular result cannot resolve the distinction.
What VAF can and cannot tell you
A rising MPL VAF over time can suggest expansion of the mutant clone, but VAF is not a direct disease-burden meter. A value can rise because the clone grows, because normal-cell production falls, or because acquired copy-neutral loss of heterozygosity makes the mutant allele more prominent. VAF should therefore be trended only with the same or a comparable assay and interpreted alongside blood counts, spleen size, marrow findings, and symptoms.
Very low VAF values also deserve caution. Modern NGS can detect tiny clones that might represent early clonal hematopoiesis rather than a fully developed MPN. If a patient has only mild, transient thrombocytosis and an MPL variant near the assay limit, repeating the blood count and excluding reactive causes can be more informative than immediately labeling the patient with a chronic neoplasm.
Treatment is driven by clinical risk, not by MPL alone
For ET, the primary treatment goal is prevention of thrombosis and bleeding. Age, prior thrombosis, JAK2 status, cardiovascular risk, platelet-related bleeding risk, pregnancy, and symptoms guide treatment intensity. MPL status can contribute to biologic understanding and may be associated with fibrotic progression in some studies, but it does not automatically mandate cytoreduction.
For PMF, therapy is guided by symptom burden, splenomegaly, anemia, molecular/cytogenetic risk, transplant eligibility, and disease stage. JAK inhibitors can be effective for symptoms and spleen reduction even when the initiating driver is MPL rather than JAK2 because the abnormal signaling converges on the JAK-STAT pathway.
When to repeat molecular testing
Routine repeated MPL testing is not necessary for every stable patient. Broader molecular reassessment becomes more useful when the disease phenotype changes—for example, worsening anemia, increasing blasts, progressive splenomegaly, or suspected transformation. New mutations in genes associated with myeloid progression can add prognostic information that the original driver test could not provide.
Distinguishing clonal from reactive thrombocytosis
Persistent thrombocytosis has a wide differential diagnosis. Iron deficiency is common and should be checked with ferritin and other iron studies. Chronic inflammatory disease, infection, recent surgery, tissue injury, malignancy, and splenectomy can also raise platelets. In these settings, inflammatory markers, clinical history, and the trend after the underlying cause is treated can be as important as molecular testing.
An MPL driver strongly supports clonality, but the absence of MPL does not make thrombocytosis reactive. JAK2 and CALR account for far more MPN cases, and a minority of true ET or PMF cases are triple-negative. Conversely, finding an age-related mutation in a gene such as DNMT3A or TET2 is not equivalent to finding an MPN-defining driver. Clonal hematopoiesis becomes more common with age and can coexist with reactive blood-count changes.
The most convincing MPN diagnosis therefore aligns three layers: a persistent clinical phenotype, characteristic marrow morphology, and a compatible clonal marker. When one layer conflicts with the others, review is more valuable than forcing the result into a binary positive-or-negative label.
References
- Essential Thrombocythemia: A Review 2025 (Review)
- Essential thrombocythemia: 2024 update on diagnosis, risk stratification, and management 2024 (Review)
- Advances in Molecular Understanding of Polycythemia Vera, Essential Thrombocythemia, and Primary Myelofibrosis: Towards Precision Medicine 2024 (Review)
- Essential thrombocythaemia: A contemporary approach with new drugs on the horizon 2024 (Review)
- Thrombopoietin Receptor MPL in Hematopoiesis and Myeloproliferative Neoplasms: Physiological Roles and Pathogenic Mechanisms 2026 (Review)
Disclaimer
MPL testing must be interpreted with the complete blood count, bone-marrow findings, other MPN driver tests, and clinical history. This article is educational and does not replace diagnosis, thrombosis-risk assessment, or treatment advice from a hematologist or hematopathologist.