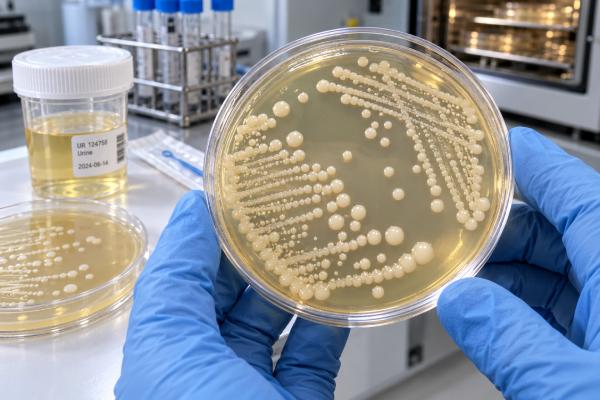
A urine fungal culture looks for yeast or other fungi in urine, most often Candida species. A positive result does not automatically mean a fungal urinary tract infection is causing symptoms. Candida can colonize the urinary tract, especially in people with urinary catheters, diabetes, recent antibiotic exposure, hospitalization, or recent urologic procedures. The key clinical question is whether the fungus represents contamination, colonization, lower urinary infection, kidney involvement, or a broader invasive infection. Standard urine culture may already detect yeast, but a fungal culture can be used when fungal infection is specifically suspected or when additional identification is needed. The result should be interpreted with symptoms, urine collection method, the amount and persistence of growth, risk factors, imaging when obstruction is possible, and the person’s overall condition. Treatment is not required for every episode of candiduria.
- Yeast in urine most often means Candida is present, but candiduria can reflect colonization rather than true infection.
- Catheters, diabetes, recent antibiotics, hospitalization, urinary obstruction, and urologic procedures increase the chance of candiduria.
- Symptoms, risk factors, and repeat or properly collected cultures matter more than the word “positive” alone.
- Asymptomatic candiduria often does not need antifungal treatment, although selected high-risk situations are managed differently.
- Fever, flank pain, obstruction, severe illness, or immunocompromise can make fungal growth more clinically important and may require urgent evaluation.
Table of Contents
- What a urine fungal culture detects
- What Candida in urine means
- Colonization, contamination, and true infection
- Risk factors and symptoms
- How the test is collected and reported
- When treatment or more testing is needed
- How to read a positive or negative result
- Common fungal culture questions
What a urine fungal culture detects
A fungal culture is designed to recover viable fungi from urine under laboratory conditions that support fungal growth. In the urinary tract, the organism found most often is Candida, a genus of yeast that commonly lives on human skin and mucosal surfaces. Less common yeasts and molds can also appear, especially in people with severe immune suppression or unusual exposures.
Some routine urine cultures can detect Candida without a special fungal culture because yeast may grow on standard bacteriology media. A dedicated fungal culture may be requested when yeast is repeatedly reported, when species identification is important, when routine culture is negative despite ongoing concern, or when clinicians suspect an uncommon fungal pathogen.
The test differs from a bacterial culture in one major interpretive way: the presence of fungus often reflects colonization rather than infection. Candida can reach a urine sample from the genital area, colonize a catheter or bladder without invading tissue, or cause true cystitis or pyelonephritis. The laboratory can show that yeast grew, but the result alone cannot identify which of these situations applies.
Microscopy may show budding yeast or pseudohyphae, and automated analyzers may flag yeast-like cells. These clues can prompt culture, but they are not equivalent to a final fungal identification. A urine Gram stain can sometimes reveal yeast as well, though it is mainly used for rapid bacterial morphology.
Fungal culture can also support susceptibility testing in selected cases, particularly when a non-albicans Candida species is recovered or treatment failure raises concern for antifungal resistance. Whether susceptibility testing is necessary depends on species, severity, and treatment plan.
What Candida in urine means
Candida in urine is called candiduria. The term is descriptive: it means Candida has been detected in urine. It does not, by itself, mean a person has Candida cystitis or a fungal kidney infection.
In hospitalized adults, candiduria is commonly associated with indwelling urinary catheters, broad-spectrum antibiotic exposure, diabetes, older age, and recent surgery or instrumentation. Antibiotics can suppress bacterial competitors and allow yeast to become more prominent. A catheter provides a surface on which Candida can form biofilm and persist.
Asymptomatic candiduria is common. When a patient has no urinary symptoms and is otherwise stable, clinicians first consider whether the catheter can be removed or replaced and whether treatment is actually indicated. Giving antifungal medication to every positive urine culture can create adverse effects, drug interactions, and selection pressure without improving outcomes.
Symptomatic Candida cystitis can cause dysuria, frequency, urgency, suprapubic discomfort, or hematuria, although these symptoms look similar to bacterial cystitis. Ascending infection can cause fever, flank pain, systemic illness, or renal complications. In severe cases, obstruction by fungal material, sometimes called a fungus ball, can impair urinary drainage.
Candiduria also does not reliably mean Candida is present in the bloodstream. Bloodstream candidiasis is a separate, serious diagnosis that requires its own evaluation. A person with sepsis, high-risk immune suppression, or signs of invasive infection needs broader assessment rather than assuming the urine result explains the entire illness.
Colonization, contamination, and true infection
The hardest part of fungal urine testing is deciding whether a positive result matters clinically. Contamination means yeast entered the specimen during collection rather than coming from the urinary tract. Colonization means yeast is living in the urinary tract or on a device without causing symptomatic tissue infection. True infection means Candida is associated with symptomatic cystitis, pyelonephritis, obstruction, or another invasive urinary process.
Several clues help separate these possibilities. A properly collected repeat sample that grows the same species is more convincing than a single questionable clean-catch specimen. Symptoms that localize to the urinary tract increase the likelihood of infection. Pyuria can support inflammation, but catheterized patients often have white blood cells even without symptomatic infection.
Colony count is less reliable for Candida than many people expect. There is no single CFU/mL threshold that cleanly separates colonization from infection in all settings. Urine concentration, catheter presence, prior antifungals, and specimen method can alter the count. Clinical context therefore carries more weight than an isolated number.
If a clean-catch specimen reports yeast together with mixed bacterial flora and many epithelial cells, contamination becomes more plausible. If a catheter specimen repeatedly grows Candida in a patient with fever and urinary obstruction, the finding deserves more attention.
The general principles of urine culture contamination still apply: collection quality can change the meaning of the report. When the result will influence treatment, repeating the culture from a better specimen can prevent unnecessary antifungal therapy.
Risk factors and symptoms
Candiduria is more likely when normal urinary defenses are disrupted. Indwelling catheters are among the strongest risk factors because they allow biofilm formation and repeated introduction of organisms. Recent antibiotics, especially broad-spectrum therapy, also increase risk by altering microbial balance.
Other important risk factors include diabetes, urinary retention or obstruction, kidney stones, urinary tract reconstruction, recent urologic procedures, hospitalization, intensive care, older age, and severe underlying illness. Neutropenia or other major immune suppression changes the level of concern because fungal findings may have different implications in high-risk hosts.
Symptoms of Candida UTI overlap with bacterial UTI. Lower-tract infection may cause burning urination, frequency, urgency, suprapubic pain, or visible blood. Upper-tract involvement may cause fever, flank pain, chills, nausea, vomiting, or systemic illness. Some patients, especially those with catheters, may have nonspecific symptoms, making overdiagnosis a risk.
A key mistake is to treat cloudy urine, odor, pyuria, or yeast growth as proof of symptomatic infection. Cloudiness and odor are nonspecific. Pyuria can occur from a catheter itself. Candida growth can reflect colonization. The diagnosis should rest on a coherent clinical syndrome, not one laboratory abnormality.
Obstruction deserves special attention. Fungal material can occasionally form obstructing masses, especially in patients with heavy fungal burden or urinary tract abnormalities. Reduced urine output, hydronephrosis, persistent fever, or flank pain can prompt imaging and urologic evaluation.
How the test is collected and reported
For a person who can urinate normally, a midstream clean-catch specimen is typical. The goal is to minimize organisms introduced from skin or genital surfaces. Begin urinating into the toilet, collect the middle portion in the sterile container, and avoid touching the inside of the cup or lid.
If a urinary catheter is present, urine should be collected from the appropriate sampling port using sterile technique rather than from the drainage bag. When a long-term catheter has been in place, clinicians may replace it before obtaining a new culture if clinically appropriate because the old catheter can be heavily colonized.
The laboratory may report “yeast,” “Candida species,” or a species-level identification such as Candida albicans, Candida glabrata, or another Candida species. Species matters because antifungal susceptibility and drug choice can differ. Some laboratories provide colony estimates; others use semiquantitative descriptions.
Turnaround time varies. Yeast can grow within a day or two, but final identification and susceptibility testing may take longer. Uncommon fungi can require specialized media or extended incubation.
A negative fungal culture reduces the likelihood that viable fungi were present in the tested specimen at a detectable level. It does not rule out every fungal infection. Prior antifungal therapy, intermittent shedding, low organism burden, or an infection outside the sampled urinary space can produce a negative result.
The result should always be compared with any routine urine culture, urinalysis, symptoms, and imaging. When Candida appears only once in a questionable specimen, repeat confirmation can be more valuable than immediate treatment.
When treatment or more testing is needed
Not every positive fungal culture needs an antifungal. In stable patients with asymptomatic candiduria, management often focuses on removing or replacing an unnecessary catheter and correcting reversible risk factors. Treatment decisions become different when symptoms are present or when the person belongs to a group at higher risk of complications.
Clinicians may consider antifungal treatment for symptomatic Candida cystitis or pyelonephritis, and in selected high-risk asymptomatic situations such as certain patients undergoing urologic manipulation. Severe immune suppression, neonatal status, pregnancy, renal obstruction, or suspected invasive candidiasis require individualized specialist-guided decisions.
When treatment is needed, species identification helps because susceptibility varies. Fluconazole is active against many susceptible Candida isolates and reaches high urine concentrations, but some species are less susceptible or resistant. Other antifungals differ greatly in urinary penetration, so a drug that is effective for bloodstream Candida is not automatically ideal for isolated urinary infection.
Persistent candiduria may lead to imaging if obstruction, abscess, structural disease, or fungus ball is suspected. A urologist may be needed when drainage is impaired. Blood cultures or broader invasive fungal evaluation may be appropriate in a critically ill or high-risk patient with compatible systemic findings.
The practical rule is to treat the patient and the clinical syndrome, not the culture line in isolation. A positive urine fungal culture is a signal to ask why Candida is present, whether it is causing disease, whether a device can be removed, and whether any complication needs to be corrected.
How to read a positive or negative result
If the result is positive for Candida and you have no urinary symptoms, ask about the reason for testing, whether a catheter is present, and whether repeat confirmation is needed. A stable, asymptomatic patient often does not require immediate antifungal treatment simply because yeast grew.
If the result is positive and you have dysuria, urgency, frequency, suprapubic pain, fever, or flank pain, clinical evaluation is more important. A clinician will consider whether symptoms fit Candida infection, bacterial coinfection, obstruction, or another diagnosis. Species identification and susceptibility may matter if treatment is planned.
If the result says “yeast” without a species, the laboratory may still be working on identification, or the amount may have been below a threshold for further workup. Ask whether a final result is pending. If the specimen was contaminated or poorly collected, a repeat test can clarify the finding.
If the culture is negative but strong risk factors and symptoms remain, clinicians may review prior antifungal or antibiotic use, repeat the specimen, consider imaging, or investigate other causes. Fungal UTI is much less common than bacterial UTI, so persistent urinary symptoms often have another explanation.
Seek urgent medical care for high fever, severe flank pain, persistent vomiting, confusion, very low urine output, low blood pressure, or rapidly worsening illness. These signs can indicate upper-tract infection, obstruction, or systemic infection and should not wait for a routine outpatient culture follow-up.
Common fungal culture questions
Does Candida in urine mean I have a yeast infection of the bladder?
Not necessarily. Candida can colonize the urinary tract or contaminate a specimen. A true Candida UTI is more likely when there are compatible urinary symptoms, persistent growth from a good-quality specimen, important risk factors, or evidence of upper-tract disease.
Can a vaginal yeast infection contaminate urine?
Yes. Yeast from the genital area can enter a clean-catch specimen. If the result is unexpected and the patient is stable, repeating a carefully collected midstream sample can help determine whether candiduria is persistent.
Should a catheter be changed if Candida is found?
When clinically feasible, removing an unnecessary urinary catheter or replacing a long-standing device can be an important part of management because Candida readily forms biofilm on catheter surfaces. Device management may be more useful than antifungal therapy for asymptomatic colonization.
Why can treatment fail even when the species is identified?
Failure can reflect an obstructed urinary tract, a fungus ball, an infected device, poor urinary penetration of the chosen antifungal, resistance, or a diagnosis that was actually colonization rather than symptomatic infection. Persistent fever or candiduria therefore calls for reassessment rather than simply extending the same drug.
Can Candida and bacteria be present at the same time?
Yes. Catheterized, hospitalized, or recently treated patients can have both bacterial and fungal organisms in urine. The challenge is deciding which, if any, is causing symptoms. A clinician may review the urinalysis, relative culture quantities, species, recent antibiotics, and the patient’s course before deciding whether antibacterial therapy, antifungal therapy, device management, or no antimicrobial treatment is appropriate.
A useful follow-up question is whether the same species has appeared more than once. Repeated recovery from properly collected specimens increases confidence that candiduria is persistent, but persistence still does not prove invasive disease. The decision to treat depends on symptoms, host risk, planned procedures, and whether an anatomic problem such as obstruction is present.
References
- Best Practices in Treatment of Fungal Urinary Tract Infections 2024 (Review)
- Microbiological Relevance of Candida in Urine Cultures 2025 (Review)
- Templated microbiology comments with candiduria to enhance antimicrobial stewardship 2022
- Novel technologies for the diagnosis of urinary tract infections 2025 (Review)
- Urinary Tract Infections: Core Curriculum 2024 2024 (Review)
Disclaimer
This article provides general information about fungal urine cultures and candiduria and is not a diagnosis or treatment plan. Candida in urine can represent contamination, colonization, or true infection, so interpretation requires symptoms, risk factors, specimen type, and clinical judgment. Seek urgent care for severe systemic symptoms, flank pain with fever, obstruction, or rapidly worsening illness.