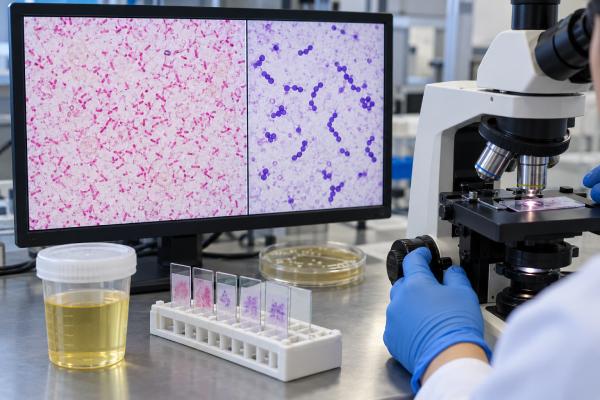
A urine Gram stain is a rapid microscopy test that can show bacteria, their broad Gram category, and sometimes the amount of inflammatory cells in a urine specimen before a culture is finished. Gram-negative rods on a stain can point toward common UTI organisms such as Escherichia coli or Klebsiella, while gram-positive cocci suggest a different group of organisms. The stain does not identify a species with certainty and does not provide final antibiotic susceptibility. Its main value is speed: a laboratory can often perform it much sooner than the 24–72 hours needed for routine culture and susceptibility testing. A useful result depends on bacterial concentration, sample quality, and the patient’s symptoms. A negative Gram stain cannot completely rule out urinary tract infection because lower bacterial counts or technical factors can make organisms hard to see.
- Urine Gram stain gives a rapid preliminary look at bacterial shape and Gram category, not a final species identification.
- Gram-negative rods often fit common UTI pathogens, while gram-positive cocci suggest organisms such as enterococci or staphylococci.
- A negative Gram stain lowers the chance of heavy bacteriuria but does not exclude UTI, especially at lower colony counts.
- White blood cells on the smear support urinary inflammation but are not specific for bacterial infection.
- Urine culture remains important when exact organism identification and antibiotic susceptibility are needed.
Table of Contents
- What a urine Gram stain does
- Gram-negative and gram-positive patterns
- How results relate to bacterial count
- Gram stain versus urinalysis and culture
- False-negative, mixed, and contaminated results
- When Gram stain is most useful
- How to interpret the report
- Common urine Gram stain questions
What a urine Gram stain does
Gram staining colors bacteria according to structural differences in their cell walls. Under the microscope, gram-positive organisms retain a purple stain, while gram-negative organisms appear pink or red after the counterstain. The laboratory also notes bacterial shape, such as rods or cocci, and may estimate whether organisms are few, moderate, or many.
This combination provides an early microbiology clue. “Gram-negative rods” is a category, not an organism name. E. coli, Klebsiella, Proteus, Pseudomonas, and other bacteria can share this appearance. “Gram-positive cocci” can include enterococci, staphylococci, streptococci, or other species depending on their arrangement and clinical setting.
A urine Gram stain may also show leukocytes, often reported as white blood cells or polymorphonuclear cells. Many leukocytes support an inflammatory response, but they do not prove that the bacteria seen are causing a UTI. Sterile pyuria and contamination can complicate the picture.
Unlike culture, Gram stain does not require organisms to grow. That makes it fast, often allowing same-day or near-immediate preliminary information. But it also limits what the test can determine. It cannot reliably provide species-level identification, colony count in CFU/mL, or a complete antibiotic susceptibility profile.
The stain is therefore best viewed as one component of a diagnostic pathway. A broader UTI test panel may combine dipstick testing, microscopy, culture, and susceptibility depending on the clinical need.
Gram-negative and gram-positive patterns
Gram-negative rods are the classic pattern in many community-acquired UTIs because E. coli is the most common cause. If a symptomatic patient has abundant gram-negative rods and pyuria, the pattern supports a bacterial UTI while culture is pending. It still cannot determine whether the organism is E. coli or another gram-negative species.
Gram-positive cocci require more context. Enterococci are important urinary pathogens in hospitalized, catheterized, older, or previously treated patients. Staphylococcus saprophyticus can cause uncomplicated cystitis, particularly in younger women. Other staphylococci may represent infection or contamination depending on the species, quantity, sample type, and clinical setting.
Bacterial arrangement can provide additional clues. Cocci in clusters suggest a staphylococcal pattern, while cocci in pairs or chains may point toward streptococci or enterococci. These are preliminary morphology observations rather than definitive identification.
If more than one distinct bacterial morphology appears in a clean-catch specimen, contamination becomes more likely, especially if culture later reports mixed flora. In a catheterized or anatomically complex urinary tract, polymicrobial infection is more plausible, so the same visual finding has a different meaning.
Yeast can also be visible microscopically, but a routine bacterial Gram stain is not the same as a dedicated fungal culture. If yeast is a central finding, interpretation should consider candiduria, catheters, diabetes, recent antibiotics, and urologic procedures. The urine fungal culture provides a more focused evaluation when fungal infection is a concern.
How results relate to bacterial count
Gram stain sensitivity depends heavily on how many bacteria are present in the sample. Heavy bacteriuria is easier to see than low-level growth. This is why a negative stain cannot rule out a culture-positive UTI with a lower colony count.
A routine culture reports quantity in CFU/mL or a semiquantitative category. Gram stain may use descriptive terms such as rare, few, moderate, or many organisms. Those descriptors are not interchangeable with specific CFU/mL thresholds because slide preparation, urine concentration, microscope field size, and laboratory technique influence what is seen.
Recent emergency-department research found that observing many bacteria on urine Gram stain had relatively high specificity but only moderate sensitivity for UTI, while the stain could predict gram-negative rod growth reasonably well when that pattern was present. This illustrates its practical role: positive findings can be informative, while negative findings are not definitive.
A traditional culture threshold of 10^5 CFU/mL should also not be treated as the sole definition of infection. Symptomatic patients can have lower counts that are clinically meaningful, and research definitions vary. For a deeper explanation of this issue, see urine colony count.
Hydration can change bacterial concentration in a spot urine sample. A very dilute specimen may contain fewer organisms per microscopic field even when infection is present. Recent antibiotics can reduce bacterial numbers as well. These factors can weaken both the stain and culture signal, especially if the specimen is collected after treatment begins.
Gram stain versus urinalysis and culture
Urinalysis, Gram stain, and culture answer related but different questions. Urinalysis looks for inflammation and chemical clues. Gram stain gives a rapid visual impression of microorganisms. Culture grows viable organisms, identifies them, and may provide susceptibility testing.
| Test | Main information | Typical speed | Key limitation |
|---|---|---|---|
| Dipstick urinalysis | Leukocyte esterase, nitrite, blood and other chemistry | Minutes | Indirect; does not identify the organism |
| Urine microscopy | WBCs, RBCs, bacteria, epithelial cells | Minutes to hours | Appearance does not equal species identification |
| Urine Gram stain | Gram category and bacterial morphology | Minutes to hours | Limited sensitivity at low bacterial counts |
| Urine culture | Organism growth, amount, identification | Usually 24–72 hours | Slower and vulnerable to contamination |
| Susceptibility testing | Likely antibiotic activity | Often follows culture | Requires a meaningful isolate and clinical context |
Nitrite can be positive with nitrate-reducing bacteria but negative with enterococci or short bladder dwell time. Leukocyte esterase reflects white-cell activity but can be positive in noninfectious inflammation. Gram stain can sometimes bridge these rapid tests and the final culture by giving a preliminary organism category.
A culture and sensitivity test remains more definitive when antibiotic choice depends on the organism. Newer rapid systems may identify pathogens or resistance markers earlier, but they do not make clinical context optional.
False-negative, mixed, and contaminated results
A false-negative Gram stain occurs when infection is present but organisms are not seen. Low bacterial concentration is a common reason. Antibiotics taken before collection, very dilute urine, uneven specimen mixing, or technical limitations can also reduce detection.
A stain can also show bacteria that do not represent bladder infection. Clean-catch urine passes through an area colonized by skin and genital organisms, so contamination is possible. If epithelial cells are numerous and multiple morphologies are present, contamination becomes more likely.
Mixed findings deserve special caution. A true polymicrobial UTI can occur, particularly with long-term catheters, urinary obstruction, stones, or complex anatomy. In a healthy person with a midstream sample, however, several different organisms are more often a collection problem. Culture helps distinguish these possibilities by showing how many colony types grow and in what amounts.
False certainty is another practical error. A preliminary report of gram-negative rods should not be translated into “definitely E. coli,” and gram-positive cocci should not be assumed to be contamination. The correct use of morphology is to narrow possibilities while waiting for definitive identification.
If the Gram stain is negative but symptoms strongly suggest UTI, clinicians may still culture the urine. Studies of Gram stain-negative specimens show that clinically important organisms can still grow, particularly at lower concentrations. A negative result should reduce probability, not close the diagnostic process.
When Gram stain is most useful
Gram stain can be valuable when a rapid bacterial category may change early management. Examples include acutely ill patients in the emergency department, complicated UTI, suspected pyelonephritis, hospitalized patients, or situations where early broad versus narrow antibiotic decisions matter.
It may also help laboratories triage specimens or provide preliminary information before culture. Some centers rely more on automated urine flow cytometry or other rapid technologies, so Gram stain is not routine everywhere. Local workflow, staffing, patient population, and test performance determine how it is used.
The test is less helpful when pretest probability is very low. Testing urine in a person without urinary symptoms can reveal incidental bacteriuria or colonization and create pressure to treat a finding that is not causing disease. Diagnostic stewardship therefore starts before the specimen reaches the microscope.
Gram stain is also not a substitute for blood cultures or broader sepsis evaluation when systemic infection is suspected. A patient with high fever, low blood pressure, confusion, or severe flank pain may need urgent treatment and additional testing regardless of the urine stain.
For routine uncomplicated cystitis in a stable patient, a dipstick and clinical assessment may be sufficient in some settings, with culture reserved for selected cases. The fact that Gram stain can provide fast information does not mean every suspected UTI needs it.
How to interpret the report
Start by reading exactly what the laboratory reported. “Gram-negative rods present” means a broad morphological group. “Many gram-positive cocci” adds quantity but still does not provide species. “No organisms seen” means the stain did not detect bacteria at its visual threshold.
Next, look for white blood cells and the rest of the urinalysis. Bacteria plus pyuria in a symptomatic patient is more persuasive than bacteria alone. Nitrite can further support nitrate-reducing gram-negative organisms, while leukocyte esterase reinforces the presence of inflammation.
Then consider the collection method. A clean-catch sample with multiple morphologies and many epithelial cells is more vulnerable to contamination than a properly obtained catheter specimen. If the result is confusing and the patient is stable, repeating a better-quality sample can be more useful than reacting to an ambiguous preliminary report.
Finally, wait for culture when it matters. Culture can tell whether the preliminary Gram pattern corresponds to a dominant organism, give a colony count, and provide susceptibility data. If the final culture conflicts with the stain, the clinician should reconsider specimen quality, prior antibiotics, organism load, and the patient’s clinical course.
Seek prompt medical care for fever, flank pain, vomiting, shaking chills, confusion, low blood pressure, or rapidly worsening symptoms. Gram stain is a laboratory clue; it should never delay evaluation of a potentially serious kidney infection or sepsis.
Common urine Gram stain questions
Can Gram stain tell which antibiotic will work?
Not by itself. Knowing that bacteria are gram-negative rods or gram-positive cocci may influence an early empiric choice in a sick patient, but resistance patterns vary within each group. Definitive antibiotic selection usually relies on culture identification and susceptibility, local resistance data, infection site, allergies, and kidney function.
What does “few bacteria” mean?
It is a semiquantitative visual description rather than a standardized CFU/mL result. Few organisms may represent low-count infection, contamination, or a diluted specimen. The significance rises when symptoms and pyuria are present and falls when the sample has many epithelial cells or no compatible symptoms.
Can Gram stain miss Enterococcus or other gram-positive organisms?
Yes. Any organism can be missed when the bacterial concentration is below the visual detection threshold. Gram-positive bacteria may also be less conspicuous in some specimens. A negative stain therefore should not replace culture when clinical suspicion is high.
Why would a clinician act before culture is final?
In a seriously ill patient, waiting one or two days for full culture data may be unsafe. A rapid Gram pattern can narrow the likely organism group while empiric therapy is started. Once culture and susceptibility return, treatment can be refined or stopped if the microbiology does not support the initial assumption.
What if the Gram stain and culture disagree?
Discordance can happen because the smear samples only a small portion of urine, the bacterial burden changes, antibiotics were given, contaminants were present, or organisms seen microscopically failed to grow under standard conditions. Clinicians usually give greater weight to the complete picture rather than declaring either test universally superior.
Does the stain show contamination?
It can provide clues but cannot prove contamination. Multiple bacterial shapes, especially in a voided specimen with many epithelial cells and weak inflammation, make contamination more likely. Culture is better at showing whether one organism predominates or several unrelated colony types are present. If the specimen quality is questionable and the patient is stable, repeating a carefully collected sample often gives a clearer answer than trying to infer too much from the smear.
References
- Clinical usefulness of urine Gram stain for diagnosing urinary tract infections at the emergency department 2024
- Is it meaningful to apply midstream urine culture to urine specimens with negative Gram stain results? 2023
- The EFLM European Urinalysis Guideline 2023 2024 (Guideline)
- Urinary Tract Infections: Core Curriculum 2024 2024 (Review)
- Performance of Urinalysis Parameters in Predicting Urinary Tract Infection: Does One Size Fit All? 2024
Disclaimer
This article provides general information about urine Gram staining and does not replace medical advice or laboratory-specific interpretation. Gram stain findings should be interpreted with symptoms, urinalysis, sample type, and culture results. Urgent symptoms such as fever with flank pain, vomiting, confusion, or signs of sepsis need prompt medical assessment.