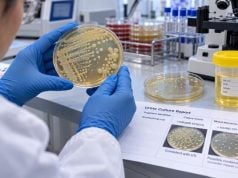
A urine colony count estimates how many bacteria grow from a measured amount of urine and is usually reported as colony-forming units per milliliter (CFU/mL). The number helps a laboratory and clinician decide whether bacterial growth is likely to represent true bladder bacteriuria, contamination, or an uncertain result. The familiar threshold of 100,000 CFU/mL, written as 10⁵ CFU/mL, is important but is not a universal cutoff for every UTI. In a symptomatic patient, lower counts of a single typical uropathogen can still be clinically meaningful, especially when pyuria is present and the specimen was collected well. In an asymptomatic person, even a high colony count may represent asymptomatic bacteriuria rather than an infection that needs treatment. Collection method also changes interpretation: catheterized specimens are less exposed to periurethral contamination than voided urine and may be meaningful at lower counts.
- CFU/mL means colony-forming units per milliliter: it estimates viable bacterial growth in the cultured urine sample.
- 10⁵ CFU/mL is not a universal UTI threshold: symptomatic patients can have true infection at 10²–10⁴ CFU/mL, depending on organism and context.
- A single typical uropathogen is more convincing than mixed growth: several organisms often suggest contamination in a voided specimen.
- Collection method matters: lower colony counts can be more meaningful in a catheterized sample than in a poorly collected voided sample.
- High counts without urinary symptoms do not automatically mean UTI: asymptomatic bacteriuria is common in some groups and usually should not be treated outside specific situations.
Table of Contents
- What CFU/mL Means
- Why 100,000 CFU/mL Is Not a Universal Cutoff
- How Symptoms and Collection Method Change Meaning
- Single Organism, Mixed Growth, and Contamination
- Why Organism Identity Matters
- How to Read Common Colony Count Results
- Asymptomatic Bacteriuria and Special Situations
- When Repeat Culture or Follow-Up Is Needed
What CFU/mL Means
A urine culture does more than report “bacteria present.” The laboratory places a measured amount of urine onto culture media, incubates it, and counts bacterial colonies that grow. Because the plated volume is known, the laboratory can estimate the number of colony-forming units in 1 milliliter of urine.
For example:
- 10² CFU/mL means about 100 colony-forming units per milliliter.
- 10³ CFU/mL means about 1,000 CFU/mL.
- 10⁴ CFU/mL means about 10,000 CFU/mL.
- 10⁵ CFU/mL means about 100,000 CFU/mL.
The word “colony-forming” matters because the test measures organisms capable of growing under the laboratory’s culture conditions. It is not a direct count of every bacterial cell or piece of bacterial DNA in the urinary tract. Standard culture can also miss organisms that do not grow well under routine conditions.
A urine culture test combines colony quantity with organism identification. When a likely pathogen grows, the laboratory may also perform antibiotic susceptibility testing. The colony count is therefore one part of a larger report, not a diagnosis by itself.
The count can be influenced by how urine was collected, how long it sat before processing, whether antibiotics were taken before collection, how concentrated the urine is, and whether one organism or several organisms grew. A result of 10⁴ CFU/mL can mean different things in a symptomatic woman with pyuria and E. coli than in an asymptomatic patient whose voided specimen grew three different skin and genital organisms.
Why 100,000 CFU/mL Is Not a Universal Cutoff
The traditional “significant bacteriuria” threshold of 10⁵ CFU/mL came largely from studies designed to distinguish true bacteriuria from contamination, especially in asymptomatic people. It remains very useful for defining asymptomatic bacteriuria in many clinical situations, but applying it rigidly to every symptomatic patient can miss real UTIs.
Modern guidance recognizes that symptomatic women with acute cystitis may have lower colony counts. Studies comparing voided urine with catheterized bladder specimens have shown that E. coli at levels as low as about 10² CFU/mL can correspond to true bladder bacteriuria in carefully selected symptomatic women, especially when pyuria is also present. Many routine laboratories, however, do not report counts below 10³ CFU/mL in the same level of detail.
This does not mean that every 100 CFU/mL result is a UTI. Lowering the threshold increases sensitivity but also risks overcalling contamination or colonization. Clinical interpretation must therefore consider:
- whether symptoms are typical for UTI;
- whether pyuria is present;
- whether a single recognized uropathogen grew;
- whether the specimen was properly collected;
- whether antibiotics were taken beforehand;
- whether the patient has a catheter or urinary abnormality.
Recent research also shows that UTI definitions vary widely between studies, with “significant” bacteriuria thresholds ranging from 10³ to 10⁵ CFU/mL. This variation reflects the fact that UTI is a clinical syndrome rather than a laboratory number alone.
The safest way to understand colony count is to ask, “How well does this quantity of this organism, from this kind of sample, fit this patient’s symptoms and urinalysis?”
How Symptoms and Collection Method Change Meaning
The same colony count can have very different significance depending on symptoms and specimen type.
A symptomatic patient with new dysuria, urgency, frequency, and pyuria has a high pretest probability of cystitis. In that setting, a lower count of a single typical uropathogen can be meaningful. A person with no urinary symptoms and the same low count is more likely to have contamination or colonization, depending on the organism and collection method.
Collection method changes contamination risk:
| Specimen type | Contamination exposure | How colony count is interpreted |
|---|---|---|
| Midstream voided urine | Passes through urethral opening and can pick up skin/genital flora | Higher counts and a single uropathogen are more convincing, but lower counts can still matter with classic symptoms |
| Straight catheter urine | Lower exposure to external flora | Lower counts may more strongly represent true bladder bacteriuria |
| Indwelling catheter sample | Biofilm and colonization become common over time | Symptoms are essential; bacteriuria alone does not prove catheter-associated UTI |
| Suprapubic aspirate | Obtained directly from bladder through abdominal wall | Any convincing bacterial growth is usually taken seriously because contamination is uncommon |
A straight catheter urine test may be used when a voided culture is repeatedly contaminated or when a cleaner bladder specimen is needed. In catheter-associated infection, guidelines often use a lower quantitative threshold such as 10³ CFU/mL in a symptomatic patient, but the presence of a catheter makes asymptomatic bacteriuria very common, so symptoms remain crucial.
Dilution can also affect the measured count. A patient who drinks a very large amount of fluid immediately before testing may produce more dilute urine. Prior antibiotics can reduce growth further. These factors are reasons to avoid dismissing a plausible infection solely because the reported count is below 10⁵ CFU/mL.
Single Organism, Mixed Growth, and Contamination
Colony count is most informative when paired with the number and identity of organisms that grow. A high count of one classic uropathogen is generally easier to interpret than a similar total count made up of several organisms.
Single-organism growth means one predominant species was recovered. Common urinary pathogens include E. coli, Klebsiella pneumoniae, Proteus mirabilis, Staphylococcus saprophyticus, Enterococcus species, and others. The significance depends on patient population and symptoms, because some organisms are more likely than others to represent contamination in a voided specimen.
Mixed growth means more than one organism grew without a clear single pathogen. In a routine midstream specimen, this often reflects contamination from skin, vaginal, or periurethral flora. Laboratories may report “mixed flora,” “mixed urogenital flora,” or a similar phrase instead of a precise CFU count for every organism.
A contaminated urine culture becomes more likely when several organisms grow, squamous epithelial cells are abundant, and the clinical picture is not convincing for polymicrobial infection. True polymicrobial UTI can occur, especially with long-term catheters, urinary obstruction, fistulas, instrumentation, or severe complicated disease, so mixed growth is not automatically meaningless.
Specimen handling can create another form of false elevation. If urine remains warm at room temperature for too long, bacteria can multiply after collection. This may increase the apparent colony count and turn a borderline specimen into a misleadingly high one. Prompt transport, refrigeration, or an approved preservative helps maintain accuracy.
Why Organism Identity Matters
A colony count becomes more or less persuasive depending on which organism produced it. E. coli is the most common cause of uncomplicated bacterial cystitis and is strongly associated with true bladder infection when it appears as the predominant organism in a symptomatic patient. Other classic uropathogens such as Klebsiella, Proteus, and Staphylococcus saprophyticus can also be clinically important, but the likelihood that a specific isolate represents infection depends on the patient’s age, sex, urinary anatomy, catheter status, and healthcare exposure.
Some organisms recovered from voided urine are more difficult to interpret because they can be part of periurethral or genital flora. A low-count isolate that is plausible as a contaminant carries less weight than the same count of a typical uropathogen in a patient with pyuria and classic symptoms. This is why laboratories sometimes suppress full identification or susceptibility testing for low-level mixed growth that appears non-significant.
Proteus deserves special attention because repeated infection can be associated with urease activity and struvite stone formation. Persistent growth of the same organism after treatment can raise concern for a stone, obstruction, or another reservoir. Repeated isolation of highly resistant gram-negative organisms may instead point toward prior antibiotic exposure, healthcare-associated acquisition, or a complicated urinary tract.
Yeast is another special case. Candiduria is not interpreted using the same simple logic as ordinary bacterial cystitis, especially in catheterized or hospitalized patients. A positive fungal culture can represent colonization rather than invasive infection. The count, symptoms, host factors, catheter status, and species all matter.
The organism therefore provides biological context for the number. CFU/mL answers “how much growth was recovered,” while organism identity helps answer “how plausible is this growth as the cause of the current symptoms?”
How to Read Common Colony Count Results
Laboratory wording varies, but common patterns can be interpreted using the combination of count, organism, symptoms, and urinalysis.
| Example result | Possible meaning |
|---|---|
| ≥10⁵ CFU/mL of *E. coli* + dysuria + pyuria | Strongly supports bacterial UTI |
| 10²–10⁴ CFU/mL of *E. coli* + classic cystitis symptoms + pyuria | Can still represent true infection in selected symptomatic patients |
| ≥10⁵ CFU/mL without urinary symptoms | May represent asymptomatic bacteriuria rather than symptomatic UTI |
| Low-count mixed organisms in voided urine | Often contamination, especially without pyuria or symptoms |
| Several organisms at high counts in long-term catheter urine | Colonization is common; diagnose CAUTI only if compatible symptoms are present |
| No growth after antibiotics were started | Does not fully exclude prior bacterial UTI because treatment may suppress culture |
Some laboratories use categories such as “no growth,” “less than 10,000 CFU/mL,” “10,000–50,000 CFU/mL,” “50,000–100,000 CFU/mL,” or “>100,000 CFU/mL.” Others report exact logarithmic ranges. A threshold used by the laboratory for reporting is not necessarily the same as the clinical threshold used to diagnose infection. Laboratories may also have rules for when they identify an organism to species level or perform susceptibility testing. Very low counts, mixed growth, or organisms judged likely to be contaminants may receive a more limited report. If the clinical suspicion is high despite a nonspecific result, a repeat specimen can be more informative than trying to extract certainty from a report that was intentionally designed to avoid overcalling insignificant growth in routine practice.
Colony count also does not measure infection severity. A person with 10⁵ CFU/mL can have mild cystitis, while someone with a lower count can have significant symptoms. Severity depends more on location and host response: fever, flank pain, vomiting, low blood pressure, kidney dysfunction, or sepsis indicate greater concern than the CFU number itself.
The urinalysis pattern adds important context. Pyuria and positive nitrite increase confidence that bacterial growth is clinically relevant, while absence of pyuria can make ordinary bacterial UTI less likely in many settings.
Asymptomatic Bacteriuria and Special Situations
Asymptomatic bacteriuria means bacteria are present in urine at defined quantitative levels without symptoms attributable to UTI. For voided specimens in adults, the classic definition generally uses ≥10⁵ CFU/mL. In women, persistence is traditionally confirmed with two consecutive specimens; in men, one appropriately collected specimen is generally sufficient for the microbiologic definition.
The critical point is that asymptomatic bacteriuria is not the same as symptomatic UTI. Most nonpregnant adults do not benefit from antibiotic treatment of asymptomatic bacteriuria, and unnecessary treatment can cause side effects, Clostridioides difficile infection, and antimicrobial resistance. Major exceptions include pregnancy and certain invasive urologic procedures in which mucosal trauma is expected.
Pregnancy has its own screening and treatment rules because untreated bacteriuria can increase the risk of pyelonephritis and adverse pregnancy outcomes. Colony-count interpretation should therefore follow obstetric guidance rather than general adult UTI rules.
People with long-term urinary catheters frequently develop bacteriuria because bacteria form biofilm on catheter surfaces. A very high count is therefore expected over time and does not prove infection. Fever, pelvic or flank symptoms, hemodynamic change, and other compatible features matter more than the count alone.
Children also have specimen-specific diagnostic criteria, and thresholds differ depending on whether urine was obtained by clean catch, catheterization, or suprapubic aspiration. Pediatric results should be interpreted using age-appropriate guidance rather than adult cutoffs.
When Repeat Culture or Follow-Up Is Needed
A repeat culture is useful when the first result is hard to trust or does not fit the patient’s symptoms. Common reasons include mixed flora, suspected contamination, persistent symptoms despite treatment, rapid recurrence, or a colony count that falls into an uncertain range for the clinical situation.
When contamination is suspected, repeating the same collection method without improving technique may simply reproduce the problem. A careful clean-catch specimen or, in selected cases, a catheterized sample can provide a clearer answer. The clinician may also compare the repeat organism and susceptibility pattern with the first culture.
If symptoms persist despite an antibiotic to which the organism was reported susceptible, reassessment should consider adherence, drug absorption, infection location, obstruction, stones, abscess, resistant subpopulations, or a non-UTI diagnosis. A repeat culture and sensitivity test may help guide the next step.
Routine repeat cultures are usually unnecessary after uncomplicated cystitis has fully resolved. Testing symptom-free people can detect asymptomatic bacteriuria and lead to unnecessary treatment. Follow-up is more appropriate when symptoms continue, recur quickly, or the patient belongs to a group in which documented clearance or repeat screening is clinically important.
The main lesson is that colony count is a context-dependent measurement, not a pass/fail UTI cutoff. A high number can represent asymptomatic bacteriuria, a low number can represent true symptomatic infection, and mixed growth can represent contamination. The organism, collection method, pyuria, symptoms, risk factors, and timing relative to antibiotics determine what the CFU result actually means.
When comparing two cultures, focus on more than whether both crossed the same numeric cutoff. A repeat specimen that grows the same organism at a similar or higher count is more persuasive than a second specimen that grows a different mixture of low-level organisms. Changes in collection method also matter: a lower count from a carefully obtained catheter specimen can carry more weight than a higher mixed count from a contaminated voided sample. This is why serial results should be read as a pattern of organism, quantity, specimen quality, symptoms, and timing rather than as isolated CFU numbers.
References
- Urine Culture: Clinical Use and Interpretation 2026 (Review)
- Recurrent Uncomplicated Urinary Tract Infections in Women: AUA/CUA/SUFU Guideline (2019, Confirmed 2022, Amended 2025) 2025 (Guideline)
- EAU Guidelines on Urological Infections – THE GUIDELINE 2026 (Guideline)
- Definitions of Urinary Tract Infection in Current Research: A Systematic Review 2023 (Systematic Review)
- IDSA 2019 Clinical Practice Guideline Update for the Management of Asymptomatic Bacteriuria 2019 (Guideline)
Disclaimer
This article is for general education and does not replace medical interpretation of a urine culture. Colony counts must be assessed with symptoms, urinalysis, organism identity, collection method, pregnancy or catheter status, recent antibiotics, and individual risk factors before deciding whether treatment or repeat testing is needed. A clinician should interpret uncertain or conflicting results rather than using a single CFU cutoff to self-treat.