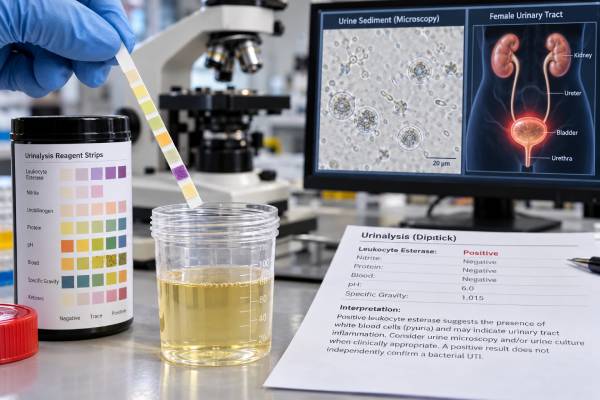
A urine leukocyte esterase test looks for an enzyme released mainly by neutrophils, a type of white blood cell. A positive result usually means white blood cells are present in the urine, a finding called pyuria. That often happens with a urinary tract infection (UTI), but it is not proof of one. Inflammation from kidney stones, sexually transmitted infections, urinary procedures, and sample contamination can also make leukocyte esterase positive. The result matters most when it is interpreted with urinary symptoms, nitrites, urine microscopy, and—when needed—a urine culture. A negative result lowers the chance of a UTI in many situations, but it does not rule infection out completely. The sample itself also matters: concentrated urine, high glucose or protein, vitamin C, some medicines, and delays in testing can affect dipstick accuracy. Understanding those limits helps prevent both missed infections and unnecessary antibiotics.
- A positive leukocyte esterase result means white blood cells are likely present in the urine; it does not by itself diagnose a UTI.
- A negative result is reassuring when symptoms are mild and nitrites are also negative, but a UTI can still be present.
- More than about 5 white blood cells per high-power field on microscopy is commonly considered pyuria, although laboratory cutoffs vary.
- False positives can come from contamination or noninfectious urinary inflammation; false negatives can occur in concentrated urine or with vitamin C and some other substances.
- Fever, flank pain, vomiting, pregnancy, severe illness, or persistent urinary symptoms are reasons to seek prompt clinical evaluation rather than relying on a dipstick alone.
Table of Contents
- What the Leukocyte Esterase Test Measures
- What a Positive Leukocyte Esterase Result Means
- UTI, White Blood Cells, and Nitrites
- False-Positive and False-Negative Results
- How the Test Is Performed and How to Prepare
- When Culture and Follow-Up Are Needed
- When to Get Medical Care
What the Leukocyte Esterase Test Measures
Leukocyte esterase is an enzyme found in certain white blood cells, especially neutrophils. A urine dipstick contains a chemical pad that changes color when this enzyme is present. The test therefore acts as a quick indirect marker for white blood cells in urine.
A normal dipstick result is usually reported as negative. Positive results may be graded as trace, small, moderate, or large, or with a numeric scale such as 1+ to 3+, depending on the laboratory and test strip. These grades are semiquantitative: they suggest increasing leukocyte esterase activity, but they do not provide an exact white blood cell count.
The related microscopic finding is pyuria, meaning increased white blood cells in urine. Many laboratories use more than 5 white blood cells per high-power field as a practical cutoff, but methods and reference ranges differ. Automated systems may instead report cells per microliter.
Leukocyte esterase is one part of a standard urinalysis. It becomes more useful when considered with symptoms and other urine findings. For example, a clinician evaluating burning with urination may also look at the urine nitrite result, blood, urine pH, microscopic white blood cells, bacteria, and epithelial cells.
The test cannot identify which organism is present and cannot show which antibiotic would work. Those questions require a urine culture and sensitivity test when culture is indicated.
What a Positive Leukocyte Esterase Result Means
A positive leukocyte esterase result means the urine probably contains white blood cells or material released from them. The most common clinical concern is a UTI, but inflammation is the finding being detected—not bacteria themselves.
The result is more convincing for infection when it fits a typical symptom pattern, such as:
- burning or pain with urination;
- new urinary urgency or frequency;
- lower abdominal or bladder discomfort;
- cloudy urine together with compatible symptoms;
- fever, chills, or flank pain when an upper urinary tract infection is possible.
Leukocyte esterase can also be positive when there is no bacterial UTI. Other possibilities include kidney or ureteral stones, inflammation after catheterization or other urinary procedures, urethritis, some sexually transmitted infections, and less commonly inflammatory kidney disorders. Vaginal white blood cells can contaminate a urine specimen and create a positive result even when the bladder urine itself is not inflamed.
This is why a positive dipstick should not be treated as a diagnosis in isolation. In someone with no urinary symptoms, especially an older adult or a person with a long-term catheter, positive inflammatory markers are common and may not represent a UTI that benefits from antibiotics. A clinician may focus instead on symptoms, examination findings, microscopy, and culture criteria.
If the dipstick is positive but the clinical picture is unclear, a white blood cell measurement in urine can help confirm whether pyuria is actually present.
The strength of the color change can provide context, but it should not be treated as a severity score. A “large” or 3+ leukocyte esterase result generally indicates more enzyme activity than a trace result, yet the grade does not reliably tell how serious an infection is, how high the bacterial count will be, or whether the kidneys are involved. A mild lower UTI can produce marked pyuria, while an early infection or a dilute specimen can produce a weaker result. Symptoms and clinical risk matter more than the number of plus signs.
A trace result is especially context-dependent. Trace leukocyte esterase in a person with classic burning and frequency may support further UTI evaluation. The same trace result in an asymptomatic person, particularly with many squamous epithelial cells suggesting contamination, may have little clinical significance. Repeating the sample is often more informative than interpreting a borderline result too aggressively.
Urine white blood cells also behave differently across patient groups. During pregnancy, urinary symptoms and abnormal dipstick findings deserve clinical attention, but urine culture is the standard method used to identify asymptomatic bacteriuria because dipsticks are not accurate enough for that screening purpose. In children, age, fever, collection method, and pretest probability strongly affect interpretation. In people with urinary catheters, pyuria is common and cannot distinguish catheter-associated infection from colonization on its own.
A useful way to think about the test is that leukocyte esterase answers, “Is there evidence of white blood cell activity in this urine?” It does not answer, “Is there definitely a bacterial infection?” or “Should antibiotics be started?” Those require the rest of the clinical picture.
UTI, White Blood Cells, and Nitrites
Leukocyte esterase and nitrites answer different questions. Leukocyte esterase reflects the body’s inflammatory response. Nitrites reflect bacterial chemistry: some bacteria convert urinary nitrate to nitrite while urine sits in the bladder.
| Finding | What it suggests | Important limitation |
|---|---|---|
| Leukocyte esterase positive | White blood cells or urinary inflammation | Not specific for bacterial infection |
| Nitrite positive | Nitrate-reducing bacteria are likely present | Some UTI bacteria do not produce nitrite |
| Both positive | UTI becomes more likely when symptoms are compatible | Culture may still be needed in higher-risk situations |
| Both negative | UTI becomes less likely | Does not exclude every infection |
A positive nitrite result is generally more specific for bacterial UTI than leukocyte esterase, while leukocyte esterase is often more sensitive for inflammation. In other words, leukocyte esterase may pick up more possible cases, but it also becomes positive for more non-UTI reasons.
Nitrites can stay negative despite a true UTI. Enterococcus and some other organisms do not reliably reduce nitrate to nitrite. Frequent urination can also produce a false-negative nitrite result because bacteria often need several hours in the bladder to generate detectable nitrite. This is one reason a negative nitrite test does not cancel out a positive leukocyte esterase result in a symptomatic person.
Symptoms still matter. An urinalysis for suspected UTI works best as one part of the overall assessment rather than as a yes-or-no infection test.
Leukocyte esterase without urinary symptoms
A common mistake is to treat a positive leukocyte esterase result simply because it is abnormal. Pyuria can accompany asymptomatic bacteriuria, in which bacteria are present in urine but the person has no UTI symptoms. In most nonpregnant adults, asymptomatic bacteriuria does not require antibiotic treatment. Pregnancy and certain urologic procedures are important exceptions in which culture-based screening or treatment may be recommended.
Older adults deserve particular caution because asymptomatic bacteriuria and pyuria become more common with age. A positive dipstick alone does not establish that confusion, weakness, or another nonspecific symptom is caused by a UTI.
False-Positive and False-Negative Results
Dipstick testing is useful because it is fast, but several factors can distort the result. Knowing them is especially helpful when the dipstick does not match the symptoms.
Causes of a false-positive leukocyte esterase result
A false positive means the strip suggests leukocytes even though the result does not reflect a true urinary inflammatory process. Common reasons include:
- contamination with vaginal secretions or genital material;
- a poorly collected sample with many squamous epithelial cells;
- oxidizing cleaning agents or chemical contamination, depending on the strip;
- reading the strip outside the manufacturer’s recommended time window.
Some apparently “false” positives are actually true detection of white blood cells from a non-UTI cause. Urethritis, kidney stones, interstitial inflammation, recent instrumentation, and genital tract inflammation can all produce leukocytes without a routine bacterial bladder infection.
Causes of a false-negative leukocyte esterase result
A false negative is possible when white blood cells are present but the chemical reaction is suppressed. Reported causes include very concentrated urine, marked glucosuria or proteinuria, high levels of vitamin C, and certain medications or antibiotics. The exact interference depends on the dipstick brand and chemistry.
Timing also matters. Urine that sits too long at room temperature can change chemically and cellular elements can degrade. Fresh urine should generally be tested promptly or refrigerated according to laboratory procedures.
If results remain inconsistent, repeating a properly collected specimen or obtaining microscopy and culture is more useful than repeatedly checking home dipsticks.
Urine concentration can create another interpretation trap. A very dilute sample may contain fewer detectable cells or less enzyme per unit volume, while highly concentrated urine can interfere with the strip reaction. For that reason, a result that conflicts sharply with symptoms should be checked against specific gravity, microscopy, and collection quality rather than accepted in isolation. Menstrual blood or vaginal discharge can also complicate the sample; when practical, repeating a clean-catch specimen after those factors have resolved may provide a clearer answer.
How the Test Is Performed and How to Prepare
For routine testing, no fasting is usually required. The most important preparation is collecting a specimen that accurately represents bladder urine rather than skin or genital contamination.
A typical clean-catch midstream collection uses these steps:
- Wash your hands and follow the collection instructions provided by the laboratory or clinic.
- Begin urinating into the toilet.
- Without stopping the stream, move the sterile cup into position and collect the midstream portion.
- Finish urinating into the toilet and close the container without touching the inside of the cup or lid.
- Return the sample promptly so it can be tested under appropriate storage conditions.
Clean-catch technique is particularly important when a UTI or contaminated culture is a concern. A more detailed clean-catch urine collection process may be used when the sample will also be cultured.
Tell the clinician or laboratory about factors that could complicate interpretation, including menstruation, pregnancy, current antibiotics, phenazopyridine or other medicines that alter urine color, high-dose vitamin C supplements, and recent urinary procedures.
For infants, people unable to provide a reliable clean-catch specimen, or situations in which contamination must be minimized, a catheterized specimen may be used. Collection bags can be useful for screening in young children, but a positive leukocyte esterase or nitrite result may need confirmation with a better-controlled specimen before a UTI diagnosis is made.
When Culture and Follow-Up Are Needed
A urine culture is not necessary for every person with a positive leukocyte esterase test. Whether it adds value depends on symptoms, risk factors, and how straightforward the presentation is.
Culture is more likely to be useful when:
- symptoms are severe, unusual, persistent, or recurrent;
- pyelonephritis, or kidney infection, is suspected;
- the person is pregnant;
- the patient is male, immunocompromised, or has important urinary tract abnormalities;
- there is a catheter or recent urinary instrumentation;
- resistant bacteria are a concern;
- symptoms continue despite treatment;
- dipstick findings and symptoms do not agree.
Culture can identify the organism and measure antibiotic susceptibility. It also helps distinguish a true single-organism infection from a contaminated specimen with mixed growth. The urine culture result must still be interpreted with symptoms and collection quality.
What if leukocyte esterase is positive but the culture is negative?
This pattern is sometimes called sterile pyuria when microscopy confirms white blood cells but routine culture does not show typical bacterial growth. Possible explanations include recent antibiotic use, sexually transmitted infections such as chlamydia or gonorrhea, kidney stones, tuberculosis in selected risk settings, inflammatory bladder or kidney conditions, and contamination.
The next step depends on the clinical context. A clinician may repeat the specimen, order nucleic acid amplification testing for sexually transmitted infections, perform imaging when stones or obstruction are suspected, or evaluate for less common inflammatory causes. The key point is that “culture negative” does not automatically mean the leukocyte esterase result was meaningless.
What if leukocyte esterase is negative but symptoms are typical?
A negative result lowers the probability of UTI but does not make it zero. If symptoms are strong, persistent, or accompanied by fever or flank pain, further evaluation may be appropriate. This can include microscopy, culture, or testing for other causes of painful urination such as vaginitis, urethritis, or sexually transmitted infection.
When to Get Medical Care
For mild urinary symptoms in an otherwise healthy adult, a leukocyte esterase result can help guide the next step, but it should not delay care when warning signs are present.
Seek prompt medical assessment for urinary symptoms with:
- fever, shaking chills, or feeling seriously unwell;
- pain in the back or side below the ribs;
- persistent vomiting or inability to keep fluids down;
- pregnancy;
- visible blood in the urine that is heavy, recurrent, or unexplained;
- inability to urinate, severe lower abdominal pain, or suspected obstruction;
- symptoms in a young child, frail older adult, or immunocompromised person;
- worsening symptoms despite treatment.
Emergency care may be needed for signs of sepsis such as confusion, fainting, very rapid breathing, severe weakness, or low blood pressure, particularly when infection is suspected.
If a home urine strip shows leukocyte esterase but you feel well and have no urinary symptoms, avoid assuming you need antibiotics. Home strips can be affected by collection technique, storage, timing, and interpretation. A clinical test and, in selected cases, culture can answer the more important question: whether there is an infection that actually needs treatment.
References
- Office-Based Urinalysis: A Comprehensive Review 2022 (Review)
- Diagnostic value of different urine tests for urinary tract infection: a systematic review and meta-analysis 2022 (Systematic Review)
- Clinical effectiveness of point of care tests for diagnosing urinary tract infection: a systematic review 2024 (Systematic Review)
- Definitions of Urinary Tract Infection in Current Research: A Systematic Review 2023 (Systematic Review)
- Accuracy of leukocyte esterase and nitrite tests for diagnosing bacteriuria in older adults: a systematic review and meta-analysis 2026 (Systematic Review)
Disclaimer
This article is for general educational purposes and does not diagnose or treat a urinary tract infection. Leukocyte esterase should be interpreted with symptoms, collection quality, other urinalysis findings, and culture when appropriate. Seek medical care promptly for fever, flank pain, pregnancy with urinary symptoms, severe illness, or worsening symptoms.