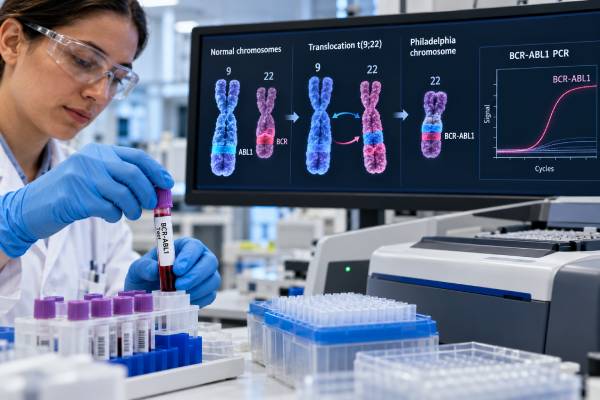
A BCR-ABL1 test looks for the abnormal BCR::ABL1 fusion gene that defines chronic myeloid leukemia (CML) and can also occur in some acute leukemias. The fusion usually forms when genetic material is exchanged between chromosomes 9 and 22, creating the Philadelphia chromosome. In a person with persistent leukocytosis, left-shifted granulocytes, basophilia, splenomegaly, or another pattern suspicious for CML, detecting BCR::ABL1 provides the key molecular evidence needed to establish the diagnosis in the correct clinical setting. Several laboratory methods can detect the abnormality, including chromosome analysis, fluorescence in situ hybridization (FISH), and reverse-transcription PCR. These methods answer related but different questions, so they are often used together at diagnosis. A positive result is highly important, but the laboratory finding still has to be interpreted with the blood counts, marrow findings, disease phase, and other clinical information. Once CML is confirmed, quantitative BCR-ABL1 PCR becomes the main tool for following molecular response over time.
- A positive BCR-ABL1 result supports a diagnosis of BCR::ABL1-positive leukemia; in the typical chronic-phase presentation, it is the defining genetic finding of CML.
- The Philadelphia chromosome is t(9;22)(q34;q11.2); it creates the BCR::ABL1 fusion, but some fusions are cryptic and are not visible on a routine karyotype.
- Karyotyping, FISH, and PCR are complementary: chromosome analysis shows the broader karyotype, FISH detects the rearrangement directly, and PCR identifies the fusion transcript with high sensitivity.
- A negative test does not always end the workup if clinical suspicion is strong, because atypical transcripts, technical limitations, specimen quality, or a different myeloid neoplasm may need to be considered.
- After diagnosis, the exact BCR-ABL1 transcript should be documented so quantitative PCR can be used correctly for treatment-response monitoring.
Table of Contents
- What BCR-ABL1 and the Philadelphia chromosome mean
- When the BCR-ABL1 test is ordered
- How karyotype, FISH, and PCR detect BCR-ABL1
- What a positive BCR-ABL1 result means
- What a negative or discordant result means
- How BCR-ABL1 CML is distinguished from other leukemias
- What happens after CML is diagnosed
What BCR-ABL1 and the Philadelphia chromosome mean
BCR::ABL1 is an acquired genetic fusion, not a change a person is born with in the usual CML setting. It forms when part of the ABL1 gene on chromosome 9 joins part of the BCR gene on chromosome 22. The classic chromosome-level event is written t(9;22)(q34;q11.2). The altered chromosome 22 is called the Philadelphia chromosome, or Ph chromosome.
The fusion produces an abnormal tyrosine kinase that stays active and continuously sends growth and survival signals to blood-forming cells. That signaling gives the abnormal myeloid clone a strong growth advantage. This is why BCR::ABL1 is both a diagnostic marker and the molecular target of tyrosine kinase inhibitor treatment.
In modern classification, CML is a BCR::ABL1-positive myeloproliferative neoplasm. The diagnosis is therefore not simply “high white blood cells plus a Philadelphia chromosome-like picture.” Demonstrating the BCR::ABL1 fusion is central. Most patients have the standard visible t(9;22) on conventional chromosome analysis, but a minority have variant or cryptic rearrangements. In those cases, molecular or FISH testing can find BCR::ABL1 even when a routine karyotype does not show the classic two-chromosome exchange.
The common CML transcripts are e13a2 and e14a2, both of which encode the p210 BCR::ABL1 protein. Less common transcripts can occur, including forms associated with p190 or p230 proteins. Knowing the transcript matters because the same transcript has to be followed reliably after treatment. A laboratory monitoring assay designed only for common p210 transcripts may not accurately measure an unusual fusion.
When the BCR-ABL1 test is ordered
BCR-ABL1 testing is usually ordered when the blood count and differential suggest CML. A typical presentation can include a markedly elevated white blood cell count, neutrophils at several stages of maturation, increased basophils, and sometimes increased eosinophils or platelets. Some people have fatigue, night sweats, weight loss, abdominal fullness from an enlarged spleen, or symptoms related to very high cell counts. Others are diagnosed after an abnormal complete blood count obtained for an unrelated reason.
The test is not a screening test for the general population. Its value is highest when there is a specific hematologic reason to suspect a BCR::ABL1-positive neoplasm. A hematologist may order it while evaluating unexplained persistent leukocytosis, a marrow showing myeloid hyperplasia, or a differential diagnosis that includes CML versus another myeloproliferative neoplasm molecular panel condition.
Peripheral blood is often sufficient for FISH or molecular testing. Bone marrow is commonly obtained at initial diagnosis because it provides morphology, blast percentage, fibrosis assessment, and metaphase chromosome analysis. Those features help establish whether the disease is in chronic phase or has evidence of progression and can identify additional chromosomal abnormalities that a BCR-ABL1-only assay cannot show.
No special diet or fasting is generally needed. The more important preanalytic issues are obtaining an adequate specimen, transporting it properly, and making sure the requested laboratory method is appropriate for the diagnostic question. If testing is being performed after therapy has already started, that timing should be communicated because treatment can rapidly lower the number of BCR::ABL1-positive cells.
Testing may also be ordered in acute leukemia. BCR::ABL1 can be found in B-cell acute lymphoblastic leukemia and, less commonly, in other acute leukemia presentations. Therefore, the presence of the fusion must be integrated with morphology, immunophenotyping, clinical history, and disease kinetics rather than interpreted as “CML” automatically.
How karyotype, FISH, and PCR detect BCR-ABL1
The three major approaches are conventional cytogenetics, FISH, and PCR-based molecular testing. They overlap, but they are not interchangeable.
| Method | What it detects | Main strength | Main limitation |
|---|---|---|---|
| Chromosome analysis (karyotype) | Philadelphia chromosome and other visible chromosome changes | Shows the broader chromosome picture and additional abnormalities | Needs dividing cells and may miss cryptic BCR::ABL1 rearrangements |
| FISH | BCR and ABL1 rearrangement/fusion in individual cells | Fast, sensitive for the targeted rearrangement, and does not require metaphases | Targeted test; does not provide a complete karyotype |
| RT-PCR | BCR::ABL1 RNA fusion transcript | Highly sensitive and identifies the transcript used for later monitoring | An assay that does not cover an atypical transcript can miss it |
Conventional chromosome analysis is especially useful at diagnosis. Bone marrow is generally preferred because it reliably supplies dividing myeloid cells. A laboratory typically evaluates at least 20 metaphases when possible. Besides confirming the classic t(9;22), karyotyping can reveal additional chromosome abnormalities that may have prognostic significance or signal disease evolution.
FISH uses fluorescent probes targeted to the BCR and ABL1 regions. It can detect the fusion in interphase cells, so the cells do not need to be actively dividing. This makes FISH useful when metaphase quality is poor or when a cryptic rearrangement is suspected. Many assays report the percentage of cells with a fusion signal pattern and provide a laboratory-specific cutoff. That percentage is not the same thing as the standardized molecular BCR-ABL1 percentage used for long-term CML response monitoring.
Reverse-transcription PCR detects BCR::ABL1 messenger RNA. At diagnosis, qualitative or multiplex PCR can establish which fusion transcript is present. Quantitative real-time PCR then becomes the preferred serial monitoring method. The BCR-ABL1 quantitative PCR test expresses common measurable transcripts on the International Scale, allowing standardized response milestones over time.
Because each method has a different blind spot, expert laboratory recommendations support combining cytogenetic evaluation with FISH and/or RT-PCR at diagnosis. The goal is not to perform redundant tests without reason; it is to establish the fusion confidently, document the transcript, and record baseline chromosome information that may matter later.
What a positive BCR-ABL1 result means
A positive result means laboratory evidence of a BCR::ABL1 fusion has been found. In a patient with the characteristic chronic myeloid clinical and marrow picture, this confirms the defining genetic abnormality of CML. The laboratory report may use terms such as “BCR::ABL1 detected,” “BCR-ABL1 fusion positive,” “t(9;22) present,” or “Philadelphia chromosome positive,” depending on the method.
The exact format matters. A karyotype may report t(9;22)(q34;q11.2). A FISH report may state that a percentage of nuclei show a BCR/ABL1 fusion pattern. A PCR report may identify e13a2, e14a2, or another transcript. These are related findings, but the numerical values should not be compared as though they are the same measurement.
A positive result does not by itself determine CML phase. Chronic phase, advanced disease, and blast-phase disease are assessed using blood and marrow blast percentages, clinical findings, and additional features. Likewise, a positive test does not supply a complete prognosis. Age, spleen size, blood counts, additional chromosome or molecular abnormalities, disease phase, and early molecular response all contribute to risk assessment.
BCR::ABL1 positivity is also clinically actionable because it identifies the constitutively active kinase targeted by CML tyrosine kinase inhibitors. The test therefore connects diagnosis directly to a biologically matched treatment strategy. However, drug selection is individualized and can depend on coexisting conditions, disease risk, mutation findings later in the course, treatment goals, pregnancy considerations, and toxicity profiles.
If the fusion is detected unexpectedly in an acute leukemia workup, clinicians must determine whether the patient has de novo BCR::ABL1-positive acute lymphoblastic leukemia, CML presenting in blast phase, or another unusual scenario. This distinction requires much more than the fusion result alone.
What a negative or discordant result means
A negative BCR-ABL1 result means the assay did not detect the targeted abnormality in the submitted specimen. If the clinical picture is not strongly suggestive of CML, that result may appropriately direct the evaluation toward other causes of leukocytosis or another myeloid neoplasm. But a single negative result should be interpreted in light of the method used and the strength of the clinical suspicion.
For example, a normal karyotype does not exclude CML if BCR::ABL1 is cryptic. Approximately a small minority of patients have a fusion not apparent as a standard t(9;22) on routine cytogenetics. FISH or RT-PCR can resolve that situation. Conversely, a limited PCR screen may be negative if the patient has an atypical BCR::ABL1 transcript that the primer design does not detect. Expert laboratory guidance therefore emphasizes assays capable of recognizing typical and atypical fusion patterns when testing a new suspected case.
Specimen quality can also matter. Low RNA quality, inadequate cell numbers, technical inhibition, or a sample collected after substantial treatment may reduce detection. Laboratories usually include internal controls to identify many technical failures, but clinicians should still review whether the test performed actually answered the intended question.
Discordance between methods is not automatically an error. FISH may be positive while karyotyping appears normal because the fusion is cryptic. PCR may identify a transcript even when only a small number of abnormal cells are present. A chromosome study may identify a complex or variant translocation that requires targeted FISH or molecular confirmation. These patterns are resolved by comparing the actual laboratory reports, not by treating “positive” and “negative” as interchangeable labels across methods.
If BCR::ABL1 remains absent after appropriate testing, classic CML is not diagnosed. The workup may then focus on other myeloid neoplasms and reactive causes, using blood smear review, marrow morphology, molecular testing, and clinical context as appropriate.
How BCR-ABL1 CML is distinguished from other leukemias
BCR::ABL1 is strongly associated with CML, but it is not exclusive to CML. B-cell acute lymphoblastic leukemia can also carry BCR::ABL1. Therefore, the correct question is not merely “Is BCR-ABL1 positive?” but “What disease is producing this BCR::ABL1-positive clone?”
CML in chronic phase usually has a broad spectrum of maturing granulocytes in blood and marrow, basophilia, and often splenomegaly. BCR::ABL1-positive B-ALL instead presents as an acute lymphoid leukemia with a predominance of lymphoblasts and a B-cell precursor immunophenotype. Leukemia flow cytometry helps establish lineage and characterize a blast population, while morphology and cytogenetic/molecular data complete the classification.
The distinction becomes more difficult when CML first presents in blast phase and the blasts have a lymphoid phenotype. In that setting, clinicians look for evidence of an underlying CML-type myeloid clone, prior blood count history, splenomegaly, basophilia, marrow features, transcript patterns, and additional genetic findings. No single one of these features is perfect, so integrated interpretation is essential.
There is also an important distinction between BCR::ABL1-positive CML and other chronic myeloid disorders that can resemble it morphologically. If BCR::ABL1 is convincingly absent, classification shifts toward other entities rather than a “Philadelphia-negative CML” diagnosis. This is one reason precise molecular testing has replaced older terminology based mostly on appearance.
A very low-level BCR::ABL1 signal found outside a compatible leukemia evaluation should not be interpreted in isolation. Assay sensitivity, potential technical issues, and the clinical setting matter. Diagnosis requires evidence that the molecular finding belongs to the pathologic clone causing the patient’s hematologic disease.
What happens after CML is diagnosed
Once CML is confirmed, the diagnostic workup establishes a baseline that will be used for years of follow-up. The care team documents the BCR::ABL1 transcript type, blood counts, spleen findings, marrow blast percentage, and chromosome results. Risk scores may incorporate age and hematologic features. Additional chromosome abnormalities, when present, can influence how the disease is viewed and followed.
Treatment with a BCR::ABL1 tyrosine kinase inhibitor usually begins promptly. From that point, quantitative PCR becomes the central laboratory measure of response. For common transcripts, results are reported as BCR::ABL1 on the International Scale. Important landmarks include 10% at about 3 months, 1% at about 6 months, and 0.1% at about 12 months, although clinicians interpret results in context and consider the trend rather than reacting to a single value in isolation. A level of 0.1% or lower is called major molecular response.
Molecular testing is usually performed about every three months early in therapy until a stable major molecular response is achieved and confirmed. In a stable patient it can then be spaced out, often to every four to six months. More frequent testing may be appropriate if the level is rising, adherence is uncertain, treatment has changed, or an attempt at treatment-free remission is underway.
A rising BCR::ABL1 level does not automatically mean treatment has failed. The team first considers adherence, dose interruptions, drug interactions, laboratory variability, and whether the rise is confirmed. If resistance or loss of response is suspected, mutation testing of the BCR::ABL1 kinase domain may help identify changes that affect sensitivity to particular inhibitors. Bone marrow and cytogenetic reassessment may also be needed if progression is suspected.
The diagnostic test and the monitoring test therefore serve different roles. Initial testing proves that the leukemia carries BCR::ABL1 and establishes the molecular identity of the disease. Serial quantitative testing asks how much measurable disease remains after treatment. Keeping those roles separate helps prevent common misunderstandings, such as interpreting a diagnostic FISH percentage as an International Scale PCR result or assuming that a detectable transcript after treatment means the therapy is not working.
For patients, the most useful questions to ask about a BCR-ABL1 report are straightforward: Which method was used? What transcript was found? Does the overall picture meet criteria for CML? Was a baseline karyotype performed? And, after treatment begins, is the molecular level falling at the expected pace? Those answers turn a complex genetic report into a practical roadmap for diagnosis and follow-up.
References
– 2025 European LeukemiaNet recommendations for the management of chronic myeloid leukemia 2025 – European LeukemiaNet laboratory recommendations for the diagnosis and management of chronic myeloid leukemia 2023 – Chronic myeloid leukemia: 2025 update on diagnosis, therapy, and monitoring 2024 – Cytogenetics and genomics in CML and other myeloproliferative neoplasms 2024 – The 5th edition of the World Health Organization Classification of Haematolymphoid Tumours: Myeloid and Histiocytic/Dendritic Neoplasms 2022
Disclaimer
This article is for general education and is not a substitute for diagnosis or treatment by a hematologist or other qualified clinician. BCR-ABL1 results must be interpreted with the testing method, blood and bone marrow findings, clinical presentation, and treatment history. Do not start, stop, or change leukemia treatment based on a laboratory result without discussing it with the treating team.